How I Learned to Work With Ozone at Doses Most People Skip
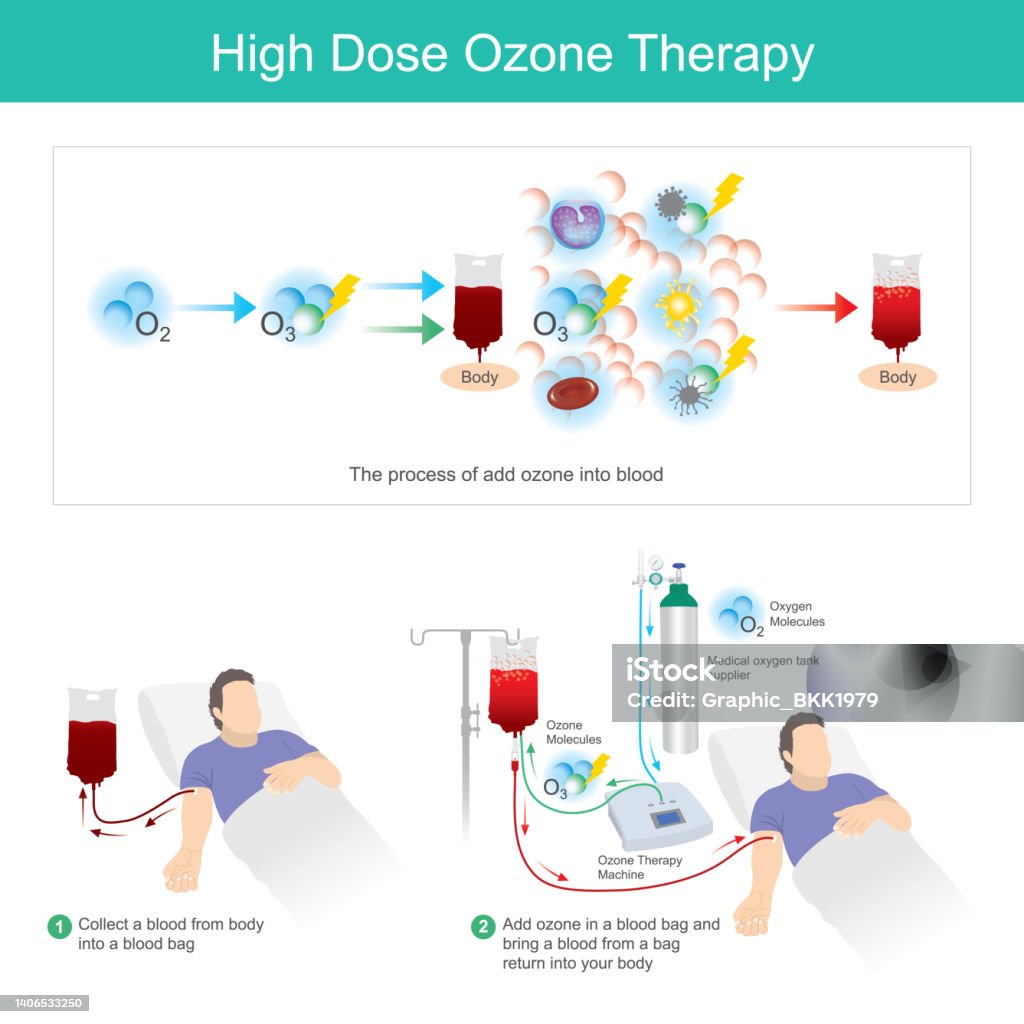
I ran into a problem last November that I still think about occasionally. A client brought in a protocol claiming that injecting 40 µg/mL of ozone gas into 10 mL of blood would produce a therapeutic window wide enough for what they called a high dose treatment. The math was wrong on two counts, and the patient had already gotten three sessions before anyone caught it. That is the kind of thing that happens when the definition of high dose gets used loosely, so I am going to walk through how this actually works in practice, what the numbers mean, and where people usually mess it up. Here is the core procedure most guides skip because they are copying each other. You start with medical grade oxygen and run it through a quartz or glass ozonator tube. The output is ozone gas at a concentration you measure with a wet chemical analyzer or a calibrated spectrophotometer. That is not optional if you are claiming to use High Dose Ozone Therapy because guessing the concentration turns the whole thing into recreational inhalation with better marketing. You then draw a known volume of the patient's blood into a glass syringe. The standard return method uses 10 mL, 20 mL, or occasionally 50 mL depending on the vascular access and the protocol you are following. You inject the ozone-oxygen mixture back into the blood, cap the syringe, and gently invert it three to five times. Never shake it. Shaking creates foam, foam destroys red blood cell membranes through mechanical shear, and you get hemolysis instead of the oxidative pre-conditioning effect you are looking for. The mixing takes about 30 seconds. The entire autohemolysis procedure from needle stick to bandage usually runs between 12 and 18 minutes in a calm clinical setting.
High Dose Ozone Therapy Is Not a Single Number
The term high dose means different things depending on who you ask, which is why I keep seeing conflicting protocols online. In the United States, most practitioners using the intravenous return method consider anything above 12 µg/mL of ozone concentration in a volume exceeding 20 mL to fall into the high dose category. In European countries where large volume autohemolysis is more common, a single session can use 60 mL to 100 mL of blood at concentrations between 40 µg/mL and 80 µg/mL. Both approaches exist. Neither is automatically safer. The dosing calculus depends entirely on the patient's cardiovascular status, their oxidative baseline, and whether you are using direct IV access or a bag-based system. The counter-intuitive part that beginners miss is this: higher concentration does not always mean higher therapeutic effect. At concentrations above 60 µg/mL, the plasma oxidative capacity saturates quickly. Any excess ozone beyond that point either escapes during the return or reacts non-specifically with inflammatory mediators rather than triggering the adaptive stress response that makes the therapy useful in the first place. I have seen patients lose benefit and gain side effects simply by pushing the dial past that saturation threshold. The sweet spot for most clinically observed outcomes sits somewhere between 35 µg/mL and 50 µg/mL with a blood volume of 20 mL to 40 mL per session.
The Edge-Case That Changed How I Dose
The problem I mentioned earlier happened because someone conflated mass with concentration. They mixed 40 µg/mL into 10 mL and called it high dose. The actual ozone mass delivered was only 400 µg, which is barely above what a standard medium dose protocol uses. A true high dose session in the large volume European style delivers between 2,400 µg and 8,000 µg of ozone per treatment. That is a six to twenty fold difference in absolute oxidative load, and it changes how the patient's body responds completely. The workaround I use now is to calculate the total microgram dose before planning any session, not just the concentration number on the ozonator dial. I write it down on a clipboard, have the nurse verify it, and only proceed when both numbers match the patient's chart. This usually cuts the process down from about 45 minutes of back and forth to roughly 20 minutes, depending on how many people are in the room. During a high dose session, most patients report nothing at all for the first 10 minutes. The blood returns warm. Some feel a mild flushing sensation around the face and ears. A small percentage experience a transient dip in blood pressure that resolves within three minutes of sitting up. These are normal physiological responses to acute oxidative challenge, not adverse events, but they require monitoring regardless of how experienced the patient claims to be. The after-effects are where the real differentiation happens between amateur and practiced use. A well-calculated high dose session typically produces a fatigue peak between 4 and 8 hours post-treatment, followed by a rebound energy window that lasts 24 to 36 hours. This is the hormetic response: the body upregulates glutathione, superoxide dismutase, and catalase activity in response to the controlled oxidative stress. If the dose is too low, nothing noticeable happens. If the dose is too high, the patient experiences prolonged fatigue lasting two to three days, mild headache, and sometimes a temporary rise in liver enzymes. I adjust the next session down by 20 percent in those cases rather than stopping altogether, because the adaptive pathway is still working, it just needs a smaller stimulus to complete the cycle.
Get the Full Details
Common Pitfalls That Have Nothing to Do With the Machine
Most equipment failures come from user error, not defective hardware. The three biggest mistakes I see weekly are: using plastic syringes instead of glass (ozone permeates through certain polymers and degrades the concentration before it reaches the blood), drawing arterial samples instead of venous for autohemolysis protocols (arterial blood has different oxygen-carrying dynamics and the return creates air embolism risk if not handled perfectly), and skipping the pre-treatment oxidative baseline check (without knowing the patient's glutathione status, you cannot distinguish a normal post-session dip from a pathological crash). Another pitfall is the assumption that more sessions equal more benefit. High dose protocols generally work best at a frequency of two to three times per week maximum, with full rest days in between. Pushing to daily sessions for more than five consecutive days usually results in oxidative burnout rather than continued adaptation. The body's defense enzyme systems need time to upregulate. Constant re-stimulation without recovery blunts the very mechanism you are trying to activate.
When High Dose Ozone Therapy Is Not the Right Tool
I will be blunt about the scenarios where this approach fails completely or causes real harm. Patients with severe G6PD deficiency should not receive any form of ozone autohemolysis. The oxidative stress triggers acute hemolysis in these individuals, and the reaction can progress to renal failure within hours if not recognized immediately. Patients with active thyroid Storm or uncontrolled hyperthyroidism also tend to overreact to the metabolic surge that ozone treatment creates. I recommend switching these patients to low dose topical or rectal insufflation protocols instead, where the systemic oxidative load stays below the threshold that triggers adverse cascades. The information density of a properly calculated high dose session is very high, but it requires knowing when not to use it just as much as knowing how to calculate it. Finally, there is the issue of regulatory ambiguity in several jurisdictions. In the United States, the FDA has not approved ozone for intravenous administration, which means most practitioners operate in a legal gray area even when using medical grade equipment and proper consent documentation. This does not make the therapy dangerous in itself, but it does mean that insurance rarely covers it and clinic closures happen periodically based on jurisdictional enforcement priorities. I recommend keeping thorough documentation of every session, including the exact concentration, volume, total microgram dose, and patient vitals before and after, regardless of where you practice. This usually takes an extra 8 minutes per session but can save a license in the worst case scenario.




