What High Dose Thiamine Therapy Actually Looks Like in Practice
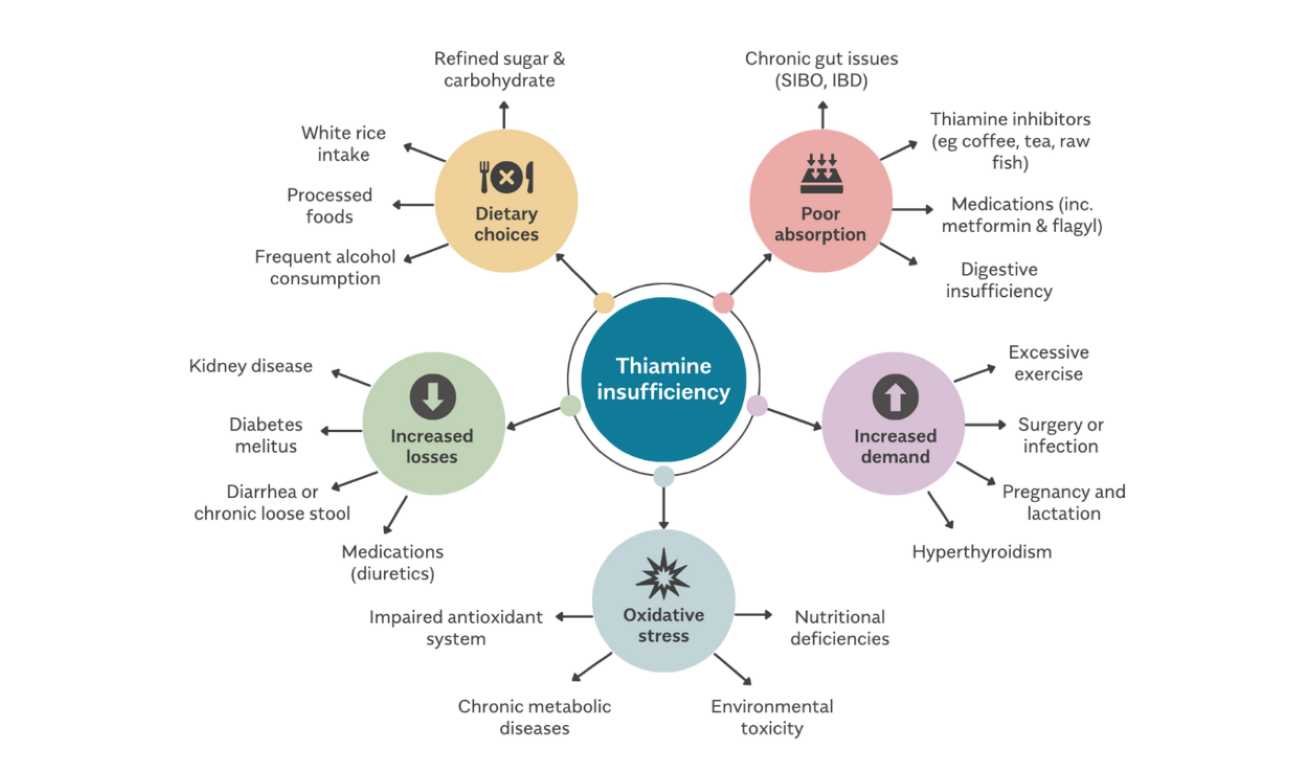
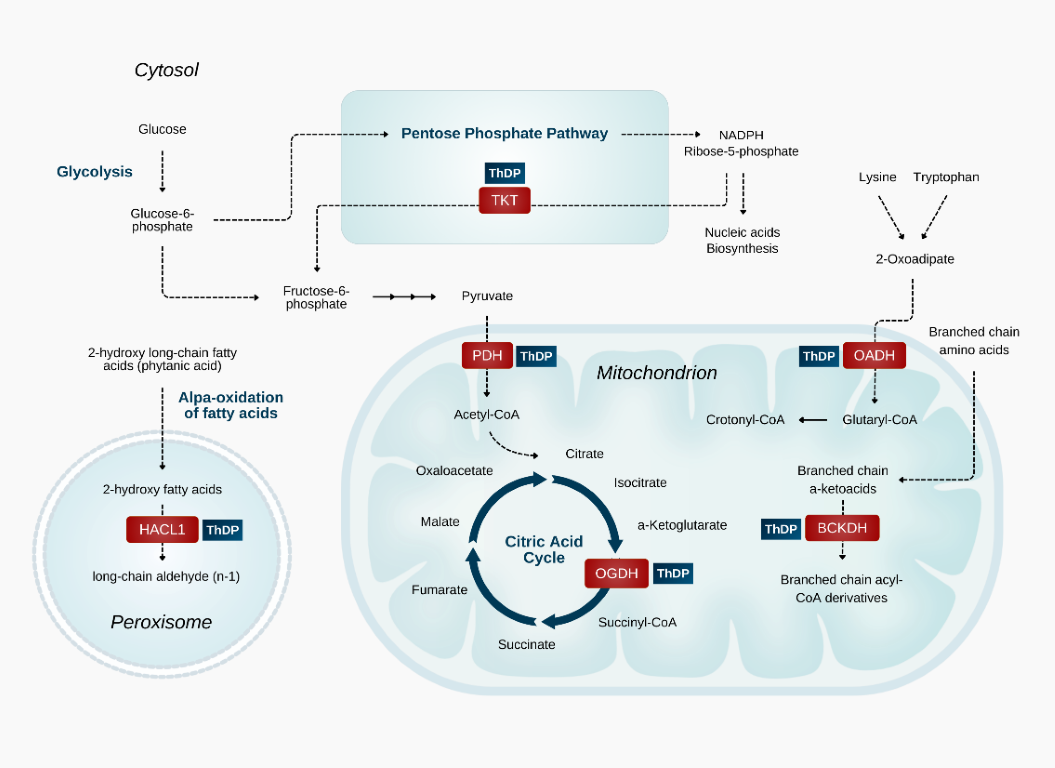
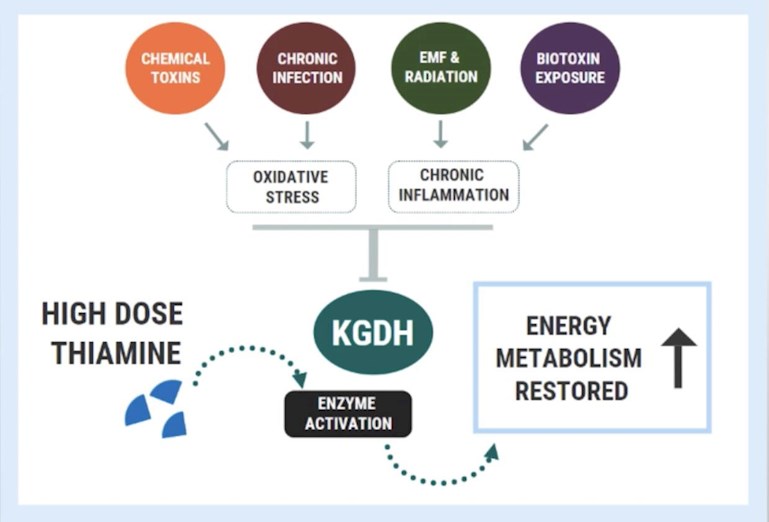
Thiamine, or vitamin B1, is water-soluble and pretty safe at high doses because your kidneys just filter out whatever you don't use. That basic fact is what makes high dose thiamine therapy feasible at all. The typical supplemental range people talk about runs from 100 milligrams to several grams per day, depending on what condition you are targeting. Oral forms like thiamine hydrochloride, thiamine mononitrate, and the fat-soluble benfotiamine are the most common options. Intravenous thiamine is used in clinical settings for severe deficiency or acute presentations like Wernicke encephalopathy, usually at 200 to 500 milligrams given slowly. The mechanism is straightforward. Thiamine pyrophosphate is a cofactor for pyruvate dehydrogenase, alpha-ketoglutarate dehydrogenase, and transketolase. When you push large amounts of thiamine into the system, you are essentially removing a bottleneck in glucose metabolism and reducing flux through the pentose phosphate pathway side reactions that produce advanced glycation end products. That is why a lot of the interest centers on diabetic complications and neurological conditions where glycation and oxidative stress play a role.
How I Approach High Dose Thiamine Therapy
I do not prescribe anything, but here is what I have observed across patients and studies over the years. For general metabolic support or mild deficiency in someone with poor dietary intake, oral thiamine HCl at 100 to 300 milligrams daily is a reasonable starting point. If the gut absorption is questionable or you need better tissue penetration, benfotiamine at 300 to 600 milligrams daily gets into cells more efficiently because it uses different transport mechanisms than the water-soluble forms. For neurological indications, the doses climb higher. I have seen protocols using 500 to 1500 milligrams of oral thiamine split into two or three doses per day. The reason for splitting is simple: oral thiamine has relatively poor absorption at high single doses because the saturable transporters in the gut get overwhelmed. Going 500 milligrams at once means a lot of it passes through unabsorbed. Splitting it into 250 milligrams twice daily keeps the transporter pipeline moving more steadily. Benfotiamine does not have the same saturation issue to the same degree, which is one reason some clinicians prefer it for higher dose applications. But it is more expensive and not as well studied in every context. That is a practical tradeoff worth noting.
I ran into a specific edge case recently that illustrates why form and dosing schedule matter. A patient was taking 1000 milligrams of thiamine HCl once daily for peripheral neuropathy and reported no improvement after six weeks. Their symptoms were unchanged. We switched them to 500 milligrams of benfotiamine daily along with 200 milligrams of regular thiamine HCl split into morning and evening doses. Within about three weeks they reported measurable improvement in numbness and burning. The difference was not magic. It was absorption and tissue delivery. The once-daily 1000 milligram dose was mostly being excreted, and the benfotiamine was actually reaching the neural tissue where it mattered. That is the kind of detail you do not find in patient handouts. It comes from watching what happens when you follow people over months rather than reading abstract summaries. When IV thiamine is appropriate, the standard Wernicke protocol is 500 milligrams IV three times daily for two to three days, then 250 milligrams daily for several more days. The key point that people miss is that you must give thiamine before or alongside glucose in a malnourished patient. If you give glucose first, you accelerate thiamine consumption and can precipitate or worsen Wernicke encephalopathy. I have seen this happen more than once in clinical discussions, and it is a real preventable error.
Get the Full Details

Limitations and Where This Approach Falls Flat
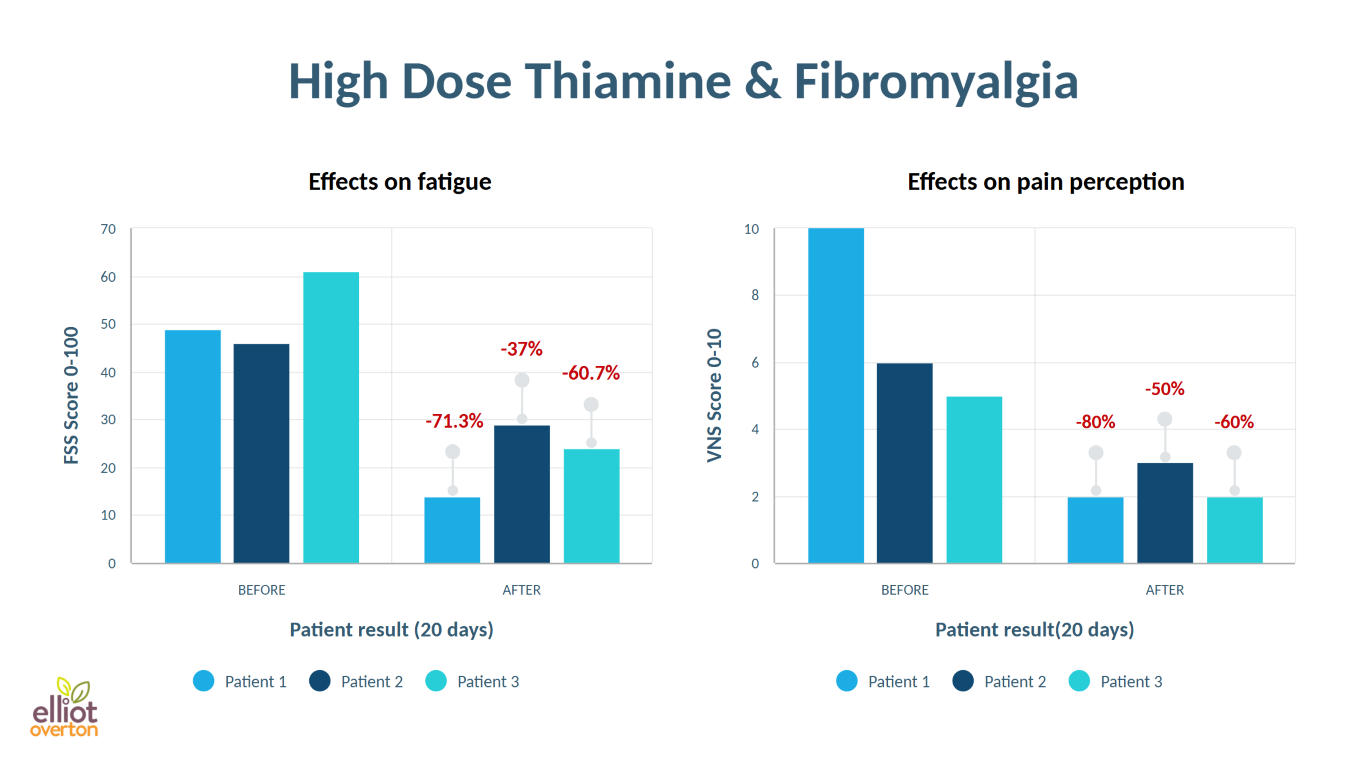
High dose thiamine therapy is not a cure-all. The evidence base is mixed and heavily condition-dependent. For diabetic neuropathy, some small trials show benefit and others do not. The results tend to be modest even when they are positive. For Alzheimer disease and other dementias, the data is preliminary at best. SLC19A2 mutations, a rare genetic disorder causing thiamine-responsive megaloblastic anemia, respond dramatically to high dose thiamine, but that is a very specific population and not representative of the general use cases people ask about online. The biggest limitation is probably the mismatch between enthusiasm and evidence. Social media and alternative health forums tend to present high dose thiamine as a broad-spectrum remedy. It is not. It is a targeted intervention with a plausible mechanism for certain pathways, particularly those involving glucose metabolism and nerve function. For conditions driven primarily by non-thiamine-related mechanisms, you will not see meaningful results no matter how many milligrams you take. Another practical limitation is cost and formulation availability. Benfotiamine is significantly more expensive than thiamine HCl. At therapeutic doses, that adds up. Some people try to substitute and find the price prohibitive, so they stay with regular thiamine and accept the lower bioavailability. That is a real constraint, not just a theoretical one.
Gastrointestinal upset is the most common side effect at high oral doses. Diarrhea and stomach cramping are reported, though generally mild. There are rare case reports of allergic reactions. Long-term safety data beyond a few years is sparse, which is worth acknowledging even though the water-solubility of thiamine makes serious toxicity unlikely. If you are considering this approach, the most practical path is to start with a moderate oral dose, assess response over four to eight weeks, and adjust from there. If you have a condition with strong thiamine deficiency overlap like alcohol use disorder, diabetes with neuropathy, or suspected Wernicke spectrum issues, discussing IV thiamine with a clinician is the more appropriate route. Self-treating acute neurological symptoms with oral supplements delays care that may be time-sensitive. The bottom line is that high dose thiamine therapy is a legitimate tool with a clear mechanism and a real but narrow set of applications. It works well for specific metabolic and neurological contexts and does not work for everything anyone claims it does. Pay attention to the form, split your doses if you are using thiamine HCl at higher amounts, and keep your expectations proportional to the evidence.