So you got an HFA diagnosis or suspect your kid has it, and now you are scrolling at 2am for actual useful info
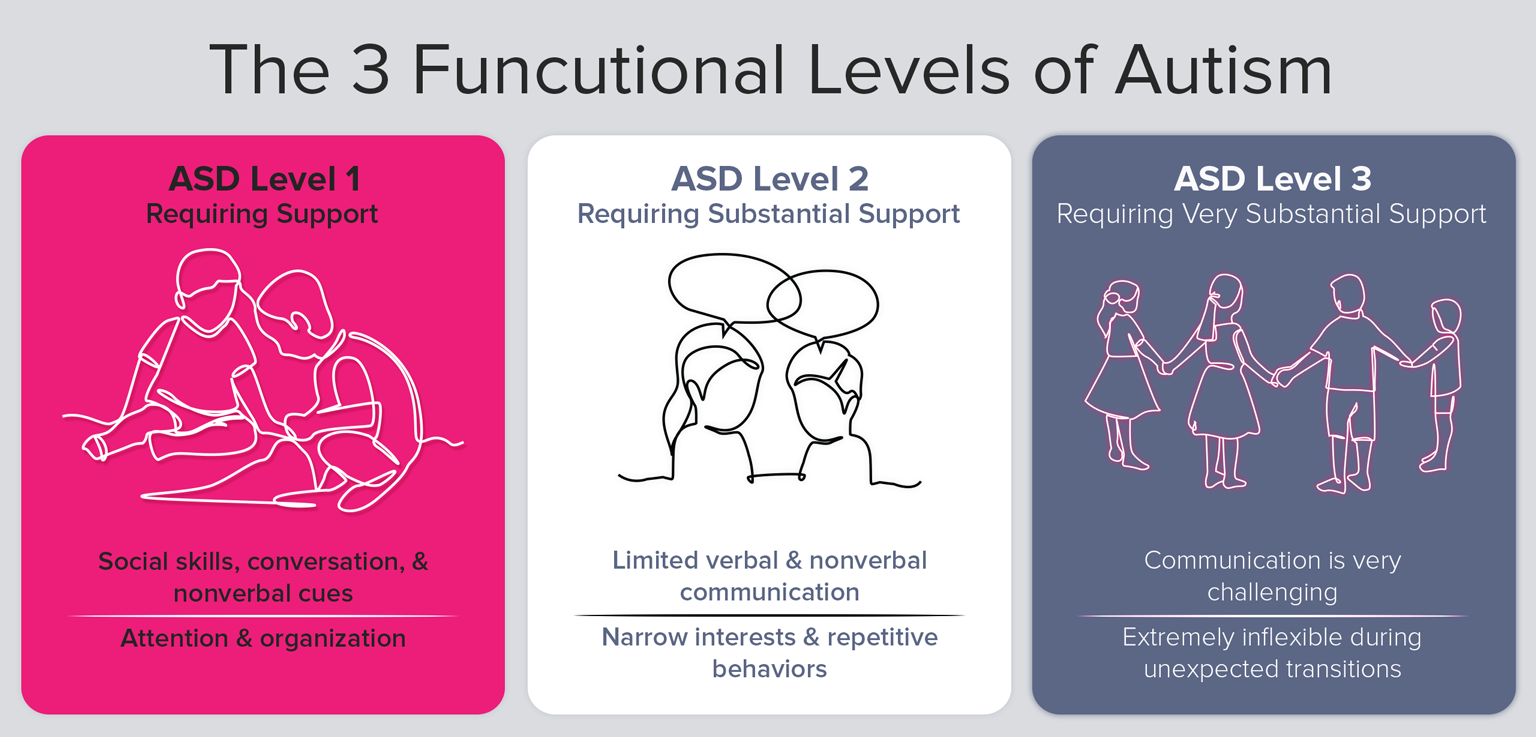
I have spent roughly eight years doing this work, and the thing nobody tells you is that High Functioning Autism Spectrum Disorder is not a checklist you tick off and file away. It is a pattern of wiring that shows up differently depending on the environment, the person's age, whether they have learned to mask, and how stressed their nervous system is on any given Tuesday. I am going to try to give you something more useful than the DSM-5 summary most people paste into group chats. The term itself is outdated clinically. You will still see it in older records, private assessments, and online communities, so expect the label. In modern diagnostic language, this would be Autism Spectrum Disorder Level 1, meaning the person requires support but does not have an accompanying intellectual or language impairment. That "Level 1" part matters a lot because it predicts things like employment outcomes and burnout risk, not just social quirks. The core features are roughly these:
Social communication differences that are not about being shy. This includes trouble reading implicit social rules, missing sarcasm until it is explained literally, and having conversations feel like solving a puzzle where half the pieces are invisible. Many people with HFA learn scripts and practice them until they sound normal, which is why some present as extremely polished in professional settings and then completely shut down at home where they feel safe enough to drop the performance. Restricted and repetitive patterns. This can look like intense, narrow interests that dominate free time, a need for routines that, when disrupted, cause genuine physiological distress, stimming behaviors like hand-flapping or rocking, and sensory sensitivities that range from mildly annoying to physically painful. The sensory piece is where most parents and partners get blindsided. A fluorescent light buzzing at 60hz might seem like nothing to everyone else but it can trigger headaches, irritability, or shutdowns in someone with auditory processing differences. What nobody puts in the pamphlet is that symptoms fluctuate wildly based on executive function load. Someone who navigates a workday fine on a low-demand week can lose basic language skills during a high-stress period. This is called autistic burnout and it is real, it is exhausting, and it is often misdiagnosed as depression or anxiety, which sometimes it co-occurs with but is not the same thing.
Assessment and Getting a Real Diagnosis
If you are pursuing an evaluation, the gold standard tools are the ADOS-2 and the ADI-R, though many clinicians rely heavily on clinical interview and developmental history. For adults, the RAADS-R and the AQ are screening questionnaires, not diagnostic instruments. They are useful as a starting point but have high false-positive rates, especially in neurotypical people who are introverted or just socially awkward. Find a clinician who actually works with adults on the spectrum. A lot of psychologists are trained to recognize autism in young boys with language delays. They will miss it in a woman who camouflages by mirroring other people's behavior, or a man who has learned to fake eye contact by counting seconds. I once had a client who failed every screening tool because she had spent twenty years learning to perform normalcy. She only qualified when we looked at her childhood records and found consistent patterns of social confusion, rigidity around routines, and sensory complaints that her parents had dismissed as being dramatic. Bring documentation if you can. Report cards with comments like "talks only about trains," old IEPs, parent recollections. The diagnostician will ask about early development, and yes, even if you had a typical first birthday, you could still be on the spectrum. Many HFA individuals develop language on time or even early, which is exactly why the diagnosis gets missed.
Get the Full Details

What Actually Helps After Diagnosis
This is where the advice gets messy because there is no universal protocol. What works depends entirely on the individual's profile. I will tell you what tends to help, what does not, and where people commonly waste time and money. Therapy that works: CBT adapted for autism, not standard CBT. Regular talk therapy assumes a certain baseline of emotional identification and social reasoning that autistic people often lack. The adapted version explicitly teaches emotion recognition, social navigation strategies, and cognitive restructuring around autistic-specific thought patterns. I recommend looking for a therapist who lists autism as a specialty, not just someone who adds it to their bio because it is trendy. Occupational therapy for sensory integration can be genuinely life-changing for people with significant sensory processing differences. The right OT will do a thorough sensory profile first and then build a custom plan. Beware of OTs who just throw weighted blankets and fidget toys at every case without assessment. That is not treatment, that is merchandising.
Medication: There is no medication for autism itself. What exists are medications for co-occurring conditions. SSRIs for anxiety and depression, stimulants or non-stimulants for ADHD (which co-occurs in roughly 50-70% of cases), and sometimes antipsychotics like risperidone for severe irritability or aggression. The key point is that treating the comorbidities often improves functioning more than anyone expects, which is why comprehensive evaluation matters before jumping to any single intervention. Accommodations: These are the unglamorous, high-impact tools. Noise-canceling headphones in open offices. Flexible deadlines for people with executive dysfunction. Written instructions instead of verbal ones. Permission to stim. Reduced lighting. Many of these cost the employer or institution almost nothing and dramatically improve quality of life and output. The Americans with Disabilities Act and similar laws in other countries cover autism, but people rarely use them because they do not know they can. Documentation from a diagnosing professional is usually all that is needed. Things that do not work or are actively harmful: ABA therapy, particularly the traditional compliance-based model, has a deeply problematic track record. It was designed to make autistic children appear neurotypical, which often means teaching them to suppress natural coping mechanisms like stimming. Many autistic adults report that ABA caused lasting psychological harm. There are newer, play-based, child-led approaches that are more ethical, but the field is still grappling with its history. Read the literature and listen to autistic voices before committing. Social skills groups can help some people learn explicit social rules, but they can also reinforce the idea that being autistic is a defect to be cured. Frame them carefully.
I want to mention a specific edge case I ran into recently. A client came to me after being told her social anxiety was the primary issue. She had been on SSRIs for three years with minimal improvement. When we looked deeper, her "anxiety" was actually chronic sensory overload from an environment that was never designed for her nervous system. She worked in a open-plan office with overhead fluorescent lighting, constant side conversations, and an expectation of spontaneous collaboration. The SSRI was doing nothing because the problem was environmental, not chemical. We recommended remote work, noise-canceling headphones, and a quiet workspace. Her anxiety dropped by an estimated 60-70% within six weeks. Medication was tapered under her psychiatrist's supervision. This is the kind of misdiagnosis that happens constantly because clinicians are trained to look inside the person rather than at the person-environment fit.

The Masking Problem and Long-Term Outlook
Masking, also called camouflaging, is when an autistic person consciously or unconsciously suppresses autistic traits to fit in. It involves forcing eye contact, rehearsing conversations beforehand, mimicking others' body language, and suppressing stims. Short-term, masking helps you get through situations. Long-term, it is associated with anxiety, depression, identity loss, and autistic burnout. Some people mask so effectively that they do not realize they are autistic until a major life stressor forces them to stop performing. The prognosis for High Functioning Autism Spectrum Disorder is generally good for independent living and employment. Most people with HFA live independently, hold jobs, and form relationships. The challenges are real but manageable with the right supports. The biggest predictor of negative outcomes is not the autism itself, it is the presence of untreated co-occurring conditions, chronic stress from masking, and lack of accommodation. Address those and the trajectory improves significantly. One counter-intuitive thing most people miss: high intelligence or strong verbal skills do not protect against burnout. In fact, they can make it worse because these people are often expected to perform at a level that their nervous system cannot sustain without consequences. The smartest autistic people I know are often the ones who crash the hardest because nobody suspected they were struggling.
If you are reading this and you think you or someone you care about might be on the spectrum, the next practical step is a proper evaluation with a qualified professional. Not a quiz. Not a Reddit thread. An actual assessment. And if you already have a diagnosis, focus on accommodations and treating co-occurring conditions before chasing interventions that promise to "cure" autism. There is no cure, and trying to erase the person's neurology usually causes more damage than the autism itself.