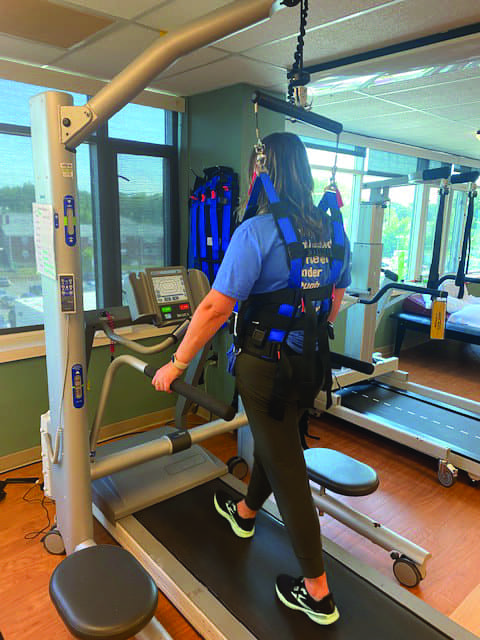
The treadmill isn't going to save you
I keep seeing people come into my clinic after trying everything else for their gait issues, and more often than not they're already burned out on generic treadmill protocols. High Intensity Gait Training isn't some miracle cure, but when it's done right it actually moves the needle on walking speed and endurance in ways that slow, casual walking simply doesn't. It sounds like a mouthful, but here's the basic setup. You strap someone into a body-weight support system on a treadmill, set the speed high, and drive them through repetition after repetition. The intensity matters more than the duration. Most protocols call for speeds between 60 and 80 percent of each person's predicted maximum walking velocity, with work intervals ranging from two to five minutes followed by short rest periods. A typical session involves anywhere from 15 to 40 minutes of actual treadmill time spread across multiple sets.
What High Intensity Gait Training Actually Looks Like in Practice
I ran into a patient last year who'd been doing standard physical therapy for six months after a stroke with zero measurable improvement in his walking speed. He could manage maybe eight minutes on the treadmill before fatigue took over, and his cadence was around 75 steps per minute. We switched him to High Intensity Gait Training at 70 percent of his predicted max velocity, which worked out to roughly 1.4 meters per second. The first week was rough. He was breathing hard, his arms were pumping, and he looked like he was about to crash after the first set. By week three, he was completing three sets of three minutes each at that speed without sitting down. His walking speed went from 0.65 meters per second to 1.02 meters per second over eight weeks. That's not a small change. That's the difference between needing a cane indoors and walking around the grocery store without thinking about it. The counter-intuitive part that everyone misses is that body weight support shouldn't be your default starting point. I've watched too many clinicians throw 30 or 40 percent of body weight off a patient right out of the gate. The whole point of this approach is neuromuscular adaptation under load. If you remove too much weight, you're just doing fast walking with extra equipment attached. My usual protocol starts patients at 10 to 20 percent support and only increases it if they can't maintain the target speed for the full work interval. Most people find they need less support than they expect once they get used to the pace. Another thing that gets glossed over in the literature is the importance of arm swing and trunk posture at high speeds. When you're driving a treadmill that fast, patients tend to grab the handrails like their life depends on it and hunch forward. That completely changes the biomechanics and defeats the purpose. I cue patients to keep their hands on the rails only for light balance support, not for weight bearing. If they're hanging off the rails, the speed is too high or the body weight support is too low. Drop the speed by 0.1 meters per second and rebuild from there. It's faster in the long run than pushing through bad mechanics.
There's also the issue of progression. A lot of protocols I see online just say increase speed over time, which is basically useless advice. The specific progression I use starts at 60 percent of predicted max velocity for the first two weeks, then adds 5 percent every one to two weeks depending on tolerance. Predicted maximum walking velocity is calculated differently depending on which reference you use, but a common formula is body weight in kilograms divided by 11, giving you meters per second. For a 70 kilogram person that comes out to about 6.4 kilometers per hour or roughly 1.78 meters per second as a predicted max. Starting at 60 percent means you're driving them at around 1.07 meters per second to begin with. It feels easy going. It isn't. The biggest limitation of this approach is that it doesn't work for everyone. If a patient has significant cardiovascular disease, uncontrolled hypertension, or a history of falls that hasn't been addressed, high speed treadmill work can be dangerous. I've seen it happen. A patient with mild cardiac issues pushed through dizziness because they didn't want to fall behind the group, and we ended up aborting the session early. Baseline screening is non-negotiable. Check resting heart rate, blood pressure, and ask about chest pain or excessive shortness of breath with minimal exertion before you even think about setting the treadmill to anything above a casual walk. Another problem is that high intensity gait training creates fatigue fast, and fatigue leads to compensation. I've had patients who'd start strong in set one and by set three they'd be dragging their foot on the swing phase because their hip flexors were shot. The workaround is to put rest intervals between sets that are actually long enough. 30 seconds of rest is a joke. I use two to three minutes of rest between sets, and sometimes I split a single session into two shorter blocks if the patient is showing signs of form breakdown. Quality of movement at speed matters more than the total number of steps completed.
Get the Full Details

For patients with Parkinson's disease, the protocol looks slightly different. The stride lengthI usually aim for the higher end of the speed range, around 75 to 80 percent of predicted maximum, because the main issue is freezing and short shuffling steps. The fast walking drives a longer step length through the force field mechanism, which is a well documented phenomenon in Parkinson's rehabilitation. But again, body weight support gets dialed back as soon as possible. These patients don't need the machine holding them up as much as they need the sensory cue of speed to override their basal ganglia timing issues. Equipment wise, you need a motorized treadmill that can sustain speeds above 2.0 meters per second without stalling or jerking. Cheap home treadmills that top out at 3.5 miles per hour and have a wobbly deck are not suitable. Body weight support systems range from expensive ceiling-mounted tracks to simpler harness-and-pulley rigs. The harness type matters less than getting the fit right. A harness that sits too high on the pelvis can restrict hip extension at high speeds. I always adjust it so the support strap sits at the iliac crest, not above it, and the patient should feel the support coming from their lower torso, not their chest or shoulders. I don't have a download link or a proprietary protocol sheet to give you. What I can tell you is that the major rehab textbooks and journal articles from the past decade all describe the same basic framework, and the specific parameters vary slightly between them. Look up the work of authors like Perella, Wolf, or Eng for the original studies. The core parameters are consistent enough that you don't need a special system to implement this. You need a decent treadmill, a body weight support harness, a way to measure walking speed, and the discipline to actually push the pace instead of coasting.
If you're a patient reading this and your therapist is having you stroll along at 2 miles per hour for 20 minutes, that's not High Intensity Gait Training. That's just walking. Ask them about the speed targets and the set structure. If they can't tell you what percentage of predicted maximum velocity you're working at, they probably aren't doing it correctly either.