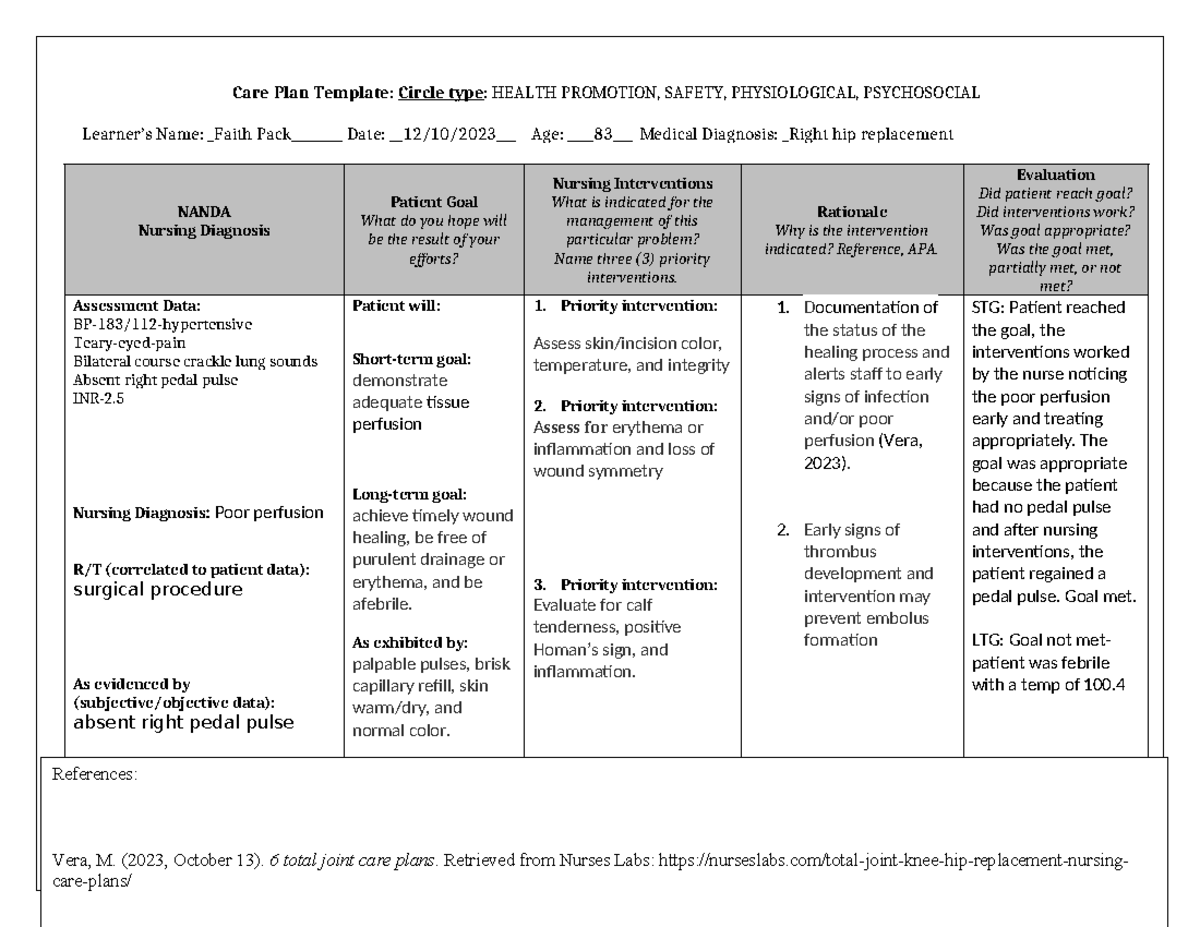
Setting up a hip replacement nursing care plan without making it a paperwork exercise
A hip replacement nursing care plan is really just a structured way of tracking what matters most in the first forty-eight hours after surgery. Most nurses already do this intuitively. The problem is writing it down in a format that actually helps the team instead of creating busywork. I started mapping these out when I was a new grad nurse and spent way too much time copying the same assessments over and over for every single patient. What changed things for me was organizing the plan around actual clinical decision points rather than just filling out the hospital's pre-printed forms. The form isn't the plan. The plan is knowing what to do when the numbers on the form start looking wrong.
Key sections of a Hip Replacement Nursing Care Plan
You need to cover pain management, mobility precautions, wound monitoring, DVT prophylaxis, and discharge education. That list sounds standard until you actually sit down to write it out and realize how many of those categories overlap in practice. Pain management on a hip replacement isn't just about giving opioids on schedule. The real work starts when you're tracking breakthrough pain that doesn't match the expected timeline. I had a patient last year whose pain scores were flat at 3 out of 10 for two days straight, and then they spiked to 8 in the evening without any obvious trigger. Turns out they were constipated from the opioid regimen and hadn't had a bowel movement in four days. His abdominal distension was masquerading as surgical pain. Once we addressed the constipation with a bowel protocol, his pain dropped back to baseline without changing the analgesic order at all. That's the thing nobody tells you during orientation: pain after hip replacement is rarely just about the incision. It's about positioning, bowel function, urine retention, and sometimes the nerve block wearing off at the wrong time. Your care plan should reflect that complexity instead of treating pain as a standalone nursing diagnosis.
Pain Management Document your baseline pain score before any intervention so you can measure change. Track medication timing relative to physical therapy sessions. Pre-medication thirty to forty-five minutes before PT makes a noticeable difference in how much a patient can actually participate in their mobility goals. Write that into the plan. Most nurses skip that detail and then wonder why the patient isn't progressing. Mobility and Precautions
Get the Full Details
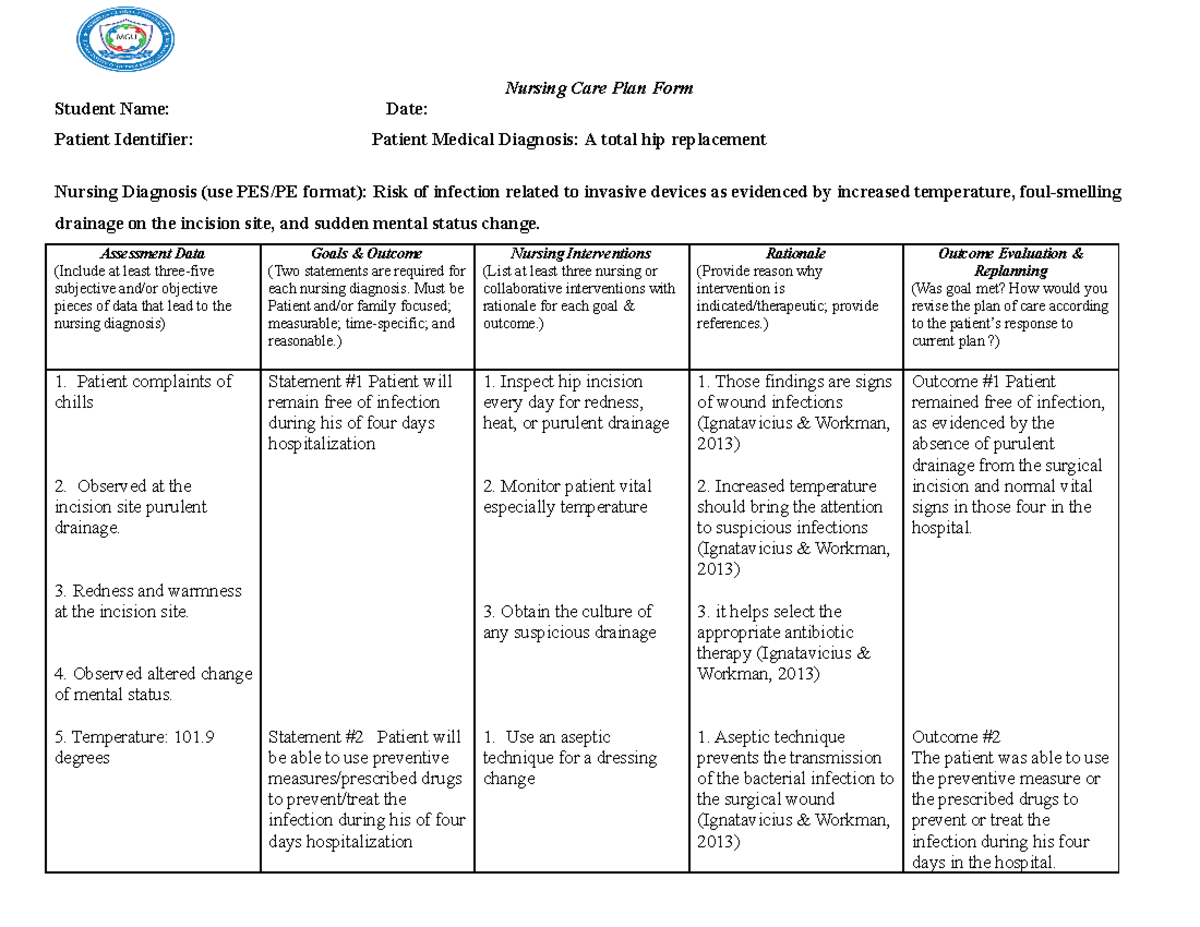
Whether the approach was anterior or posterior determines what precautions you document. Posterior approach means no hip flexion past ninety degrees, no internal rotation, and no adduction across the midline. Anterior approach has different restrictions but the care plan still needs to specify exactly what the patient can and cannot do. Vague language like "follow hip precautions" is useless. Write out the specific limitations. I've seen care plans that just said "bed rest until cleared" for post-op day one. That's not a plan. That's a placeholder. The plan should state exactly when mobilization is expected to begin, what the initial goal is, and what assistive device will be used. Most patients are out of bed the same day or the next morning. Writing that expectation into the care plan changes how the whole team approaches the patient. Wound and Incision Monitoring
Document the dressing status at each shift change. Note drainage amount, color, and odor. A small amount of serosanguinous drainage is normal. Bright red bleeding that soaks through a dressing within an hour is not. Write down exactly when you changed the dressing and what you found. Future nurses need that timeline to spot trends. DVT Prophylaxis Hip replacement carries one of the highest risks for post-operative deep vein thrombosis among common surgical procedures. The care plan needs to specify which pharmacological prophylaxis is ordered, when the next dose is due, and whether mechanical compression devices are being used. If the patient has a contraindication to anticoagulants, note that and document the alternative plan. I worked with a patient who developed a hematoma after his first dose of enoxaparin. The plan didn't have a contingency documented, so there was a delay while the team decided what to do next. If you had written that contingency in advance, the response would have been immediate.
Discharge Planning This starts on admission, not on discharge day. Document the patient's support system at home, their living situation, and any barriers to independence. A patient who lives alone in a second-floor walk-up with no elevator access is going to need a different plan than someone with family nearby and a ground-floor bedroom. Write that down early so OT and PT can adjust their recommendations accordingly. The discharge teaching section should cover specifically what you'll educate the patient on: medication schedules, wound care instructions, signs of infection to report, DVT warning signs, and follow-up appointment timing. Don't just check a box that says "discharge teaching provided." Note what was covered and what the patient demonstrated back to you. Teaching comprehension matters more than the act of teaching itself.
Where this approach breaks down
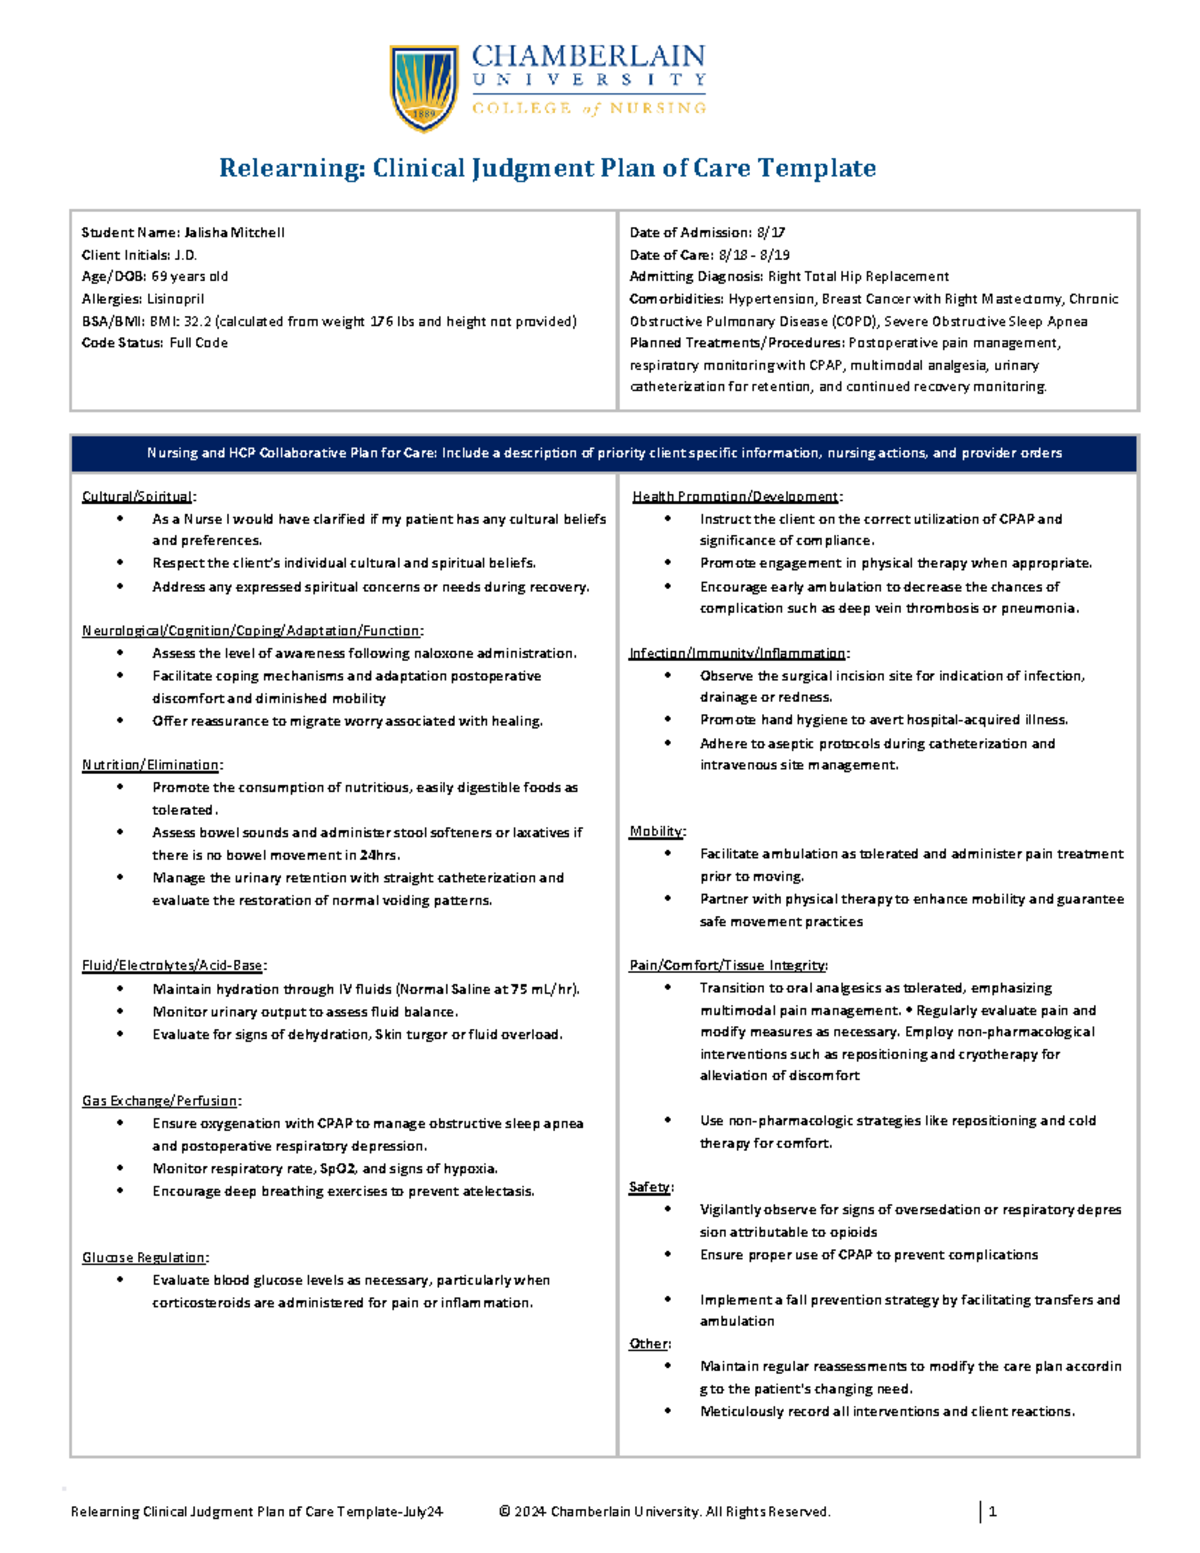
A structured care plan doesn't help if the rest of the team isn't using it. I've seen care plans that were beautifully detailed but sat untouched in the chart while the floor team followed whatever workflow they'd been doing for years. The plan became irrelevant because nobody referenced it after the initial shift handoff. Another limitation is that care plans based on standard protocols can miss individual variation. A textbook hip replacement recovery assumes a certain trajectory. Real patients don't always follow the textbook. Some patients have uncontrolled diabetes that slows wound healing. Others have cognitive impairment that makes compliance with hip precautions nearly impossible. The care plan needs room to adapt to those realities or it becomes a false sense of security. The biggest practical problem I run into is time. Writing a thorough care plan that actually reflects the patient's individual situation takes longer than most nurses have during a busy shift. The workaround I use is keeping a personal template with the standard sections already laid out, then customizing each one for the individual patient during the first assessment. That cuts the documentation time down to about ten to fifteen minutes per patient instead of the twenty to thirty it would take from scratch every time.
If you're looking for a starting point, many hospital systems have their own built-in templates in the electronic health record. Those tend to be generic but functional. For something more detailed that you can adapt, I've found that pulling from evidence-based post-operative protocols from organizations like the American Association of Hip and Knee Surgeons gives you a solid foundation to build from. The key is making it yours instead of just copying a template and calling it done. What matters most is consistency. A mediocre care plan that gets updated and referenced daily is worth more than a perfect one that gets written and forgotten. Track your interventions. Note when something doesn't go as expected. Adjust the plan. That's the part that actually improves patient outcomes.


