The Actual Workflow
Most people approach documentation from the wrong angle. They start by looking for software that claims HIPAA compliance, then figure out their clinical process around that tool. This creates friction because the software was never designed for the way therapy actually happens in practice. The better approach is to map your note-writing process first, then select a platform that fits. I spent three years trying to force a general EMR system to handle specialty therapy documentation before I realized the problem wasn't the software, it was the mismatch between how I structured sessions and how the system expected data to flow. A standard SOAP note template doesn't capture the nuance of process-oriented modalities like EMDR or somatic experiencing. I started using narrative progress notes with embedded structured fields instead. It took about two weeks to adjust, then it became faster than SOAP every time.
Choosing the Right Platform for Hipaa Compliant Therapy Notes
HIPAA compliance isn't a feature you toggle on. It's a set of technical safeguards that any proper platform must maintain at the infrastructure level. This means encrypted data at rest, encrypted transmission, automated access logging, business associate agreements with the vendor, and the ability to terminate access immediately. If a vendor can't provide their latest SOC 2 Type II report or ATTEST checklist, walk away. There are plenty of alternatives. For solo practitioners and small groups, platforms like TherapyNotes, SimplePractice, and Theranica handle most of the compliance burden internally. The tradeoff is that you're locked into their template structures unless you pay for custom fields. I've seen therapists spend forty-five minutes per note fighting a platform's dropdown menus instead of writing actual clinical content. That adds up to roughly six hours a week wasted on interface navigation rather than documentation. If you have specific workflow needs, consider a platform-agnostic approach. Use an encrypted note-taking app like Standard Notes with a HIPAA BAA, pair it with a separate encrypted file storage system for audio recordings and PDFs, and maintain your own access logs in a spreadsheet. This gives you total flexibility but requires you to manage the compliance piece yourself. I ran this setup for eighteen months before switching to a dedicated platform because the administrative overhead became unsustainable during audit season.
What Actually Goes Into a Compliant Note
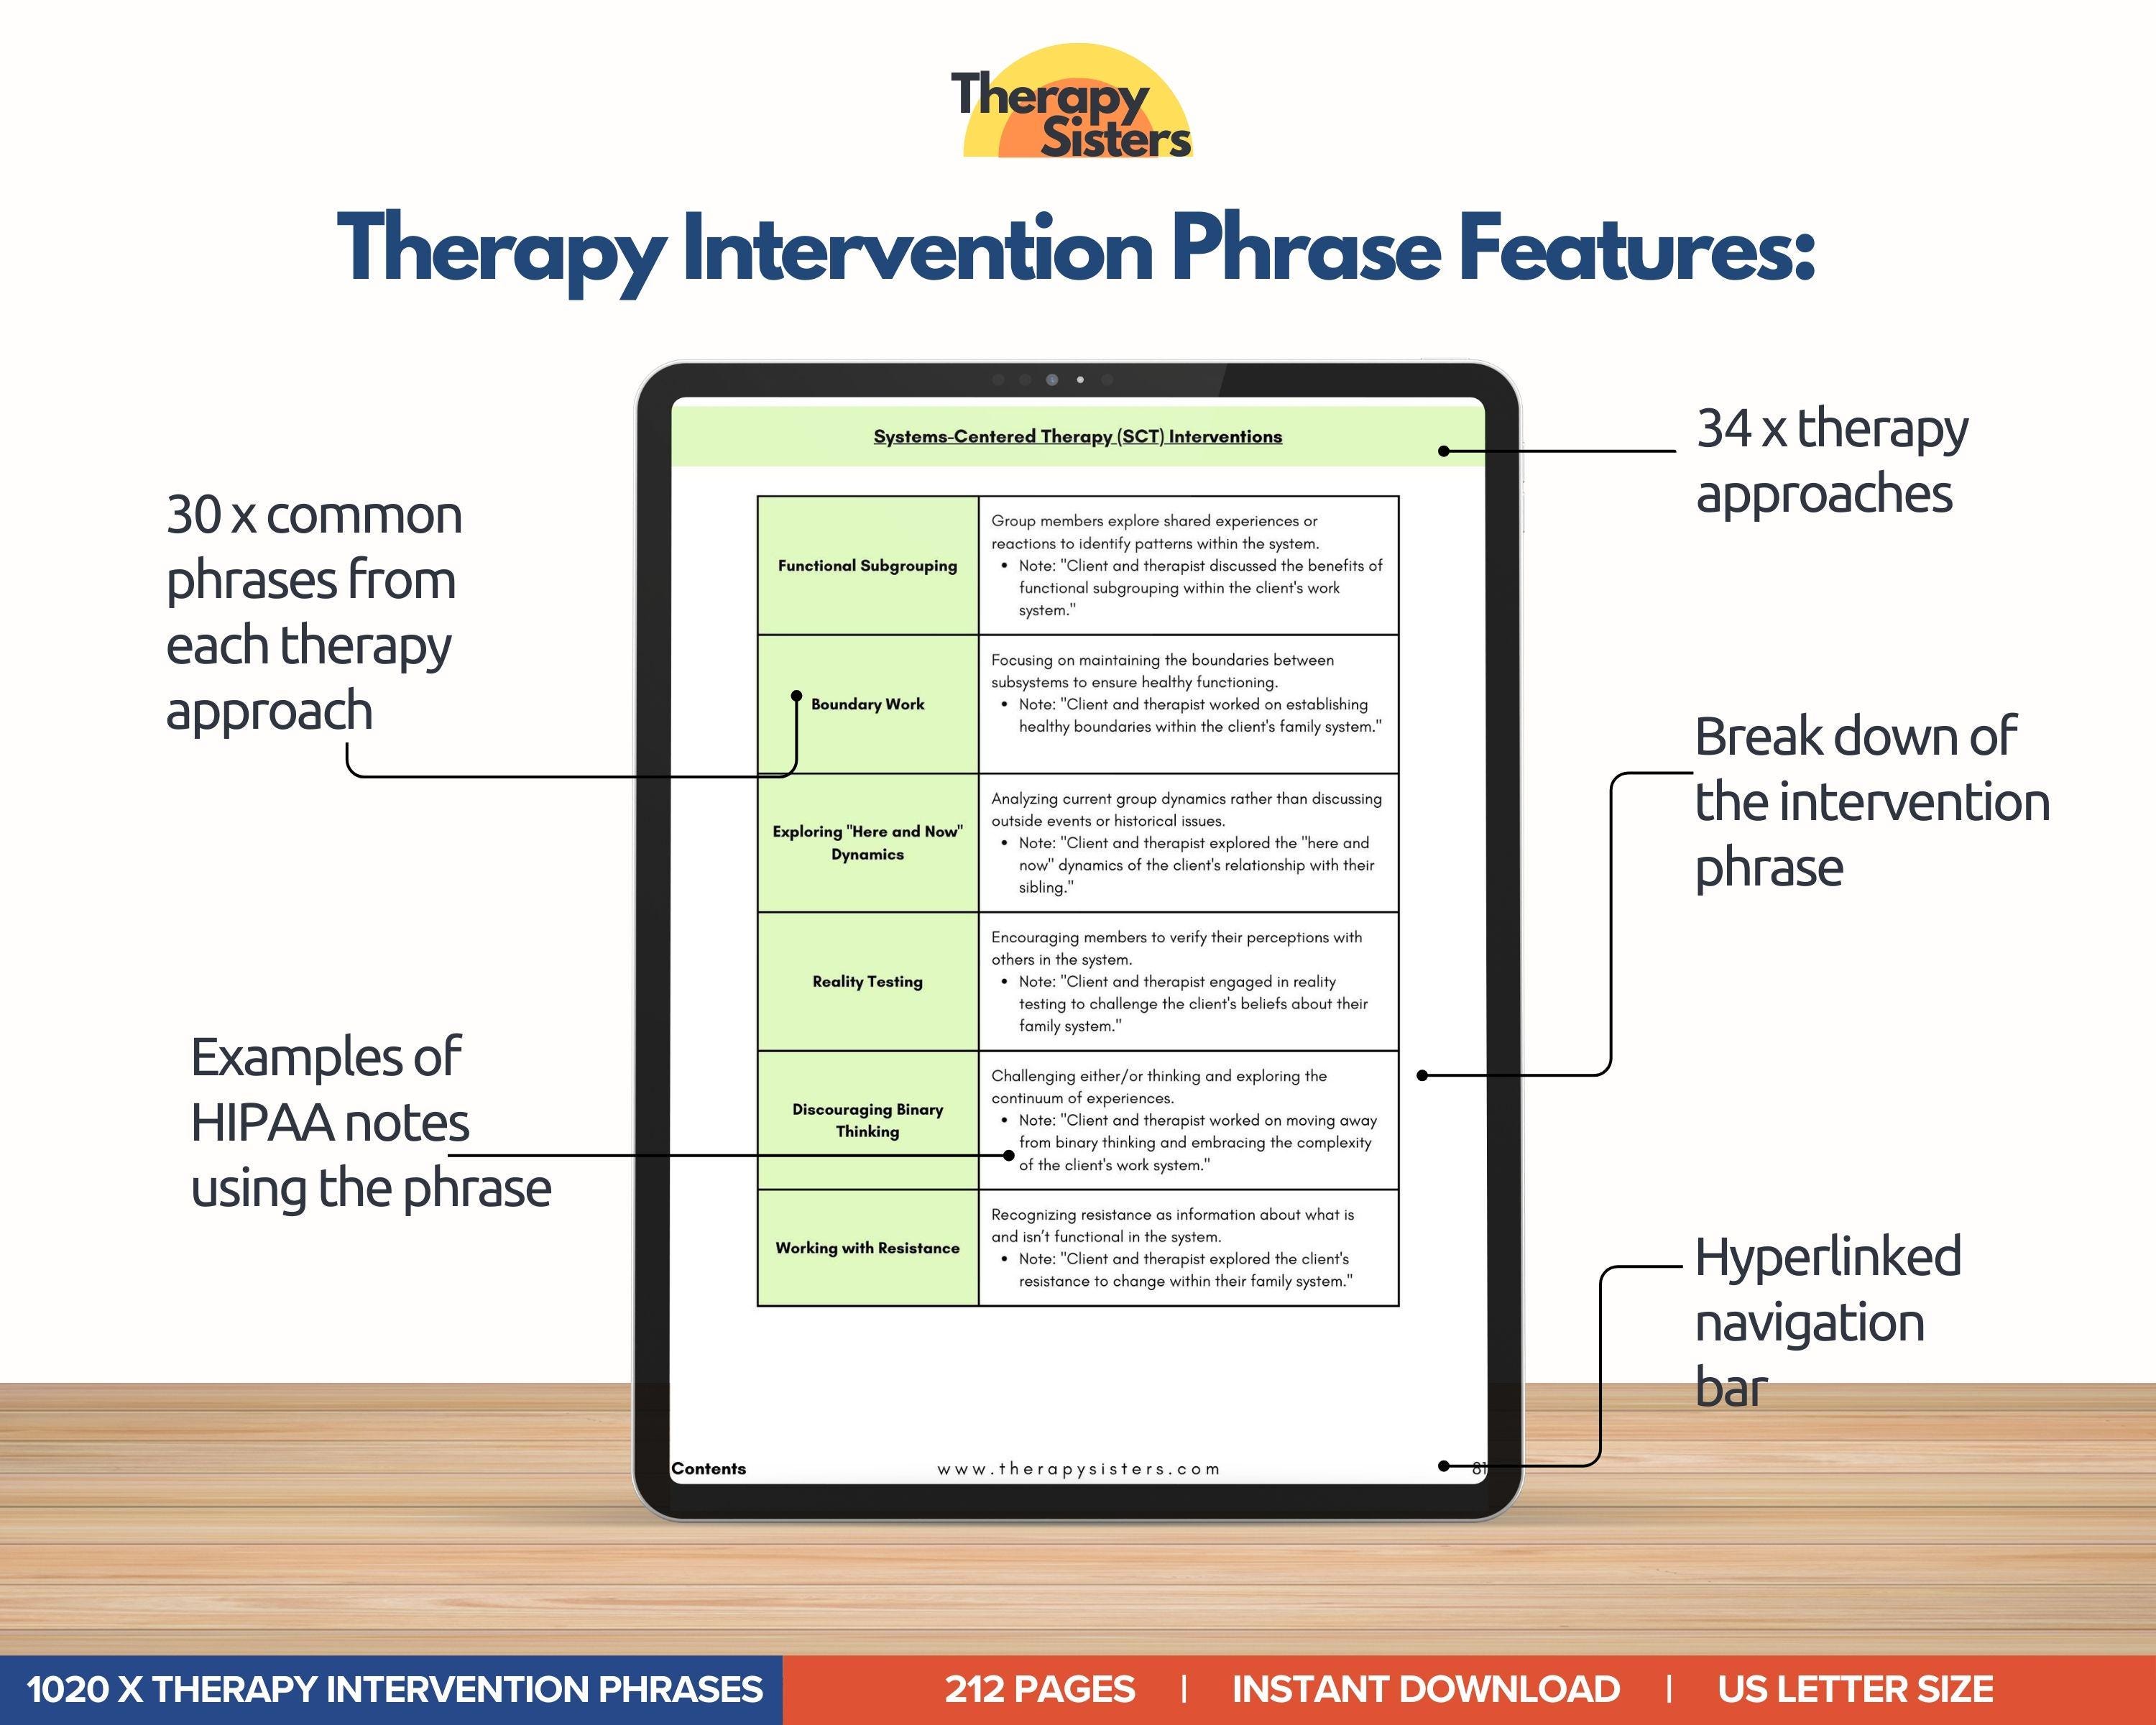
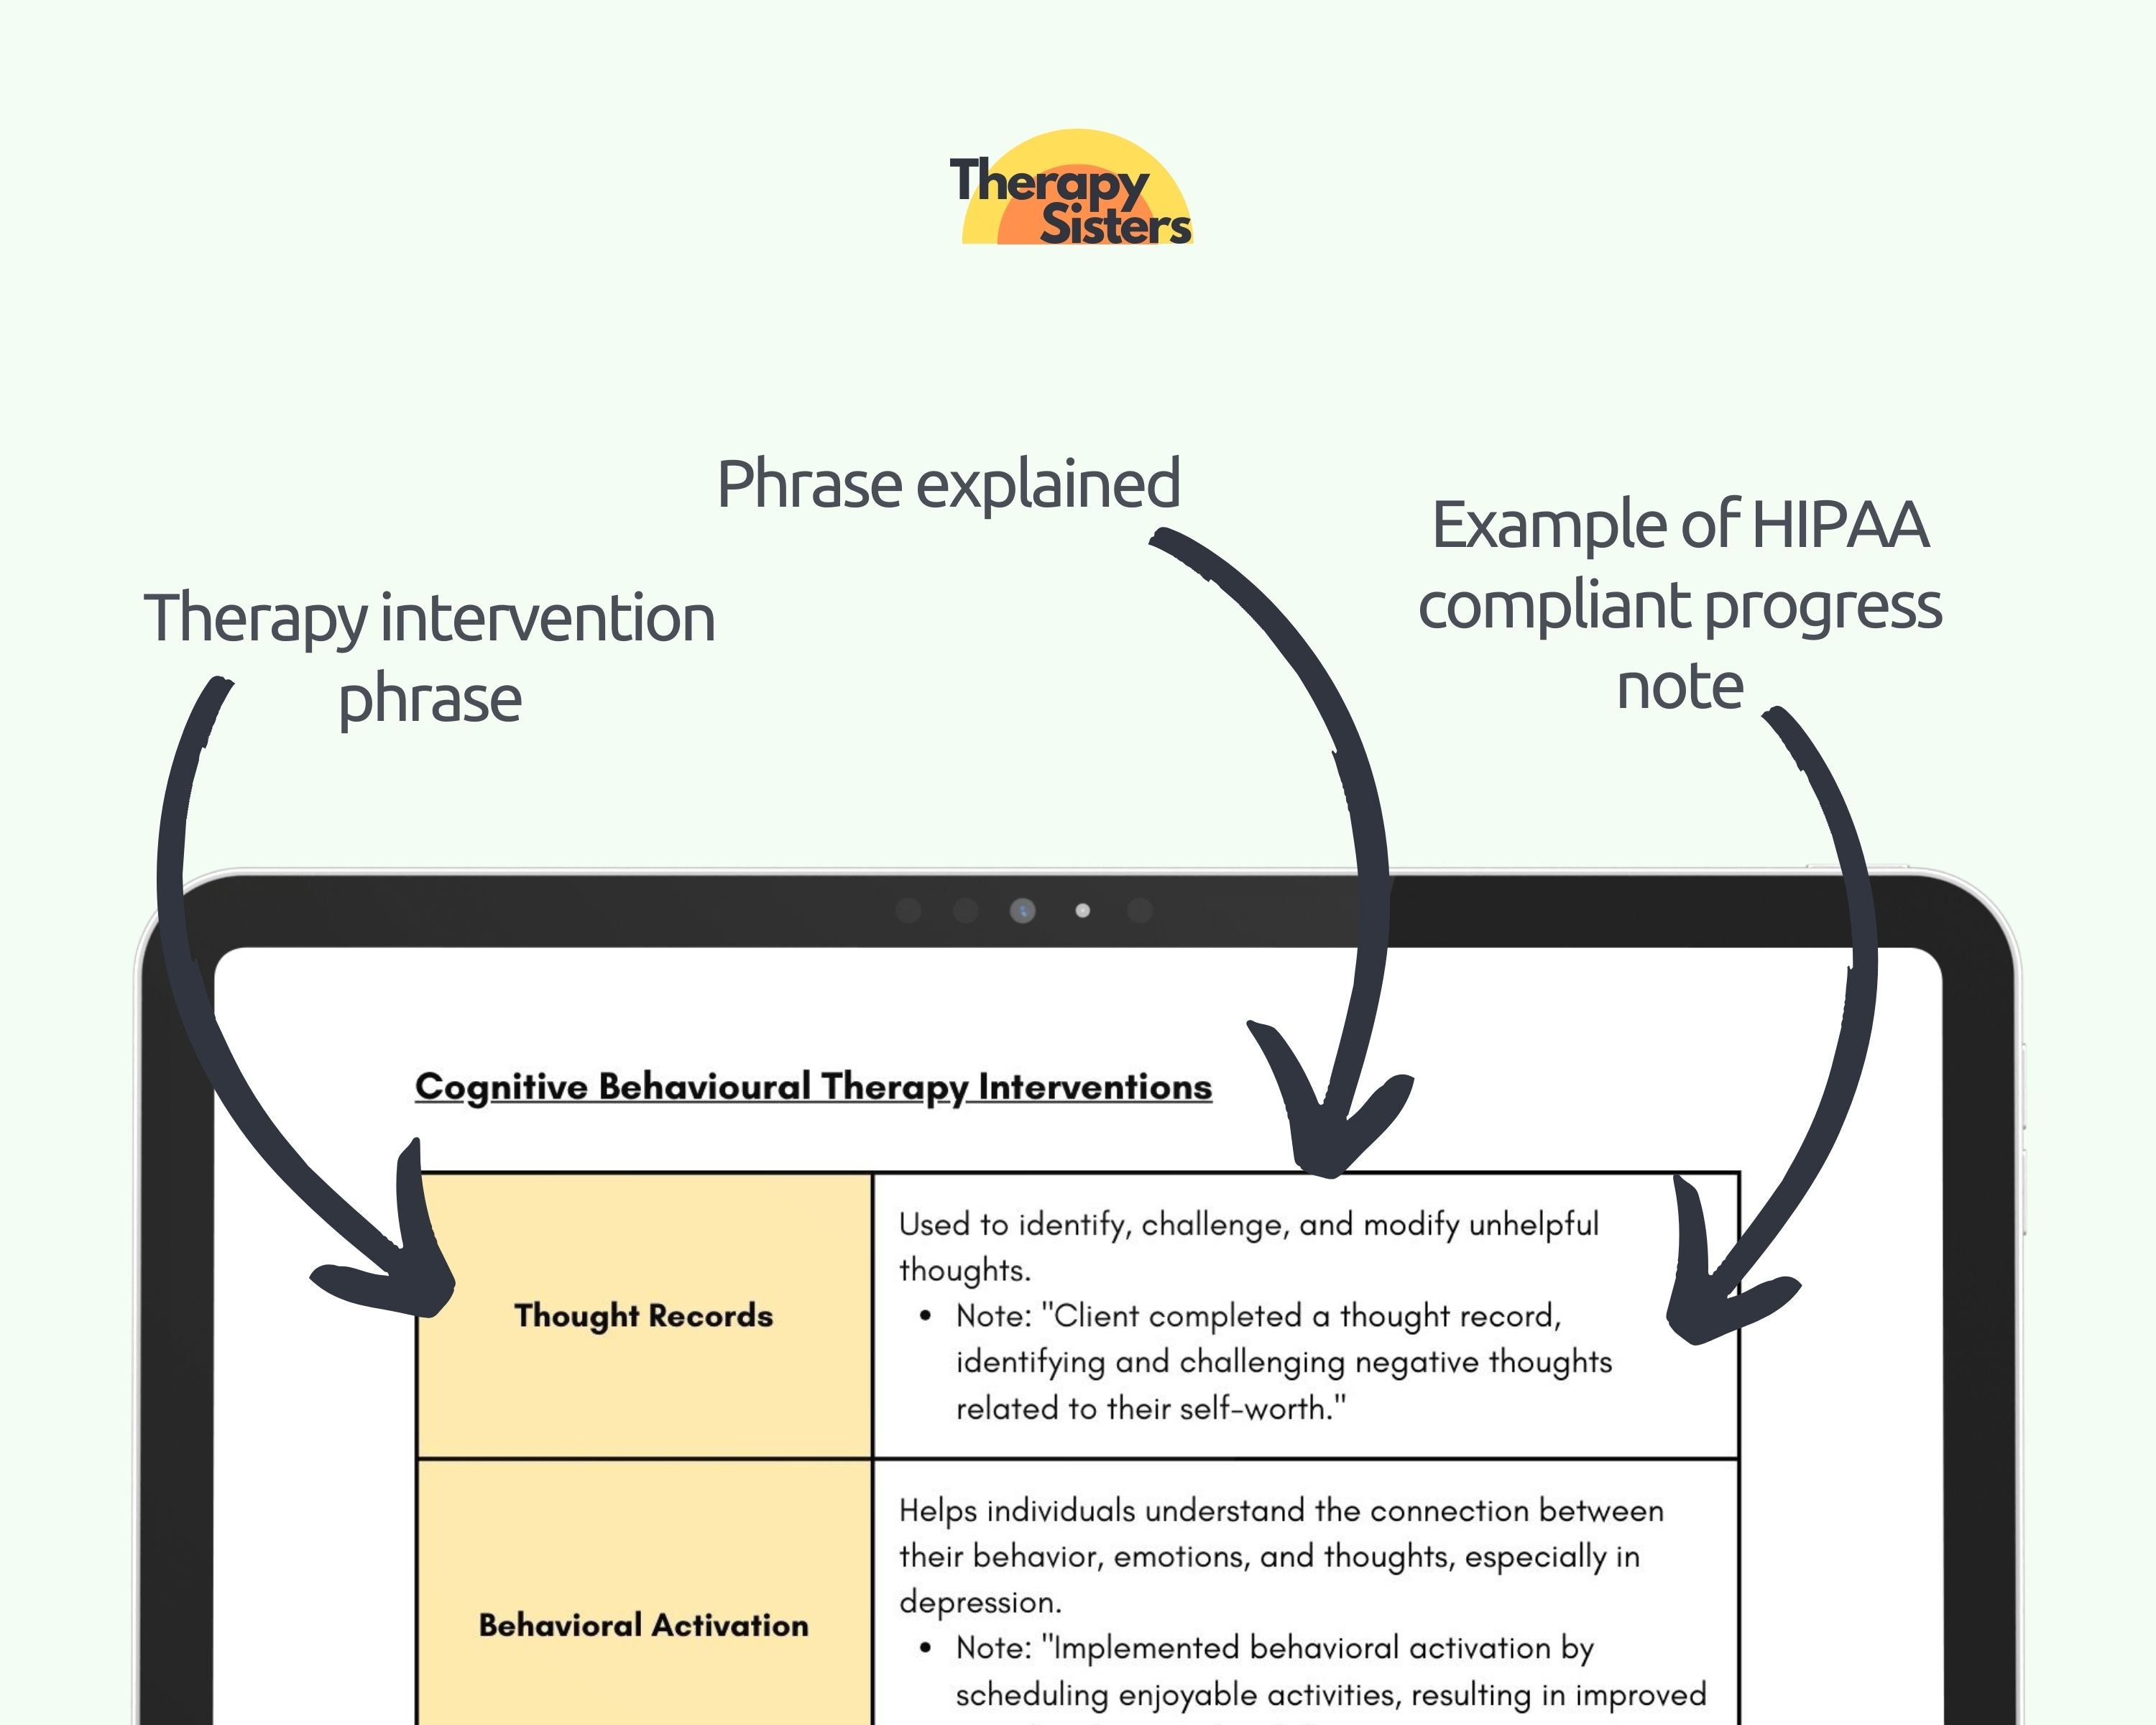
A HIPAA compliant therapy note contains the same core elements as any clinical note: date of service, modality used, client presenting concerns, interventions applied, client response, risk assessment, and plan for next session. The compliance part applies to how that information is stored, transmitted, and who can access it. The content itself isn't regulated differently under HIPAA compared to general clinical documentation standards. Here's where beginners get tripped up. HIPAA compliance requires you to maintain minimum necessary access. If you have an assistant who handles billing, they should not have access to your full clinical notes. Restricting their view to demographics, insurance information, and billing codes only is the standard approach. I had a compliance auditor flag my practice because my billing assistant's login still had read access to a note from two years ago. We hadn't thought about it because the note wasn't being used, but the system maintained that access indefinitely. Fixed it by implementing role-based access controls with automatic expiration after ninety days of inactivity. Another edge case that caught me off guard involved telehealth platforms. I was using a video platform that wasn't explicitly HIPAA compliant for the recording feature. The sessions themselves were fine, but the auto-recordings stored on the platform's servers created a compliance gap. I switched to a platform with built-in encrypted recording storage and a BAA, which added about eight dollars per month to my bill. Worth it the first time an auditor asked about your recording retention policy and I could point to a specific feature rather than winging it.
Get the Full Details

Retention and Encryption Requirements
Adult therapy records must be retained for a minimum of six years from the date of last service, or longer if your state mandates a longer period. Some states require seven, eight, or even ten years. I keep mine for seven because it varies by state depending on where my clients live and I don't want to manage multiple retention schedules. Adult records are the easier category. Pediatric records are different. You must retain them until the client reaches the age of majority plus the standard retention period. In most states that means age eighteen plus six years, so until the client is twenty-four. This creates a situation where you're maintaining records for clients you haven't seen in many years. I use a tiered storage system. Active records stay on my primary encrypted platform. Records past the first five years of retention get moved to a separate encrypted archive with restricted access. The archive costs less per gigabyte and the restricted access satisfies the minimum necessary requirement for dormant files. Encryption needs to be AES-256 at minimum. Anything less and your compliance posture is questionable. I once reviewed a platform that advertised "enterprise-grade encryption" but was only using AES-128. Their marketing materials made it sound impressive until I checked the technical specifications. AES-128 is technically still compliant with HIPAA's encryption standards, but it's the kind of detail that comes up during a thorough audit and creates unnecessary questions you'd rather not answer.
Business Associate Agreements
Every vendor you share client data with needs a signed BAA. This includes your hosting provider, your backup service, your email provider if you're using a business account, your transcription service, and any consultant who might access your systems. I learned this the hard way when my cloud storage provider changed their terms of service and I realized their previous agreement didn't cover HIPAA obligations. I had to pull all client data off their servers within thirty days and migrate to a provider that signed BAAs upfront. The migration took about twelve hours of actual work spread across a weekend. The BAA itself is usually a standard document provided by the vendor. Don't try to write your own unless you have legal counsel experienced in healthcare compliance. The template they provide is negotiated between their legal team and frequently reviewed attorneys. Your signature on it shifts certain responsibilities to them and confirms that they've agreed to maintain the required safeguards. Without a signed BAA, you're personally liable for any breach involving that vendor's handling of your data. There's a common misconception that you need a BAA with every tool you use, even ones that don't touch PHI. If a vendor never sees, processes, or stores any protected health information, a BAA isn't required. Screen sharing software where the client is actively participating in their own session doesn't require a BAA because you're not transmitting PHI to them. But if that same software has a feature that records the session to their servers, suddenly they're a business associate and you need the agreement. The line is thin and easy to miss.
Common Mistakes That Trigger Violations
Accidental disclosure is the most frequent violation I see. This happens when a therapist sends a note or treatment summary to the wrong email address, posts a case consultation in a group chat without deidentifying the client, or leaves a printed note on a communal printer. I had a colleague print a session summary for a client who was in the waiting room. She grabbed the wrong stack of papers from the printer. The client received another person's progress notes. It was reported as a breach even though no harm resulted, and the correction process cost her practice over two thousand dollars in compliance consulting fees. Another mistake involves session recordings. Recording a therapy session creates an additional layer of compliance requirements beyond the written note. The recording is subject to the same retention, encryption, and access controls. Some therapists record sessions for supervision purposes and store those recordings on a personal device without encryption. That's a violation. Even if the device has a passcode, that doesn't meet HIPAA's encryption standard for PHI at rest. I use a dedicated encrypted external drive for all recordings, and the drive is stored in a locked cabinet when not in use. It's more cumbersome than leaving a file on a laptop, but it's the kind of thing that matters when something goes wrong. Audit trails matter more than most therapists realize. HIPAA requires you to be able to produce a record of who accessed what information and when. If you can't generate that report in a reasonable timeframe, it looks like you don't have adequate controls in place, even if your controls are actually fine. I test my audit trail functionality quarterly by running a sample report for a random date range. It takes about ten minutes and ensures I'm not caught flat-footed during an actual audit or investigation.

When Technology Isn't Enough
No software makes you compliant. Software helps you maintain compliance, but the actual responsibility sits with you as the covered entity. I've seen practices invest fifteen thousand dollars in a comprehensive platform and still fail a compliance review because their staff policies were incomplete, their BAA inventory was outdated, and their incident response plan was a single page that said "call the IT guy." Compliance is a system, not a product. The technology is one component of that system alongside policies, training, and ongoing monitoring. The downside of dedicated therapy platforms is vendor lock-in and cost escalation. What starts at fifty dollars a month can climb to two hundred or more as you add features, additional providers, and storage tiers. I've watched practices get stuck on platforms because migrating thousands of notes is painful and the vendor makes it deliberately difficult to export everything in a usable format. Before committing to any platform, verify that you can export your complete record set including all metadata, audit logs, and attachments in a standardized format like HL7 FHIR or at minimum a well-structured CSV with clear field mapping. If you're operating at a very small scale with minimal risk exposure, a hybrid approach using basic encrypted tools can work adequately. I know several therapists who manage with a HIPAA-compliant email service, an encrypted note template in a locked spreadsheet, and a simple access log. It's less elegant than a full platform but it's compliant if done correctly and costs a fraction of the price. The tradeoff is that you're responsible for updating your security measures as threats evolve, whereas a platform vendor handles most of that burden for you.
The field changes frequently enough that whatever setup you choose today will need adjustment in a few years. New encryption standards emerge, regulatory guidance gets updated, and vendors change their terms. Budget time each quarter to review your documentation workflow against current requirements. Thirty minutes every three months prevents a lot of headaches down the line.