What Dicentric Chromosome Analysis Actually Is
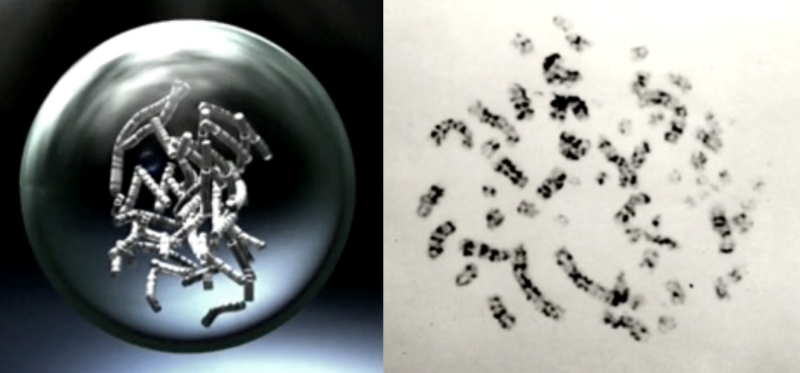
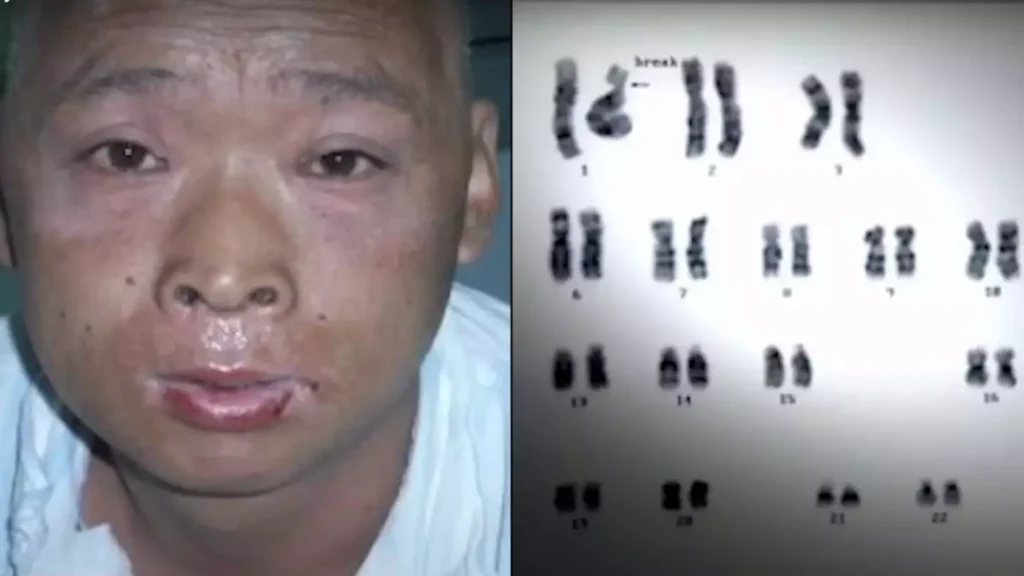
When someone asks about Hisashi Ouchi Chromosomes, they are usually talking about the cytogenetic data from the Tokaimura criticality accident in September 1999. Hisashi Ouchi was exposed to an estimated 17 gray of whole-body neutron and gamma radiation. Scientists studied his lymphocyte chromosomes extensively because the dose was high enough to produce clear, quantifiable chromosomal aberrations. The primary metric they used is the dicentric chromosome assay, which counts chromosomes with two centromeres instead of one. That structural error is the gold standard for retrospective radiation dosimetry. The chromosome analysis on Ouchi's blood samples showed dicentric frequencies that were off the normal scale. Within days of the accident, his peripheral blood lymphocytes were cultured and karyotyped. The dicentric yield was used to reconstruct the absorbed dose and track how rapidly his bone marrow was failing. What makes this case notable is not just the dose estimate but the serial sampling over time. Scientists had repeated measurements before he died, which is rare in radiation protection work. Most people never get more than one blood draw after an exposure event. The technical process starts with collecting venous blood into heparinized tubes. You culture the lymphocytes for about 48 hours with phytohemagglutinin to stimulate division. Colcemid is added near the end to arrest cells in metaphase. You hypotonic treat with potassium chloride, fix with methanol and acetic acid, drop the slides onto clean glass, and stain them. Traditionally that means Giemsa banding or fluorescence plus quinacrine. You then scan metaphase spreads under a microscope and score each cell for dicentrics, rings, and translocations. A trained scorer typically examines several hundred cells before the confidence interval on the dose estimate becomes useful.
One thing beginners get wrong is the counting threshold. If you only score 50 cells, your statistical uncertainty is enormous at high aberration frequencies. At the levels seen in severe acute exposures, cells with multiple dicentrics per nucleus are common, and you need enough cells to capture that distribution. I once ran an assay where the first 100 cells looked normal, but cells 101 through 200 had a spike in complex exchanges. Stopping early would have given a wildly incorrect dose. My workaround was setting a hard minimum of 200 scored metaphases and stopping only when the cumulative dicentric count stabilized within a tight band. That takes time, usually around 90 minutes per run if you are working alone, but it prevents the kind of error that matters when you are making treatment decisions. The Ouchi case also highlights a limitation of the assay that is easy to overlook.Dicentric chromosomes are stable markers for early dose reconstruction, but they are lost as cells divide. After repeated bone marrow stimulation or transplantation, the original aberration pattern changes. Ouchi received a bone marrow transplant during his treatment, which means later blood samples reflected donor chromosomes rather than his own original exposure signature. If you are doing retrospective dosimetry on a patient who has had a transplant, the assay reads the donor's baseline, not the exposed individual's. That can make the data unusable for confirming the initial dose. In practice, you have to sequence your samples carefully and take the earliest possible post-exposure draws before any cellular therapy alters the cytogenetic picture. There are newer methods that complement the dicentric assay. Fluorescence in situ hybridization with paint probes can detect balanced translocations that do not carry the fitness cost of dicentrics. These persist longer in dividing cells and are useful when dicentric frequencies have declined. Automated scoring systems using image analysis are also available now, which speeds up the process significantly. However, automated systems still require manual validation, especially when aberration frequencies are above 10 percent. I have found that running both manual and automated scores in parallel on high-aberration samples reduces false positives from misidentified fused chromatids. The trade-off is roughly double the hands-on time for the first month of training.
For anyone actually running this assay outside of a reference laboratory, the main bottleneck is scorer availability and consistency. Inter-laboratory variability in dicentric scoring can be substantial. Two experienced scorers might disagree on complex exchanges in the same slide by 15 to 20 percent. Normalization protocols and joint scoring exercises help, but they are not always feasible in urgent situations. The International Center for Radiation Protection and the IAEA maintain intercomparison programs that laboratories can join to benchmark their scoring accuracy. Participating in at least two rounds per year keeps your personal bias in check.
Get the Full Details

Practical Steps to Run the Assay Yourself
You need a few specific materials before starting. Heparinized blood collection tubes, RPMI 1640 culture medium supplemented with 20 percent fetal bovine serum, phytohemagglutinin P, colcemid solution, 0.075 molar potassium chloride for hypotonic treatment, Carnegie Hill fixative made from three parts methanol to one part glacial acetic acid, and clean 75 by 25 millimeter microscope slides. A CO2 incubator set to 37 degrees Celsius, a centrifuge with a swing-bucket rotor, and a light microscope with oil immersion objectives are essential. Fluorescence microscopes are optional unless you plan to do FISH work. The culture step takes roughly two days. You mix one milliliter of whole blood with nine milliliters of culture medium containing phytohemagglutinin and incubate it. Shake the culture flask gently every six to eight hours to keep cells suspended and oxygenated. Add colcemid at the 48-hour mark and incubate for another 40 minutes. Then centrifuge at about 200 times gravity for 10 minutes. Decant the supernatant carefully and resuspend the pellet in prewarmed potassium chloride for five minutes. Centrifuge again, remove supernatant, and add fixative slowly while mixing. Repeat the fixation cycle twice more, then drop the cell suspension onto slides from about 30 centimeters above the surface. Air dry them completely before staining. Scoring takes the bulk of the time. You scan each slide systematically in a grid pattern, focusing on well-spread metaphases where chromosomes are individually resolved. A dicentric chromosome has two distinct centromeric constrictions and two arms extending from each. You record the number of dicentrics per cell, any rings, and any acentric fragments. Complex exchanges involving three or more breaks are noted separately. You aim for 200 to 500 scored cells depending on the expected dose range. At low environmental doses, you need more cells to detect a signal above background. At very high doses, fewer cells may suffice because the aberration frequency is so elevated, but you must also account for cell cycle delay, which means fewer cells actually reach metaphase.
Converting dicentric counts to dose requires a calibration curve generated from your own laboratory setup. You expose parallel blood samples to a known radiation source, usually a cesium-137 gamma irradiator, at several dose levels ranging from zero to about eight gray. You run the assay on each sample and plot dicentric frequency against dose. The resulting curve is typically linear-quadratic, described by the equation Y = C plus alpha D plus beta D squared. The coefficients alpha and beta are specific to your equipment, your scoring criteria, and your culture conditions. Using someone else's calibration curve without validating it against your own setup introduces systematic error that can shift dose estimates by 20 to 40 percent. This is a common pitfall in emergency response scenarios where time pressure tempts people to skip the calibration step. If you need results quickly after an accident, there is a simplified version called the fast dicentric assay. It uses shorter culture times and focuses only on scoringdicentrics without elaborate banding. You can get a preliminary dose estimate in about four to six hours instead of two days. The trade-off is lower resolution and a wider confidence interval. Fast assays are useful for triage, not for final medical documentation. I have used them in simulated drills and they cut the initial assessment window from 48 hours down to roughly five, which makes a real difference when patients are arriving simultaneously. The data from the Hisashi Ouchi Chromosomes case remains one of the most detailed records of human radiation chromosome damage ever compiled. It demonstrated that even at extremely high doses, the dicentric method can provide meaningful dose estimates if samples are collected early and scored rigorously. It also showed the limits of what cytogenetics alone can tell you, especially after therapeutic interventions alter the hematopoietic system. The practical takeaway is that the assay works, but only when you respect the timing, the calibration, and the scorer variability. Skipping any of those three steps tends to produce numbers that look precise and are actually misleading.