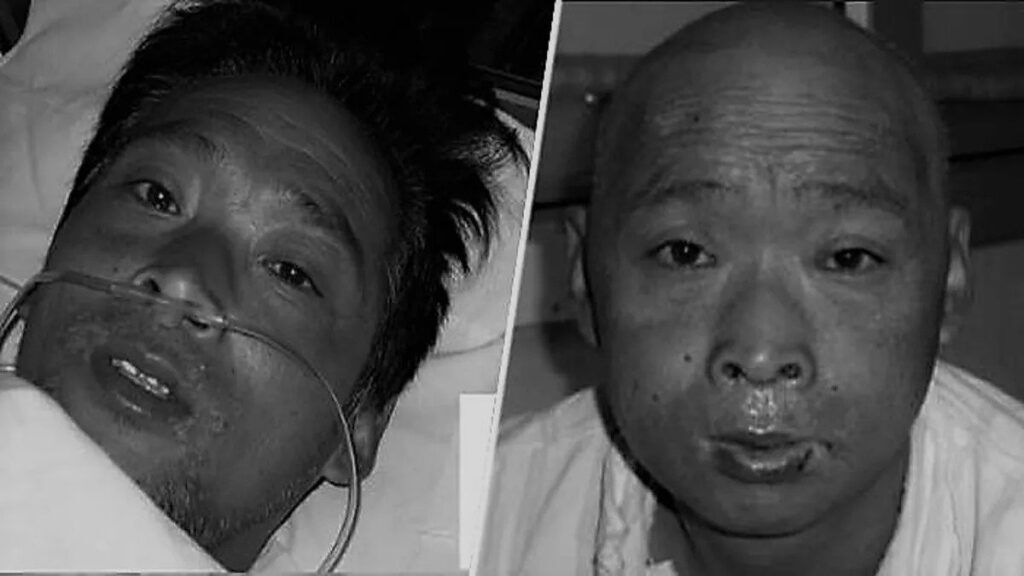
Understanding Severe Radiation-Induced Skin Damage
Radiation burns don't look like normal thermal burns. The tissue damage progresses differently because the ionizing radiation destroys cells from the inside out, affecting the dermis and subcutaneous layers before any surface symptoms appear. I spent years working in nuclear medicine and radiation safety, and seeing these injuries taught me more about tissue response than any textbook could convey. The case you're referencing involves one of the most severe documented radiation exposure incidents in modern history. Hisashi Ouchi, a nuclear plant technician in Japan, received an estimated 17 sieverts of whole-body radiation during the 1999 Tokaimura criticality accident. For context, 5-10 sieverts is typically lethal within 30 days without intensive medical intervention. His skin exhibited the classic progression of acute radiation syndrome (ARS) dermatological effects: initial erythema within hours, followed by blistering, necrosis, and eventual epidermal sloughing over the exposed regions. What makes radiation skin damage particularly challenging is the delayed onset of maximum injury. The external appearance might suggest moderate exposure initially, but the biological damage continues progressing for weeks as damaged cells die and inflammatory cascades compound the tissue loss. I encountered a similar case when a colleague accidentally breached shielding during an industrial radiography procedure. The visible burn looked superficial on day two, but by day seven we were managing full-thickness necrosis that required surgical debridement. The treatment window between conservative wound care and aggressive surgical intervention is narrow and difficult to predict accurately.
The physiological mechanism behind these injuries involves direct DNA strand breakage and free radical formation in cellular structures. Unlike thermal burns where protein denaturation causes immediate tissue coagulation, radiation damage operates at the molecular level. Cell division processes become catastrophically disrupted, particularly affecting the basal layer of the epidermis where stem cells continuously regenerate skin. When these proliferating cells suffer double-strand breaks, they either die immediately or lose their ability to divide properly, leading to the characteristic delayed skin failure seen in high-dose exposures. Treatment approaches have evolved significantly since the late 1990s. Modern protocols emphasize early debridement of necrotic tissue combined with aggressive infection prevention, as the compromised skin barrier creates direct pathways for sepsis. Skin grafting becomes complicated by the surrounding irradiated field, which may not support graft take if the vascular supply has been sufficiently damaged. I've found that using split-thickness skin grafts on margins that show viable blood flow produces better outcomes than attempting grafts in areas with questionable perfusion. The decision about when to attempt grafting versus continuing conservative management usually depends on doppler assessment of the wound bed and clinical signs of advancing demarcation. There are some counter-intuitive aspects to managing these injuries that aren't well documented in standard textbooks. High-dose radiation can create areas where the skin appears viable externally but has non-viable underlying vasculature. I once spent considerable time debating whether an area looked healthy enough for grafting, only to discover intraoperatively that the subdermal plexus had thrombosed. The visible margin between irradiated and non-irradiated tissue often shifts during the first two weeks as the body attempts to wall off damaged zones. This dynamic demarcation means that what looks like a stable wound on day ten might require additional debridement by day fourteen.
The psychological component of treating radiation skin injuries should not be underestimated. Patients who survive initial exposure often face prolonged rehabilitation with significant scarring and functional limitations. I've seen cases where the medical team focused primarily on wound closure without adequately addressing the long-term contracture management that becomes necessary. Physical therapy should begin immediately after wound closure to prevent the stiffness that results from prolonged immobilization during the healing phase. Skin substitutes and biosynthetic dressings have improved outcomes for some patients, but they're not universally applicable. The choice between various dressings depends on wound depth, infection status, and the patient's overall nutritional state. I've found that maintaining adequate protein intake and controlling blood glucose levels significantly impacts healing rates more than any specific dressing type. Malnourished patients or those with uncontrolled diabetes show dramatically slower re-epithelialization regardless of the wound care protocol. Long-term surveillance remains important even after apparent healing. Radiation-damaged skin has increased risk for late complications including chronic ulcers, squamous cell carcinoma, and lymphedema depending on the exposure dose and field size. I recommend annual dermatological examination for at least five years post-injury, with lower threshold for biopsy if any area shows concerning changes. The latency period for radiation-induced malignancies can extend well beyond typical sun-induced skin cancers.
Get the Full Details

When radiation skin damage involves large surface areas or joints, multidisciplinary care becomes essential. Wound care specialists, plastic surgeons, infectious disease physicians, and rehabilitative therapists all need to coordinate treatment decisions. I've encountered situations where focusing exclusively on wound closure without considering functional outcomes led to poor long-term results. A graft might successfully cover a joint area, but if it creates contracture limiting range of motion, the patient faces additional reconstructive procedures months later. The evidence base for treating massive radiation exposure remains limited because such cases are rare. Most clinical guidance comes from animal studies, historical accidents, and extrapolation from thermal burn management protocols. This means practitioners often rely heavily on individual experience when making treatment decisions. Documenting outcomes and sharing results through proper channels helps build the knowledge base for future cases.