What You Actually See Under The Microscope When Studying Renal Architecture
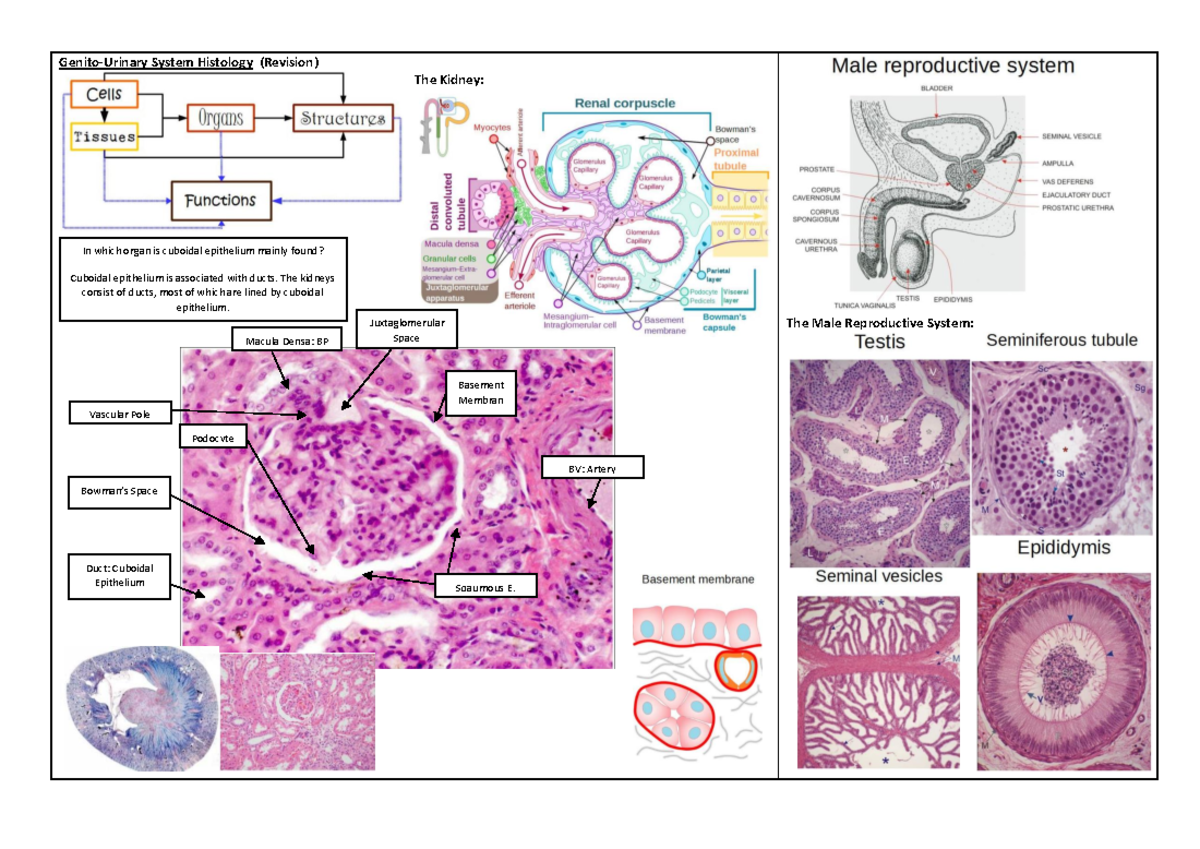
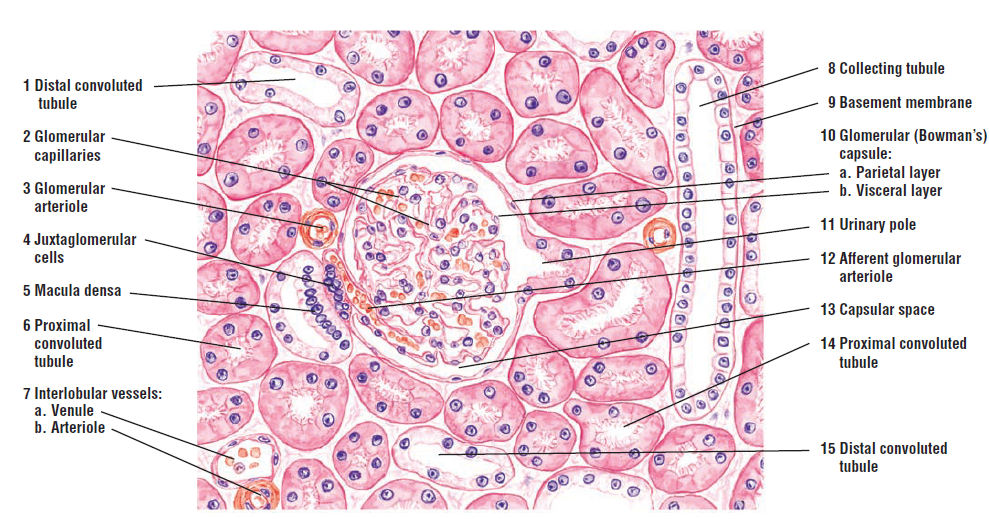
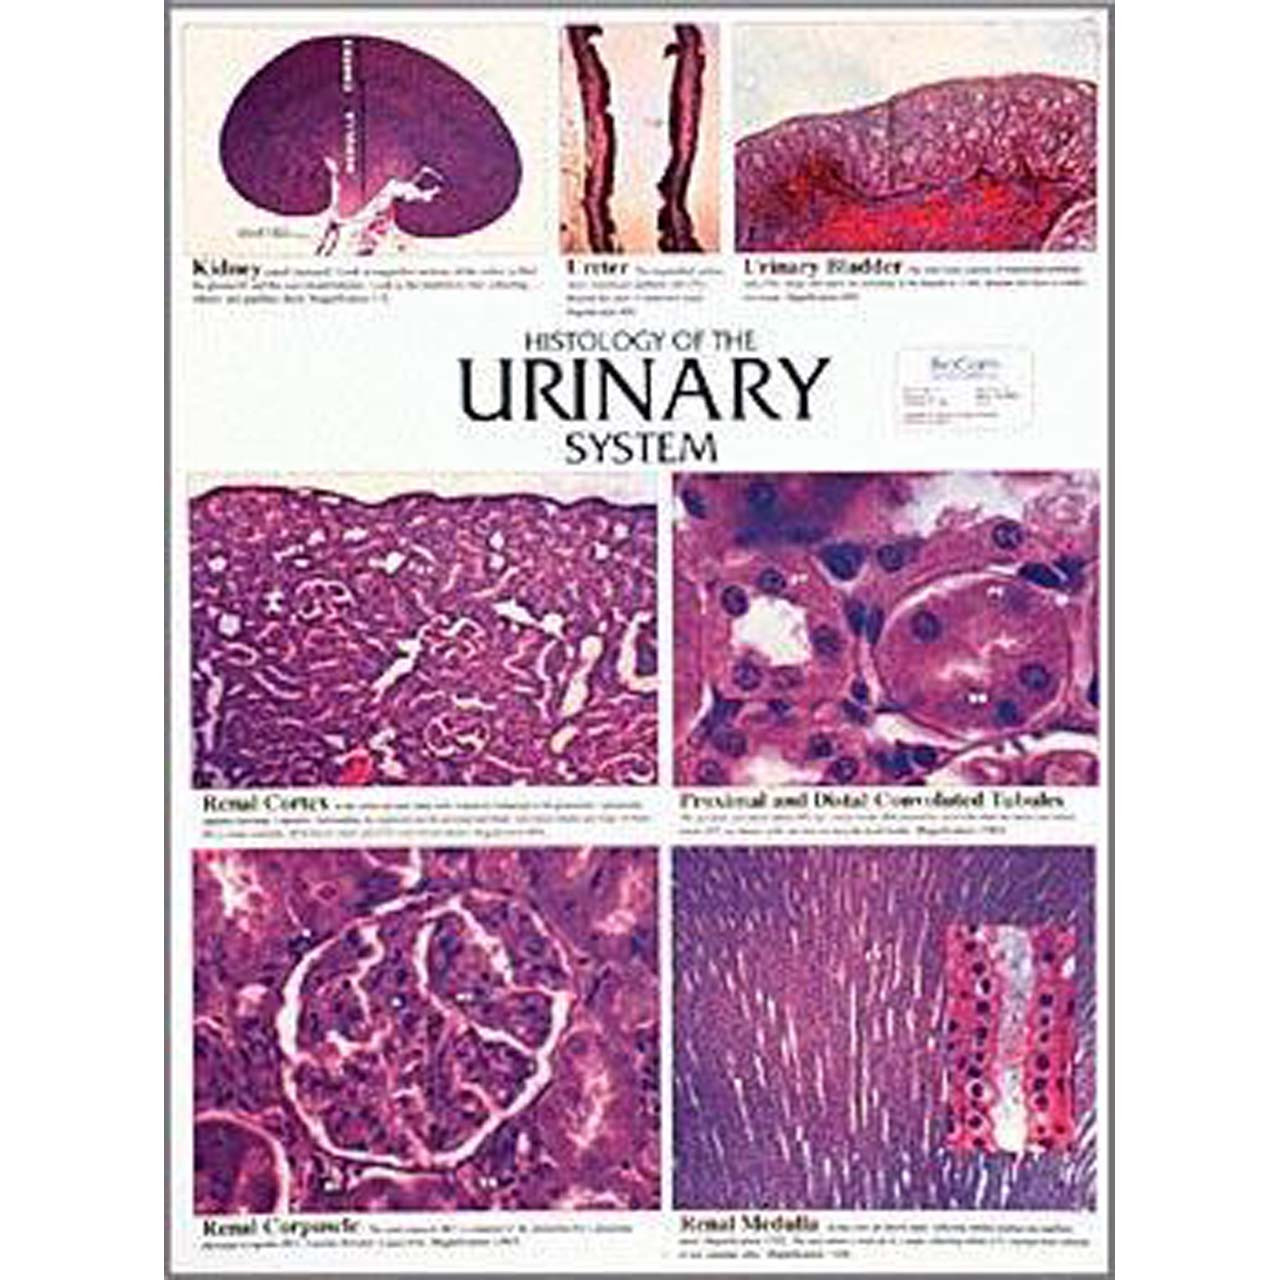
I spent three years grinding through slide after slide of kidney tissue before I stopped misidentifying things. The urinary system sounds straightforward on paper. The cortex, the medulla, the collecting ducts. That is until you are staring at a H&E-stained section at 40x and you cannot tell whether you are looking at a proximal convoluted tubule or a loop of Henle because they both just look like epithelial circles to a tired student. The Histology Of The Urinary System demands you learn to read cellular detail at the level of individual microvilli and basal infoldings, not just memorize organ names from a diagram. Start with the kidney. It is the organ that contains every structure you need to recognize, and it gives you the most histological variety per slide. Everything else in the urinary tract is largely lined by variants of transitional epithelium, which gets repetitive fast. The renal corpuscle is your starting landmark. It sits in the cortex and consists of the glomerulus surrounded by Bowman's capsule. The parietal layer of Bowman's capsule is simple squamous epithelium, thin and flat. The visceral layer is made up of podocytes that wrap around the capillaries. You will struggle to see podocyte foot processes on standard H&E because they are too fine. Those require silver impregnation stains or electron microscopy. Do not waste time hunting for them on a routine section. Instead, look for the urinary space, the clear area between the visceral and parietal layers, and use that to confirm you have found a corpuscle.
Beyond the corpuscle, you need to map the nephron segments. Proximal convoluted tubules are the most abundant. They are identifiable by their eosinophilic cytoplasm, brush border of microvilli on the luminal surface, and relatively small lumens. The cells are cuboidal to low columnar. Distal convoluted tubules have clearer lumens, less eosinophilic cytoplasm, no visible brush border, and the nuclei sit more centrally within the cells. Students consistently confuse PCTs and DCTs. The single most reliable differentiator is the brush border. If you see it, it is proximal. If you do not, it is likely distal. That rule saves you from second-guessing yourself on every ambiguous tubule. The loop of Henle presents its own problems. The descending limb is simple squamous epithelium with a very narrow lumen. The ascending limb is cuboidal, thinner than the proximal tubule, and again lacks a brush border. In light microscopy, the thin segments are easy to miss unless you are scanning the outer medulla carefully. They are thin walls precisely because their function is passive water and ion permeability, not active transport. The thick ascending limb blends into the distal convoluted tubule without a clear anatomical boundary. You will see a gradual transition, not a hard line. Moving to the medulla, the collecting ducts take over. They are lined by simple cuboidal epithelium with distinct cell borders. The nuclei are round and centrally located. The cytoplasm is paler than proximal tubules but more eosinophilic than distal ones. Collecting ducts are your final convergence point before urine exits the renal pyramids through the ducts of Bellini. These open at the renal papilla into the minor calyx.
I learned this the hard way during a practical exam where I was asked to identify a segment of nephron from a cross-section with no landmarks provided. I spent four minutes trying to decide between proximal tubule and thick ascending limb. I had marked proximal because the cytoplasm was eosinophilic, but I had missed that the lumen was actually quite large and irregular, which is more consistent with ascending limb. I lost points on that question. After that, I started training myself to check three features in order: lumen size and shape, cytoplasmic eosinophilia, and presence or absence of a brush border. That sequence reduced my identification errors significantly.
Get the Full Details
The Rest Of The Tract And What Makes It Different
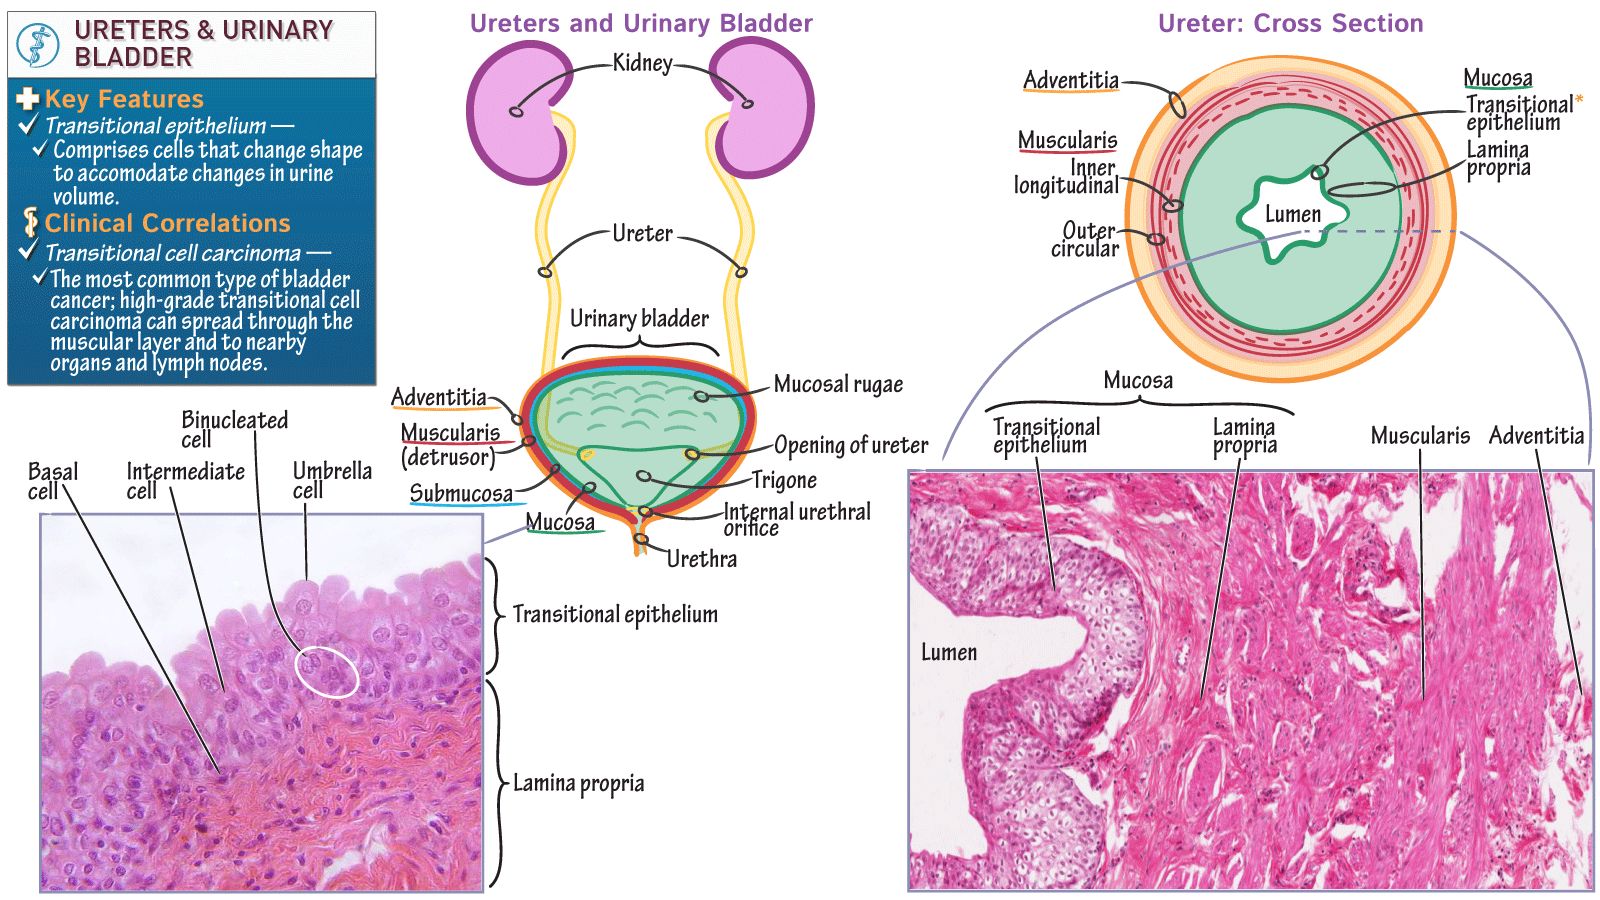
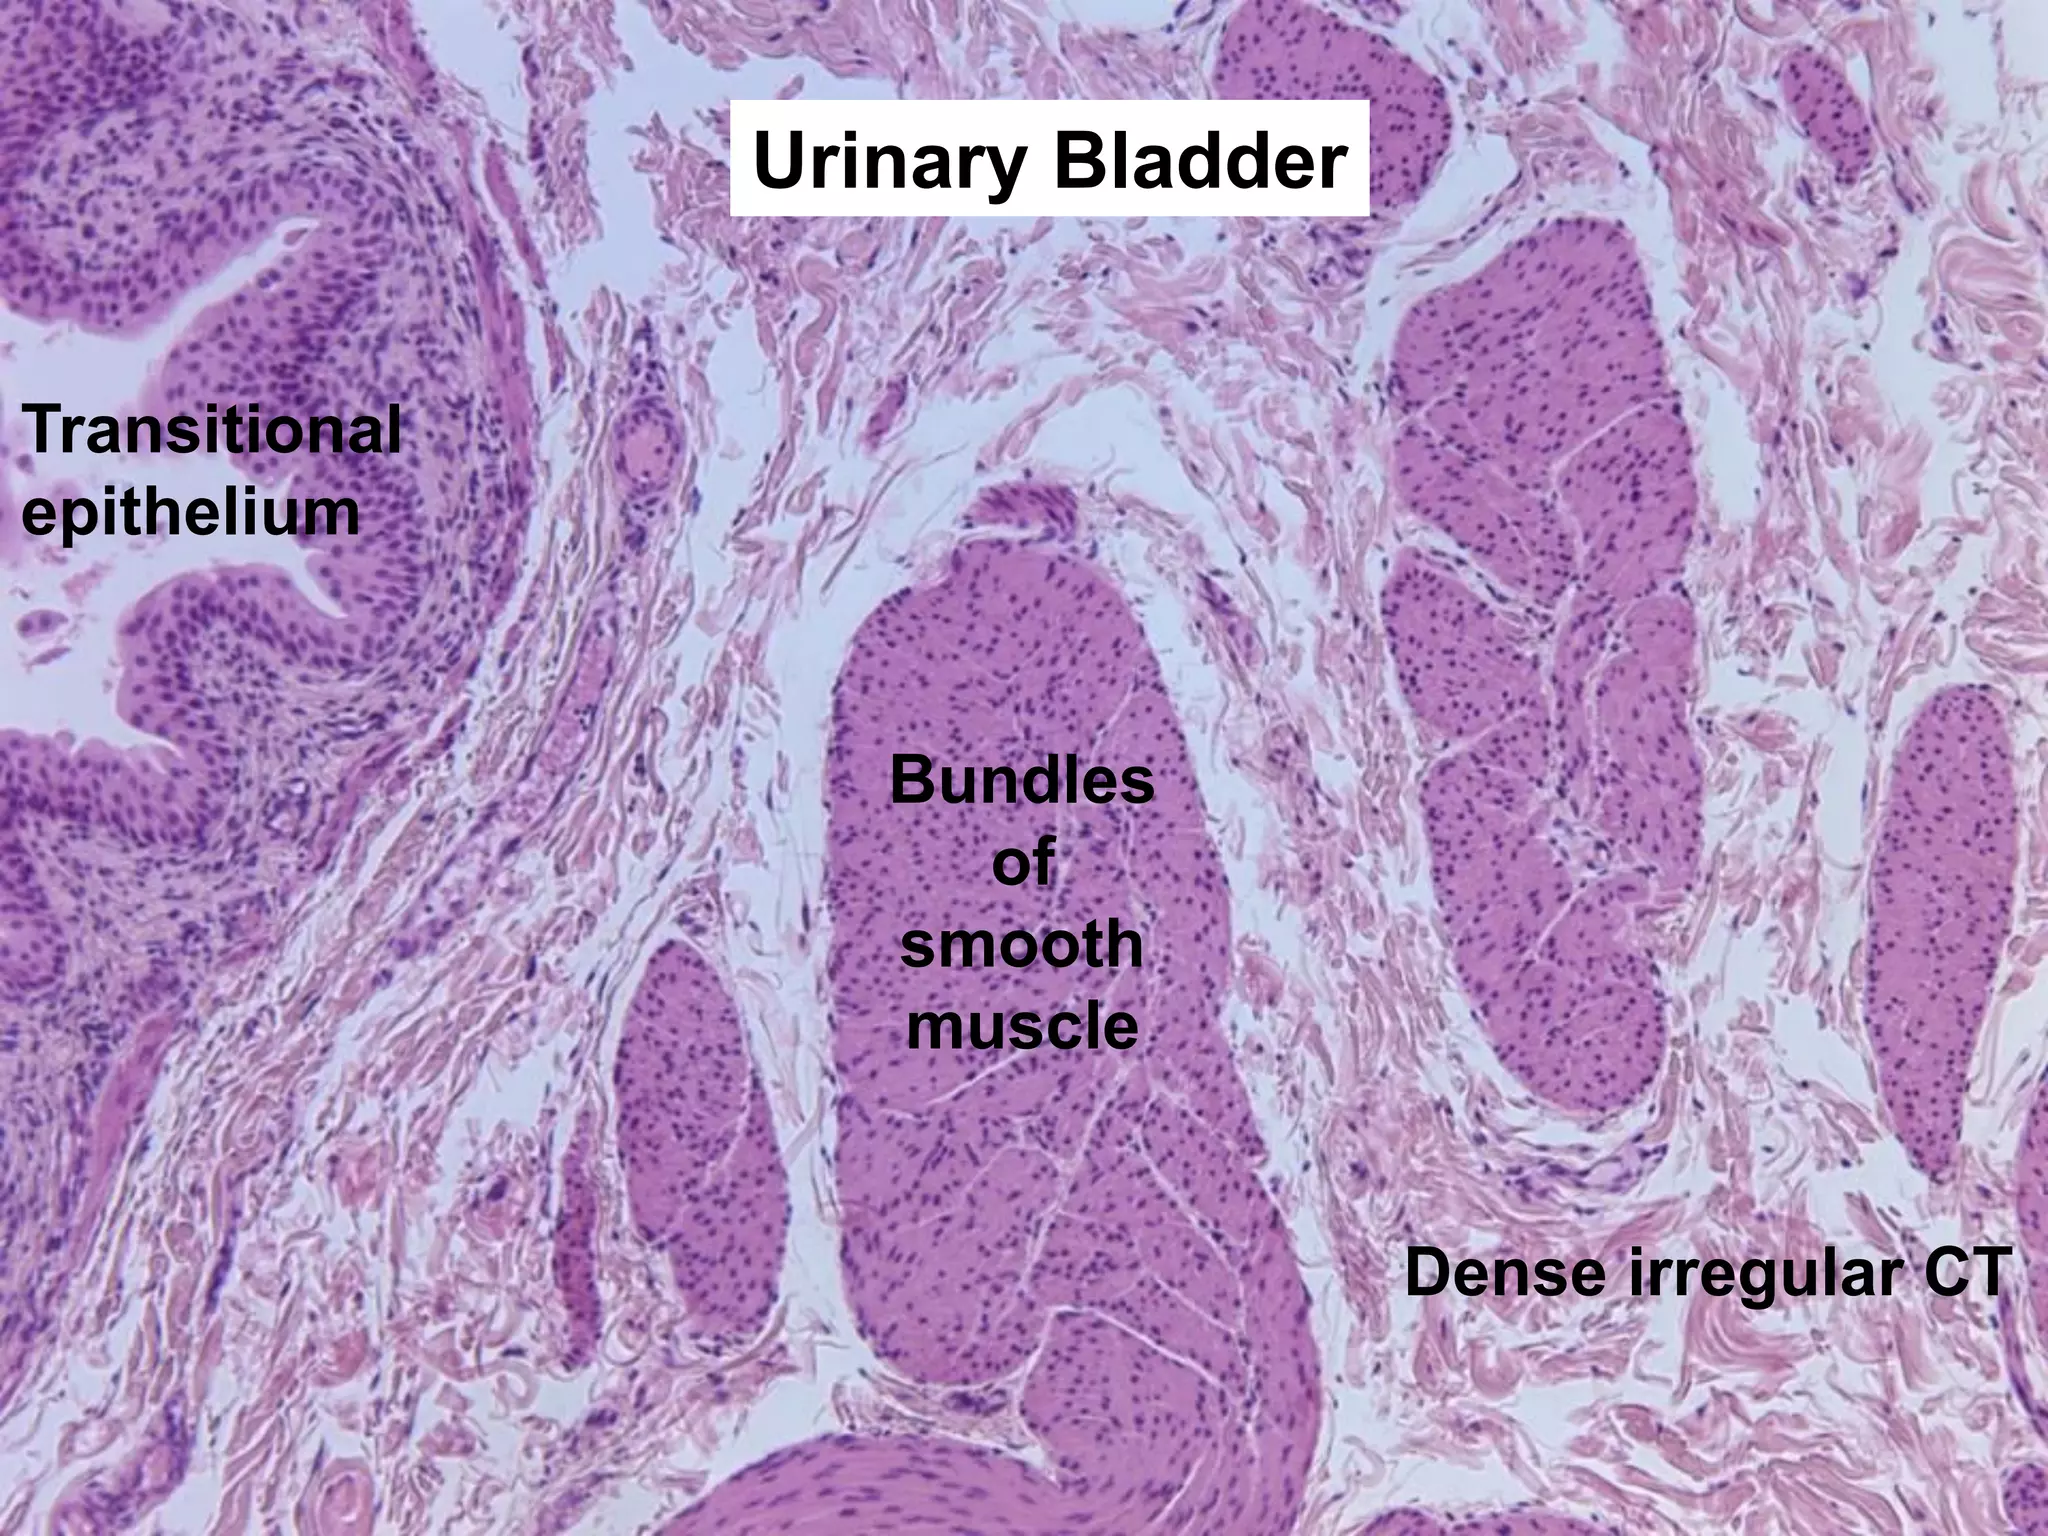
The ureters, bladder, and proximal urethra share one histological feature above all others. They are lined by urothelium, also called transitional epithelium. This is not a trivial distinction. Urothelium is specialized for stretching and acts as a permeability barrier against urine. Under ordinary conditions, it looks stratified with dome-shaped superficial cells. When the organ is distended, those dome cells flatten out and the tissue appears much thinner. You will see both states on different slides, and both are normal. Do not call a contracted urothelium "hyperplastic" or a stretched one "atrophic." That is a common mistake on lab reports. The urothelium has multiple layers. The basal layer consists of small cuboidal cells attached to the basement membrane. The intermediate layer contains polygonal cells. The superficial layer has the characteristic dome or umbrella cells, some of which are binucleated. The apical surface of these umbrella cells bears a thickened plasma membrane called the apical membrane or plaques, which are rich in uroplakin proteins. You cannot see plaques on light microscopy. They require immunohistochemistry. But you can infer the presence of a healthy urothelial barrier by the uniformity and continuity of the superficial cell layer. If that layer is disrupted, the tissue is abnormal regardless of the staining quality. The lamina propria underneath the urothelium is loose connective tissue containing blood vessels, nerves, and occasional lymphoid aggregates. Beyond that lies the muscularis. In the ureter, this is typically two layers: an inner longitudinal layer and an outer circular layer. In the bladder, the detrusor muscle is three layers in the trigone region but often described as two in general textbooks. The outermost layer varies by location. The intraperitoneal bladder is covered by serosa. The extraperitoneal portions have adventitia instead. Confusing serosa with adventitia on an exam is a quick way to lose marks, so always check whether a mesothelial lining is present before labeling the outer layer.
The prostate and seminal vesicles are sometimes grouped into urinary system courses because of anatomical proximity, but they are not part of the urinary tract histologically. The prostate is a mucosal gland with fibromuscular stroma. Its secretory epithelium is mostly simple columnar to cuboidal. You will see corpora amylacea, the laminated eosinophilic bodies, in older specimens. These increase with age and are not pathological. The urethra changes character along its length. The prostatic urethra is lined by transitional epithelium in most regions. The membranous and spongy urethra transition to stratified columnar or pseudostratified epithelium, and the external meatus becomes stratified squamous. This gradient matters because it determines susceptibility to different pathologies.
Staining Choices And What They Reveal
H&E is the default, but it leaves gaps. For renal histology, PAS stain is nearly essential. It highlights the glomerular basement membrane and the brush border of proximal tubules because both are rich in glycoproteins and carbohydrates. The Bowman's capsule basement membrane is normally thin and faint on H&E. On PAS, it stains bright magenta and you can assess thickness and integrity much more accurately. Thickening of the GBM is a hallmark of diabetic nephropathy and other glomerulopathies. If you are studying pathology, skipping PAS is a serious oversight. Masson's trichrome is useful for fibrosis. Collagen stains blue, muscle and cytoplasm stain red, and nuclei stain black. In chronic kidney disease, the interstitium becomes fibrotic and tubules atrophy. Trichrome makes that fibrosis immediately visible in a way that H&E does not. The distinction between normal pink collagen in the capsule and pathological blue collagen in the interstitium is something you develop an eye for after processing enough slides. For the urothelium, immunohistochemistry for uroplakin III is the gold standard for confirming urothelial differentiation in tumors. Normal urothelium shows strong membranous staining. Urothelial carcinoma may lose that staining pattern, and the degree of loss correlates with grade. This is clinically relevant and worth understanding even if you are only doing basic histology, because it connects structure to function and disease.
A specific problem I ran into involved identifying early amyloid deposition in renal biopsies. On H&E, the mesangial expansion looked subtle and nonspecific. I spent considerable time comparing sections before realizing the material was amorphous and eosinophilic in a way that matched Congo red positivity rather than normal mesangial matrix. The workaround was straightforward once I knew to look for it. I switched to Congo red staining and viewed the sections under polarized light. The apple-green birefringence was unmistakable. This taught me that when H&E findings are ambiguous in renal pathology, moving to a special stain early rather than delaying is more efficient than spending hours debating morphology on a single preparation.
Common Pitfalls And How To Avoid Them
One persistent issue is confusing arcuate vessels with tubular cross-sections. Arcuate arteries and veins run along the corticomedullary junction and their walls are thicker than surrounding tubules. The endothelial lining is flat and the lumen is often collapsed or irregular. A novice might label a cross-sectioned arcuate artery as a proximal tubule because both have eosinophilic cytoplasm and a central lumen. The difference is in the wall structure. Blood vessels have smooth muscle in their media. Tubules have epithelial cells. Check for the presence of a muscular wall and an internal elastic lamina, especially on elastic van Gieson stain if available. Another frequent error is misidentifying juxtaglomerular apparatus components. The JGA is where the distal convoluted tubule contacts its own glomerulus. The macula densa cells in the DCT are tall, narrow, and tightly packed. They sit opposite the afferent arteriole, where juxtaglomerular cells are modified smooth muscle cells that appear larger and more granular. These granules contain renin. On H&E, the granules are visible as coarse eosinophilic material in the cytoplasm. Students often miss the JGA entirely because they do not know where to look. It is always at the vascular pole of the glomerulus, where the afferent and efferent arterioles enter and exit. Find the glomerulus first, then locate the vascular pole, and scan the adjacent DCT for the macula densa. The renal lymphatics are another structure that gets overlooked. They are thin-walled channels in the interlobular and capsular regions, often containing pale proteinaceous fluid. They are easy to confuse with blood vessels, but the walls are much thinner and the lumens are more irregular. Lymphatic vessels lack red blood cells inside their lumens, which is a quick distinguishing feature. This is a minor point for most courses, but it comes up in advanced histology practicals.
Practical Workflow For Slide Analysis
When you are given an unknown kidney section, do not start at 400x. You will lose orientation immediately. Begin at 4x to identify cortex versus medulla. The cortex is darker and more granular. The medulla is paler with parallel striations from the collecting ducts and loops of Henle. At 10x, locate the renal corpuscles to confirm you are in the cortex. Then move to 40x for tubule identification. Reserve 100x oil immersion for basement membrane detail and brush border examination. Work through a systematic checklist for each field of view. Corpuscle present or absent. Tubule type by lumen size and cytoplasmic staining. Basement membrane thickness if visible. Interstitial cellularity. Vascular structures and their wall composition. This prevents you from fixating on one structure and missing the broader architecture. I used to jump straight to 400x on the first interesting-looking glomerulus and then spend ten minutes trying to figure out where I was. That approach is slow and unreliable. The bottom-up method is slower at first but far more accurate once you build the habit. For the ureter and bladder, the workflow is simpler but no less important. At low power, confirm the presence of urothelium and note its thickness. At medium power, assess the lamina propria and muscularis layers. At high power, examine the superficial umbrella cells for integrity and the basal layer for mitotic activity. Mitotic figures in the urothelium are rare in normal tissue. If you see them, especially near the surface, that is a red flag for dysplasia or neoplasia. Document the depth of the affected layer and the architectural distortion. These are the features that separate reactive changes from true pathology.

Resources That Actually Help
The WHO Classification of Tumours of the Urinary System and Kidney is dense but authoritative for pathology correlations. For pure histology, the digital slide archives from university pathology departments are invaluable because you can zoom without losing focus. The Rosai and Ackerman resources are good references but better suited for surgical pathology than basic histology. For a purely histological atlas, Bancroft's Theory and Practice of Histological Techniques remains one of the more complete practical guides, even though it is technical in tone. There is no substitute for looking at real slides. Virtual slide collections from institutions like the University of Michigan or the Electron Microscopy Image Library provide high-quality images with annotations. The Electron Microscopy Image Library in particular has excellent TEM images of podocyte foot processes and cilia in the efferent ductules, which you cannot appreciate from light microscopy alone. If you are trying to understand why certain diseases affect specific segments of the nephron, those images clarify the structural basis far better than any textbook description. The urinary system histology is not inherently difficult. It is detailed and it requires patience. The structures are small and they overlap in appearance. The key is building a reliable identification sequence and sticking to it rather than guessing from memory. Once you can confidently distinguish proximal from distal tubules and recognize the urothelium at any degree of distension, the rest of the system falls into place with relatively little additional effort.