Navigating ICD-10 Codes for Hypertension History
When you're coding claims for patients with a history of hypertension, the last thing you want is a denial that sends you back into the charts for three days. I've been doing this long enough to know that a single wrong digit can cascade into rejections, audits, and lost revenue. The system seems straightforward until it isn't. That's where most people trip up. The core code you'll be reaching for is Z86.73, which covers personal history of hypertension. It sits in the Z chapter for factors influencing health status and contact with health services. The key word here is "history." You use this when the condition is no longer present, has been resolved, or is being managed and documented as a past condition. If the patient currently has active hypertension, you code I10 instead. Mixing those two up is the fastest way to trigger a medical necessity review from any payer. I remember working a case last fall where a patient had a history of gestational hypertension that resolved after delivery, but the outpatient clinic was still documenting it as an active problem. The coder put I10 on the claim and it went straight to denial. What actually should have happened was we pulled the delivery records, confirmed resolution, and switched to O26.1- for the pregnancy-related hypertension, then documented Z86.73 as a secondary code for the historical component. Took about twenty minutes once I had the delivery summary in hand, but the denial came back two weeks later because nobody had pulled those records in the first place.
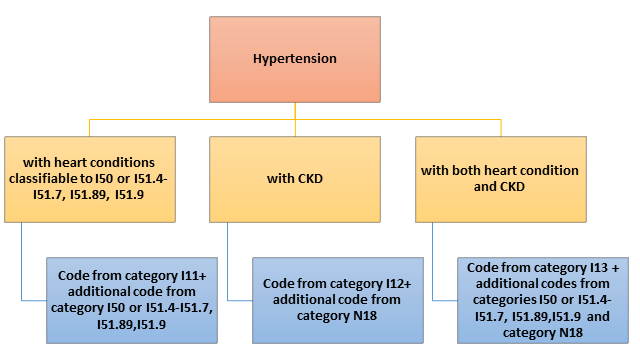
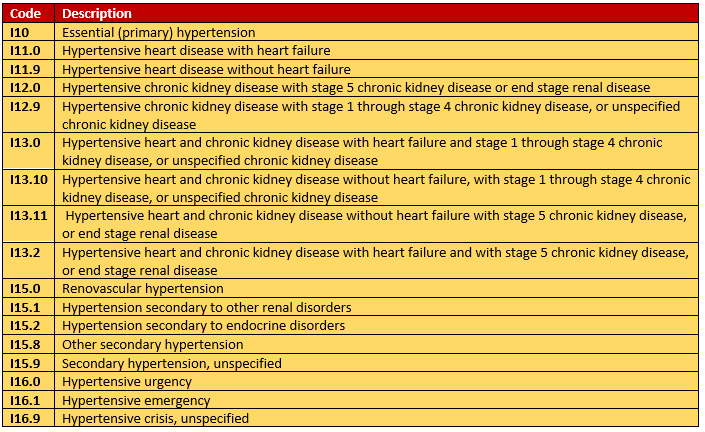
Here's something beginners consistently miss: Z86.73 cannot stand alone as a primary diagnosis on most payer claims. It's a supplementary code by design. Payers expect an active condition or reason for the encounter to be listed first. If you lead with Z86.73, you're essentially telling the reviewer there's nothing wrong right now, which triggers questions about why the visit happened at all. I've seen this take down whole batches of claims during quarterly audits because the coder thought the historical code was sufficient. The secondary issue involves code specificity. Z86.73 itself doesn't get further subclassification in the base code, but if you're dealing with hypertensive heart disease that's been historically treated, you're looking at I11.- with the appropriate fifth character. If the patient had hypertensive chronic kidney disease and it's now managed, I12.- applies. The trick is knowing when the historical code takes precedence versus when the current complications still need active coding. My rule of thumb: if there's ongoing treatment or monitoring for the complication, code the complication. If the complication is resolved and only the original hypertension history remains, Z86.73 is appropriate as a secondary. Another edge case that burns people is family history versus personal history. Z85.7 is for family history of hypertension. Z86.73 is personal. These are not interchangeable even if a patient says their mother had high blood pressure and they used to have it too. The documentation has to support which one applies. I had a claim denied last year because the physician wrote "family and personal history of hypertension" in the notes without clarifying which was relevant to the encounter. The auditor picked family history over personal because it was listed first. Lesson learned: always push for clarification when the documentation is ambiguous, even if it means a quick call to the provider.
If you're looking for official code references, the CMS ICD-10-CM tabular list at cms.gov is the authoritative source, and the WHO's icd.who.int database has the international version. Most billing platforms also pull these from official annual updates, but those sometimes lag behind the October release dates. I keep a local copy of the current year's tabular list bookmarked because relying on automatic updates in your software has gotten me caught more than once. The limitations here are real. Z86.73 only applies when the hypertension is truly in the past. If a patient has controlled hypertension on medication, that's still active and you code I10. The word "controlled" doesn't make it historical. It's a common mistake in primary care documentation where providers write "hypertension controlled on lisinopril" and coders see "controlled" and jump to Z86.73. That's incorrect. The patient is still being treated for it. You code I10 with the appropriate seventh character if applicable, and Z86.73 has no role in that scenario. For patients with both a current diagnosis and a resolved historical component, you can sequence both I10 and Z86.73, but only if the documentation explicitly states there are two separate clinical situations. A patient who had gestational hypertension during a prior pregnancy and now has essential hypertension qualifies. A patient who simply had high readings twenty years ago and now has consistently normal readings doesn't qualify for both. The distinction matters during audits and the difference is entirely in the clinical documentation, not in what makes logical sense.
Get the Full Details

One final note on timing. ICD-10-CM codes are updated annually, usually effective October first. The Z86.73 code itself has been stable since the 2015 transition from ICD-9, but surrounding codes in the I10-I16 range shift periodically. Always verify your code set against the current fiscal year's edition before submitting high-volume claims. The audit risk from using outdated codes outweighs the five minutes it takes to check the update notices.