How To Assign ICD-10 Codes When Documenting Past Methamphetamine Use
Most coders and clinicians get tripped up on this one because the coding manual gives you two different pathways and never clearly explains when to pick one over the other. You're looking at either a Z code for personal history, or an F code if there's an active or past-with-remission diagnosis documented by the provider. The documentation has to actually support whichever direction you go, and too many people assume Z86.44 applies whenever substance use ever came up in a chart. It doesn't always. Let me walk through how this actually works in practice and what to watch out for.History Of Meth Use Icd 10
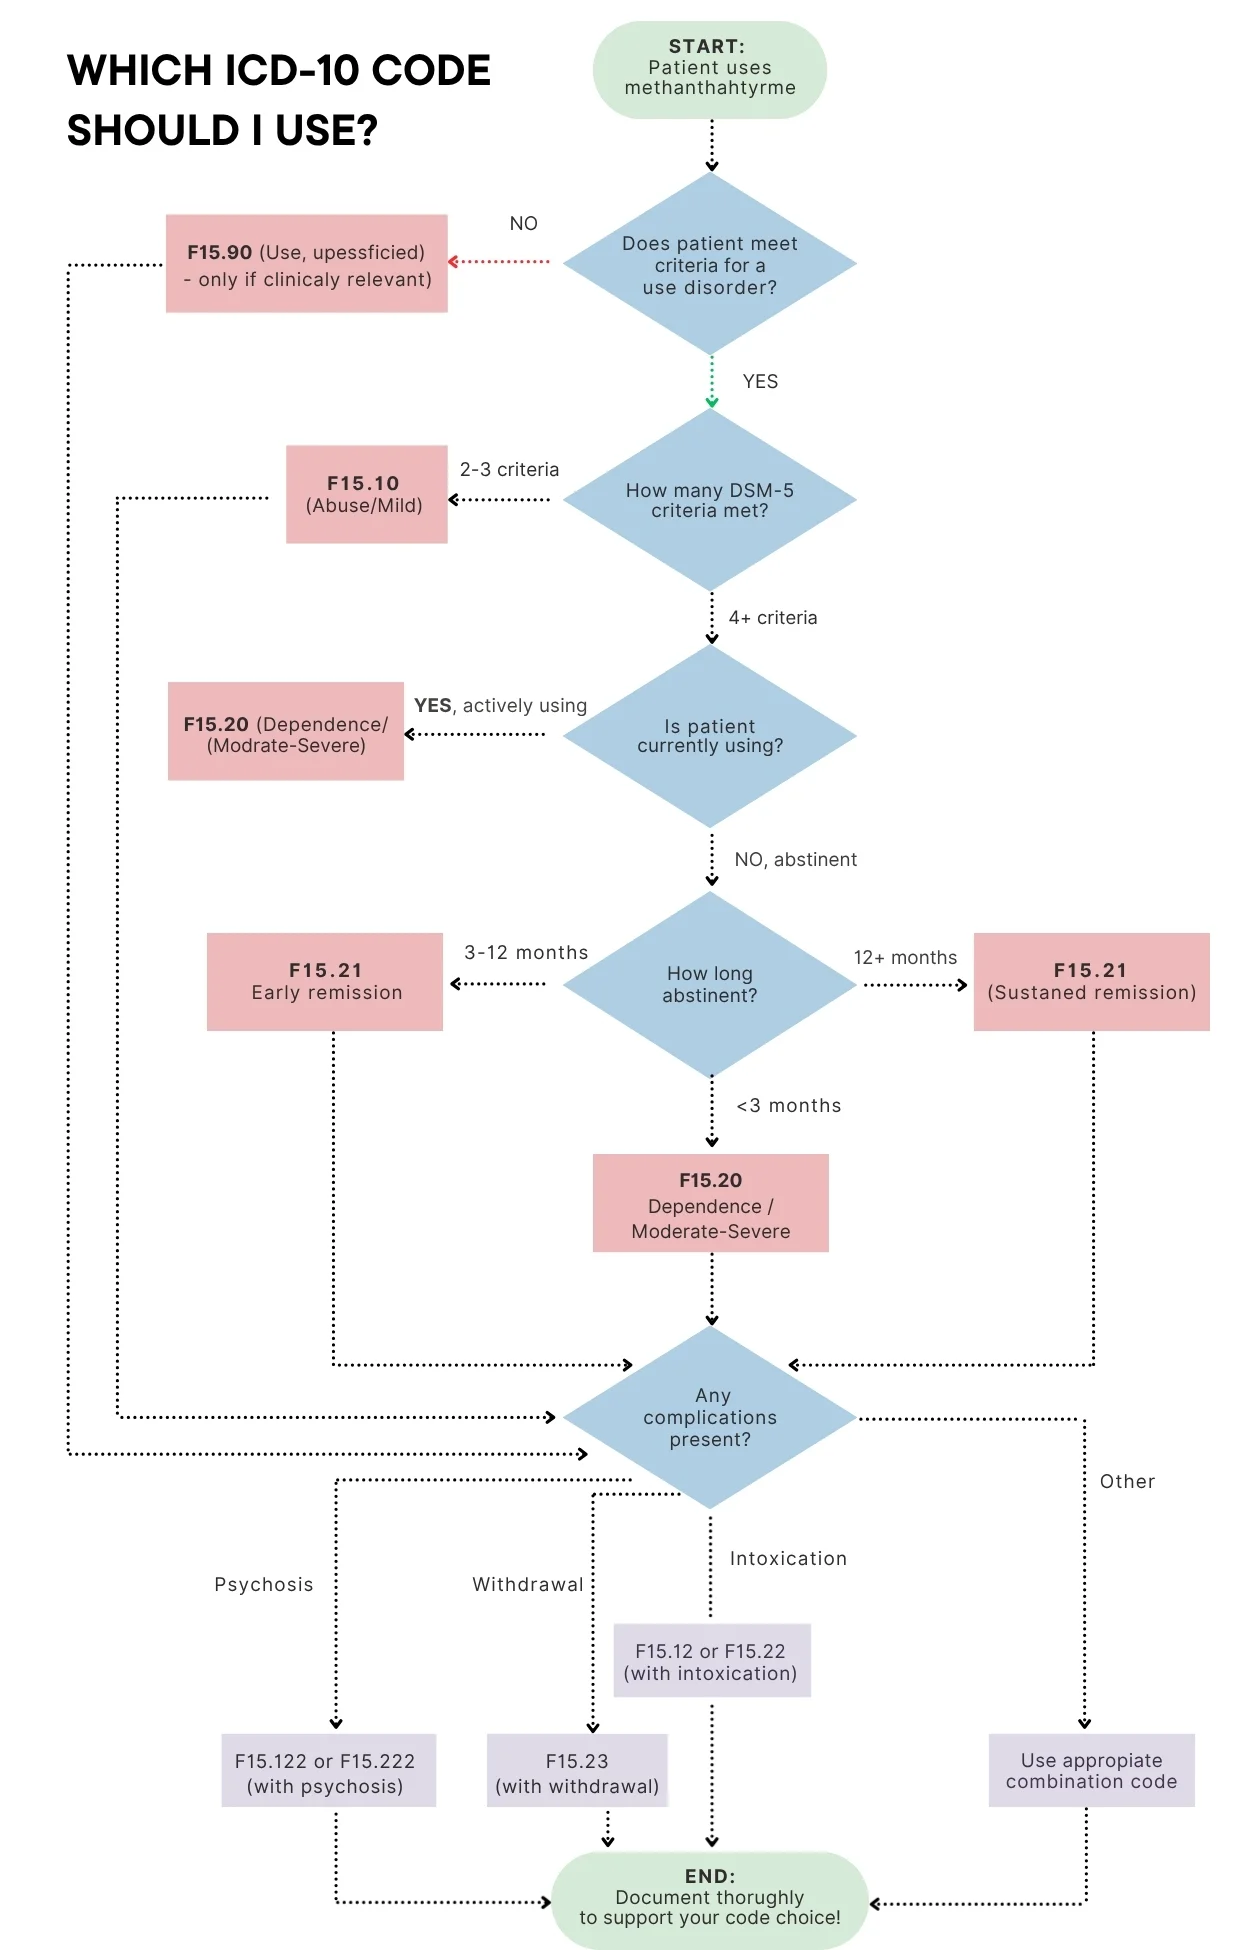
The core code you'll reach for most of the time is F15.20 for stimulant use disorder, methamphetamine, uncomplicated. That's for an active diagnosis. If the patient has a history of meth use but the provider has explicitly stated they are in remission or no longer meet criteria, the structure changes. You'd look at Z86.44, which is personal history of other psychotropic drug abuse. There's also F15.10 through F15.23 depending on whether you're documenting abuse versus dependence, and the specifier changes based on remission status. Here's where it gets messy though. The ICD-10-CM Tabular List under category F15 covers amphetamine and other stimulant use disorders, and methamphetamine falls squarely in there. The "history of" concept is handled differently depending on whether the provider documented an active disorder in the past that's now resolved, versus a distant history where the patient once used but was never formally diagnosed. Z86.44 applies to the latter scenario — history of abuse, not necessarily history of a formal diagnosis. If the chart says "history of methamphetamine abuse," that maps to Z86.44. If it says "history of methamphetamine use disorder, in sustained remission," that's F15.21. I ran into a specific problem last year that highlights why this matters. A provider documented "history of meth use, quit 3 years ago" on a routine visit. The EHR default was auto-populating F15.20 because the problem list had an old meth use diagnosis on it from years prior. I flagged it because the provider's note made clear there was no current disorder and no formal diagnosis of remission — just a vague personal history statement. The correct code was Z86.44, not an F code. When I called the provider, they'd actually meant to document a social history item for context on a mental health evaluation, not a current or remitted disorder. The initial code was wrong, and fixing it required pulling the actual encounter note rather than relying on the problem list. That's a common trap. Problem lists are backward-looking and accumulate everything ever mentioned. Encounter notes reflect what's actually being addressed that day.
Another thing that trips people up is the distinction between history of abuse and personal history of substance dependence. Z86.44 covers abuse history for drugs other than alcohol and tobacco. But if someone has a documented history of dependence specifically, some coding guidance still points toward F15 codes with the appropriate remission specifier rather than the Z code. The 2024 ICD-10-CM guidelines are a bit ambiguous here because the Alphabetic Index under History, history of, substance can lead you to different places depending on which subterm you follow. Always verify with the Tabular List and the Official Guidelines for Coding and Reporting, not just the index. The practical workflow I use is straightforward. First, confirm whether the methamphetamine use was ever formally diagnosed as a disorder. If it was, and the provider documents ongoing issues, use F15.20 with the appropriate fifth or sixth character for severity and remission status. If the provider documents the patient is in sustained remission, that's F15.21. If the documentation only mentions past use or abuse without a formal disorder diagnosis, Z86.44 is the safer bet. Then double-check that the encounter reason aligns. You shouldn't be coding a history of meth use as the primary reason for a visit about a knee injury, unless that history is directly relevant to the treatment being provided. There's a significant limitation to keep in mind. Z86.44 is a status code. It tells you something happened in the past but it doesn't capture the clinical significance. For reimbursement purposes, particularly with value-based contracts or substance use disorder quality measures, Z86.44 alone may not satisfy documentation requirements. Some payers require an F code with a remission specifier even for past diagnoses if they want to track recovery metrics. Always check your payer-specific guidance before defaulting to Z86.44 just because it seems like the simplest fit.
If you're working in an EHR and want to reduce errors, set up a conditional logic rule that forces a selection between Z86.44 and the F15 remission codes based on whether the encounter note contains keywords like "remission," "recovered," or "no longer meets criteria." Without that kind of guardrail, the system will default to whatever was last coded and you'll carry forward incorrect history codes indefinitely.
Get the Full Details