Where Nuclear Medicine Actually Started
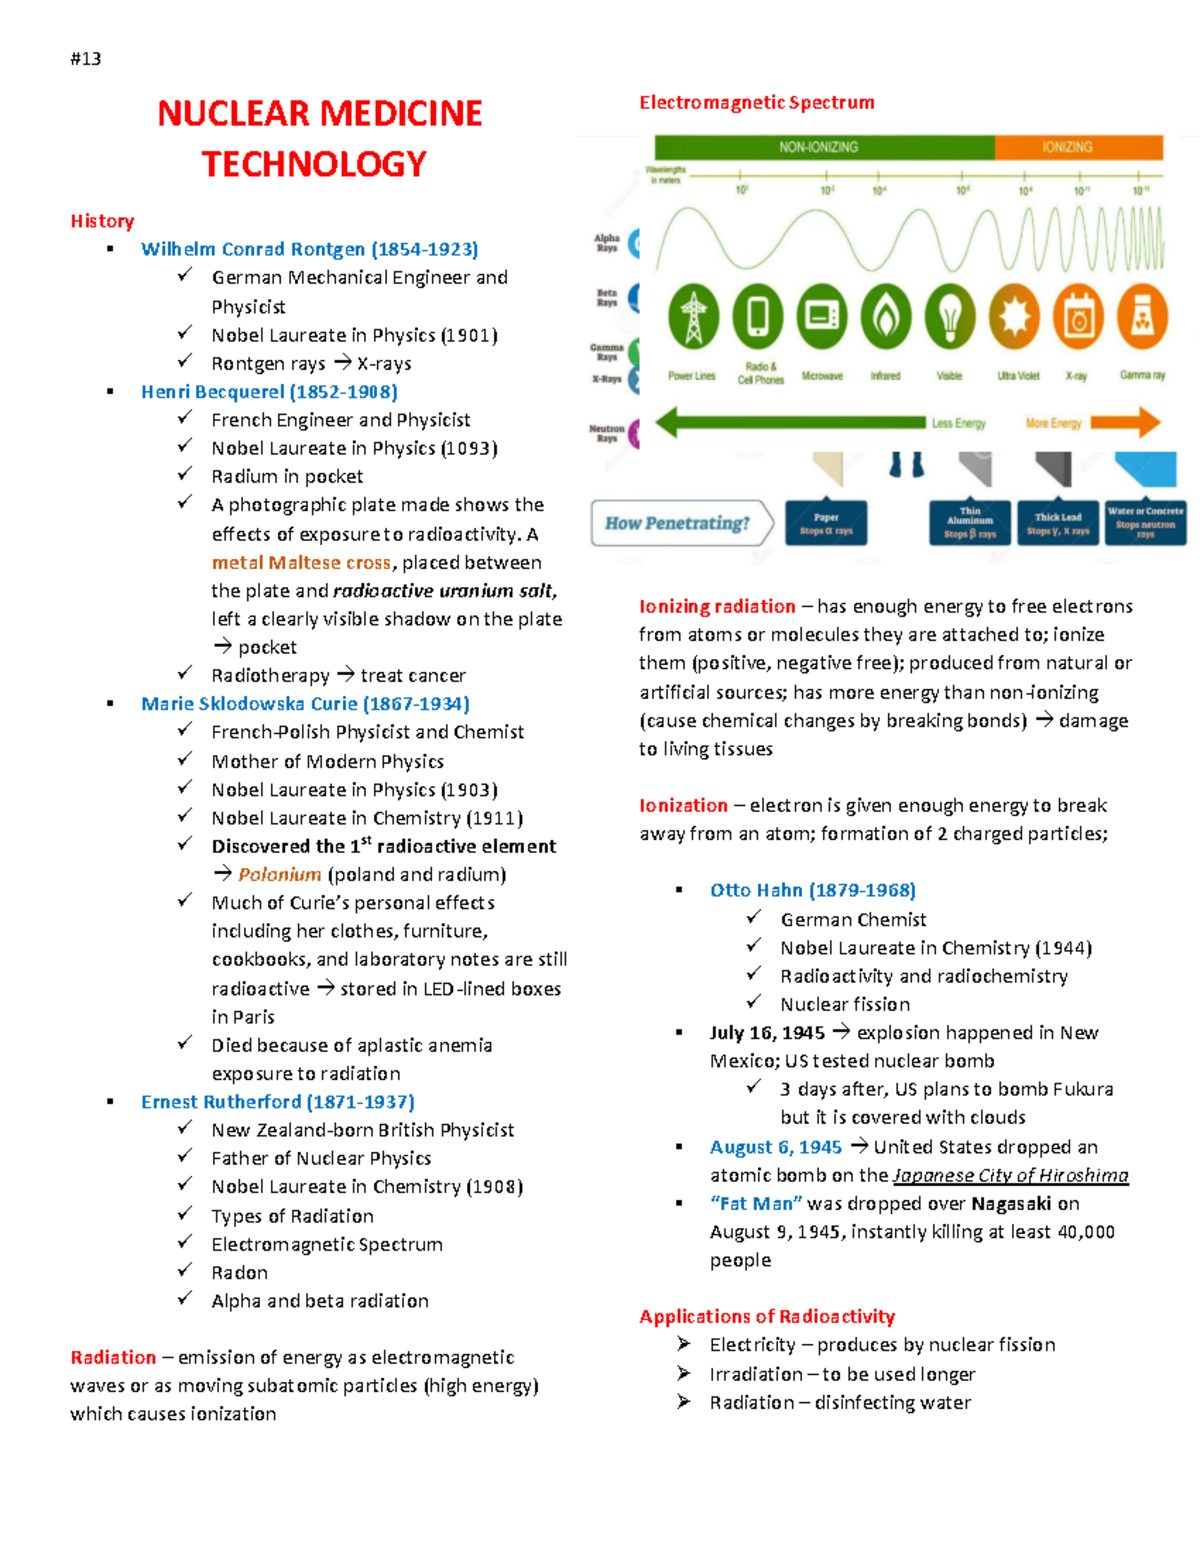
The first real use of radioactivity in medicine wasn't some dramatic breakthrough. It was basically trial and error. People noticed that radioactive materials behaved in predictable ways inside the body, and some of them figured out how to measure that from the outside. That observation period ran from around 1896 through the early 1900s, when physicists and doctors were still figuring out whether radiation was useful or just dangerous. I spent a lot of time digging through old literature on the History Of Nuclear Medicine because people often treat it like a clean progression of discoveries. It wasn't. There were dead ends, failed instruments, and researchers who pivoted hard when their funding dried up.
History Of Nuclear Medicine: The Early Instrumentation Phase
Harold Johns at the University of Saskatchewan is someone you need to know if you're actually studying this field. He built the first cobalt-60 therapy unit in the late 1940s and early 1950s. This wasn't a minor project. He was working with very crude detection equipment and had to solve shielding and collimation problems that nobody had properly documented yet. His work directly influenced how therapeutic radiology developed across North America. Meanwhile, in the United States, George de Hevesy had already shown in the 1920s that you could use radioactive tracers to follow chemical processes in living organisms. That insight is basically the foundation of everything that followed, but it took another twenty years before anyone figured out how to turn it into a practical diagnostic tool. One thing beginners consistently miss is that early nuclear medicine wasn't separate from physics research. The same people doing isotope production for weapons programs were also producing medical isotopes. The K-67 cyclotron at Berkeley, for example, made thorium-227 for clinical use in the 1950s while simultaneously supporting weapons research. That overlap created supply chain issues that still echo today whenever there's a political disruption to reactor operations.
Scintillation Cameras and the Real Shift
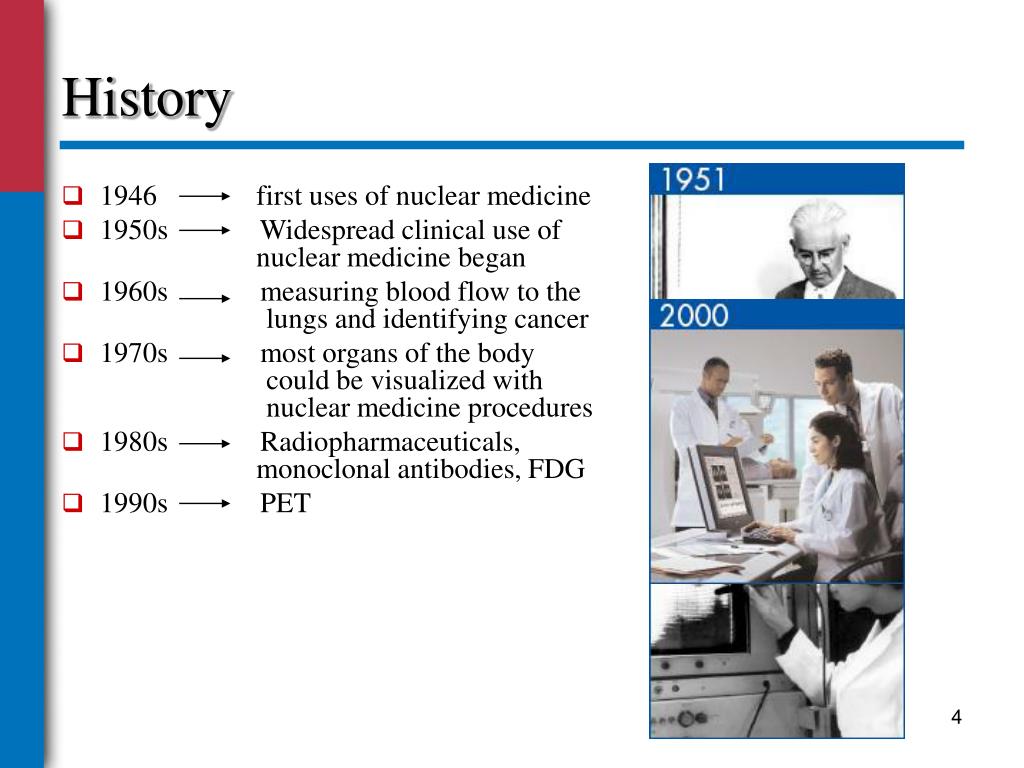
Oskar Lange and Hal Anger changed everything in 1952-1953. Anger invented the scintillation camera, which became known as the gamma camera. Before this, you were doing planar imaging with point detectors that moved slowly over the patient. You could get an image, but it took a long time and the resolution was poor. Anger's design let you capture a whole organ image at once by using a NaI crystal coupled to a bank of photomultiplier tubes. The math behind Anger logic is straightforward but easy to botch in practice. You calculate the position of a scintillation event by comparing the relative signal strength across all the PMTs. The formula itself isn't the hard part. Getting uniform response across the entire crystal surface is what takes months of adjustment. I once calibrated a duplicate gamma camera that had been sitting in storage for three years. The manufacturer's acceptance test procedure assumed you'd never opened the collimator housing. In reality, every time you touch that housing you shift the distance between collimator and crystal by fractions of a millimeter, which throws off spatial linearity. The workaround was to run a full uniformity correction using a flood source, then verify linearity with a bar phantom, and finally re-zero the PMT voltages one channel at a time while watching the center-of-gravity output on the oscilloscope. It took about four hours. The factory manual estimated two days.
Get the Full Details

Radiopharmaceutical Development
Technetium-99m arrived in 1958 and solved a practical problem that had been limiting the field. Previous isotopes either decayed too slowly, emitted the wrong energy, or required a particle accelerator to produce. Tc-99m has a 6-hour half-life, emits a 140 keV photon that's ideal for detection, and comes from a molybdenum-99 generator that can be shipped to hospitals. This changed nuclear medicine from a research discipline to a clinical one almost overnight. The generator system itself is a piece of engineering you don't see discussed enough. The Mo-99 adsorbs to alumina in a column, and Tc-99m elutes with saline. But the breakthrough wasn't just the physics. It was figuring out that you could ship the parent isotope and have it continuously produce the daughter on-site. Before generators, you needed a cyclotron next door to your hospital. That limited nuclear medicine to maybe a dozen centers worldwide. There's a common misconception that Tc-99m replaced all other tracers. It didn't. F-18 for PET, I-131 for thyroid therapy, and In-111 for white blood cell labeling all filled specific niches. Each one has different production requirements, different biological behavior, and different regulatory pathways. The History Of Nuclear Medicine is really the history of building a toolkit, not finding a single magic isotope.
PET and the Second Revolution
Positron emission tomography started as a physics experiment. Peter Morrison and Ed Zanzonigos at Brookhaven built the first human PET scanner in the early 1970s using BGO crystals. The first clinical application was measuring cerebral glucose metabolism with F-18 FDG. This wasn't an immediate success. The scanners were enormous, the sensitivity was terrible compared to modern systems, and reconstruction algorithms took hours on mainframe computers. What actually drove PET forward was the development of better radiopharmaceuticals combined with faster electronics. LSO and LuAG crystals in the 1990s improved timing resolution enough to make coincidence detection practical without massive shielding. That's when PET went from research instrument to clinical tool, and it happened faster than most textbooks suggest because the timeline compresses years of incremental hardware improvements into a single narrative.
SPECT Advances and Hybrid Imaging
SPECT is often treated as the older, inferior cousin of PET. That's not accurate. SPECT has different advantages. It can use a wider range of isotopes, it's cheaper to operate, and newer systems with solid-state CZT detectors have closed the sensitivity gap significantly. The History Of Nuclear Medicine includes both modalities running in parallel, each solving different clinical problems. Hybrid imaging, specifically SPECT/CT and PET/CT, addressed one of the fundamental limitations of nuclear medicine. Functional images have poor anatomical localization. Adding a CT scan lets you overlay metabolic activity on actual anatomy. This isn't just convenience. It changes diagnostic confidence substantially. Studies show that hybrid imaging reduces indeterminate findings by roughly 30 percent in oncology applications. One practical issue people run into with hybrid systems is attenuation correction. The CT scan provides the attenuation map, but if the patient moves between the PET and CT acquisitions, the correction becomes inaccurate. I worked with a site that had a recurring problem where pediatric patients couldn't hold still long enough for both scans. Their solution was to use a low-dose CT scout view for attenuation correction rather than a full diagnostic CT, which cut the total exam time from about 45 minutes to 20 minutes while maintaining acceptable image quality for most clinical indications.

Regulatory and Safety Evolution
Nuclear medicine has always operated under tighter regulatory constraints than most medical specialties because you're handling radioactive materials. The NRC in the United States, the IAEA internationally, and equivalent bodies elsewhere have shaped how the field practices. Early on, dose limits were poorly defined. Some procedures that would be unacceptable today were performed routinely in the 1950s and 60s simply because nobody had established baseline safety data. The shift toward ALARA principles in the 1970s changed practice fundamentally. It wasn't just about lowering patient dose. It affected how isotopes were stored, how waste was handled, and how staff were monitored. The practical impact was that nuclear medicine departments needed licensed health physicists, whereas before they might have had a part-time radiation safety officer who was also the lab technician. A counter-intuitive point about dose: lower administered activity doesn't always mean better imaging. With modern cameras, you can sometimes get diagnostic quality images with significantly reduced counts, but the relationship isn't linear. Below a certain threshold, noise dominates and you lose the ability to distinguish pathology from artifact. The optimal dose depends on patient size, camera sensitivity, and the specific clinical question. blanket dose reduction policies without considering these variables can actually worsen diagnostic accuracy.
Current State and Where It's Heading
Theranostics is the current major trend. This means using matching pairs of diagnostic and therapeutic isotopes for the same biological target. Lu-177 PSMA for prostate cancer and I-131 for thyroid disorders are established examples. The concept is older than most people realize. The systematic approach to pairing isotopes emerged in the 2010s, but the principle of targeted radionuclide therapy dates back to the 1940s with I-131 for hyperthyroidism. The main bottleneck right now is isotope supply. Mo-99 production remains concentrated in a small number of reactors worldwide. When one shuts down for maintenance, the global supply tightens and procedures get delayed. This isn't a hypothetical problem. It happens periodically and affects scheduling in hospitals that don't maintain their own isotope reserves. New delivery systems like Ac-225 and Tb-161 are expanding the therapeutic range. Alpha emitters in particular offer higher linear energy transfer, which means more damage per decay but shorter range in tissue. This is promising for micrometastatic disease but requires different handling and quality control procedures than beta emitters. The regulatory framework hasn't fully caught up with these newer isotopes, which creates uncertainty for clinical programs trying to adopt them.
The field has come a long way from point detectors and manual chart recording. Modern systems integrate digital reconstruction, automated dose calculation, and structured reporting. But the core principle hasn't changed: introduce a tracer, measure where it goes, infer what's happening physiologically. Everything else is engineering optimization around that basic idea.