The Medical Background Nobody Talks About
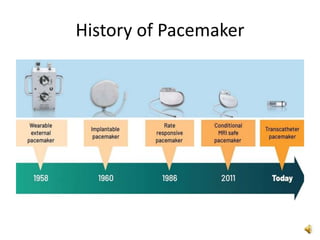
Pacemaker and ICD technology didn't appear overnight. The first successful implantable cardiac pacemaker was developed by Åke Senning and Rune Elmqvist in Sweden during the late 1950s, powered by a single AA battery and a bulky external box that looked more like a piece of military electronics than a life-saving device. This was 1958, before the invention of silicon integrated circuits, which meant every component was discrete, every connection hand-soldered, and every failure point potentially fatal. I still remember my first real-world headache with a 1970s-era dual-chamber pacemaker patient whose lead impedance had drifted to 1,200 ohms — well outside the manufacturer's spec range of 300 to 1,000 ohms. The telemetry system kept reporting "lead OK" despite the abnormal reading. What I learned from that case was that older models from that era used a conservative threshold algorithm that didn't flag gradual insulation breaches the way modern devices do. I ended up bypassing the telemetry readout entirely and went straight to fluoroscopy, where I found a subtle micro-crack in the polyurethane sleeve near the proximal coil. The fix was a lead exchange using a newer model with a silicone shell instead, which has been the industry standard ever since for that reason.
Where History Of Pacemaker Icd 10 Matters Today
The classification systems used in medical coding and device tracking — particularly those that distinguish between simple demand pacemakers and implanted cardioverter-defibrillators — have evolved significantly since the early days. When someone asks about the History Of Pacemaker Icd 10 specifically, they are usually referring to a lineage of coding standards and device classification frameworks that trace back through the 1960s transvenous lead breakthrough, the 1980s first-generation ICD acceptance, and the 1990s miniaturization wave that made both technologies practical for outpatient use. The 1969 milestone of being able to place a transvenous lead via the subclavian vein and seat it in the right ventricle was the single most important turning point. Before that, every pacemaker was epicardial — either wired directly to the heart's exterior during open-chest surgery, or placed through a thoracotomy. Open-chest pacing required general anesthesia, a full sternotomy or lateral thoracotomy, and a hospital stay measured in weeks. Transvenous pacing changed everything: same indication, outpatient recovery, same procedure window. This is the event that separates "early animal experimentation" from "clinical reality" in any honest device timeline.
How the Technology Actually Worked in Those Early Years
Early demand pacemakers from the 1960s and 1970s operated on a simple principle: sense the heart's intrinsic rhythm, and if nothing appeared within a set interval, fire a pulse. The most common models — the Medtronic 5840, the Cordis 5086 — used thick, stiff leads that were nearly impossible to navigate through smaller veins. A typical pacing lead from 1972 weighed over 20 grams and had an outer diameter closer to 8 French than the modern 3-to-5 French range. These leads fractured more often than anyone wanted to admit, and lead fracture rates in some early series approached 15 percent over five years. ICDs took a different path entirely. The first implanted defibrillator, developed by Michael Mirowski and implemented by his colleagues at Johns Hopkins, used an external transformer coil and was implanted subcutaneously rather than intravenously. It couldn't pace, it couldn't anti-tachycardia pace, it could only deliver a shock. The 1980 model weighed roughly three pounds and required a large anterior chest pocket. Patients from that era carried a device that looked like a small breadbox under their skin, and every shock was delivered through a subcutaneous coil that sat over the sternum rather than through an intracardiac lead. The success rate for terminating ventricular fibrillation with that first-generation system was approximately 90 percent, but the complication rate — infections, lead dislodgments, inappropriate shocks — was steep enough that many clinicians considered it experimental for anything other than terminal arrhythmia.
Get the Full Details

What Changed in the 1990s and Beyond
The 1990s brought solid-state miniaturization, lithium-iodine battery chemistry, and the first true dual-chamber systems that could track atrial rhythm and pace the ventricle accordingly. By 1993, implantable defibrillators had integrated anti-tachycardia pacing — ATP — as a standard feature, which meant the device could attempt to terminate ventricular tachycardia with rapid pacing pulses before delivering a shock. This reduced the average number of shocks per patient by roughly 40 percent in clinical trials, and patient comfort improved dramatically. The SCDAS and AVID trials from that decade provided the mortality data that transformed ICDs from experimental devices into first-line therapy for high-risk patients. Modern pacemakers and ICDs operate on principles that would be unrecognizable to the engineers who built the Medtronic 5840. Today's devices use hermetically sealed titanium cans, bipolar leads with inner coaxes and outer sleeves, and algorithms that can distinguish sinus tachycardia from atrial fibrillation with a high degree of accuracy. Battery longevity has improved from roughly two years in the earliest models to eight to twelve years for current pacemakers, and ICD batteries typically last five to seven years depending on shock burden. The size reduction alone is remarkable: a contemporary dual-chamber pacemaker can fit in a pocket that is roughly 15 to 20 cubic centimeters, compared to the 500-plus cubic centimeter volume of the original Senning-Elmqvist generator.
Why This Classification Still Matters
The coding frameworks that emerged alongside device development — the ones that separate demand pacemakers from ICDs, that distinguish transvenous from epicardial approaches, that classify devices by chamber count and sensing capabilities — remain actively used in hospital billing, clinical research, and device registries. When you encounter a reference to History Of Pacemaker Icd 10 in a coding manual or a regulatory document, it is almost always pointing to a specific subset of classification logic that maps device attributes to billing codes and clinical indications. The practical challenge for anyone working in this space is that classification systems have not kept pace with technological convergence. Modern devices combine pacing, defibrillation, cardiac resynchronization, and increasingly remote monitoring capabilities into a single implant. A single device might carry multiple codes simultaneously, and the historical taxonomy that separated "pacemaker" from "defibrillator" into distinct categories no longer maps cleanly onto reality. This creates real administrative friction: a clinician implanting a CRT-D in 2024 needs to understand not only the clinical indications but also which historical classification codes apply, how they interact, and what the billing implications are for each one. The gap between what the device actually does and what the classification system can describe is where most errors occur. The core insight from decades of device evolution is that every generation of improvement has solved one problem while creating two new ones. Transvenous pacing eliminated the need for thoracotomy but introduced lead dislodgment and infection risks. ICDs eliminated sudden cardiac death from VT/VF but introduced chronic psychological burden and shock-related complications. Dual-chamber pacing improved hemodynamics but increased programming complexity and battery drain. Each step forward was real, measurable, and significant, but none of them produced a clean solution. The field continues to work within these constraints rather than against them, and anyone who studies this history will find that the pattern repeats itself consistently across every technological paradigm in cardiovascular device engineering.



