ICD-10 Coding for Parkinson's Disease: What the Manuals Won't Tell You
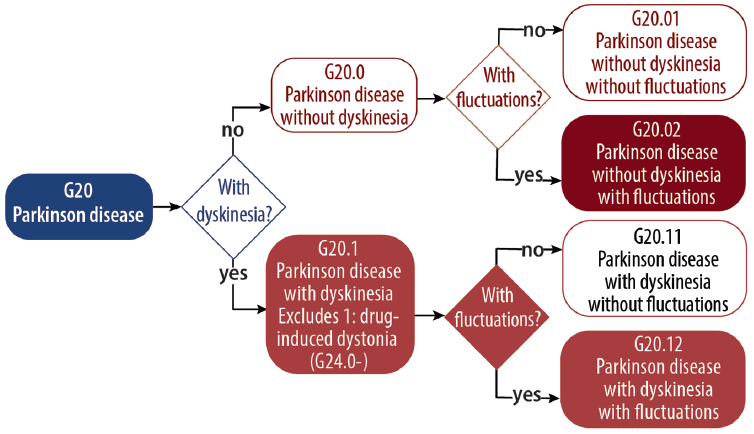
The ICD-10-CM code for Parkinson's disease is G20. That's the starting point and honestly where most people stop. It gets assigned when a patient has active, ongoing Parkinson's. But the coding gets messier the moment you start looking at history, secondary causes, and complications. I've spent years doing coding audits for neurology practices and the number one error isn't picking G20 wrong. It's misusing the Z codes for personal history and then piling on secondary parkinsonism codes that don't actually apply. If a patient had Parkinson's disease in the past and it's now resolved or they're no longer being treated for it, you code Z86.69 — Personal history of other diseases of the nervous system. This includes past Parkinson's. The critical detail here is that G20 drops out entirely. You don't keep G20 as a secondary code alongside Z86.69 just because the patient "has a history of it." That's a denial trigger. Payers will flag it as an active disease code being billed with a history code simultaneously. I ran into this exact problem last year during a routine audit. A neurology clinic was billing G20 alongside Z86.69 for a patient who'd been off Parkinson's medications for three years after a deep brain stimulation evaluation that never went forward. The chart note said "history of Parkinson's" in the assessment section but the attending had left G20 on the problem list as an active diagnosis. The claim got denied twice before we caught it. The workaround was straightforward: remove G20 from the active problem list, update the HPI to reflect the resolved status with a clear note about medication discontinuation, and bill only Z86.69. But the real lesson was fixing the workflow so problem lists auto-expire when a diagnosis is marked resolved in the EHR.
Secondary and Symptomatic Parkinsonism Codes
G20 is specifically for idiopathic Parkinson's disease. If the parkinsonism is caused by something else, G20 is wrong. Here are the codes that actually come up in practice: G21.0 — Malignant neuroleptic syndrome. This comes up when a patient on antipsychotics develops acute parkinsonian symptoms with autonomic instability. It's not chronic Parkinson's. It's drug-induced and it's coded separately. G21.1 — Other drug-induced parkinsonism. This is probably the most commonly misused code in outpatient neurology. Any patient developing tremor or bradykinesia after starting metoclopramide, prochlorperazine, or a typical antipsychotic goes here. The key is documenting the causative agent. Without that in the chart, auditors will assume you meant G20 and deny it.
G21.2 — Secondary parkinsonism due to other extrapyramidal and movement disorders. This is the catch-all for post-encephalitic parkinsonism, drug-induced parkinsonism not elsewhere classified, and certain vascular presentations. It's vague by design, which means it's also vague in audit reviews. If you use G21.2, make sure the provider documented the specific underlying cause in the notes. G21.3 — Progressive supranuclear palsy. This used to get misdiagnosed as Parkinson's for years. It's now a distinct code and should be coded as such when the clinical features — vertical gaze palsy, early falls, axial rigidity — are documented. G21.4 — Vascular parkinsonism. This is the one that causes the most reimbursement friction. Many payers expect a separate code for the cerebrovascular disease (I67.89 or whatever applies) alongside G21.4. If you only code G21.4 without the vascular etiology, the claim looks incomplete. I've seen denial rates climb to 18% on these cases when the vascular component wasn't separately coded.
Get the Full Details
Complications and Associated Codes
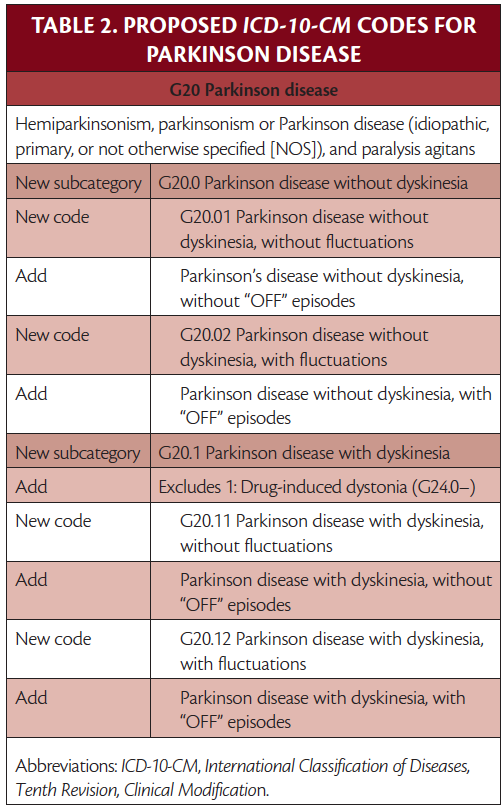
Parkinson's patients almost always have comorbidities that need coding attention. R26.2 — Difficulty in walking, is almost universal for moderate to advanced cases and should be paired with G20. R25.1 — Athetosis, and R25.2 — Cramps and spasms show up when dyskinesia is present, usually as a side effect of levodopa treatment over time. F03.90 — Unspecified dementia, is increasingly appearing alongside G20 as disease duration increases. The 2023 ICD-10-CM guidelines say to code dementia associated with Parkinson's when documented. That's G20 plus F02.1 — Dementia in Parkinson's disease. F02.1 is the specific code and it takes priority over F03.90. I see F03.90 used far too often when the documentation clearly supports F02.1. For medication management complications, G97.1 — Drug-induced extrapyramidal side effects, sometimes gets used interchangeably with G21.1. They're not the same. G97.1 is for extrapyramidal side effects from medications other than those used to treat Parkinson's itself. If a patient on carbidopa-levodopa develops dyskinesia, that's an expected complication of the disease and treatment, not a separate G97.1 code. But if they're on an antiemetic and develop parkinsonism, G21.1 or G97.1 becomes relevant.
What Most Coders Get Wrong
The biggest issue I see is combining G20 with Z79.40 — Long-term (current) use of levodopa preparation. These can absolutely be coded together. Levodopa use is a status code and G20 is the active diagnosis. There's no conflict. The problem comes when G20 is used for a patient who's only been on a dopamine agonist like pramipexole. Z79.40 is specifically for levodopa. Using it for other Parkinson's medications is incorrect. The proper code for other long-term medications would be Z79.899 — Other long-term (current) drug therapy. Another common mistake: assigning G20 when the documentation only says "parkinsonism" or "parkinsonian syndrome" without specifying idiopathic. Parkisonism is a symptom complex. Without the provider clarifying it as idiopathic Parkinson's, the appropriate code is G21.9 — Secondary parkinsonism, unspecified. G20 requires the specificity of "Parkinson's disease" in the documentation. I had a case where a hospitalist documented "rule out Parkinson's" in the admission notes and the coding team assigned G20. The claim was flagged because rule out diagnoses don't support G20 assignment. The final diagnosis after workup was drug-induced parkinsonism, which should have been G21.1 from the start.
Practical Workflow Tips
If you're building a coding review process for Parkinson's cases, start with the problem list in the EHR. Check that G20 is only active when the patient is currently being treated. Then verify the medication list aligns — levodopa users get Z79.40, other Dopamine agonists get Z79.899. Cross-reference the assessment section for any dementia documentation. If F02.1 applies, make sure it's not buried in a notes section that the coder missed. For inpatient settings, the principal diagnosis should be G20 when Parkinson's is the reason for admission or a major factor in the stay. If the admission is for something else entirely — say, a hip fracture in a patient with well-controlled Parkinson's — G20 becomes a secondary diagnosis. But if the admission is for Parkinson's-related complications like severe dyskinesia or medication adjustment, G20 stays principal. The distinction matters for DRG assignment and reimbursement. ICD-10-CM official guidelines for the current fiscal year are available on the CDC website. The specific section on nervous system diseases and neoplasms covers the G20-G26 range in detail. I keep a printed copy in my office because the online version updates more often than the annual PDF release and the changes matter for compliance.