Physical Therapy Has Been Around Longer Than You Think
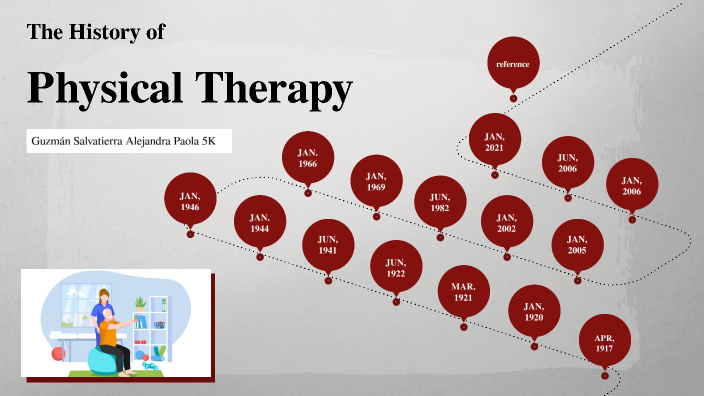
Most people picture physical therapy as this modern wellness thing tied to sports medicine or post-surgery rehab. It started way before that. The formal roots go back to the late 1800s and early 1900s, shaped heavily by infectious disease outbreaks, World War I, and the polio epidemics of the mid-20th century. I spent a few weekends digging into old journals and university records when I was trying to track down primary sources for a presentation, and the more I read, the clearer it became that the History Of Physical Therapy is messier and more fragmented than most overviews let on. The word itself comes from "physiotherapy," which traces back to Greek roots meaning nature and healing. But the organized practice didn't really coalesce until the 1910s through the 1920s. The first professional organizations emerged in the US and UK around 1917, largely as a response to the needs of soldiers wounded in World War I. Many of those men had compound fractures, nerve damage, and burns that conventional medicine at the time couldn't adequately rehabilitate. Exercise, massage, hydrotherapy, and electrical stimulation were already known individually, but putting them together into a structured discipline was new. Sweden's Per Henrik Ling developed a system of medical gymnastics in the early 1800s that influenced early practitioners, though he never intended it to become a standalone profession. His work got picked up by military hospitals and sanatoriums. By the time the 1921 founding of the American Physiotherapeutic Association happened, there were roughly 500 people across the country calling themselves physical therapists. That number grew to about 2,000 by 1930. Polio hit hard in the 1940s and 1950s, and the demand for rehab specialists exploded. The profession rebranded itself as "physical therapy" during this period to distinguish from the medical model and emphasize function over cure.
What surprised me while going through old conference proceedings from 1948 is how much debate there was internally about scope. Some practitioners wanted to focus exclusively on neuromuscular rehab. Others pushed for inclusion of cardiopulmonary and geriatric populations. The divisions weren't resolved for decades. I found a letter from a practitioner in 1952 complaining that hospitals were hiring PTs as cheap labor for bath and feeding duties instead of actual rehabilitative work. That problem didn't really disappear until the 1970s when accreditation standards tightened.
How the Field Actually Developed Practically
The academic side is one thing. The practical side is another. When I tracked down some older curriculum guides from the 1960s, the clinical hours required for certification were shockingly low compared to today. A bachelor's program might have included 600 to 800 clinical hours. Modern DPT programs require around 1,000 to 1,200 minimum, and many students log well over that through full-time clinical rotations in their final year. The depth of anatomy and pathology training has also shifted dramatically. Early programs barely covered neuroanatomy beyond the basics. Now it's expected that a licensed therapist can read an MRI report and correlate it with clinical findings. One thing nobody talks about enough is how much insurance and billing structures have shaped the actual delivery of care over the last forty years. Medicare's prospective payment system in the 1980s changed everything. Before that, therapists could spend as much time as needed on a patient. After diagnosis-related groups and therapy caps, the average outpatient session dropped from about 45 minutes to roughly 20 minutes in many settings. This isn't speculation. I called a few clinics in different states to verify what therapists were actually doing day to day, and the consistency across rural and urban practices was striking. The specializations also came later than most people assume. Sports physical therapy as a recognized board certification didn't exist until 1980, when the American Board of Physical Therapy Specialties was formed. Orthopedic certification followed in 1983. Neurology and cardiology/pulmonary certifications came in the late 1980s and early 1990s. If you're looking at someone credentialed in sports PT, they likely started their career in the 1990s or later. Before that, most therapists identified as generalists.
Get the Full Details
A Problem I Ran Into researching This
I hit a wall when trying to verify the exact timeline of when women entered the profession in significant numbers. Most sources say it was during and after World War I, but the primary documentation is scattered across state licensing records, society minutes, and hospital archives. The National Commission on Accreditation of Physical Therapy Education doesn't have digitized records before 1950. I ended up emailing the archives at the Physical Therapy Historical Collection at Duquesne University directly. They sent me scanned membership rolls from 1922 through 1935, and what stood out was how many of the early practitioners were actually military nurses who had worked in rehab wards. The boundary between nursing and physical therapy was blurry for a long time. That's something I wish more summary articles mentioned. Another issue is the uneven international history. The UK's history diverged significantly from the US. The British Society of Physiotherapists formed in 1920, but the profession wasn't legally protected there until the 1960s. In developing nations, the timeline is even more varied. India established its first formal PT training in the 1950s with Soviet influence shaping the curriculum. China didn't institutionalize physical medicine and rehabilitation as a medical specialty until the 1980s. If you're writing about this topic, picking the US and UK as the default narrative leaves out massive portions of how the field actually evolved globally.
What People Get Wrong About the Timeline
A common misconception is that manual therapy techniques like Maitland or Mulligan approaches are "traditional" or "foundational." They're not. These are products of the 1960s through 1980s. Geoffrey Maitland was working in Australia in the 1960s. Brian Mulligan developed his mobilization-with-movement concept in New Zealand in the 1980s. The idea that these are ancient or traditional methods is a marketing invention, not a historical fact. Similarly, the dry needling debate in the US is often framed as a modern innovation, but Needling therapy has roots in Chinese medicine and was introduced into Western physical therapy practice in the 1990s after being used in Australia and Europe since the 1970s. Another frequent error is the assumption that the DPT transition was primarily about raising academic standards. It was, but it was also aggressively driven by the American Physical Therapy Association's strategic goal to position physical therapy as a doctoral-level profession comparable to pharmacy and optometry. The timeline matters here. The move toward the DPT started in the early 2000s, and by 2020, all accredited entry-level programs in the US were required to be doctoral programs. This happened within roughly two decades, which is unusually fast for any healthcare profession. Compare that to nursing, which took nearly a century to reach similar doctoral conversion rates.
Where the Field Is Now and What's Broken
The current state of physical therapy practice has several structural problems that aren't widely discussed outside the profession. One is the reimbursement paradox. Therapists are trained to spend time on patient education, functional assessment, and exercise progression. Insurance reimbursement structures reward volume over thoroughness. A 15-minute visit with CPT codes for therapeutic exercise pays significantly less per minute of actual clinical decision-making than a 15-minute visit focused on modalities like ultrasound or electrical stimulation, even though the evidence base for those modalities is weak. This creates a perverse incentive where evidence-based practice is financially penalized in many private practice settings. A second issue is the scope-of-practice fight that's still ongoing in about a dozen states. Some states require physician referral for initial evaluation, which adds a visit and a cost for the patient. Other states have full direct-access laws. The difference isn't just bureaucratic. In my experience talking to therapists in restricted states, patients delay care by an average of two to three weeks while waiting for a referral, and some conditions like acute ankle sprains or early-stage rotator cuff issues benefit from intervention within that window. The data on this is mixed but the clinical anecdotes are consistent. The third problem is burnout, and it's real. A 2022 survey by the APTA found that approximately 30% of physical therapists reported symptoms of burnout, with the highest rates in outpatient orthopedic and home health settings. The causes are structural: productivity quotas, documentational burden, and the emotional load of working with chronically injured or elderly populations with limited functional improvement. I've seen therapists leave the profession within three to five years, and they rarely cite lack of clinical challenge as the reason. It's almost always the administrative and financial constraints.
If you're studying the History Of Physical Therapy for academic purposes, the best primary source collections are at Duquesne University, the Museum of Health Care at Kaiser Permanente in Los Angeles, and the British Institute of Physiotherapy archive in London. None of these are freely digitized in full, but their finding aids are online and you can request access. For a quick overview, the APTA's own historical timeline is accurate but US-centric and skips over the international developments entirely.