The Cochlear Implant Isn't What Most People Think It Is
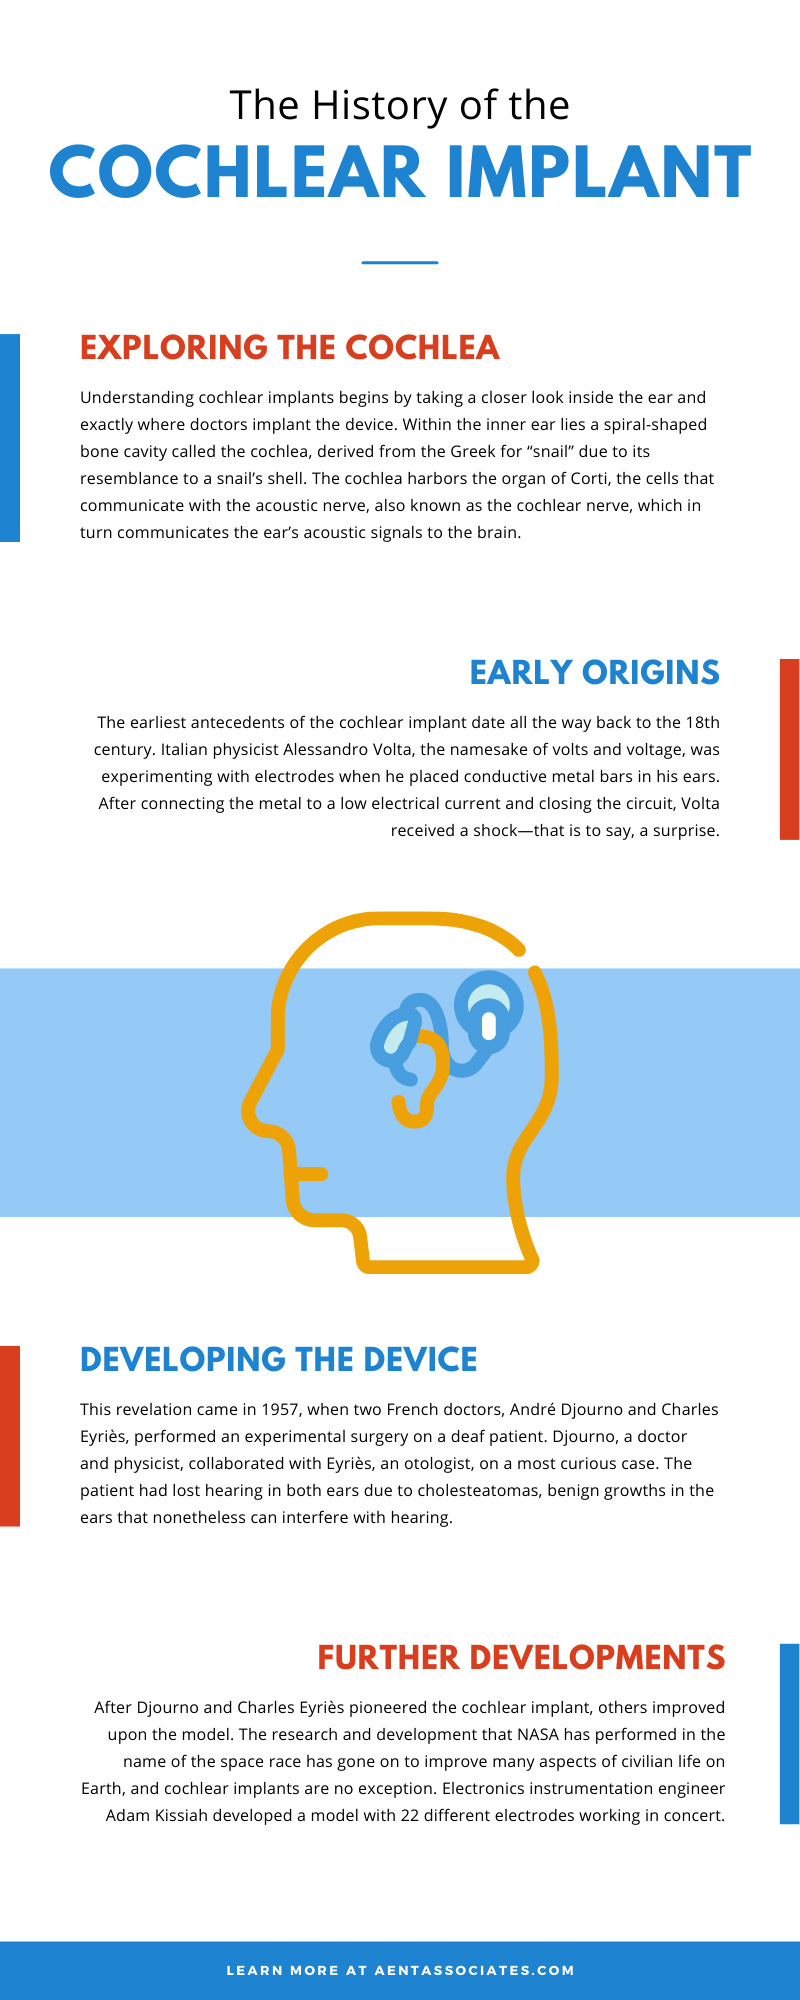
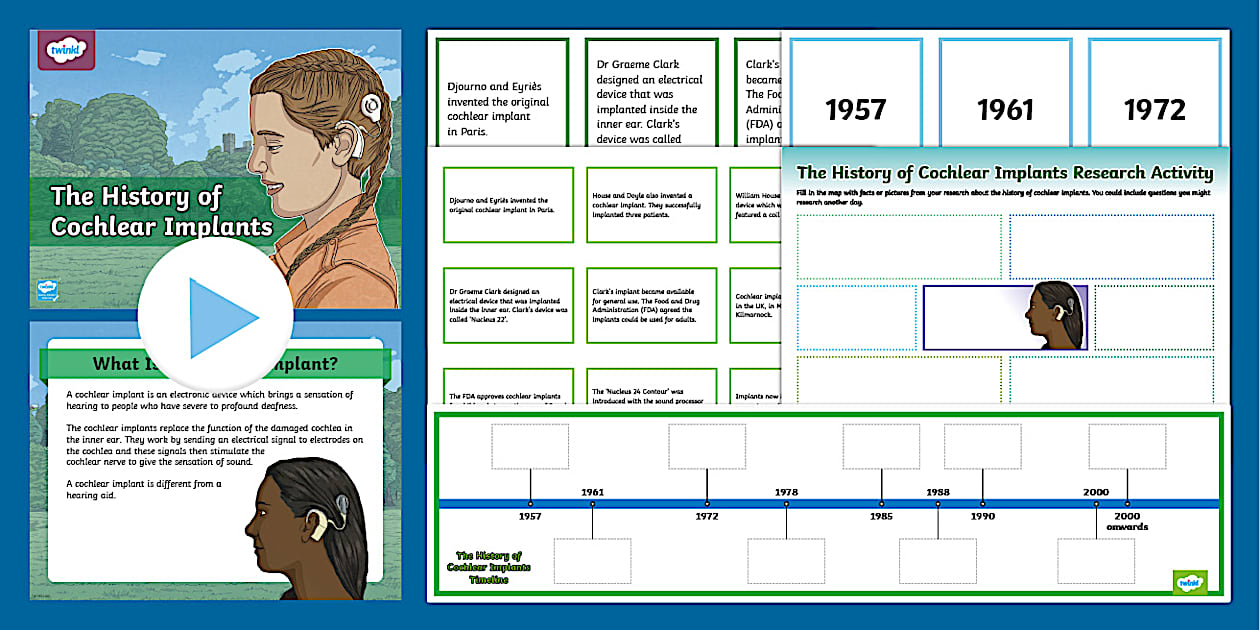
Most people assume the cochlear implant was some overnight breakthrough, a perfect solution that just appeared in the 1970s and immediately worked for everyone. That is not how any of this happened. The history is messy, filled with failed experiments, government dead-ends, and people who spent decades getting sued into submission before anything resembling a modern device ever reached a patient. The actual History Of The Cochlear Implant traces back much further than most summaries acknowledge. The earliest real attempts at electrical stimulation of the auditory nerve date to the 1950s and 60s, when researchers like William F. House in Los Angeles and Charles eyriès in France started experimenting with single-electrode implants. House's work in particular produced what we might call the first truly practical cochlear implant, though calling it "practical" is generous by modern standards. The device required a enormous external processor, the electrodes were crude, and the results varied wildly from patient to patient. Some gained enough hearing to understand speech with lip-reading. Others got nothing meaningful out of it at all. The University of Utah team, led by John C. (Jack) Ryan, ran parallel experiments around the same time and actually ended up with slightly better outcomes in certain metrics because they used a different electrode placement strategy. That detail matters more than textbooks usually let on. The debate over intracochlear versus extracochlear electrode placement is still actively discussed in clinical circles today, even though most modern implants use intracochlear arrays now. The Utah team's approach of placing electrodes through the round window rather than drilling into the scala tympani directly influenced a lot of later design choices, and it is worth noting that their early patients often had more variable results precisely because the electrode contact with the nerve wasn't as consistent.
The real turning point came in the late 1970s with the multichannel approach. Blake Servine and his colleagues at the House Clinic realized that stimulating different regions of the cochlea separately produced dramatically better speech recognition than a single electrode ever could. This was not a gentle evolution. It involved a lot of trial and error, several patent disputes that dragged through federal court, and regulatory hurdles that nearly killed the whole project before it really got going. The FDA finally granted approval for the multi-channel implant in 1984, but only after a rigorous protocol that limited the study to post-lingually deafened adults who had lost their hearing after acquiring speech and language. Children were not included in those early trials, and that decision has been heavily criticized in hindsight. Before the multichannel work, single-channel implants were essentially limited to providing environmental sound awareness and maybe some crude speech reading support. A patient might learn to distinguish a doorbell from a phone, or tell when someone was talking in their direction. Speech comprehension without visual cues was nearly impossible. That changed with multichannel devices, but not overnight. Even in the mid-1980s, a significant number of implant recipients struggled to achieve usable speech perception. The technology was there in principle. The signal processing was nowhere near good enough yet. One thing most people do not understand about the early implant era is how much the surgery itself was a bottleneck. The original House-Stricker and Utah single-electrode procedures required a relatively open mastoidectomy and direct access to the cochlea. Complication rates were not trivial. Facial nerve injury, though rare, was a real risk. CSF leaks happened. Patients sometimes went home with significant facial weakness that lasted weeks or, in rare cases, longer. Modern CI surgery is far more refined. We now routinely use cortical mastoidectomy approaches with smaller incisions and image-guided navigation in complex cases, but those improvements did not arrive until the 1990s and 2000s. The early surgeries were brutal by comparison.
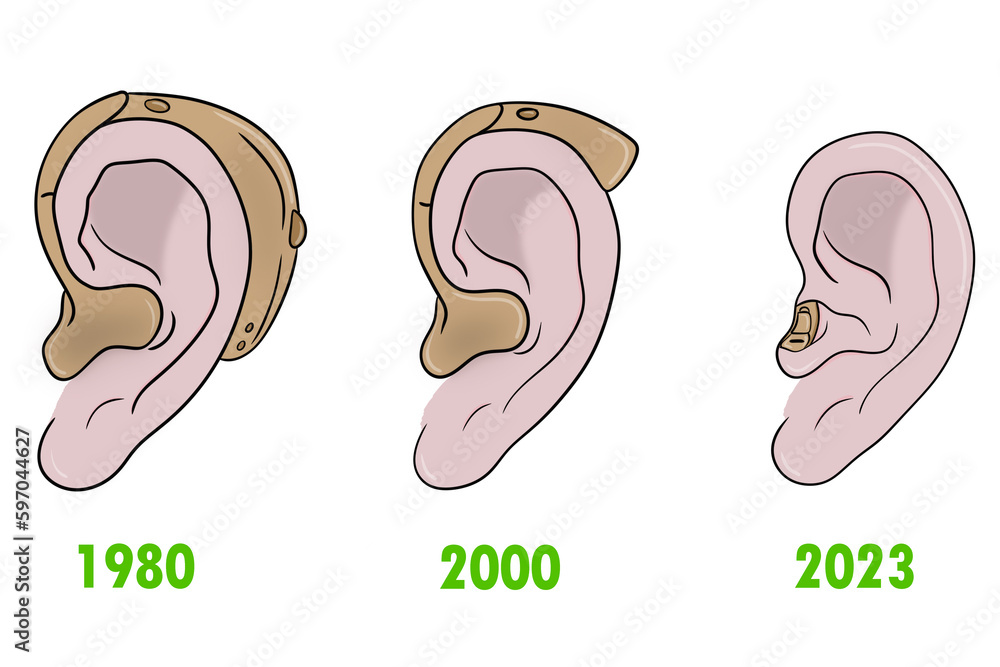
The external processor evolution is another area where the popular narrative skips too quickly. The first processors were backpack-mounted or wore like a shoe box on the body. Head-worn versions came later. The miniaturization of the speech processor from a room-sized unit to something that sits behind the ear took roughly fifteen years of incremental engineering. Each generation introduced new compression algorithms, new filter bank designs, and new debates over whether more channels always meant better outcomes. They did not, as it turned out. Adding channels beyond a certain point gave diminishing returns and sometimes introduced new artifacts that made speech understanding worse, not better. I worked through a case a few years back involving a patient who had received a first-generation single-channel implant as a child in the early 1980s and never received a upgrade because of a combination of anatomical issues and insurance gaps. By the time they came to us for a revision, the cochlea had significant ossification from years of untreated deafness. Standard electrode arrays simply would not pass through the modified turn. We ended up using a specially ordered ultra-thin perimodiolar array and had to be very deliberate about the insertion depth to avoid further trauma. The patient did not regain meaningful speech understanding from that ear. The ossification had gone too far. This is the kind of outcome that does not make it into product marketing materials, but it is a realistic endpoint that clinicians encounter more often than the public realizes. Not every implant failure is about the device itself. Sometimes it is about what the disease process did to the anatomy over decades of untreated deafness.
Get the Full Details

How The Signal Processing Actually Worked Out
The speech coding strategies that became standard — ACE, CIS, SPEAK — represent a lot of iterative optimization that is easy to take for granted now. The ACE strategy, which stands for Advantage Code Execution, was developed at the Nucleus/Clarke group in Australia and became the dominant approach for many years. It selects a subset of channels to activate on each pulse train cycle based on the spectral peaks of the incoming sound. This is a form of temporal masking that exploits how the auditory system actually works. You do not need every frequency band represented simultaneously for the brain to reconstruct speech. The brain fills in gaps reasonably well if you give it the right landmarks. CIS, or Continuous Interleaved Sampling, works differently. It subdivides the sound spectrum into fixed bands and presents pulses from each band in a staggered sequence. This was the dominant strategy for a long stretch and remains in use on some devices. The key difference between CIS and ACE is really about how information is extracted from the waveform before it gets sent to the electrodes. ACE is generally more efficient in noisy environments because it tracks the spectral envelope more closely. CIS is simpler to implement and was easier to debug in the early days of digital signal processing, which mattered when your computational budget was measured in kilobytes of RAM. There is a common misconception that adding more electrodes automatically improves outcomes. It does not. The number of active channels and the number of physical electrodes are two different things. Most modern implants have between twenty-two and thirty-two electrodes per array, but only a fraction of those are typically used as active channels in any given strategy. The limiting factor is not how many contacts you can physically place inside the cochlea. It is how much spectral resolution the human auditory nerve can actually use. Research has consistently shown that beyond roughly twelve to sixteen independent spectral channels, additional information does not translate into better speech understanding for most users. The nerve does not have the fidelity to carry it.
This is one of those counter-intuitive points that trips up people who approach the topic from an engineering background. More is not better here. The biological constraint is the bottleneck, not the technology. Implant manufacturers knew this to some degree but continued pushing higher electrode counts because it looked good on spec sheets and created a perception of advancement. The clinical data did not always support the marketing claim.
What Happened With Pediatric Outcomes
The early exclusion of children from clinical trials was a significant limitation that shaped the entire field for years. Once pediatric implantation became standard practice in the 1990s, the results were genuinely remarkable. Children implanted before the age of two, particularly those with no family history of deafness and access to consistent therapy, often develop spoken language skills that are within the normal range. This was not guaranteed. It required early identification through newborn hearing screening programs, which did not become widespread in the United States until the late 1990s with the implementation of universal newborn hearing screening legislation in most states. The age of implantation is probably the single most important predictor of outcome in pediatric cases. A child implanted at eighteen months will typically perform substantially better on language measures than a child implanted at three years, all else being equal. The critical period hypothesis is relevant here, though the exact boundaries of that period are still debated. What is clear is that prolonged auditory deprivation before implantation produces measurable changes in the central auditory pathways that no amount of electrical stimulation fully reverses. The brain reorganizes. Some of that reorganization is maladaptive for processing electrical hearing signals specifically. I encountered a case recently where a teenager had been implanted at age fourteen after years of deafness without intervention. Their parent had declined the implant initially due to religious considerations and then hesitated for other reasons during the critical early years. The device worked technically. The electrodes fired, the processor was functioning correctly, the imaging showed no anatomical abnormalities. But the patient's speech recognition scores remained in the difficult-to-understand range even after six months of consistent use. This is not a device failure. It is a neural plasticity limitation. The auditory cortex had been repurposed. It needed time, intensive therapy, and often a period of reduced reliance on the implant while the brain recalibrated. Some patients in this situation eventually catch up. Some do not. The data does not lie, but the individual variation is large enough that you cannot predict it with confidence.
The Regulatory And Patent Landscape
The patent wars around cochlear implant technology are one of the less discussed but highly consequential parts of this history. The key patents held by companies like Advanced Bionics, Cochlear Limited, and MED-EL created barriers that shaped which devices could be sold in which markets and for how long. The FDA's De Novo classification process for the multi-channel implant set a precedent that influenced how subsequent generations of devices were evaluated. The regulatory pathway for implantable auditory devices is now one of the most tightly controlled in medical device regulation, and that did not happen by accident. It happened because early devices caused real harm to some patients and because the consequences of a malfunction inside the skull are obviously severe. Insurance coverage remains a practical obstacle in many jurisdictions despite the strong evidence base for benefit. Medicare covers cochlear implants for both adults and children who meet specific criteria, but private insurers vary widely. Some require a period of trial with a hearing aid first. Others impose strict age cutoffs or audiometric thresholds that may not reflect the actual clinical reality of who benefits most. This is not a theoretical problem. It directly affects who gets the device and when they get it, which loops back to the critical importance of early intervention in pediatric cases.
What Still Does Not Work Well
No amount of historical context changes the fact that cochlear implants are far from a complete solution. Music perception remains poor for the vast majority of users. The temporal resolution required to encode pitch contours and rhythm in music is fundamentally at odds with how electrical stimulation of the cochlea works. Speech in quiet conditions can be quite good with a modern device, especially for children who were implanted early. Speech in noise is where the limitations become glaring. Even the best current strategies struggle significantly in restaurant or classroom environments where multiple sound sources are competing. Bimodal fitting, combining a cochlear implant in one ear with a hearing aid in the other, provides some improvement in noise performance but not the full binaural benefit that two intact ears would provide. Bilateral implantation helps more but introduces its own set of surgical and logistical complications. The evidence for bilateral implantation benefit is mixed across studies, and the cost-benefit calculation is not straightforward for families or insurers. There is also the matter of MRI compatibility. While most modern implants are rated for MRI at 1.5 Tesla and many at 3 Tesla without magnet removal, this was not always the case. Early implants required surgical replacement of the internal magnet before any MRI scan could be performed. The risk of imaging-related complications, including magnet displacement and tissue heating, is a real consideration for patients who may need neurological imaging later in life. This is a practical concern that comes up regularly in clinical practice and one that device manufacturers have addressed only incrementally.
The bone conduction and hybrid implant alternatives deserve mention as realistic options for specific patient populations. Those are separate categories with their own histories and limitations, but they exist precisely because the standard cochlear implant approach does not fit everyone. Some patients have residual low-frequency hearing that would be destroyed by a standard electrode insertion. EAS, or electric-acoustic stimulation, devices address this by using a shorter electrode array that preserves residual acoustic hearing while providing electrical stimulation for the high frequencies where hearing is lost. The tradeoff is that you are giving up some high-frequency electrical resolution to maintain low-frequency acoustic input, and whether that tradeoff is beneficial depends heavily on the individual's remaining hearing profile. The cochlear implant is one of the most successful neuroprosthetic devices ever developed. It is also an imperfect solution to a complex biological problem. The history of its development reflects that tension throughout. Every major advance came with unintended consequences, and every accepted standard was once a controversial experimental approach that faced serious opposition from within the medical community itself.