
What Actually Happens When You Treat A Disease Like This As A Social Problem
Most people think of HIV/AIDS as purely a medical issue. The virus exists, the drugs exist, the science is solved. The harder part is everything that surrounds the actual medicine. Funding cycles. Insurance paperwork. A patient missing three clinic appointments because their bus route changed. These are the things that determine outcomes way more than viral load measurements. I spent years watching community health programs try to close the gap between treatment availability and treatment adherence. The programs that worked usually had one thing in common: they stopped trying to solve the disease and started solving the logistics around the disease.
Understanding Hiv Aids As A Social Problem
It sounds obvious but it is worth stating plainly. HIV/AIDS affects social structures differently across regions, across income levels, and across population groups. Two patients with identical CD4 counts and identical prescriptions can end up at wildly different health outcomes depending on whether they have stable housing, whether their employer requires drug disclosure, whether their community has a stigmatization pattern that makes clinic attendance socially costly. That gap is where the social problem lives. Policies shaped around this reality look different than policies shaped around virology alone. They include transportation stipends, anonymous distribution points, workplace non-discrimination enforcement, and funding models that survive beyond election cycles. All of them matter. None of them are particularly novel. The gap between knowing this and doing it is political will and sustained budgeting, not scientific insight.
How Actual Outreach Programs Work In Practice
A functional program starts with mapping where treatment dropoff happens. Most people do not stop treatment because they do not understand their diagnosis. They stop because navigating the system becomes unsustainable. A mobile clinic that appears at a known gathering point once a week reduces appointment friction more effectively than a pamphlet campaign distributed at a hospital entrance fifty miles away. Partner notification and contact tracing are the other piece people underestimate. Traditional methods here rely on patient willingness. That is a bottleneck. Programs that use expedited partner therapy or provide anonymous notification services see better coverage without forcing patients into uncomfortable conversations. The tradeoff is regulatory. Some jurisdictions restrict expedited prescribing. You have to know your local statutes before implementing anything.
Get the Full Details

A Specific Edge Case And What I Did About It
One program I worked with hit a wall that turned out to be mundane. A cluster of patients in a rural county were losing follow-up care because the regional clinic required in-person pharmacy pickups every thirty days. Those patients lived two hours away on a route with no public transit. The medical reason for the thirty-day refill limit was not clinically necessary for stable patients on antiretrovirals. It was a state pharmacy regulation designed for controlled substances. HIV medications are not controlled substances. The fix was not dramatic. We compiled a brief with three components: peer-reviewed evidence showing that ninety-day supplies are safe and standard of care for stable patients, a list of other states that already permitted this, and a letter from the attending physician stating medical necessity. We submitted it to the state board of pharmacy under their existing rule for therapeutic interchange exemptions. Approval took eleven months. The first patient on the ninety-day supply was dispensed medication in March. The lesson is not that bureaucracy is impossible to move. It is that the barrier was regulatory, not clinical. Most dropoff points you encounter will have a regulatory or administrative root. Identifying which one saves weeks of wasted effort.
Common Missteps In Program Design
The biggest mistake I see is building interventions around patient education first. Patients know they need to take medication. They fail because of scheduling conflicts, side effect management, stigma, or cost. Education does not solve any of those. Peer support groups, directly observed therapy where appropriate, and cost-reduction pathways solve the actual barriers. Education is table stakes. It is not the intervention. Another mistake is relying exclusively on hospital-based care for prevention. PrEP and PEP distribution through community health centers, sexual health clinics, and harm reduction programs reaches higher risk populations more efficiently than a hospital referral model. Hospital settings are good for diagnosis and treatment initiation. They are poor at routine prevention distribution for people who do not walk through their doors. A third pitfall is measuring success by diagnosis rates alone. More diagnoses sounds positive until you realize that diagnosis without guaranteed treatment access just creates a larger population of people who know their status and cannot act on it. That outcome damages trust in the healthcare system. Pair every diagnostic expansion with a confirmed treatment enrollment pathway before you scale. Otherwise you are generating data, not health improvements.
What Actually Reduces Transmission At Population Level
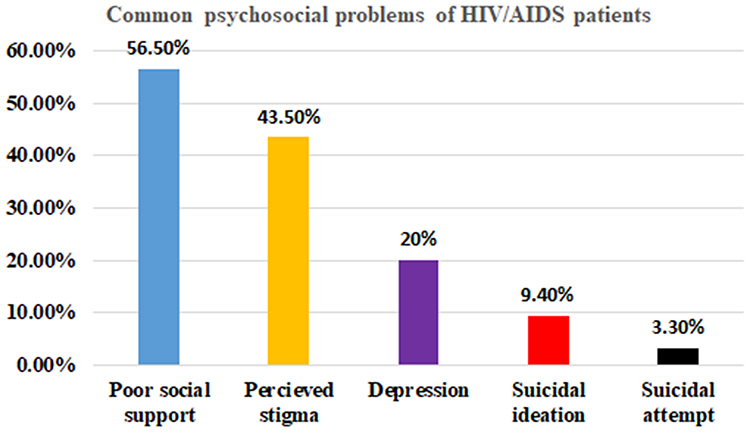
Treatment as prevention is the mechanism. Undetectable equals untransmittable is not a slogan. It is an evidence-backed clinical finding that has held across multiple longitudinal studies. When a significant portion of a population maintains viral suppression through consistent treatment, community-level transmission drops. This is measurable. It has been measured in sub-Saharan Africa, in Southeast Asia, in North America. The limitation is that treatment as prevention only works if people stay on treatment. Adherence gaps create viral rebounds, which create resistance, which undo the prevention benefit. The social problem reappears at the adherence stage. Housing instability, mental health comorbidity, substance use disorders, and transportation barriers all feed into missed doses. Any strategy that ignores these factors will underperform relative to its potential. PrEP fills part of the gap for people not yet diagnosed or not yet connected to care. But PrEP adherence has the same logistical dependencies. Daily pills require daily routines. Long-acting injectables require clinic visits every two to six months. Both demand stable access to healthcare infrastructure. Neither eliminates the need for broader social supports.
Where Current Approaches Fall Short
Curing HIV remains unsolved beyond the handful of documented cases involving bone marrow transplants for cancer. Those cases are not scalable. Gene editing approaches are in early research phases and carry significant safety uncertainties. Until a practical cure exists, the entire framework depends on lifelong treatment. That creates a permanent financial and logistical burden on healthcare systems. Systems that do not plan for that permanence underfund prevention and overinvest in acute care, which is the opposite of cost-effective. Stigma persists despite decades of advocacy because it is reinforced by structural forces, not just individual prejudice. Insurance exclusions, employment discrimination, criminalization laws in multiple jurisdictions, and inadequate sex education all feed the same cycle. Legal challenges have chipped away at the worst restrictions. They have not removed the foundation. Programs that treat stigma as solely an awareness problem waste resources. Programs that address the structural incentives behind stigma see measurable change.
Practical Steps If You Are Building Or Improving A Program
Audit your current dropout points first. Pull the data on lost to follow-up rates by month, by location, by demographic. The pattern will tell you where the real problem is. Most programs skip this step and implement whatever solution matched a successful grant proposal somewhere else. Solutions do not transfer across contexts without adjustment. Map every barrier your target population faces onto a timeline. Diagnosis, initial treatment, medication refill, routine monitoring, specialty care referral. Identify which step has the highest attrition. Build your intervention around that step. Everything else is secondary until that step improves. Partner with organizations that already have trust in the communities you are trying to reach. Medical institutions do not automatically have that trust. Community-based organizations, peer networks, and faith groups often do. Co-design programs with them instead of handing them a finished protocol to distribute. Implementation quality degrades fast when the people delivering the program did not help build it.
Track outcomes beyond viral suppression. Track retention rates. Track patient-reported barriers. Track cost per patient maintained on treatment versus cost per patient lost to follow-up. The financial data alone usually changes how administrators prioritize funding more effectively than any clinical argument. Hiv Aids As A Social Problem is not a metaphor. It is the accurate description of what happens when a virus interacts with housing policy, insurance design, criminal law, transportation infrastructure, and cultural attitudes. Treating it as a social problem means working on all of those simultaneously. Treating it as purely a medical problem means accepting that medical solutions will underperform their theoretical potential every single time.



