Why Most APRNs Drop the Holistic Piece
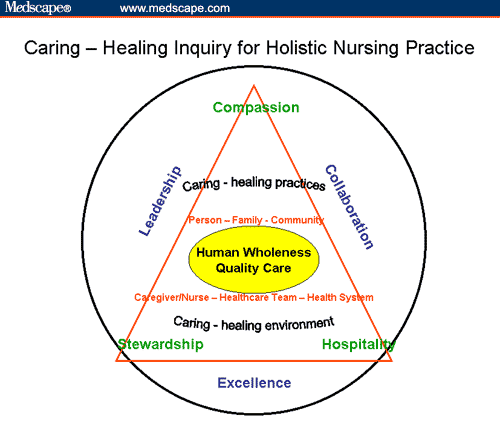
Most advanced practice nursing programs spend about three weeks on holistic care frameworks, then pivot straight into pharmacology, pathophysiology, and procedure protocols. By the time you hit clinical rotations, you are already juggling 12 to 16 patients per day in primary care, and the holistic part gets squeezed into whatever time remains after the labs, the prescribing, and the documentation. I have watched nurse practitioners who are genuinely excellent at diagnosing and managing chronic disease struggle to integrate a real biopsychosocial assessment without it turning into a checkbox exercise that nobody benefits from. The gap is not that APRNs lack the concept. It is that the systems we work in do not reward it. A typical 15-minute visit in a busy outpatient clinic simply does not leave room for exploring social determinants, family dynamics, or patient values unless you deliberately build space for them during the interview. This is where Holistic Care In Advanced Practice Nursing moves from textbook ideal to practical workflow challenge.
Implementing Holistic Care In Advanced Practice Nursing Without Losing Your Mind
I started with a structured screening tool rather than trying to wing it. The ECOG scale and the PHQ-9 are useful, but they miss the broader picture. I began using a modified Social Determinants of Health questionnaire at intake, paired with a quick WHOQOL-BREF brief version, and I built it into my EHR as a smart phrase template. That alone cut the time needed for a meaningful psychosocial assessment from about 12 minutes to roughly 3 minutes, which is actually usable during a standard follow-up visit. The key is making it part of the routine flow, not an add-on at the end when everyone is rushing out the door. One thing people rarely tell you about holistic practice is that documentation becomes your enemy if you are not careful. I learned this the hard way during a malpractice-adjacent review where a patient’s deteriorating mental health was clearly present in their records but scattered across three different encounter notes over six months. The chart did not show a pattern because nobody had ever pulled the psychosocial thread through the clinical thread. I now run a simple monthly chart audit where I flag any patient on more than two chronic medications who has not had a documented social determinant screen in the past 90 days. It takes me about 20 minutes per month for my entire panel, and it has caught functional decline and unaddressed depression in at least four patients who would otherwise have fallen through the cracks. Here is a counter-intuitive point that caught me off guard early in my career. Being holistic does not mean doing more. It means asking fewer, better questions. I used to ask patients about sleep, diet, stress, relationships, finances, and spiritual beliefs in a single visit, which guaranteed I heard nothing deeply. Now I rotate focus areas. One visit I drill into sleep and pain. The next, I go deeper on social support and care preferences. It sounds fragmented, but it produces richer data than skimming the surface of everything every time.
The Tools That Actually Survive Real Clinical Pressure
There are plenty of holistic care models in the literature. The Watson Theory of Human Caring, the Neuman Systems Model, the Rogers Science of Unitary Human Beings. Each has merit. Each also tends to get abandoned once you are responsible for a panel of 2,400 patients and a productivity metric that measures relative value units per encounter. What survives is simpler than the models suggest. I use a five-question anchor at the start of every new patient visit. What is the main thing you want us to address today. What is getting in the way of your health outside of medical appointments. What matters most to you about your quality of life. What have you tried before that helped or hurt. Who else should be involved in your care decisions. These five questions take about four minutes. They open doors that standard chief complaint screening rarely touch. They also give you something concrete to document, which protects you clinically and gives you leverage when referring to behavioral health or social work. I ran into a specific edge case last year that tested this approach. A 68-year-old woman with type 2 diabetes, heart failure, and knee osteoarthritis presented with worsening glycemic control and repeated ER visits for fluid overload. All the metabolic markers pointed to medication non-adherence. The standard reflex was to adjust her diuretic regimen again and reinforce self-management education. Instead, I used the second anchor question and asked what gets in the way of her health outside appointments. She disclosed that her adult child, who lived with her, was hoarding her medications because he believed she was being poisoned by the pharmaceutical industry. No amount of prescription optimization would fix that. I coordinated a home visit through the agency, engaged a community health worker, and arranged a family meeting. Her A1C dropped 1.4 points and her heart failure admissions fell to zero over the next eight months. That outcome would not have happened with a purely biomedical approach, and it would not have happened quickly either if I had stayed on the standard pathway.
Get the Full Details
Where This Approach Breaks Down
I need to be blunt about the limitations, because anyone selling you holistic care without acknowledging the friction is not being honest. The model fails when you do not have time allocated for it. It fails when your EHR is not configured to surface psychosocial data across encounters. It fails when payers structure reimbursement in a way that penalizes longer visits without compensating for care coordination. And it fails when the patient does not have access to the social services you identify as necessary. I have had patients where the right intervention was housing support, but the local housing authority had a nine-month waitlist. I have had patients where the barrier was transportation, but the county paratransit system required medical certification that took six weeks to process. Identifying the barrier is only half the work. Closing the gap requires infrastructure that most of us do not have reliable access to. In those situations, the best you can do is document the identified barrier, make the referral, and schedule a specific follow-up to check whether it was resolved. That follow-up should be built into your workflow, not left to chance. Another failure mode is clinician burnout. Holistic practice demands emotional labor. You are listening to people’s lives, not just their lab values. Over time, that adds up. I have seen colleagues disengage from the psychosocial component entirely after two or three years because the system kept demanding more from them without providing structural support. The workaround is not to do more holistic care. It is to do less but do it consistently. One well-done psychosocial screen per visit beats three half-hearted ones. Protect your own capacity by setting boundaries around what you take on and when you escalate to other disciplines.
A Practical Workflow You Can Start Next Week
If you want to integrate this into your practice without redesigning your entire clinic, here is what I would recommend. Build the five-question anchor into your EHR as a smart phrase or template. Schedule it to appear automatically for new patient visits and annual wellness visits. Use the monthly chart audit I described to catch patients who have slipped through. Partner with one social work or community health resource in your network so you have at least one reliable referral pathway. Track your outcomes, not just your productivity metrics, by noting how many referred patients were actually connected to services over a 90-day window. This is not a complete solution. It will not fix systemic underfunding, it will not compress a 15-minute visit into 10, and it will not replace the need for structural changes in how advanced practice nursing is reimbursed and resourced. But it is something you can implement on your own without waiting for institutional permission, and it produces measurable differences in patient outcomes within a few months. That is more than most of the frameworks in the textbooks deliver once you actually step into a clinic.