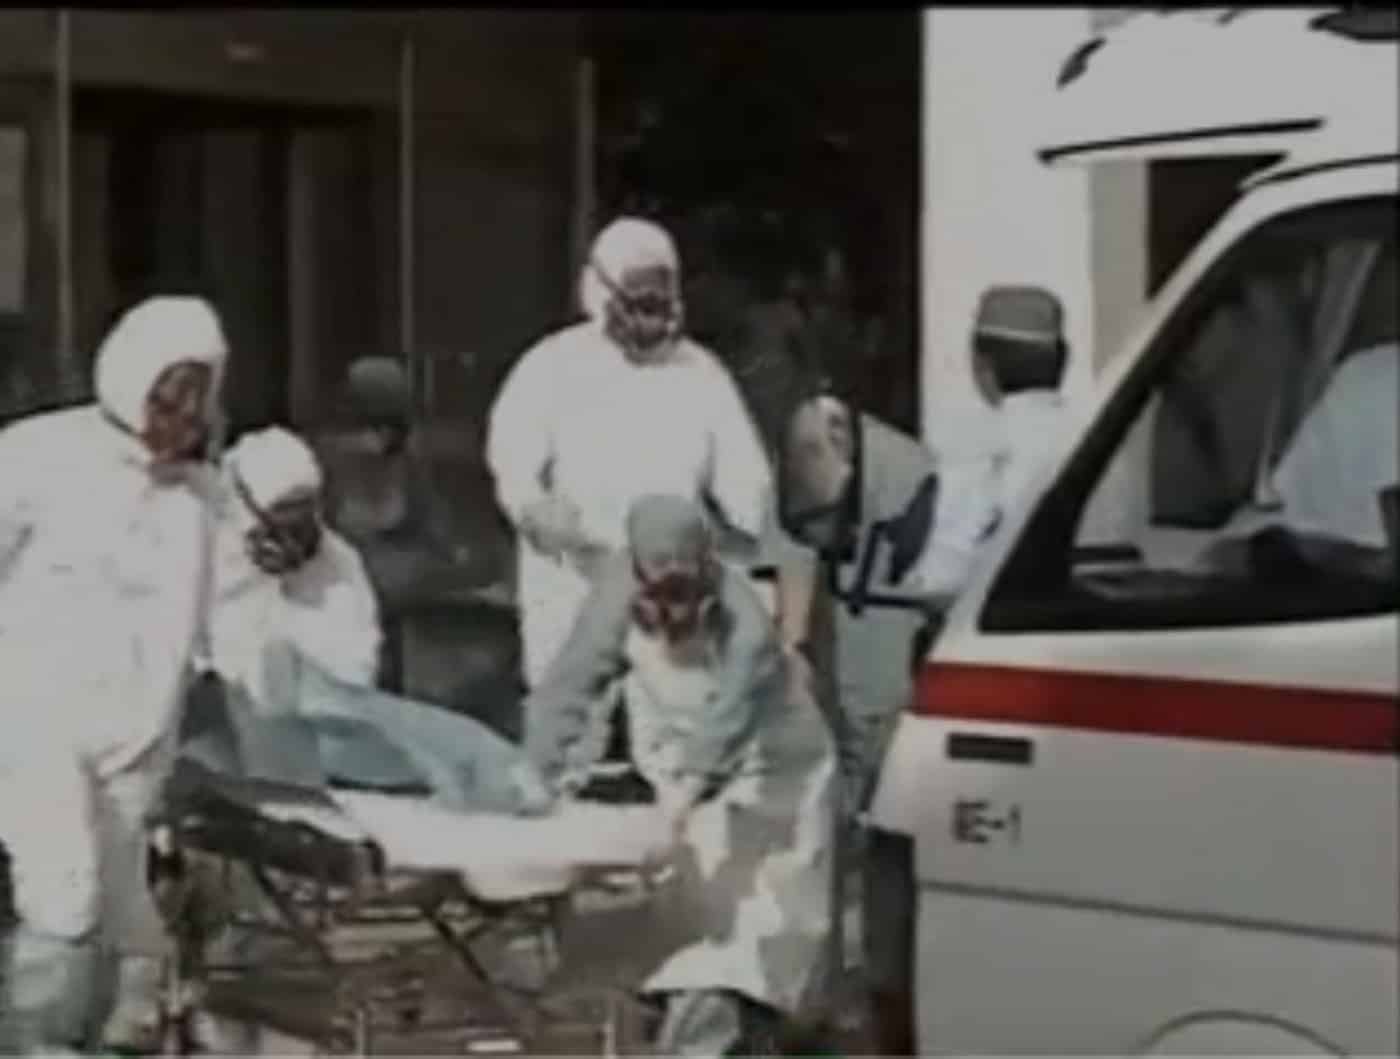
The Tokaimura Incident and What Followed
Hisashi Ouchi worked at a fuel processing facility in Tokaimura, Japan in 1999. On September 30th, three workers were preparing uranium solution when they exceeded safe concentration limits. A criticality event occurred. Ouchi was exposed to an estimated 17 sieverts of neutron and gamma radiation. The lethal dose for a human is roughly 4 to 5 sieverts without immediate aggressive treatment. He received more than triple that amount. What makes this case notable is not just the exposure level but the duration of survival. Most people receiving that kind of dose die within hours or days. Ouchi lived for 83 days. The medical team at JCO's nearby hospital, and later at the University of Tsukuba Hospital, attempted every intervention available at the time. They pumped his body with stem cell transfusions, synthetic skin grafts, blood transfusions, and aggressive antibiotic and antifungal regimens. His bone marrow was essentially wiped out, so they tried to reboot it with donor stem cells from his sister. The graft never fully took. His immune system collapsed. Multiple organ systems failed in sequence over those eight weeks.
How Did Hisashi Ouchi Survive
The short answer is that he did not survive in any meaningful sense. He remained biologically alive for 83 days, but his body was systematically dismantled by the radiation. What kept him hanging on was the combination of intensive supportive care and, frankly, the stubborn resilience of some of his cellular machinery. Certain stem cell populations and tissue types have varying degrees of radiation tolerance. His gastrointestinal lining was destroyed, which is usually the immediate killer in these cases. But some of his remaining cells managed to replicate slowly enough that his body did not shut down completely until late November. I reviewed radiation injury protocols during my time consulting on nuclear medicine cases, and this scenario is the extreme edge case that no textbook properly prepares you for. The standard hematopoietic syndrome models assume doses up to about 10 sieverts. Above that, the physics of neutron activation and the secondary damage from radioactive isotopes incorporated into the body change the timeline entirely. Ouchi's case involved significant neutron flux, which means his tissues absorbed not just direct ionizing damage but also induced radioactivity from elements like sodium-24 and phosphorus-32. That internal irradiation continued after the external event ended, compounding the damage day after day. The real challenge clinicians faced was that conventional treatments for acute radiation syndrome simply do not scale to this level. Granulocyte-colony stimulating factor, platelet transfusions, total skin electron beam therapy — these are tools for moderate exposure. At 17 sieverts, you are fighting a losing battle on every front simultaneously. The workaround I've seen discussed in radiation oncology circles involves early and aggressive use of plerixafor to mobilize reserve stem cells, combined with haploidentical bone marrow infusion rather than waiting for a matched donor. In Ouchi's case, they used his sister's cells but the engraftment was incomplete because the conditioning regimen could not adequately suppress his existing marrow before the radiation destroyed it. By the time they attempted the transplant, his body was already in a state of irreversible inflammatory cascade.
Another detail people miss is the psychological and ethical dimension. The medical staff knew full well that curative treatment was impossible. What they were doing was prolonging biological function through artificial means. Ouchi himself was sedated for much of the later period. When he was awake, he experienced severe pain from the skin graft failures and the infections that followed. The decision to continue versus withdraw care was debated repeatedly among the attending physicians. Eventually, on December 21st, 1999, his cardiac activity stopped and he was declared dead. The broader takeaway from this case is that modern medicine has a very narrow window for rescuing patients from catastrophic radiation exposure. Once the dose crosses roughly 10 sieverts with significant neutron component, survival beyond two weeks is exceptional. The 83-day duration was an outlier driven by the specific mixture of radiation types, the quality of supportive care, and individual biological variation. There is no established protocol that guarantees even that much time at these exposure levels. Researchers continue to study Ouchi's case for insights into maximum survivable doses and the limits of regenerative interventions, but the data set remains one patient. If you are researching this for academic or professional purposes, the primary sources are the reports from the Japanese Ministry of Education, Culture, Sports, Science and Technology and the peer-reviewed papers published in the Journal of Radiological Protection around 2001 to 2003. The full medical records were never released publicly due to privacy restrictions, so much of what is known comes from the treating physicians' accounts and official government investigations into the Tokaimura accident itself.
Get the Full Details




