Understanding Shingles Transmission
Most people I talk to who have dealt with shingles are genuinely confused about how it spread. The virus part is straightforward, but the actual mechanics of transmission trip people up constantly. Here is what you need to know.How Do You Catch Shingles
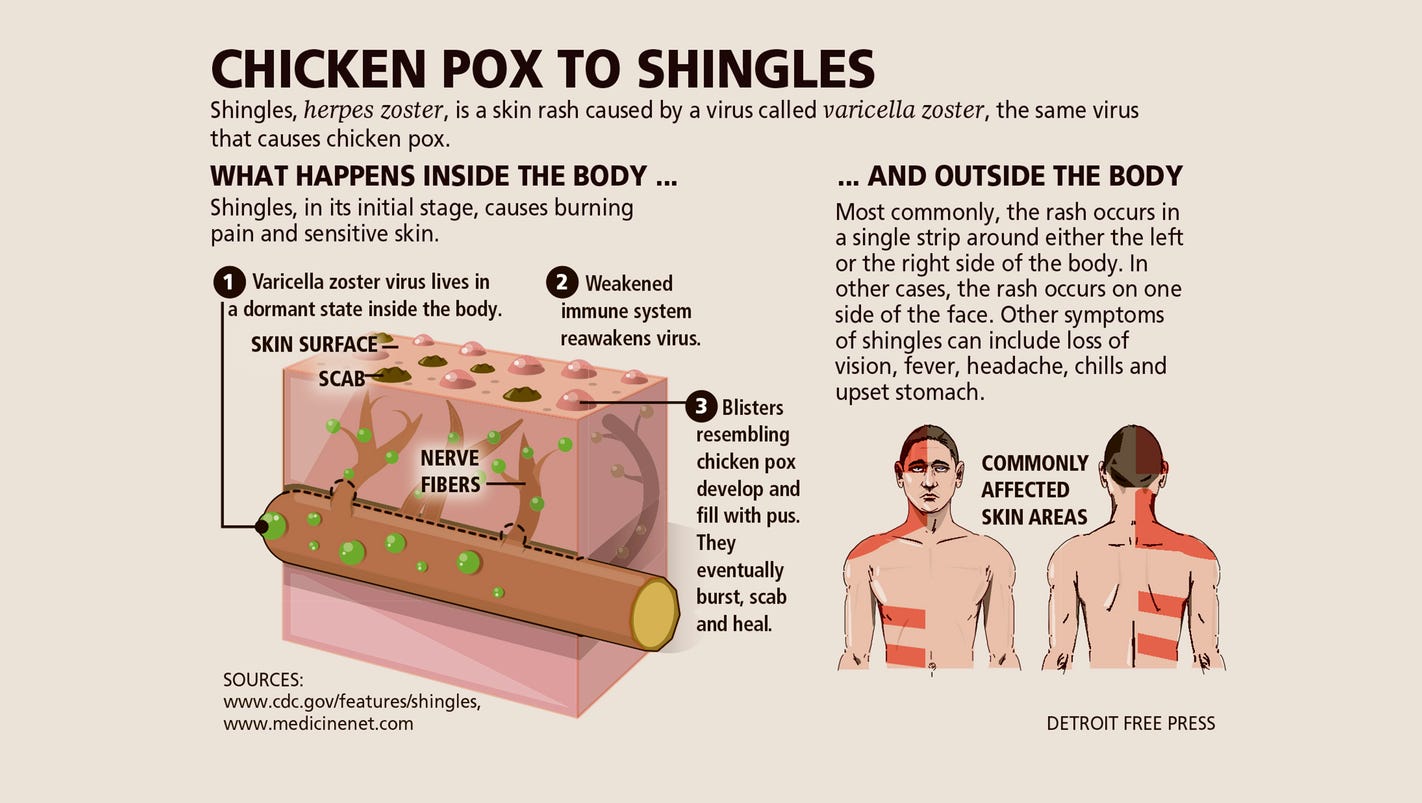
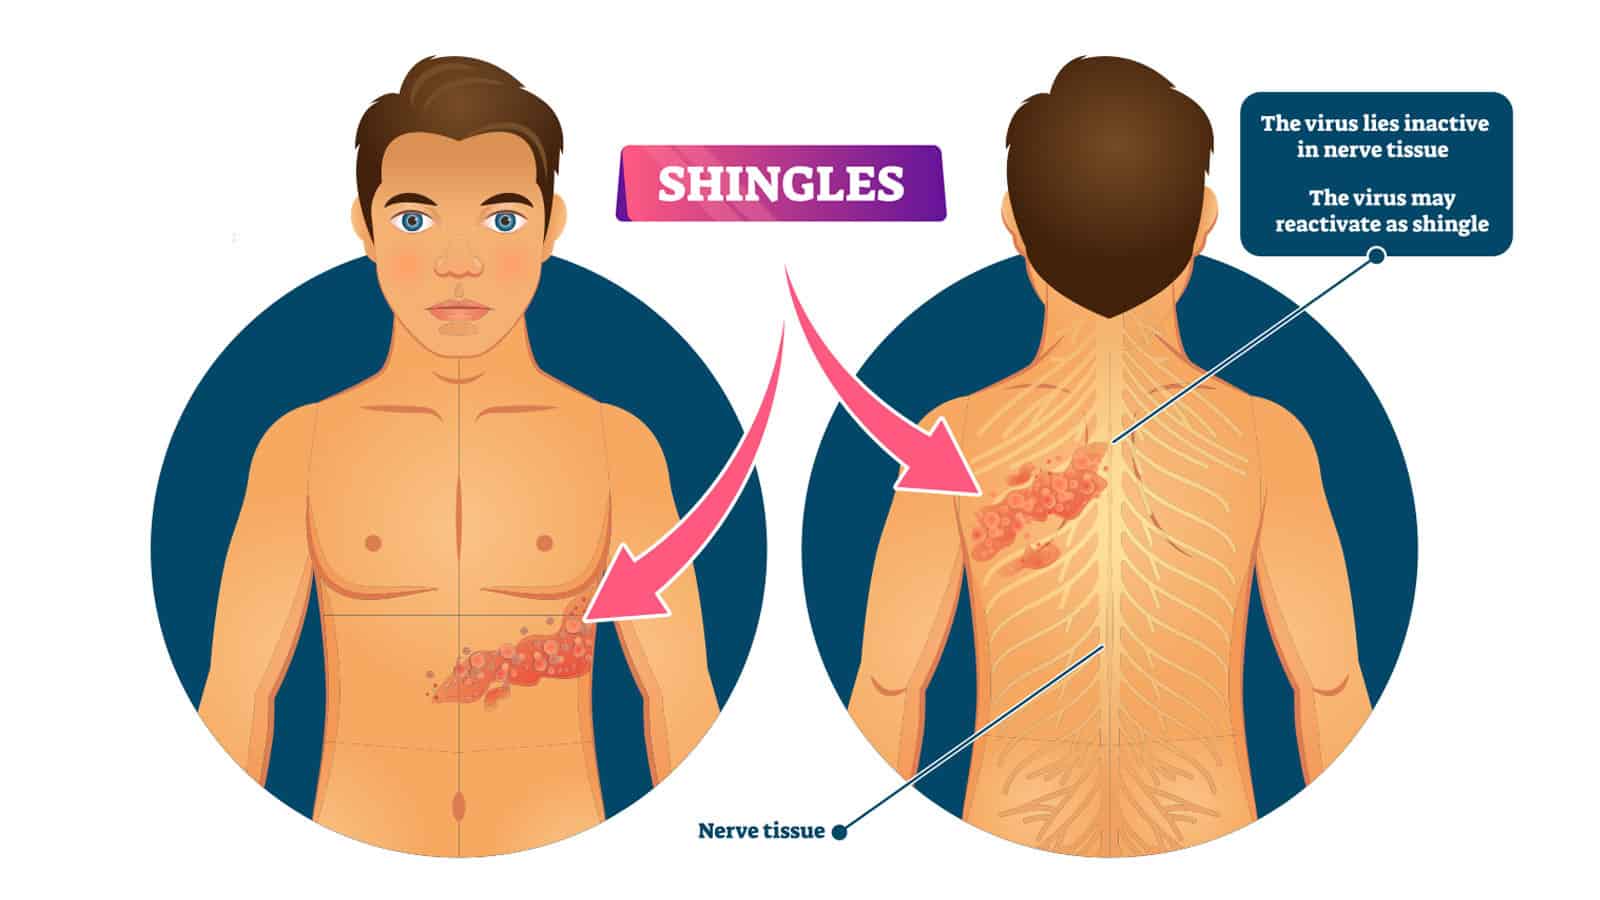
You do not catch shingles from someone who has shingles. This is the single most common misconception I hear. Shingles is caused by the reactivation of varicella-zyster, the same virus that causes chickenpox. Once you have had chickenpox, the virus lies dormant in your nerve tissue. It can reactivate later in life as shingles. What you can catch from someone with active shingles is chickenpox. Specifically, if you have never had chickenpox or the vaccine, direct contact with the fluid from shingles blisters can transmit the virus and cause a primary chickenpox infection. You cannot give someone shingles directly. I spent about an hour on the phone with a nurse at an urgent care center trying to explain this to a patient who was convinced her coworker had "given her shingles." It took three separate conversations before the concept stuck. The transmission route just does not intuitively map to how people think about contagion.
The Actual Transmission Mechanism
Varicella-zoster is spread through direct contact with blister fluid. That means touching the rash, not breathing near someone who has it. Airborne transmission is theoretically possible but extremely rare in practice. The virus does not circulate through the air like influenza or measles. The window of communicability runs from the time the rash appears until all blisters have crusted over. This usually takes seven to ten days. Once the lesions are dry and scabbed, the risk drops to essentially zero. I always tell people to cover the rash with clothing or a bandage if they cannot stay home from work or social obligations. It is not about protecting others from shingles. It is about protecting people who have never had chickenpox from getting it for the first time as an adult, which tends to be much more severe.
Who Actually Gets Reactivated Shingles
Anyone who has had chickenpox can get shingles. The virus stays in your body for life. It is not a one-time infection where the virus leaves and comes back from the outside. It is already there, sleeping in your dorsal root ganglia, and it wakes up when your immune system stops keeping it in check. Reactivation risk increases significantly after age fifty. The immune system naturally weakens with age, a process called immunosenescence, and the varicella-zoster-specific T-cell response that keeps the virus suppressed becomes less effective. This is why the shingles vaccine is recommended starting at age fifty for healthy adults and at forty-five for immunocompromised individuals. Immunocompromised people are a different category entirely. I once treated a patient on rituximab for lymphoma who developed shingles at age thirty-eight with no other risk factors. Rituximab depletes B cells, and while the mechanism of shingles reactivation involves T-cell dysfunction, the overall immune suppression created a permissive environment. This is worth noting because standard risk-profile lists do not always flag every immunosuppressive therapy.
Get the Full Details
Practical Steps If You Suspect Exposure
If you have never had chickenpox and you have been in close contact with someone who has active shingles, do not wait for symptoms. Post-exposure prophylaxis with varicella-zoster immune globulin (VariZIG) can be effective if administered within ten days of exposure. This is particularly important for pregnant women, newborns, and severely immunocompromised individuals who cannot receive the live vaccine. For everyone else, the practical move is straightforward. If you have had the chickenpox vaccine, you are already protected. Two doses provide approximately ninety percent protection against chickenpox and substantially reduce the risk of reactivation since the vaccine strain also establishes latency. If you have not been vaccinated and are unsure whether you had chickenpox, a simple IgG blood test can determine your immunity status.
Common Pitfalls and What People Get Wrong
One thing nobody talks about enough: you can get shingles even if you have had the vaccine. The Zostavax vaccine reduces risk by about fifty percent, and the newer Shingrix vaccine reduces risk by about ninety percent, but neither provides absolute protection. In my experience, patients who received the older Zostavax vaccine in their fifties sometimes develop breakthrough shingles in their sixties, usually milder but still painful. Another frequent error is assuming that if you have had shingles once, you cannot get it again. Recurrence happens in roughly six to eight percent of patients. The immune response to the initial outbreak provides some protection but not complete immunity. I had a patient return six years after his first episode with the same dermatomal rash pattern on the opposite side. Same nerve roots, same virus, different limb. He was frustrated that he had to go through the whole antiviral course again. The antiviral window matters more than most people realize. Acyclovir, valacyclovir, and famciclovir all work by inhibiting viral DNA replication. They are most effective when started within seventy-two hours of rash onset. After that window, the benefit drops off sharply because the virus has already replicated to peak levels and the damage is primarily immune-mediated rather than actively replicative. I see patients who wait five or six days because they thought it was just a bug bite or insect sting, and by the time they present, the antivirals offer minimal benefit for outbreak duration.
Prevention Is Still the Most Practical Approach
The Shingrix vaccine is a recombinant zoster vaccine that does not contain live virus. It is given as two intramuscular doses, typically in the deltoid, with a gap of two to six months between doses. The efficacy in adults over fifty is around ninety-one percent and remains above eighty-five percent even in the oldest age groups. It is not a one-and-done vaccine in the way people hope. Immunity wanes over time, though protection against severe complications like postherpetic neuralgia appears to persist longer than protection against clinical shingles itself. If you are immunocompromised and have questions about vaccination timing relative to your treatment cycle, talk to your oncologist or rheumatologist. I have seen too many patients get the vaccine during active chemotherapy when it will be effectively useless, then get told they need to wait six months after treatment ends before getting any meaningful immune response. Timing matters here more than almost any other medical intervention. The bottom line is that shingles is not contagious as shingles. It is contagious as chickenpox under the right conditions, and those conditions require direct contact with blister fluid from someone who has not previously been exposed to varicella-zoster. Cover the rash. Wash your hands. Get vaccinated if you are eligible. Then move on with your day.