Acute Gout Management
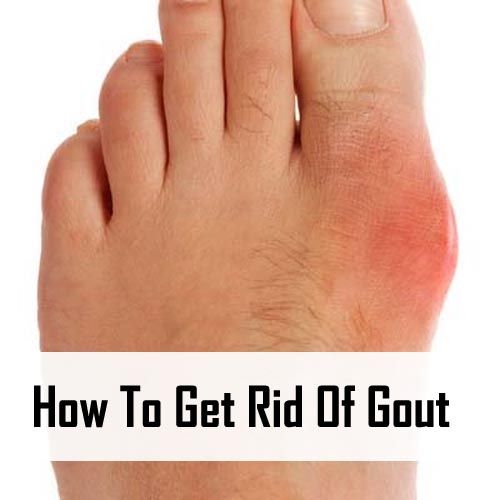
Gout is inflammation caused by monosodium urate crystals depositing in joints. Most common in the first metatarsophalangeal joint, but you will see it in ankles, knees, wrists, and elbows too. The acute attack hits fast—usually overnight—and peaks within 12 to 24 hours. If you are reading this during an active flare, the goal right now is pain control and inflammation reduction. Uric acid lowering is a separate conversation that comes after the fire is out. I treated my first serious gout flare in my late twenties and made the classic mistake of trying to start allopurinol during the attack itself. What happened is the last thing you want: as serum urate drops rapidly, existing crystals become unstable and shed more fragments into the joint space. That actually prolongs and worsens the flare. I spent an extra four days in pain because of that. The rule is straightforward. Wait until the acute episode has completely resolved before starting or adjusting any urate-lowering therapy. If you are already on allopurinol or febuxostat when a flare hits, do not stop it. Just treat the inflammation on top of it.
How Do You Get Rid Of Gout
The three first-line options for an acute gout flare are NSAIDs, colchicine, and corticosteroids. Each has its place and none of them work equally well for every patient. NSAIDs are usually the first choice if you have no contraindications. Indomethacin at 50 milligrams three times daily has been the traditional standard, but naproxen at 500 milligrams twice daily or celecoxib at 200 milligrams once daily work just as well and are easier on the stomach. Start at full dose immediately. Do not wait to see if it helps before escalating. You need to hit it hard in the first 24 hours. If you have chronic kidney disease, peptic ulcer history, or are on anticoagulants, skip this category entirely. Colchicine works by disrupting microtubule polymerization, which stops neutrophils from migrating toward the urate crystals and participating in the inflammatory cascade. The old dosing protocol of 1.2 milligrams followed by 0.6 milligrams an hour later is still the FDA-approved regimen, but I have found that many patients get equivalent relief with a lower total dose and significantly fewer gastrointestinal side effects. A 0.6 milligram dose at onset, then 0.3 milligrams twice daily for the next few days gets people through most flares without the violent diarrhea that makes compliance impossible. Renal dosing adjustments are mandatory here. If your eGFR is below 30, colchicine becomes risky and you should move straight to steroids or consult a rheumatologist.
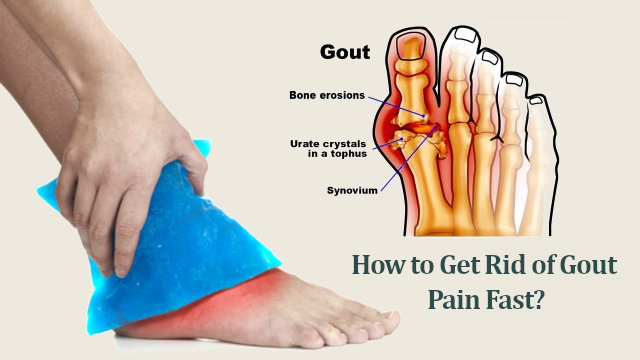
Corticosteroids are the go-to when NSAIDs and colchicine are off the table. Prednisone at 30 to 40 milligrams daily for five to ten days, then taper over another week, is the standard approach. Intra-articular triamcinolone injection is an excellent option when only one or two joints are involved. I have injected my own flares with a 40 milligram per milliliter triamcinolone suspension using a 25-gauge needle. It provides near-immediate relief in the targeted joint and avoids systemic side effects. The caveat is that you need to rule out septic arthritis first. A hot, swollen joint is gout until proven otherwise, but missing an infection in that same joint while injecting steroids is a catastrophic error. If there is any doubt about the diagnosis, aspirate the joint and send it for cell count and culture before injecting anything. There is a practical detail most guides skip. Ice helps, but not in the way people assume. Direct ice application to an acutely inflamed gout joint will cause vasoconstriction that can actually promote further crystal precipitation in the tissue. Instead, use intermittent cold therapy—15 minutes on, 45 minutes off—to reduce pain signaling without dropping local temperature enough to worsen crystal stability. Elevation and rest matter far more than ice. Hydration is often understated. Aim for at least 2 to 3 liters of water daily during a flare. This supports renal clearance of urate and helps prevent new crystal formation. Alcohol, especially beer and spirits, inhibits urate excretion and directly triggers flares in susceptible individuals. I had a patient who attributed his recurrent flares solely to red wine and completely stopped only beer. He kept drinking beer and kept flaring. The purine content in beer is the real driver, not the color or type of alcohol. Clear spirits mixed with water are the least provocative option if someone is going to drink during remission, but avoidance is still the safest bet.
Get the Full Details
Long-Term Urate Lowering
Once the acute inflammation is gone, you shift to preventing the next attack. This is where urate-lowering therapy becomes essential. The target serum urate level is below 6 milligrams per deciliter for most patients, and below 5 milligrams per deciliter if you have tophi visible on exam or imaging. Getting below that threshold causes existing crystal deposits to slowly dissolve. It takes time—often months to years depending on the burden—but the evidence is clear that sustained urate lowering prevents future flares and reverses joint damage. Allopurinol remains the first-line agent globally. It is a xanthine oxidase inhibitor that blocks the conversion of hypoxanthine to xanthine and xanthine to uric acid. The starting dose should be low—100 milligrams daily, or even 50 milligrams in patients with Stage 3 or worse chronic kidney disease—and titrated up every two to four weeks based on serum urate levels. The old practice of starting at 300 milligrams daily is outdated and increases the risk of adverse reactions without improving outcomes. The ALMIRALL study and subsequent guidelines support low-start, slow-titrate approaches even in advanced CKD. The serious warning here is allopurinol hypersensitivity syndrome. It is rare—roughly 1 in 1,000 to 1 in 10,000—but it carries a mortality rate of 20 to 25 percent when it occurs. It is strongly associated with the HLA-B*5801 allele, which is far more common in patients of Han Chinese, Korean, and Thai descent, and also elevated in African populations. If you are prescribing allopurinol to a patient from one of these backgrounds, genetic screening before initiation is not optional. It is standard of care. The test costs about $200 and takes one to two weeks. Skipping it because the reaction is "rare" is not a defensible decision when the consequence can be fatal.
Febuxostat is the alternative for patients who cannot tolerate allopurinol. It is also a xanthine oxidase inhibitor but has a different chemical structure and is primarily hepatically metabolized, so it does not require renal dose adjustment. The FDA issued a black box warning for febuxostat due to increased cardiovascular mortality seen in the CARES trial compared to allopurinol. That does not mean febuxostat is dangerous for everyone with gout. It means you should avoid it in patients with established cardiovascular disease and use it preferentially in those with significant renal impairment who cannot take allopurinol. The dosing range is 40 to 80 milligrams daily, and you again titrate to serum urate target. Probenecid is a uricosuric agent that has been around since the 1950s and is largely forgotten in the United States, though it remains commonly used in Europe and Asia. It works by inhibiting URAT1 in the proximal tubule, reducing urate reabsorption and increasing renal excretion. It requires adequate renal function (creatinine clearance above 50) and adequate hydration to be effective. The starting dose is 250 milligrams twice daily, titrated to response. The major limitation is that it only works if the kidneys can still excrete urate, and it increases the risk of uric acid kidney stones. If you have a history of nephrolithiasis, probenecid is a poor choice. Lesinurad combined with a xanthine oxidase inhibitor is another uricosuric option, approved for patients who have not responded adequately to allopurinol or febuxostat alone. It has similar stone risk considerations to probenecid and adds the complexity of dual therapy, so it is generally reserved for refractory cases.
Pegloticase is a recombinant urate oxidase given as an intravenous infusion every two weeks. It converts uric acid directly to allantoin, a much more soluble compound that is easily excreted. This is not a first-line or second-line treatment. It is for severe, refractory gout with heavy tophaceous burden that has failed oral therapy. The infusion reactions are common—about 30 to 40 percent of patients experience them—and premedication with acetaminophen, an antihistamine, and a corticosteroid is standard protocol. Anti-drug antibodies develop in a majority of patients over time, which neutralizes the drug's effect, so it is typically limited to six to twelve months of use. The cost is substantial, roughly $150,000 to $200,000 per year, and prior authorization from insurance is essentially always required.

Practical Considerations Most People Miss
Prophylaxis during the initiation phase of urate-lowering therapy is critical and consistently underprescribed. When you start allopurinol or febuxostat and serum urate drops, the changing crystal equilibrium causes mobilization flares. These are not treatment failures. They are a sign that the therapy is working and crystals are dissolving. Without prophylaxis, up to 50 percent of patients will experience at least one flare in the first six months of treatment, and many will simply stop the medication because the flares feel worse than their baseline gout. The standard prophylactic approach is low-dose colchicine at 0.6 milligrams once or twice daily, or a low-dose NSAID, continued for at least six months after reaching the target urate level. If the patient cannot tolerate colchicine or NSAIDs, low-dose prednisone at 5 to 10 milligrams daily is an acceptable alternative. The duration matters. Six months is the minimum. Patients with tophi should stay on prophylaxis for at least 12 months or until the tophi are clinically resolved. Stopping prophylaxis too early is one of the most common reasons I see patients abandon urate-lowering therapy permanently. Dietary modification alone will lower serum urate by approximately 1 milligram per deciliter at best. That might take you from 9 to 8, but it will not take you from 9 to below 6. Lifestyle changes are necessary adjuncts but they are not sufficient as monotherapy for most patients with established gout. The patients who think diet alone can control their gout are almost always the ones who present with destructive tophaceous disease because they refused pharmaceutical treatment. I have seen it repeatedly.
Specific dietary triggers are worth knowing. High-purine foods include organ meats, anchovies, sardines, mussels, scallops, and gravy. Fructose-sweetened beverages are a significant and often overlooked trigger. The fructose metabolism pathway directly increases purine turnover and urate production. A study published in the New England Journal of Medicine showed that consuming a high-fructose beverage increased serum urate by approximately 0.5 milligrams per deciliter within two hours. Sugar-sweetened soda, energy drinks, and fruit juices with added fructose are the biggest offenders. Artificial sweeteners do not have this effect. Switching from regular soda to diet soda is a genuinely useful intervention, not just a cosmetic change. Weight loss improves urate handling through multiple mechanisms: reduced insulin resistance decreases renal urate reabsorption, decreased leptin levels reduce inflammatory tone, and overall metabolic improvement supports better urate excretion. But rapid weight loss through fasting or very low-calorie diets can actually trigger flares by increasing ketone production, which competes with urate for renal excretion. Gradual weight loss of one to two pounds per week is the safe approach. Crash diets make gout worse in the short term even though they help in the long term.
When to Refer
Most gout can be managed in primary care. Referral to rheumatology is warranted when the diagnosis is uncertain and joint aspiration has not been performed, when there is refractory disease despite adequate trials of allopurinol and febuxostat, when pegloticase is being considered, when there are complex comorbidities that make drug selection difficult, or when tophi are causing mechanical problems such as nerve compression or joint instability that may require surgical intervention. The bottom line is that gout is highly treatable but it requires a two-phase approach that most patients and some clinicians conflate. Acute attacks need anti-inflammatory treatment. Long-term prevention needs urate-lowering therapy. Doing one without the other guarantees recurrence. The flare will come back, usually within six to twelve months, and each recurrence causes cumulative joint damage. Getting the sequence right and staying consistent with the maintenance phase is what separates patients who control their gout from patients who cycle through emergency rooms every few months.