What Warts Actually Are
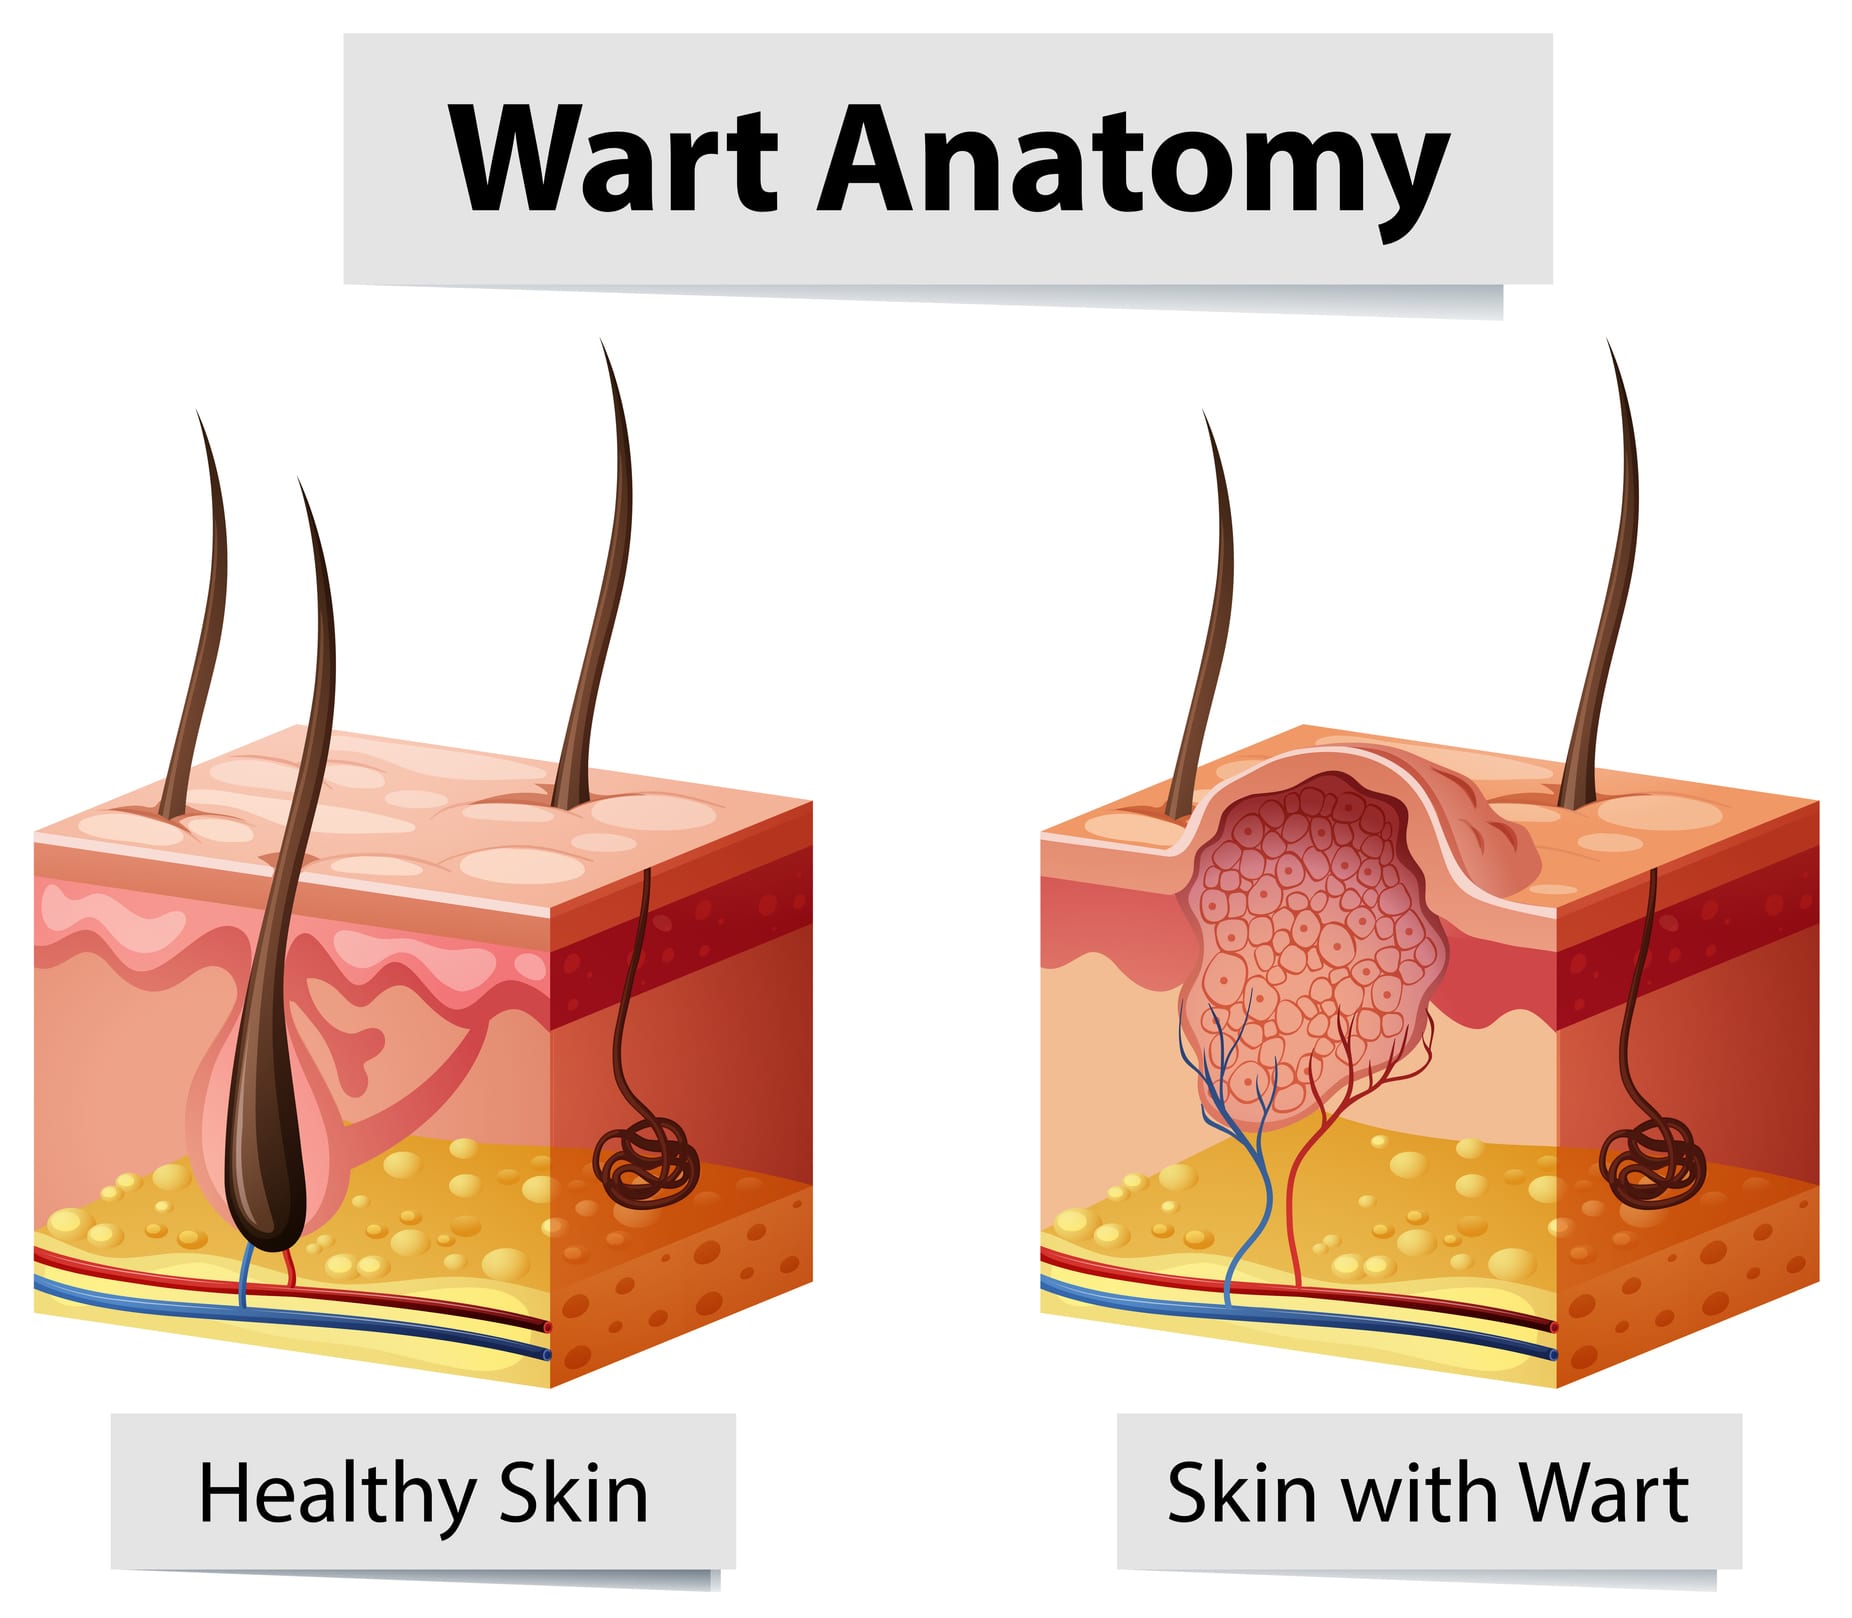
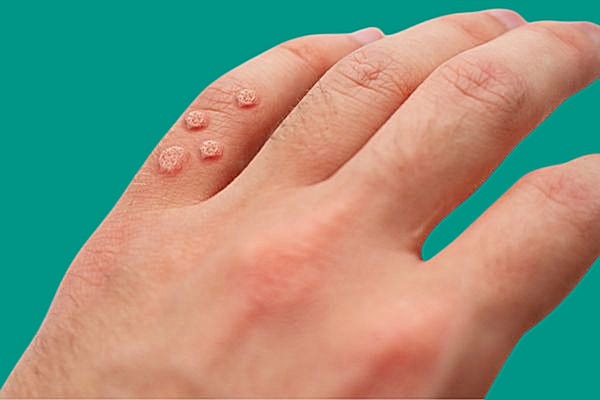
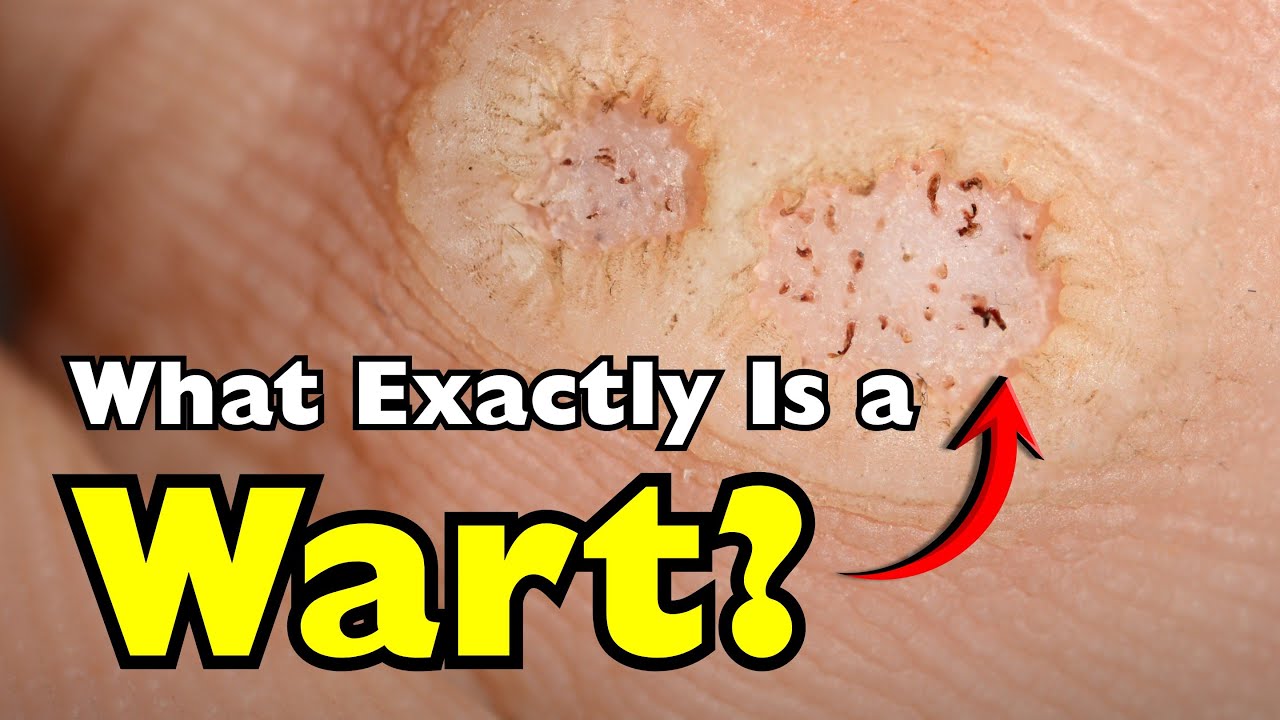
Warts are skin growths caused by the human papillomavirus (HPV). There are over 100 strains of this virus, and different ones target different parts of the body. The most common types you will encounter are common warts on the hands, plantar warts on the soles of the feet, flat warts on the face, and filiform warts near the mouth or eyelids. Each type has its own behavior and response to treatment, which matters more than people realize. You get warts through direct skin-to-skin contact with someone who has one, or by touching a surface that a wart-bearing person contacted recently. The virus enters through tiny breaks in the skin that are often too small to notice. Walking barefoot in a communal shower or pool deck is one of the most common ways plantar warts show up. Shaving over an area with tiny micro-cuts can spread flat warts across your face or legs. The virus does not need a large open wound. A paper cut from last Tuesday is enough. I spent years seeing this in practice, and the pattern is always the same. People think warts only spread through direct contact with another person's wart. That is only half the story. Indirect transmission through shared towels, razors, nail clippers, and gym equipment accounts for a significant portion of cases. The virus can survive on surfaces for days depending on moisture and temperature. A damp towel left in a locker room bag is basically a petri dish for HPV.
Another thing most people miss is that the virus can remain dormant in the skin for weeks or even months before a visible wart appears. So if you developed a wart three months after swimming at a particular pool, blaming the pool might be accurate, but your immune system had the opportunity to clear it during those three months and simply didn't. This is why some people get warts constantly while others touch the same surfaces and never develop one. Immune competence is the single biggest factor in whether HPV takes hold.
Why Some Warts Come Back After Treatment
This is where people get frustrated. You pay for cryotherapy, you apply salicylic acid for six weeks, and two months later a new bump appears in the exact same spot or right next to it. The reason is that most at-home and even clinical treatments only address the visible portion of the wart. The viral infection extends into the surrounding skin beyond what you can see. When you cauterize or peel away the top layer, the virus in the adjacent tissue is still active and will eventually produce new growth. I once had a patient who kept getting plantar warts on the same spot of her heel despite repeated freezing sessions at the dermatologist. She was paying for treatments every four to six weeks and going back three or four times. The breakthrough came when we stopped treating the wart itself and started focusing on the environment. She had been wearing the same pair of work boots for five years without rotating them. The interior was moist, warm, and full of viral particles from previous warts she had shed. We switched her to rotating between two pairs of boots and treated the interior of the old pair with an antifungal powder daily. The new warts stopped appearing within three months. It was not a treatment issue. It was a reservoir issue. Here is a counter-intuitive point that clinicians don't always emphasize enough. Warts are often most contagious when they are irritated or bleeding. Picking at a wart, shaving over it, or having it rub against tight shoes spreads viral particles into the surrounding skin. This is called autoinoculation and it is why people tend to get clusters of warts rather than isolated single warts. The moment you stop picking, the spread usually slows down significantly.
Get the Full Details
What Actually Works for Removal
Salicylic acid is the first-line treatment for most common warts and it has decent evidence behind it. The key is consistency and proper application technique. You soak the wart in warm water for five minutes, file away the dead skin on the surface with a disposable emery board, apply the acid directly to the wart only, and cover it. Repeat this daily for eight to twelve weeks. If you skip days or apply it to surrounding healthy skin, you will get irritation without results and might actually damage the skin barrier enough to let the virus spread further. Cryotherapy using liquid nitrogen works faster but it is not a guaranteed one-and-done. Most people need two to four sessions spaced two to three weeks apart. The mechanism is creating a blister under and around the wart, which lifts the infected tissue away from the healthy skin below. The blistering is what kills the virus in that area. If the freeze is too shallow, the viral reservoir remains intact and the wart regrows. If it is too deep, you risk scarring, which is especially problematic on weight-bearing areas like the soles of the feet. For stubborn warts that resist both salicylic acid and cryotherapy, cantharidin is an option some dermatologists use. It is a blistering agent derived from blister beetles that is painted onto the wart and left on for a few hours. It causes a controlled blister beneath the wart, similar to cryotherapy but without the cold. The advantage is that it is painless during application and can reach deeper tissue. The downside is that it is not available in all clinics and the blister that forms can be uncomfortable for a day or two.
Another approach that gets mentioned less is electrosurgery or curettage. This is a minor procedure where the wart is scraped away and the base is cauterized. It tends to work well for filiform warts and plantar warts that have failed other treatments. The trade-off is that it leaves a scar and requires local anesthesia. For facial warts, scarring is an unacceptable risk for many people, which is why topical treatments or laser therapy are preferred even though they take longer.
What Does Not Work
Duct tape occlusion is one of the most commonly recommended home remedies and the evidence is mixed at best. Some small studies showed marginal improvement over placebo, while others found no difference. The theory is that suffocating the wart triggers an immune response. In practice, the occlusion alone rarely does much. If you are going to try it, combine it with salicylic acid and file the surface regularly, otherwise you are just keeping a wart moist and warm, which is the opposite of what you want. Garlic, apple cider vinegar, and other folk remedies have no credible clinical evidence supporting them. Some people report success, but anecdotal reports are not reliable indicators. The risk with these home remedies is that they often cause chemical burns on the surrounding skin, which damages the barrier and can actually increase the chance of spreading the virus to adjacent areas. I have seen patients bring in raw garlic slices stuck to their fingers with first-degree burns around the wart they were trying to treat. Over-the-counter wart removal kits that use a freezing spray are convenient but they are not as cold as liquid nitrogen used in a clinic. The temperature difference means the freeze is shallower and less effective. They can work for small, recent warts but for established warts that have been present for months, the results are usually disappointing. The cost per session is lower, but the number of sessions required tends to be higher, which narrows or eliminates any savings.
When to See a Professional
If a wart is painful, bleeding, changing color, or located on your face or genitals, you should see a dermatologist. Facial warts carry a higher risk of scarring and misdiagnosis. Genital warts are caused by different HPV strains and require completely different management. A wart on the face that you treat aggressively with acid or freezing might look fine after it heals, but the scarring could be cosmetically significant. A professional can distinguish between a wart and other skin growths like seborrheic keratosis, skin tags, or in rare cases, squamous cell carcinoma, which can sometimes be mistaken for a wart. Warts that do not respond to any treatment after three months of consistent effort should be evaluated by a professional. At that point, the standard first-line options have likely been exhausted and you need access to stronger interventions or a different diagnostic approach. Immunocompromised individuals, including people with HIV, organ transplant recipients, and those on biologic medications, should seek professional care early. Their warts tend to be more numerous, more resistant to treatment, and more likely to recur. The bottom line is that warts are annoying but manageable. The virus lives in the skin, not in the blood, and your immune system is fully capable of clearing it given enough time. Treatment speeds things up and reduces discomfort, but it does not eliminate the possibility of recurrence because the virus can hide in surrounding tissue. Consistency with treatment, avoiding trauma to the area, and keeping the surrounding skin healthy are the factors you can actually control.