The Medical Reality of Pregnancy Termination
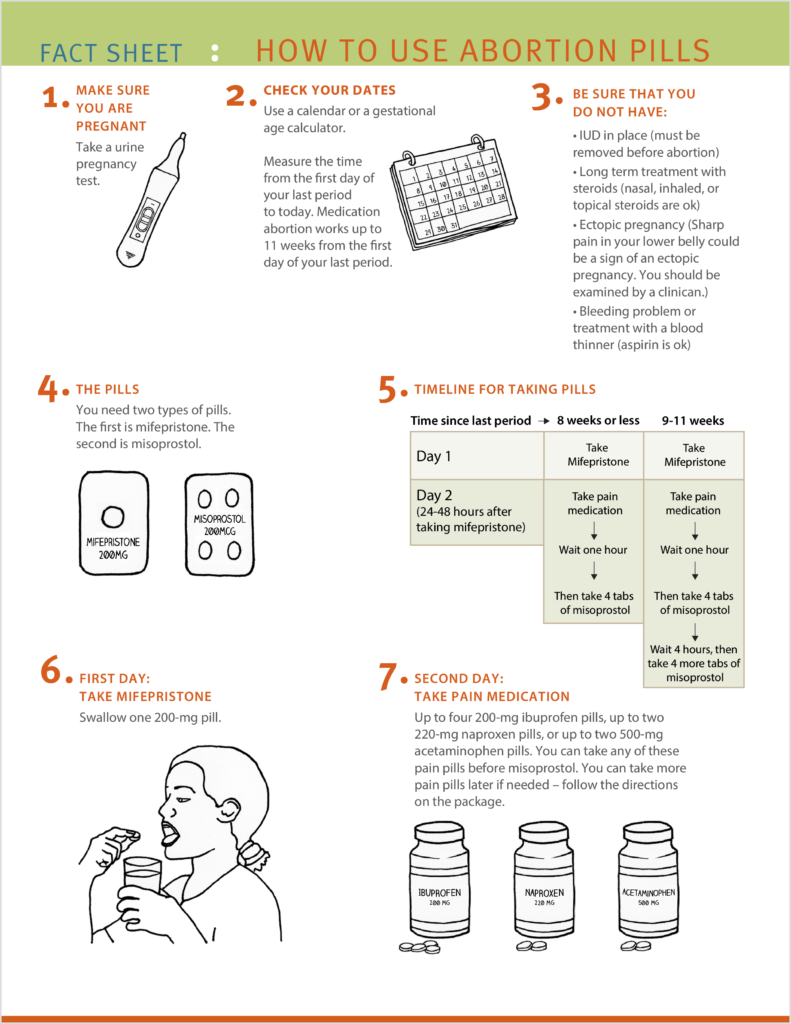
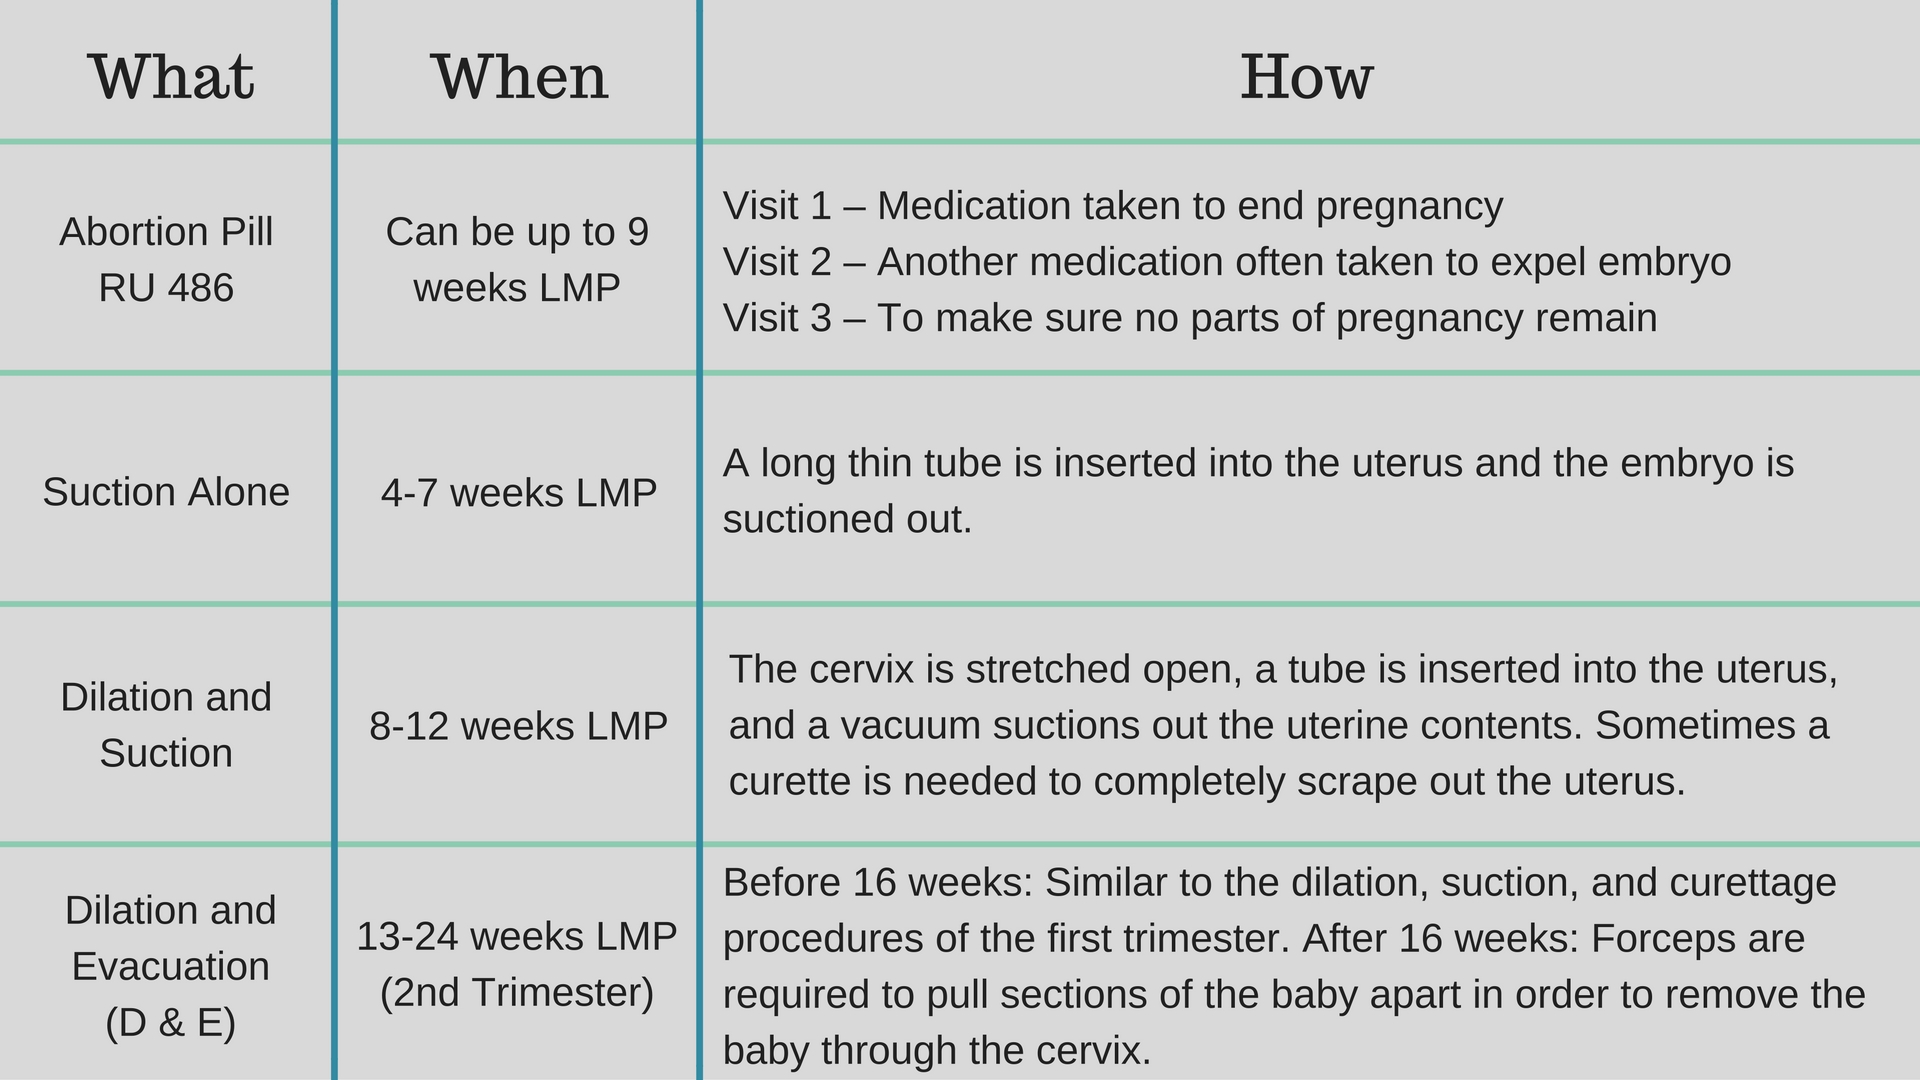
Most people asking this question want a straightforward breakdown of what actually happens during the two main types of abortion procedures. The answer depends heavily on how far along the pregnancy is, but both methods are well-established medical practices with decades of clinical data behind them. There are really two categories here: medication abortion and procedural abortion. They work differently and are used at different stages of pregnancy. Medication abortion typically involves two drugs taken about 24 to 48 hours apart. The first drug is mifepristone, which blocks progesterone — the hormone that keeps the uterine lining supporting the pregnancy. Without progesterone, the pregnancy cannot continue. A day or two later, misoprostol is taken, usually through the cheek or under the tongue. That drug causes the uterus to contract and expel its contents. This method is generally used up to about 10 to 11 weeks of pregnancy, depending on local guidelines and provider protocols.
The process feels like a very intense period for most people. Cramping starts within a few hours of taking the second medication. Bleeding is heavier than a normal period and can include clots. Nausea, diarrhea, and chills are common side effects too. Most people manage this at home over the course of several hours. Procedural abortion, sometimes called aspiration or suction abortion, is what most people are talking about when they say "clinic abortion." It's a quick in-clinic procedure. The provider uses local anesthesia to numb the cervix, then gently opens it slightly with small dilators. A thin tube connected to a syringe or a suction device is passed through the cervix into the uterus. The pregnancy tissue is removed using gentle suction. The whole procedure typically takes about 5 to 10 minutes from start to finish, though you'll spend a couple hours at the clinic for preparation and recovery observation. I've seen people assume the procedure is some kind of surgical operation with incisions. It isn't. There are no cuts, no general anesthesia in most cases, and no hospital stay involved. The word "aspiration" comes from the suction method, not from any cutting instrument. A lot of anxiety comes from misinformation about what the procedure actually looks like.
For later pregnancies, typically past 12 to 14 weeks, a procedure called dilation and evacuation (D&E) is used. This requires more cervical preparation over a day or two before the actual procedure, which is similar in concept to aspiration but involves additional instruments to remove the tissue. Dilation and introduction is another option in some places later in pregnancy, but it's less commonly used due to longer time requirements and different risks. Here's something people don't usually expect: pain management during these procedures is often much better than anticipated. Local anesthesia numbs the area effectively, and the cramping afterward is usually manageable with over-the-counter pain relievers like ibuprofen. I've talked to patients who expected to need prescription pain medication and ended up needing nothing stronger than Advil. That's not true for everyone, but it's common enough that providers will ask about your pain tolerance and preferences beforehand. One edge case worth mentioning: some people have a uterus that's positioned unusually, like significant retroversion or a septate uterus. In my experience, this can make the procedure slightly more technically challenging for the provider. It doesn't make it unsafe, but it does mean the provider needs to be comfortable with anatomical variations. Always mention any known uterine abnormalities or previous surgeries to your provider so they can plan accordingly. I once worked with someone who had a prior myomectomy that altered her uterine shape, and the clinic simply scheduled extra time and used ultrasound guidance to navigate it safely.
Get the Full Details

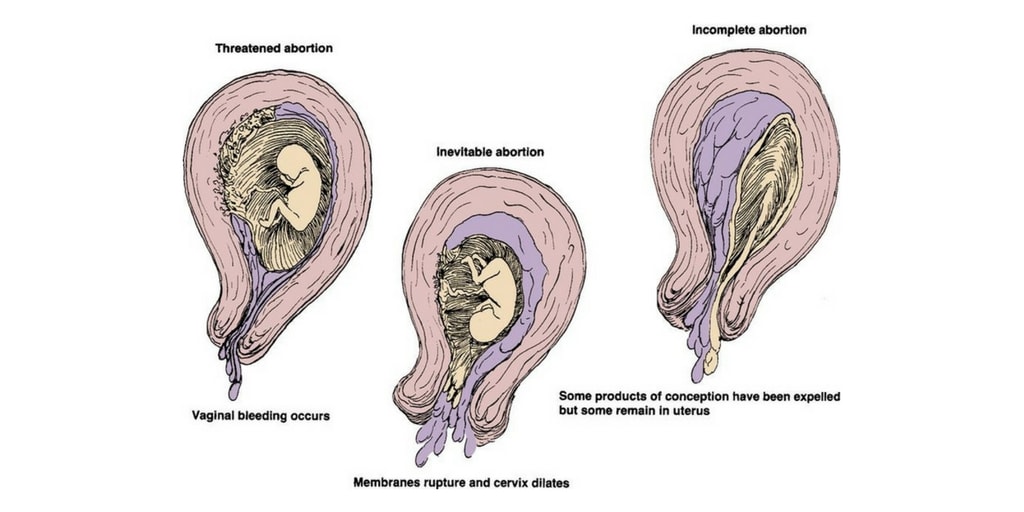
Risks exist with any medical procedure. With medication abortion, the main concern is incomplete abortion, where some tissue remains. This happens in about 2 to 5 percent of cases. If that occurs, a follow-up procedure may be needed. Heavy bleeding is rare but serious — so rare that the American College of Obstetricians and Gynecologists reports it in less than 1 percent of medication abortions. Infection is also uncommon, occurring in well under 1 percent of cases when the procedure is done properly. For procedural abortion, the risks are similarly low. Uterine perforation occurs in roughly 1 in every 1,000 procedures. Cervical injury is possible but uncommon with modern techniques. The risk of future fertility problems is extremely low when the procedure is performed by a trained provider. This is important because there's a persistent myth that abortion causes infertility, and the medical evidence simply doesn't support it. One practical detail that catches people off guard: after a medication abortion, most providers recommend waiting about a week before using tampons or having sex to reduce infection risk. After a procedural abortion, the same advice usually applies. It's not because the risk is high — it's just standard precaution to let the cervix close back up completely.
The legality and availability of these services vary enormously by location. Some places have no restrictions beyond standard medical care. Others have gestational limits as early as 6 weeks, or mandatory waiting periods, or required ultrasounds before the procedure. If you're searching for information, the local regulations matter just as much as the medical information. Many providers offer telehealth consultations now, especially for medication abortion, which has expanded access significantly in recent years. If you or someone you know is considering this option, the most practical step is contacting a licensed reproductive health provider or clinic. They can give you specific information about what's available in your area, what the timeline looks like, and what to expect based on your individual situation. General web searches will give you broad information, but they won't replace a conversation with a qualified professional who knows your medical history.