CBT for Generalized Anxiety Disorder: What Actually Happens in Therapy
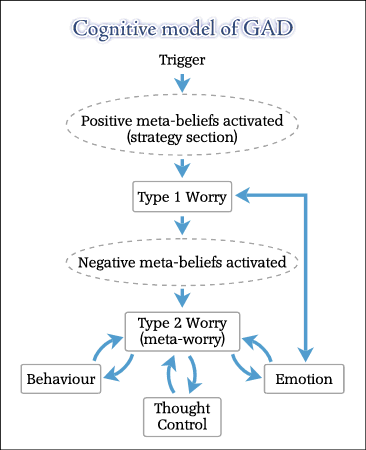
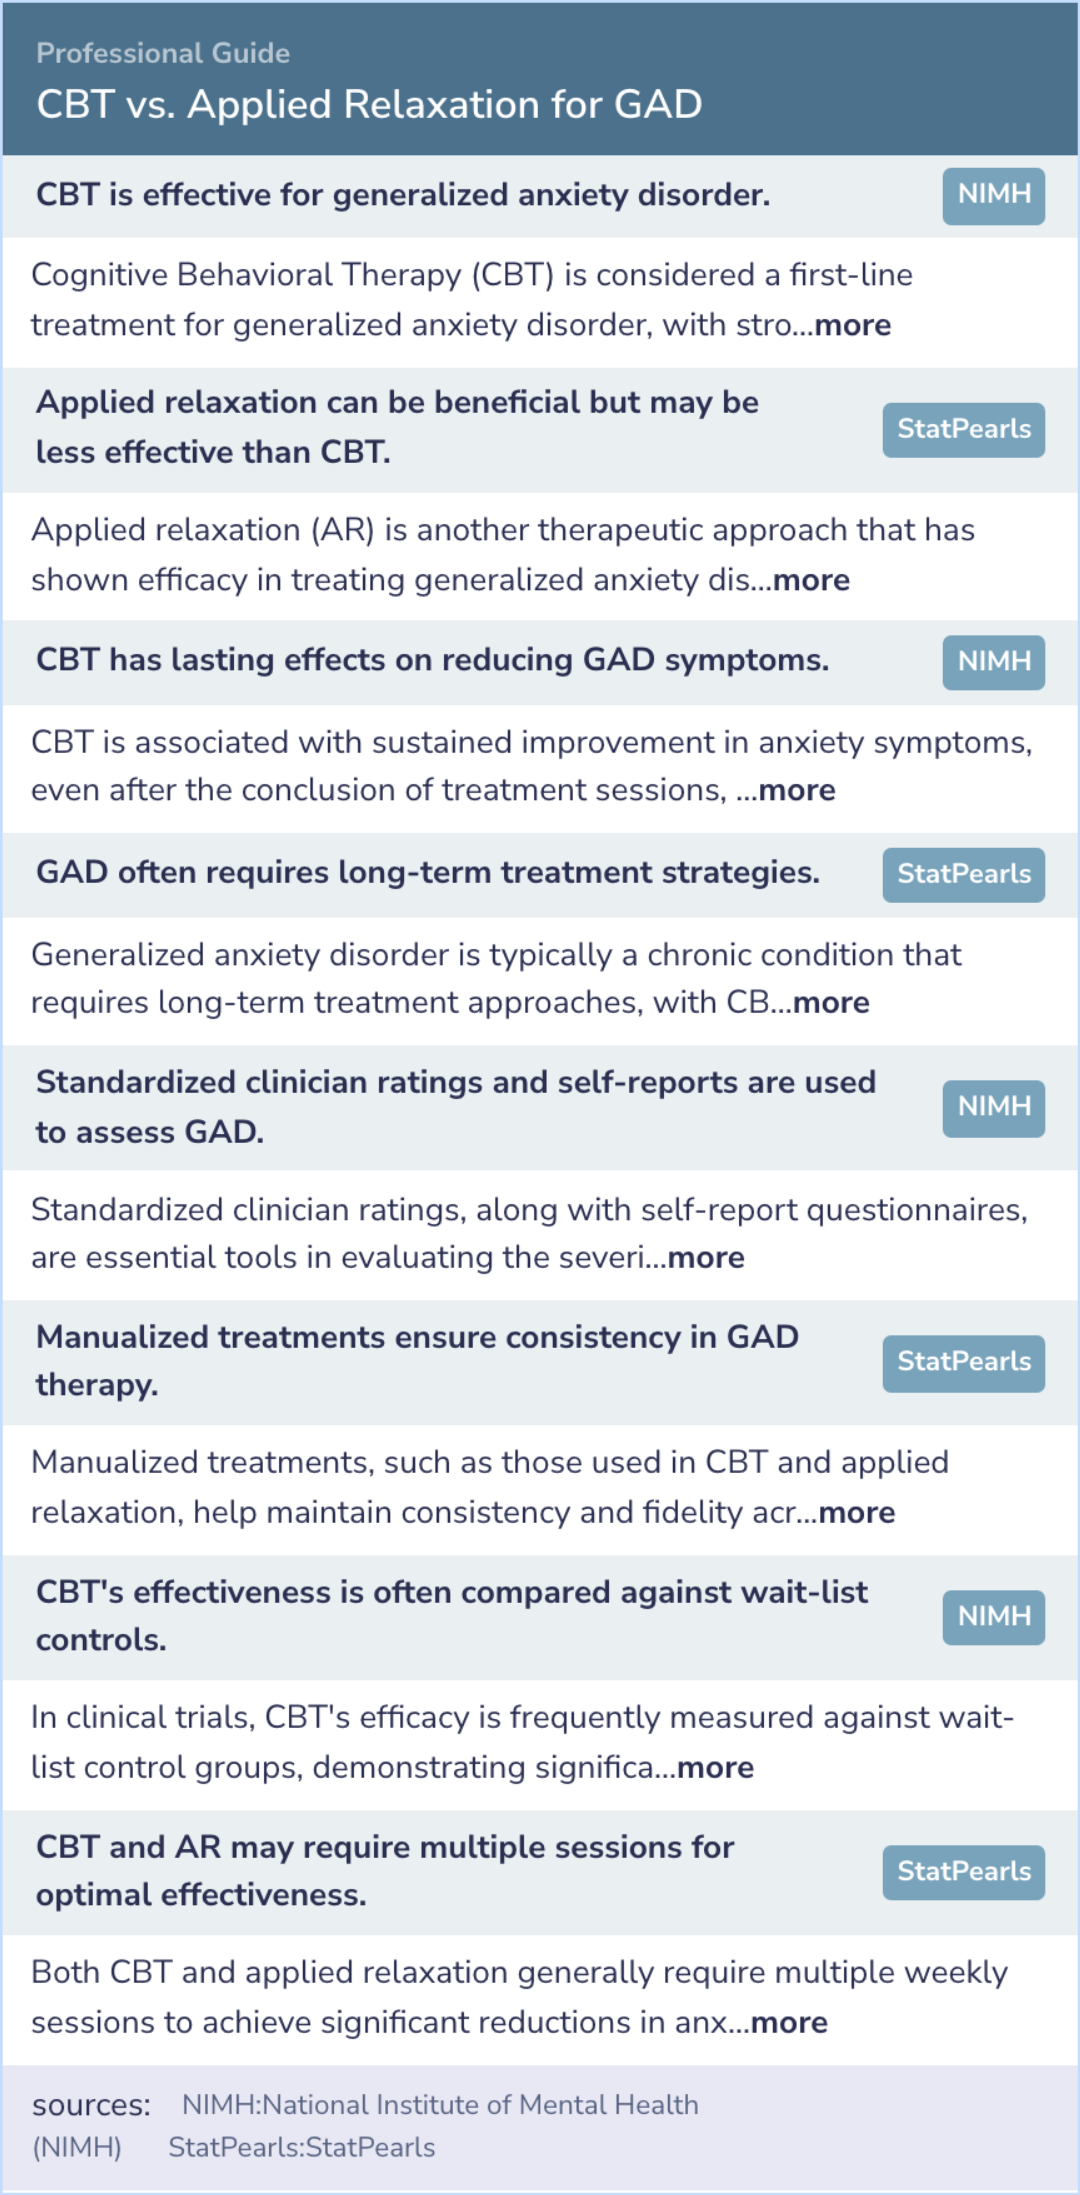
I've spent years working with clients who have GAD, and I can tell you that CBT is one of the more reliable tools we have. It's not magic, it's not a cure-all, but it does something specific and measurable for most people. The framework is straightforward enough that you can understand it without a psychology degree, which is actually part of why it works. Cognitive Behavioral Therapy operates on a simple premise: your thoughts influence your feelings and behaviors. With GAD, that means the endless worry loops aren't just random—they're patterns you can identify and change. The therapist helps you catch those patterns, challenge them, and replace them with more grounded thinking. It sounds basic because it is basic. That doesn't make it less effective. In practice, sessions usually involve tracking your worries, identifying the cognitive distortions driving them, and testing whether your fears hold up to scrutiny. You'll keep thought records. You'll practice reframing techniques. Eventually, the spiral of "what if" starts to slow down because you've built a counter-narrative in your head. Most people see meaningful reduction in symptoms within 12 to 20 sessions. I've seen clients cut their daily anxiety levels in half within eight weeks when they actually did the homework.
What Makes CBT Different for GAD
Not all anxiety disorders respond to CBT the same way. With GAD specifically, the treatment targets something called worry exposure. That's when you deliberately sit with uncertainty instead of trying to resolve every hypothetical scenario. Standard exposure therapy is well known for phobias, but worry exposure is less obvious and often harder to stick with. Your instinct is to figure things out, to mental-circle until you reach some kind of answer. CBT asks you to stop doing that and simply tolerate not knowing. One counter-intuitive thing I've noticed is that clients who try to use CBT as a problem-solving tool often stall out. They want to resolve every worry logically. But GAD worries aren't really problems to solve—they're habits to unlearn. The ones that work are the ones who accept that some questions don't have answers and practice staying with that discomfort anyway.
What to Expect Week by Week
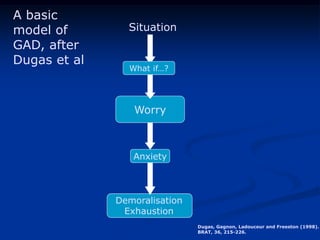
Early sessions focus on psychoeducation. You learn how the anxiety cycle works—trigger, thought, emotion, physical response, avoidance. It's not particularly exciting but it gives you a map. From there, you start identifying your personal worry themes and the thoughts underneath them. This is where the thought record comes in, and honestly, it's the part people either love or hate depending on whether they're honest with themselves. By weeks four through eight, you move into behavioral experiments. You test your predictions against reality. If you think "if I don't check my phone every ten minutes, something bad will happen," you don't check your phone and you observe what actually occurs. Nine times out of ten, nothing happens. Your brain slowly learns that the world doesn't end when you don't catastrophize about it. Late-stage sessions shift toward relapse prevention. You consolidate the skills, review what worked, and plan for high-risk situations. Relapse isn't failure—it's data. People who come back for a booster session or two after completing treatment tend to maintain gains better long-term.
Get the Full Details
The Hard Parts Nobody Mentions
CBT requires actual work between sessions. If you treat it like a passive treatment where you just show up and talk, it won't do much for you. The homework isn't optional filler. I've seen clients improve dramatically in six weeks because they practiced daily, and others plateau for months because they skipped the worksheets. Another thing people don't talk about is that CBT can feel uncomfortable at first. Facing your thoughts directly means sitting with anxiety, not running from it. Some clients drop out during the first month because the exercises trigger them more than help them initially. That's normal but it's also real. If you're struggling, you can adjust the pace. You don't have to power through everything at once. There's also the limitation that CBT doesn't address trauma or underlying neurochemical issues as directly as other approaches might. If your anxiety has a strong PTSD component or is tied to a medical condition, CBT alone might not be enough. Combining it with medication or trauma-informed therapy often produces better outcomes. I recommend talking to a professional about what combination makes sense for your situation rather than assuming one approach fits everyone.
What I've Learned from Watching This Work Over the Years
One edge case that comes to mind is clients who are highly intellectual. They get stuck in analysis paralysis during CBT because they can deconstruct every concept but never actually do the exercises. The workaround I found effective was assigning very small, almost ridiculous behavioral experiments. Like setting a timer for two minutes and not engaging with a worry thought at all. It sounds trivial but it builds the muscle. Once they could do the tiny version, the bigger ones became possible. The other thing I'd note is that CBT works best when the therapist-client fit is decent. A rigid therapist who treats it like a cookbook protocol can miss what's actually going on for the client. The technique matters but so does the relationship. People who feel understood in therapy stick with it longer and get better results. If you're considering CBT for GAD, expect it to take effort. Expect to feel some discomfort. And expect it to actually help if you commit to the process. It's not the only option out there but it's one of the most evidence-backed ones we have, and that's worth something.