The Couch Is Dead. Long Live the Couch.
Classic psychoanalysis is the Freudian model most people picture when they think about therapy. Five days a week, patient on the couch, analyst out of sight, free association, dream interpretation, transference analysis as the primary vehicle of change. It's a labor-intensive undertaking that assumes the patient has the time, money, and psychological flexibility to commit to what amounts to a lifestyle restructuring. The average treatment runs anywhere from three to five years. Contemporary psychodynamic therapy is still psychodynamic. It still cares about unconscious processes, transference, defense mechanisms, and early relational templates. But it looks more like what you'd actually find in a private practice office today. One session per week, usually, faces-to-face, often time-limited at 20 to 40 sessions depending on the model. The therapist is more active and engaged. The focus narrows to a clearly identified focal conflict rather than treating the entirety of the personality.
How Does Contemporary Psychodynamic Therapy Differ From Classic Psychoanalysis
The differences aren't just cosmetic. They represent genuine theoretical divergence about how change actually happens in the therapeutic room. In classic analysis, the analyst maintains neutrality and anonymity. You're not supposed to disclose anything personal, respond warmly, or offer advice. The idea is that the blank screen forces the patient to project onto the therapist, making transference reactions available for interpretation. Short-term psychodynamic therapy flips that. The therapist is allowed to be a real person in the room. Warmth is permitted. Self-disclosure, when used sparingly, is sometimes considered useful. The therapeutic relationship itself becomes curative, not just a vehicle for interpretation. The technical stance is where the biggest gap sits. In Freud's original setup, the analyst interprets resistance before understanding. You don't explore content until the patient's defenses against the material become visible. Modern psychodynamic therapists often do the opposite. They build alliance first, then gently apply interpretive pressure. The sequence matters because research suggests that interpreting defenses in a patient who doesn't feel understood produces resistance, not insight.
Frequency is the second major divider. I've worked with patients who were analyzed at the classic frequency early in their careers. It works for a very small subset of people who present with high ego strength, good reflectivity, and genuine neurotic conflict rather than characterological rigidity or personality disorder. For most people, five times a week is unsustainable. They can't afford it. They can't structure their lives around it. They drop out within three months because the setup exceeds their actual capacity to tolerate the regression. Time framing represents another structural difference. Classic analysis is unbounded. There's no endpoint built into the arrangement. Contemporary psychodynamic work, especially the Davanooshi and Sifneos models, builds termination into the first session. The patient signs up knowing there will be an end. This changes how material emerges. Patients often mobilize more quickly because the clock is visibly ticking. I ran into a specific case about two years ago where a patient came in diagnosed with what looked like mild obsessive-compulsive personality structure. Classic analysis would have suggested long-term work because the defenses were rigid and the transference would likely be intensely hostile and intellectualized. Instead, I set a frame of 25 sessions with a focal conflict around authority dependency. We named it directly in session two. The patient pushed back hard, called the approach superficial, questioned whether limiting time could possibly address the depth of the issue. That pushback was the transference. We interpreted it within three sessions and the resistance softened considerably. We ended at session 23 with measurable change on the clinical global impression scale. A classic analyst would have kept going for three years, maybe achieved similar outcomes, maybe not. The evidence base strongly favors time-limited models for this kind of presentation.
Get the Full Details
Technique Under Pressure
Interpretation timing is the skill that separates competent psychodynamic work from amateur hour. In classic analysis, you wait. You wait for the transference neurosis to develop fully. You wait for the repetition to become unavoidable. Then you interpret. That patience is a luxury that weekly therapy doesn't afford. You have to be faster, sharper, and more strategic about when to raise an interpretation versus when to let it sit. The focal conflict technique, developed by Alexander and French and later refined by Hanna and others, gives therapists a concrete way to stay anchored. You identify a recurring triangle: the self in relation to others, the problematic response, and the withheld desired response. Every session, you check back against that triangle. If the patient drifts into random biography, you gently bring them back. This structure keeps time-limited therapy from collapsing into supportive counseling, which is a common failure mode when therapists aren't well-trained in the model. Supportive psychodynamic therapy occupies a middle ground that's often misunderstood. It's not full analysis and it's not purely supportive therapy in the non-dynamic sense. The therapist maintains a psychodynamic lens while using more encouragement, clarification, and confrontation than interpretation. It's appropriate for patients with lower ego strength, borderline organization, or acute crisis. The mistake beginners make is confusing supportive technique with abandoning the psychodynamic framework. You can be supportive and still track transference, still notice defenses, still understand the material unconsciously. Those are not mutually exclusive.
Here's something most introductory textbooks don't emphasize enough. Transference doesn't need to be full-blown to be therapeutically useful. In classic analysis, you wait for the transference neurosis, a complete displacement of childhood object relations onto the analyst. In contemporary work, micro-transference moments happen constantly. A slight irritation at the therapist's question, a defensive intellectualization, a sudden silence. These are treatable in the moment without waiting for a full transferential configuration. This is one reason shorter treatments can work. You don't need the cathedral. You can work with the bricks as they appear.
Where the Model Breaks Down
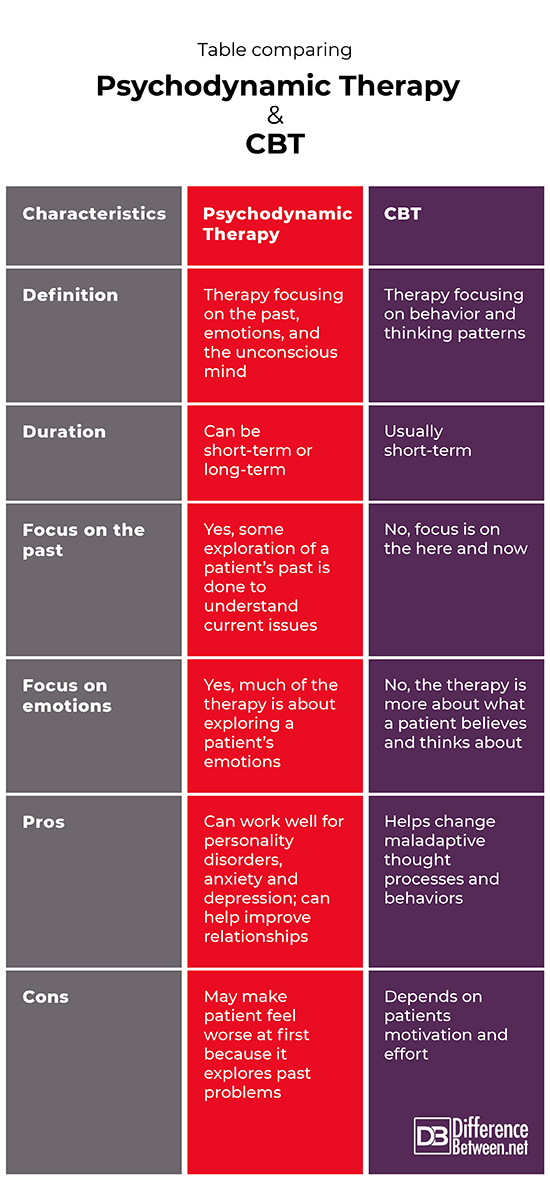
Psychodynamic therapy is not a universal solution. It performs poorly with acute psychosis, active substance dependence, severe borderline personality disorder without adequate stabilization, and situations requiring immediate behavioral intervention. There's also a class bias that deserves mention. The original psychoanalytic model assumed a patient who could afford multiple sessions per week for years. Modern adaptations have made it more accessible, but even 20 to 40 weekly sessions represents a significant time and financial commitment that excludes a large portion of the population. The evidence base is stronger for time-limited psychodynamic therapy than for classic analysis, primarily because it's easier to study. Meta-analyses show moderate to large effect sizes for personality disorders and depression, with gains that tend to continue after treatment ends, which is one of the model's more attractive features. Classic psychoanalysis has far less empirical support, not because it doesn't work but because the methodology for studying a five-year, five-times-weekly treatment is extraordinarily difficult. If you're looking for a practical alternative for clients who can't commit to any form of dynamic therapy, supportive structured therapy or CBT provides more immediately measurable outcomes in fewer sessions. That's not a value judgment about psychodynamic work. It's an acknowledgment that different problems require different tools. Obsessive rumination responds well to exposure and response prevention. Acute panic disorder responds to interoceptive exposure. Psychodynamic therapy excels at chronic relational patterns, characterological issues, and the kind of repetitive suffering that clients have been carrying for decades without understanding why.

The core theoretical commitment that survives across all variations remains the same. Behavior and subjective experience are determined by unconscious processes. Early relationships shape adult patterns. Resistance is both an obstacle and a clue. Understanding leads to change, but understanding must be emotionally experienced, not just intellectually acquired. Everything else, the frequency, the stance, the duration, the technical sequence, those are tactical decisions shaped by what the patient can actually tolerate and what the clinical situation demands.