The Innate System Is Your Boring First Line of Defense
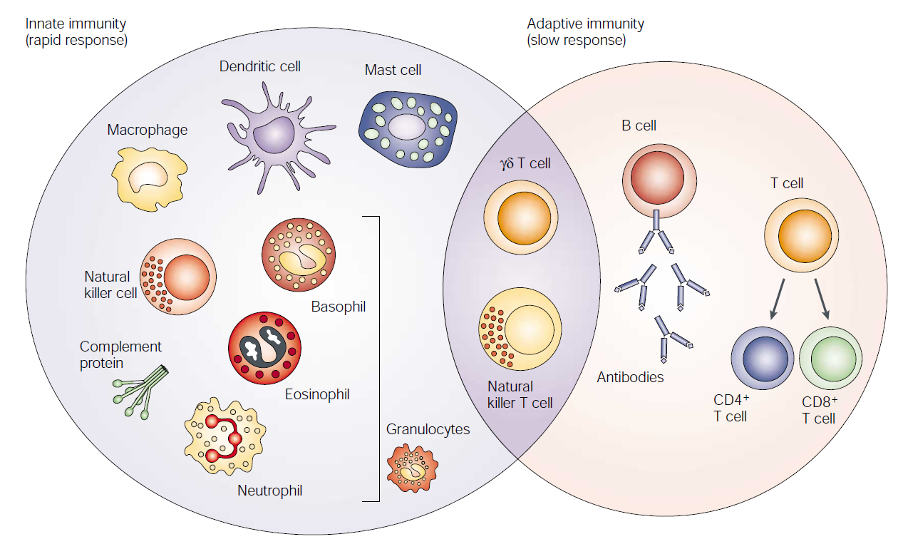
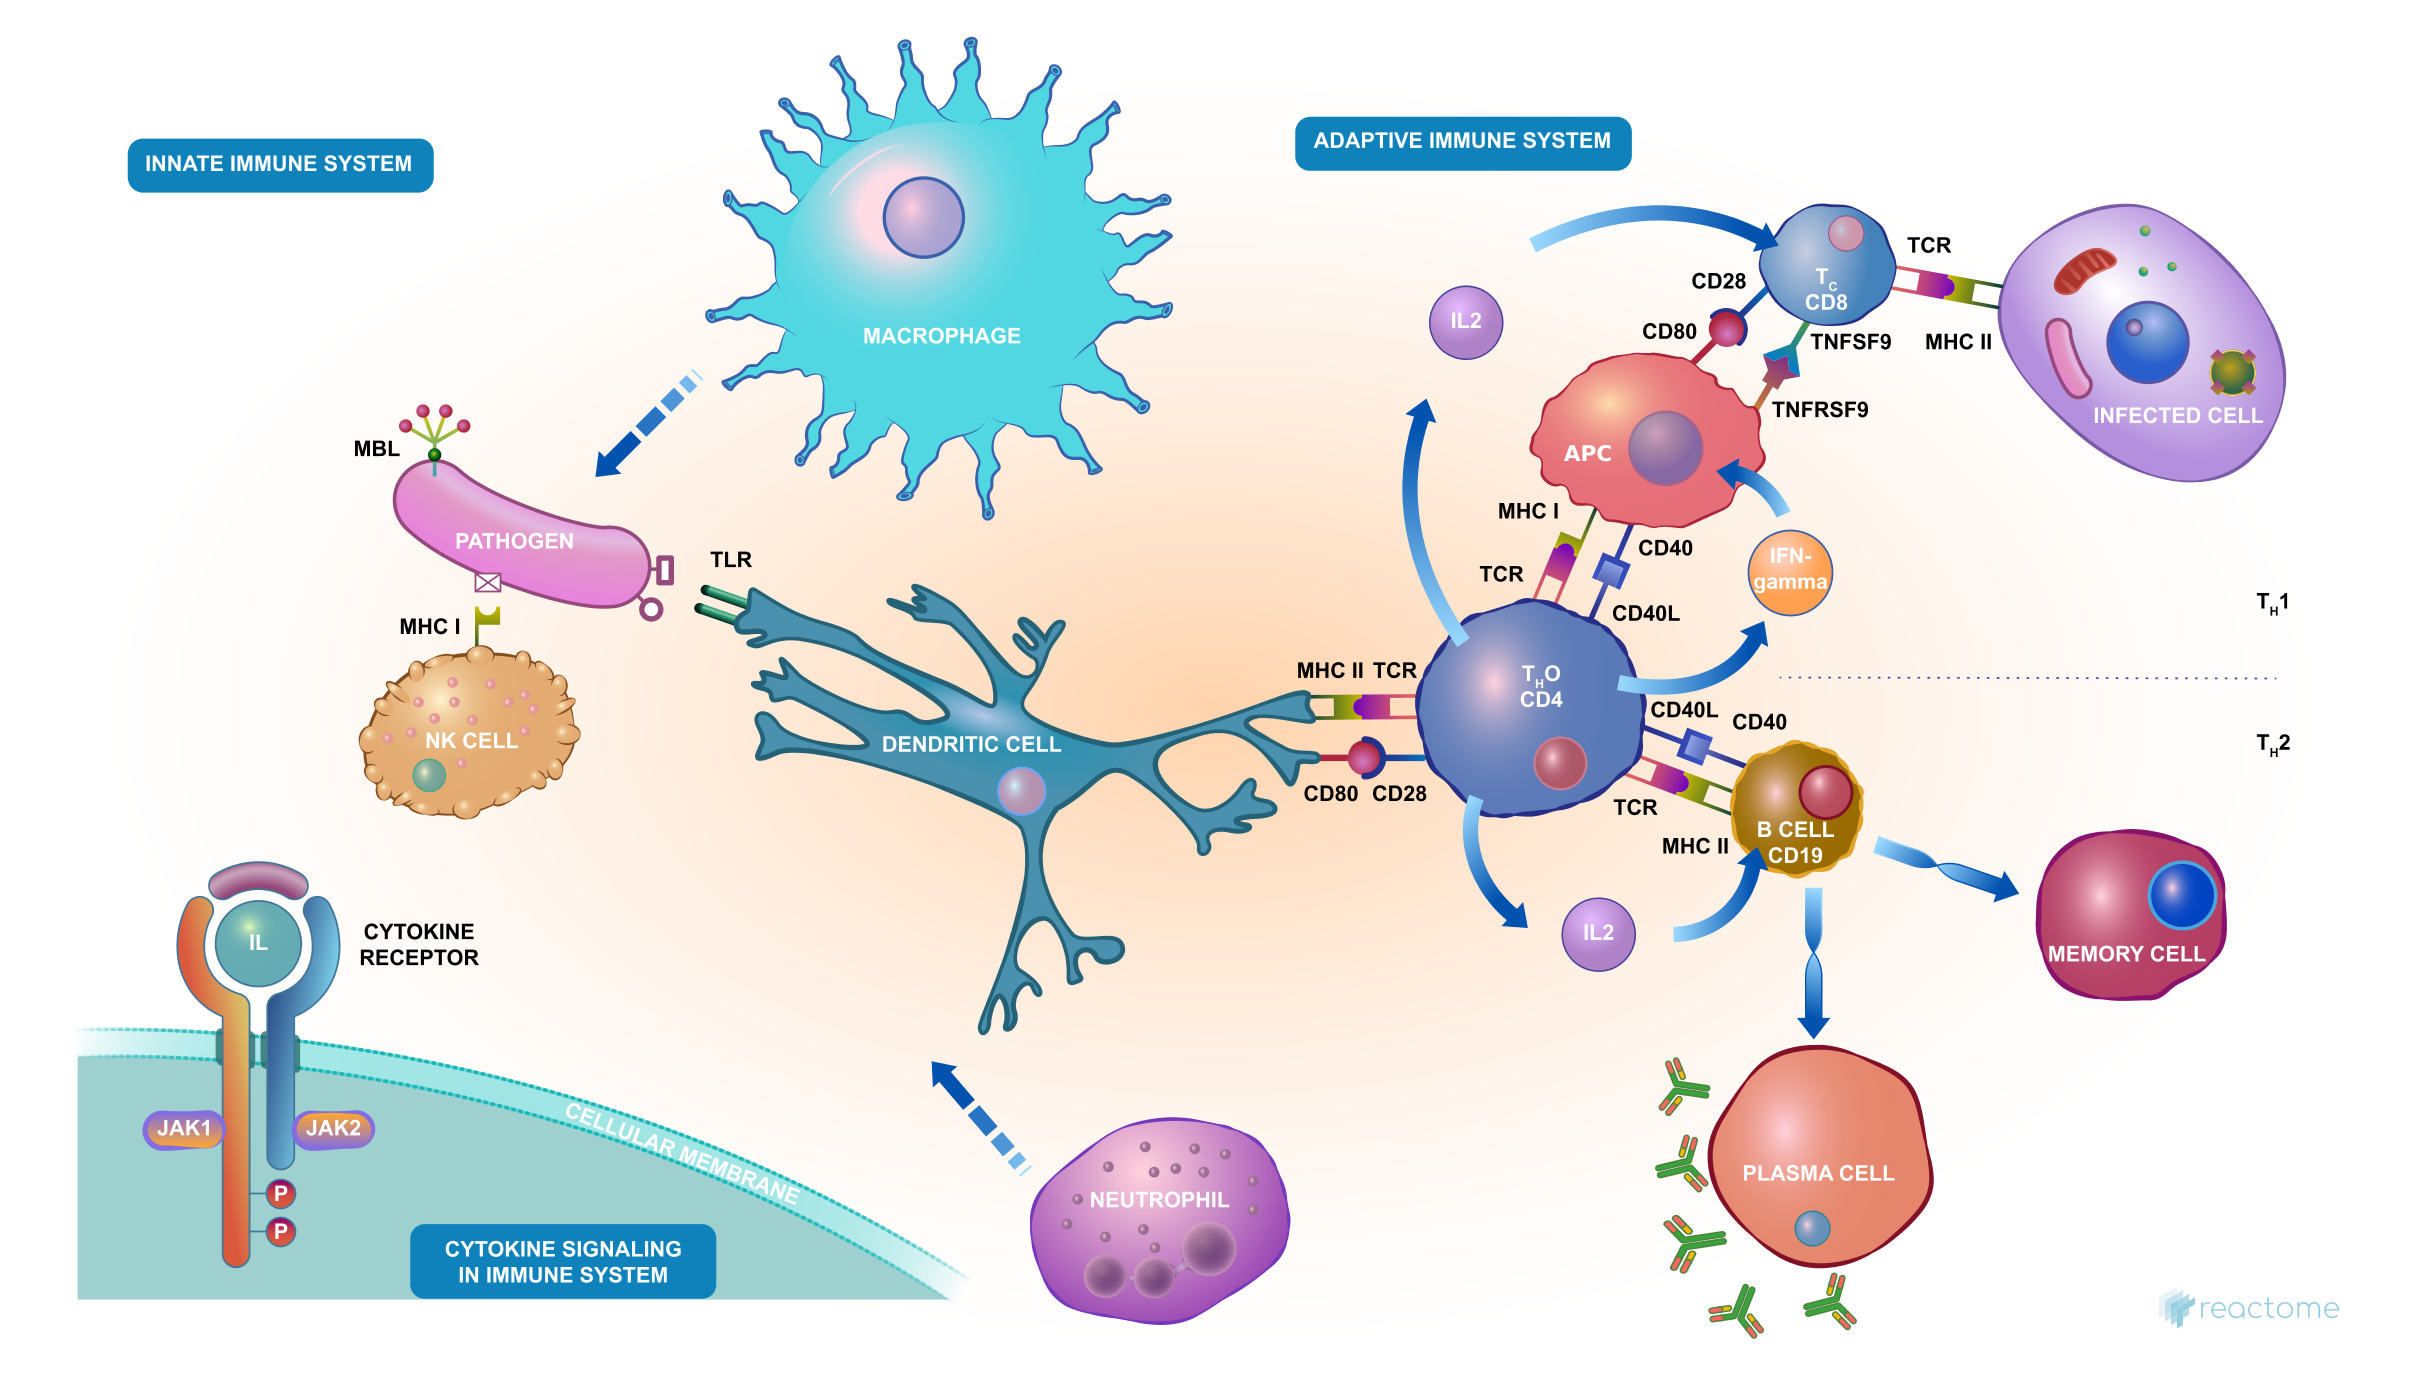
Your immune system is not a single thing. It is a network of cells, proteins, and signaling pathways that operate across multiple timelines and geographic zones in your body. When people ask How Does The Immune System Work, they usually expect one clean explanation. It does not work that way. The innate system responds in minutes. The adaptive system takes days to ramp up. Both are constantly running in the background whether you are sick or not. Macrophages patrol your tissues. They eat anything that looks foreign through a process called phagocytosis. Neutrophils arrive next in large numbers and release antimicrobial peptides. Dendritic cells are the messengers. They pick up pieces of whatever the macrophages ate, travel to the nearest lymph node, and present those pieces to T cells. That handoff is the moment innate immunity becomes adaptive immunity. Miss that step and the whole response stalls.
How Does The Immune System Work At The Molecular Level
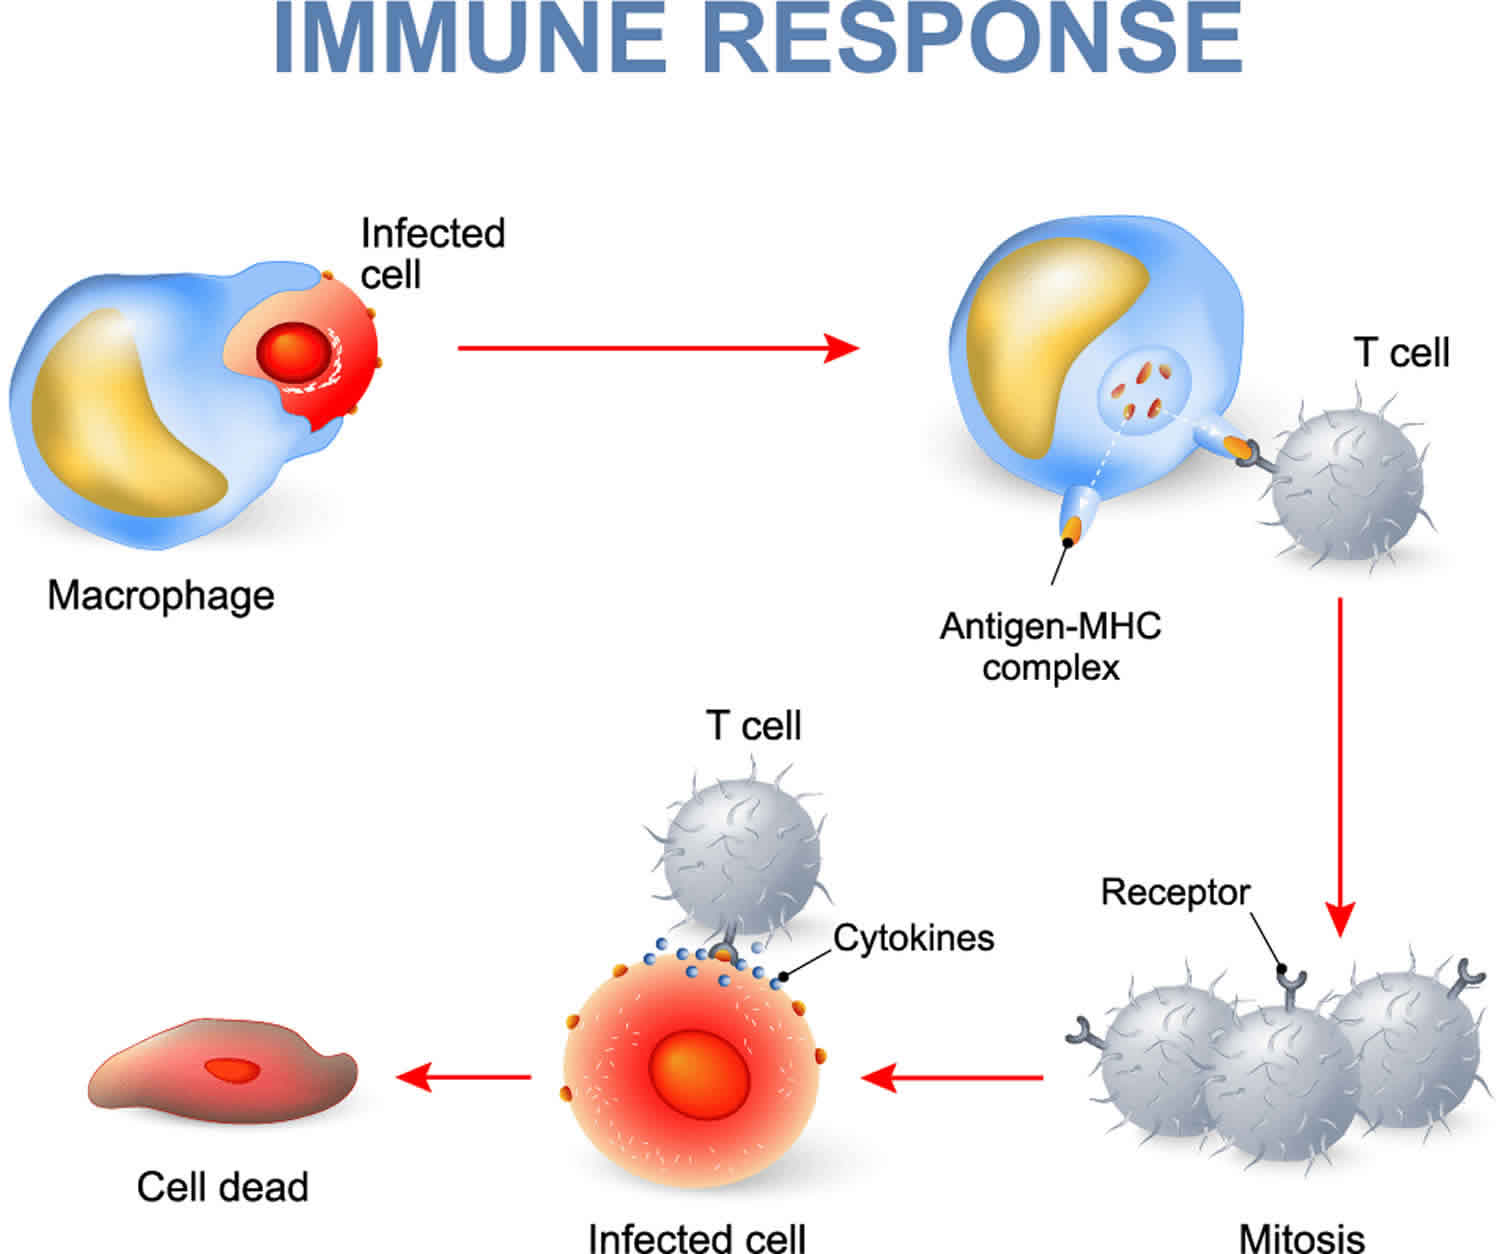
MHC molecules are the reason your immune system can tell friend from foe. Every nucleated cell in your body displays peptide fragments on MHC class I molecules. CD8 T cells check those fragments. If the fragment comes from a virus inside the cell, the T cell kills that cell. MHC class II molecules appear mostly on professional antigen-presenting cells. CD4 T cells read those and then coordinate the broader response by activating B cells and macrophages. The counter-intuitive part most people miss is that tolerance is not the default state. Your immune system is inherently reactive. It has to be actively taught not to attack you. Central tolerance happens in the thymus and bone marrow during development. Self-reactive cells get deleted there. But peripheral tolerance is where the real work happens. Regulatory T cells suppress autoreactive cells that escaped the thymus. Checkpoint proteins like CTLA-4 and PD-1 shut down overactive responses. When these mechanisms fail, autoimmunity follows. I spent two years working on a project involving HLA typing and transplant matching. The specific problem I ran into was a patient with a near-perfect HLA match who still rejected the graft because of minor histocompatibility antigens. Standard typing panels do not cover those variants. The workaround was switching to next-generation sequencing-based HLA typing that resolved ambiguities at the peptide-binding groove level. It added about three days to the reporting timeline but caught mismatches that conventional methods missed. Without that extra resolution, we would have proceeded with a graft that was never going to hold.
Adaptive Immunity Is Slower But More Precise
B cells produce antibodies. Each B cell carries a unique receptor generated through V(D)J recombination, a process that shuffles gene segments randomly to create enormous diversity. When a B cell encounters its matching antigen, it activates, proliferates, and differentiates into plasma cells that pump out antibodies at roughly a thousand per second. Some become memory B cells that persist for decades. That is why secondary exposures to the same pathogen are usually handled before symptoms appear. T cell activation requires two signals. Signal one is the T cell receptor binding to the antigen-MHC complex. Signal two is a co-stimulatory molecule like CD28 binding to B7 on the antigen-presenting cell. Without both signals, the T cell becomes anergic or dies. This is not a flaw. It is a deliberate safety mechanism to prevent accidental activation by bystander antigens. Cancer therapies that block checkpoint proteins like PD-1 work by removing the brake that tumors place on T cells, essentially restoring signal two in an environment where it was artificially suppressed. The complement system bridges innate and adaptive immunity in ways that are easy to overlook. It is a cascade of about thirty plasma proteins that get activated sequentially. Once the first component triggers, the reaction amplifies exponentially. C3b coats pathogens for opsonization. C5a recruits more immune cells to the site. The membrane attack complex punches holes in bacterial cell walls. Complement deficiencies are rare but clinically significant. People with C3 deficiency have recurrent bacterial infections starting in early childhood. The bottleneck is obvious: without C3 opsonization, phagocytes cannot efficiently clear even common pathogens.
Get the Full Details
There is a real limitation here that nobody likes to talk about. The adaptive immune system is highly specific but slow to mount a primary response. During that window, the pathogen replicates unchecked. This is why asymptomatic circulation of viruses like SARS-CoV-2 matters so much for public health. By the time adaptive immunity kicks in, the host has already been shedding virus for days. Vaccines collapse that timeline by establishing memory before exposure. But vaccines also have limits. They reduce disease severity and transmission risk but rarely provide sterile immunity against rapidly mutating respiratory viruses. No amount of boosting fixes the fundamental mismatch between vaccine design timelines and viral evolution rates.
What Actually Happens During an Infection
A bacterium enters through a cut in your skin. Resident macrophages phagocytose it immediately. The macrophage releases IL-1, IL-6, and TNF-alpha. Those cytokines cause local blood vessels to dilate and become permeable. That is inflammation. Swelling, redness, heat, pain. The classic signs are not damage. They are the result of immune cells rushing to the site. Neutrophils follow within hours. They are short-lived soldiers that dump granules full of reactive oxygen species and proteolytic enzymes onto the bacteria. The pus you see is mostly dead neutrophils and bacterial debris. Dendritic cells carry bacterial fragments to the draining lymph node. There they present antigens to naïve T cells. Only a tiny fraction of T cells recognize the specific antigen. Those cells clone themselves rapidly. Within five to seven days, you have a army of antigen-specific effectors flooding back into the bloodstream. The fever you get during infection is not a side effect. Interleukin-1 and tumor necrosis factor act on the hypothalamus to raise your body temperature set point. Higher temperatures slow bacterial replication and speed up immune cell trafficking. A mild fever is functionally useful. Pushing it down completely with antipyretics can prolong certain infections by half a day to a full day according to clinical observations, though the tradeoff is comfort and preventing febrile seizures in vulnerable populations.
Lymph nodes swell during infection because that is where B cells and T cells are actively dividing. The germinal center reaction inside the node is where affinity maturation happens. B cells that produce higher-affinity antibodies get selected to survive. Those that do not undergo apoptosis. This selection process is what makes secondary responses stronger and faster. It is also why some infections confer longer-lasting immunity than others. The strength of the germinal center reaction varies significantly between pathogens. Mucosal immunity deserves more attention than it gets. The gut, lungs, and other mucosal surfaces are protected by IgA antibodies that are transported across epithelial layers by the polymeric immunoglobulin receptor. Secretory IgA neutralizes pathogens at the portal of entry without triggering the inflammatory cascade that IgG would. Breast milk is rich in secretory IgA because maternal antibodies are tailored to the pathogen environment the infant will actually encounter. This is not theoretical. Exclusive breastfeeding reduces infant gastrointestinal and respiratory infections by measurable margins in populations with limited sanitation infrastructure.
The System When It Goes Wrong
Autoimmune disease is the immune system failing to maintain tolerance. Type 1 diabetes destroys pancreatic beta cells. Rheumatoid arthritis targets joint tissue. Multiple sclerosis attacks myelin. The common thread is loss of self-tolerance, but the specific triggers vary. Molecular mimicry is one mechanism where a pathogen shares structural similarity with self-antigens. The immune response cross-reacts. Post-streptococcal rheumatic fever is a documented example of this. Allergy is another misfire. The immune system treats harmless environmental proteins as threats and mounts an IgE-mediated response. Mast cells degranulate, releasing histamine and other mediators. The result is runny nose, hives, or in severe cases anaphylaxis. The prevalence of allergic disease has increased dramatically over the past few decades, which argues against a purely genetic explanation. The hygiene hypothesis suggests that reduced microbial exposure in early childhood leaves the immune system with insufficient regulatory training. Immunosenescence is the gradual decline of immune function with age. Thymic involution reduces naive T cell output. Memory T cell populations expand but with reduced diversity. The response to new vaccines is weaker in older adults. That is why flu vaccine efficacy drops significantly after age sixty-five and why pneumococcal conjugate vaccines are preferred over polysaccharide formulations in this population. The biology is clear. The intervention is just dose adjustment and vaccine type selection.
The gut microbiome modulates immune responses in ways that are still being mapped. Certain bacterial species promote regulatory T cell differentiation. Others trigger Th17 responses. Dysbiosis, or microbial imbalance, has been linked to inflammatory bowel disease, allergic disease, and possibly autoimmune conditions. Probiotics show modest benefits for specific conditions but the effects are strain-specific and transient. You cannot generalize from one study to a broad recommendation. The microbiome-immune axis is real. The clinical applications are still early. Cytokine storms represent the extreme end of immune dysregulation. When the system overreacts, the resulting inflammation can cause capillary leak, hypotension, and multi-organ failure. This is what kills in severe sepsis and was observed in a subset of severe COVID-19 cases. Anti-cytokine therapies like tocilizumab, which blocks the IL-6 receptor, can interrupt this cascade. But blocking one pathway can leave others unchecked. The therapeutic window is narrow. Timing matters more than the drug choice in many cases. Primary immunodeficiencies are genetic disorders that impair specific immune functions. X-linked agammaglobulinemia eliminates B cell development. Patients present with recurrent bacterial infections after maternal antibodies wane around six months of age. The treatment is lifelong immunoglobulin replacement therapy, typically administered intravenously or subcutaneously every three to four weeks. The cost is substantial. The alternative is repeated hospitalizations for pneumonia and sepsis. The math works out in favor of replacement therapy even without considering quality of life.
Practical Takeaways
Sleep deprivation reduces natural killer cell activity by roughly 70 percent after one night of restricted sleep. Chronic stress elevates cortisol, which suppresses inflammatory signaling but also impairs vaccine responses. These are not motivational talking points. They are measurable physiological effects with clinical relevance. The magnitude of the impact depends on baseline health, age, and the specific stressor. Vaccines train the adaptive system without causing disease. They introduce antigens in a controlled format that triggers dendritic cell maturation, T cell priming, and B cell affinity maturation just like a real infection would, except without the replication phase. The immune memory they generate is what provides protection. Understanding this mechanism makes it easier to see why vaccine schedules exist and why booster doses are sometimes necessary. Antibiotics treat bacterial infections. They do nothing against viruses. Using antibiotics for viral illnesses contributes to resistance and disrupts the microbiome. The clinical indication should be bacterial infection confirmed or strongly suspected based on presentation and testing. This is basic but consistently violated in practice.
The immune system is not designed for optimal performance. It is designed for survival. It prioritizes rapid response over precision. It accepts collateral damage as the cost of keeping you alive long enough to reproduce. Every autoimmune condition, every allergy, every cytokine storm is a manifestation of that fundamental design tradeoff. The system works because the alternative is worse, not because it is elegant.


