What You're Actually Looking At
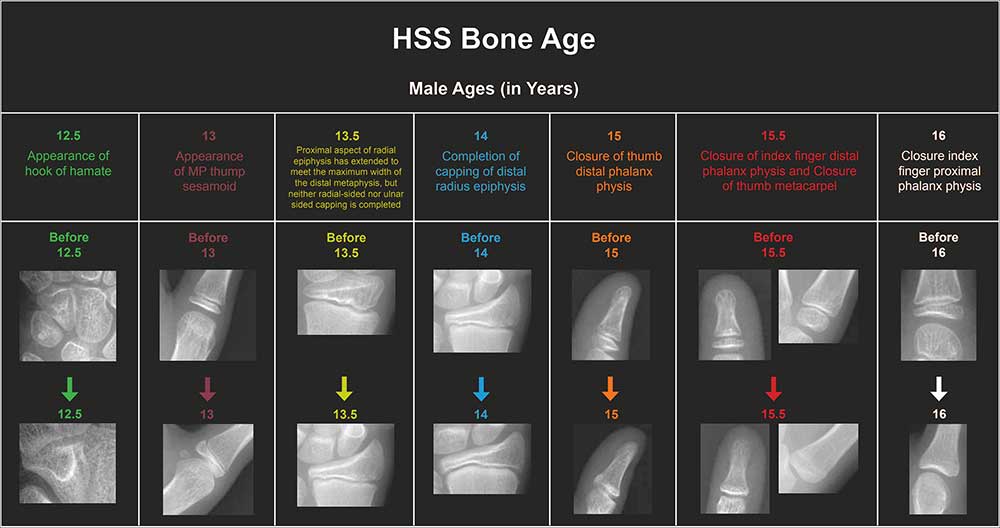
Bone age isn't some mystical measurement. It's a comparison between a patient's skeletal maturity and their chronological age, determined by imaging specific regions where bone development follows predictable patterns. The standard approach uses a left hand and wrist radiograph, though you'll see some pediatric endocrinology practices imaging just the knee or clavicle depending on the clinical question. The result is a number, expressed in years and months, that either tracks closely with the patient's actual age or signals a deviation worth investigating further. There are two primary methodologies in clinical use: the Greulich-Pyle atlas method and the Tanner-Whitehouse 3 (TW3) method. The atlas method is far more common because it's faster. You take the radiograph, lay it next to reference images for various ages, and pick the closest match. It takes maybe 5 to 15 minutes for someone who has done this regularly. The TW3 method scores individual bones—specifically the radius, ulna, carpals, and the metacarpals and phalanges—on a numerical scale, then feeds those scores into a regression equation. It takes 20 to 40 minutes per study and produces a more granular result. Most general radiology departments use Greulich-Pyle. The endocrine or research settings lean toward TW3. There's also a newer third option that has been gaining traction: automated AI-based systems. These tools analyze the radiograph and produce a bone age estimate in under a minute. They're trained on large datasets, typically the Greulich-Pyle atlas images. They're fast enough to use in high-volume clinics, but they still have calibration issues in certain populations. I'll get to that.
The process itself is straightforward. You order a PA (posteroanterior) hand radiograph. The patient's left hand is preferred because it's the non-dominant side in most of the population, and the reference standards were built using left hands. The hand is positioned flat against the detector with fingers slightly separated, palm down, and the X-ray beam centered on the mid metacarpal head. No special preparation is needed from the patient. You don't need sedation unless the patient is too young or uncooperative, which is rare after age three or four. One thing people overlook is that the radiographic technique matters more than you might think. If your exposure is too high, the distal phalanges wash out and you can't assess the epiphyseal ossification centers properly. If it's too low, the carpal bones merge into a grey mass and you lose detail where you need it most. A typical setting is around 50 to 60 kVp and 2 to 4 mAs for a pediatric hand, but this varies by patient size and equipment. Get the technique wrong and your bone age reading will be off by six months to a year, sometimes more.
The Atlas Method in Practice
When I first started reading bone ages, I treated the Greulich-Pyle atlas like a multiple-choice test. Pick the image that looks closest and move on. That's incorrect and it leads to systematic errors. The atlas contains reference standards for both boys and girls, separated by year of age from newborn to 18 years for girls and 19 years for boys. The images are photographs of actual children, not diagrams, which means there's natural variation within each age group. Your job is to find the closest match across multiple anatomical regions simultaneously, not just one bone. For example, a boy might have his distal radius matching a 12-year-old reference, his proximal phalanges matching a 13-year-old, and his carpals matching an 11-year-old. In that case, you're looking at a bone age somewhere around 12, with the understanding that different regions mature at different rates. That's normal. Skeletal maturation isn't perfectly synchronized across the hand. The atlas method has well-documented limitations. The original studies were conducted on white, middle-class American children from the 1930s and 1940s. When you apply those standards to a child who is ethnically different, from a different socioeconomic background, or who has a chronic condition, the readings can drift. Black children tend to mature slightly earlier than the atlas predicts. Asian populations show varying patterns depending on the subgroup. I've seen cases where a child of South Asian descent had a bone age reading that was consistently 8 to 10 months ahead of what theGreulich-Pyle standard suggested, and the discrepancy only became apparent when I cross-referenced with the TW3 scores.
Get the Full Details

The Tanner-Whitehouse Method
TW3 is more involved but it's also more objective in a way that matters. Instead of comparing the whole hand to a reference image, you score individual bones. Each bone gets a score from 1 to 6, sometimes higher for certain structures, based on the stage of ossification. There are 20 bones in the standard TW3 protocol. The scores are summed and converted into a bone age using published tables. The whole procedure is slower, but it reduces inter-observer variability significantly compared to the atlas method. Studies show inter-reader agreement improves from roughly 0.6 to 0.85 correlation coefficients when you move from Greulich-Pyle to TW3. The problem with TW3 is that it requires formal training. You need to go through a structured course or spend months reading practice cases to get reliable. Most general radiologists never do that. They stick with the atlas method. That's fine for routine cases. It becomes a problem when the clinical stakes are high—when you're deciding whether to intervene for a child with short stature, or whether to adjust hormone therapy for someone with a disorder of sexual development.
A Problem I Ran Into
Not long ago I read a bone age for a 10-year-old girl with a history of craniopharyngioma treated with surgery and radiation. She was well below the third percentile for height, and the clinical team wanted to know if she was a candidate for growth hormone therapy. The Greulich-Pyle reading came back at 7.5 years. That's a significant delay. I felt confident enough to report it without a second look, but I sent it to an endocrine radiologist for a second opinion because something about the carpal development looked slightly off for a delay that severe. The second reader used TW3 and got a bone age of 9.2 years. A 17-month difference between methods on the same patient. The issue wasn't that either reader was wrong. It was that the Greulich-Pyle method tends to underestimate bone age in patients with chronic illness or malnutrition because the reference population didn't include that demographic. The delayed ossification I was seeing was real, but the atlas method was amplifying it. The workaround was to use the RUS (radius, ulna, short bones) score from TW3 as the primary reading and note the Greulich-Pyle result as a secondary reference. The clinical team made their treatment decision based on the TW3 value, which was closer to what her chronological age would predict for a child with her particular history.
When Bone Age Readings Fail Completely
There are scenarios where bone age determination is essentially useless, and it's important to recognize them before you order the X-ray. Obese children consistently read older than their chronological age. This isn't a technical error—it's a real biological phenomenon linked to higher leptin levels and earlier pubertal onset. If you're evaluating an obese child for precocious puberty, a bone age of 12 in a 9-year-old might reflect adiposity rather than true endocrine pathology. The reading is accurate for what it measures, but it doesn't tell you the cause. Children with sickle cell disease, celiac disease, or renal osteodystrophy often have distorted skeletal maturation that doesn't follow normal patterns. In those cases, the carpal bones may appear fragmented or irregular due to underlying bone metabolism issues, making both atlas and score-based methods unreliable. I've seen readings vary by two full years between two trained readers on the same film in a patient with longstanding renal failure. That's not reader error. That's the bone architecture being too abnormal to assess with standard methods. Another blind spot: bone age has limited utility in adolescents past the age of 14 to 15 for girls and 16 to 17 for boys. By that point, most of the relevant epiphyseal plates are fused or fusing, and there's very little information left to extract. A bone age of "16 or greater" in a 17-year-old girl tells you almost nothing clinically. The reference standards become sparse in that range anyway, which compounds the problem. You're essentially guessing at that point.

The Automated Systems
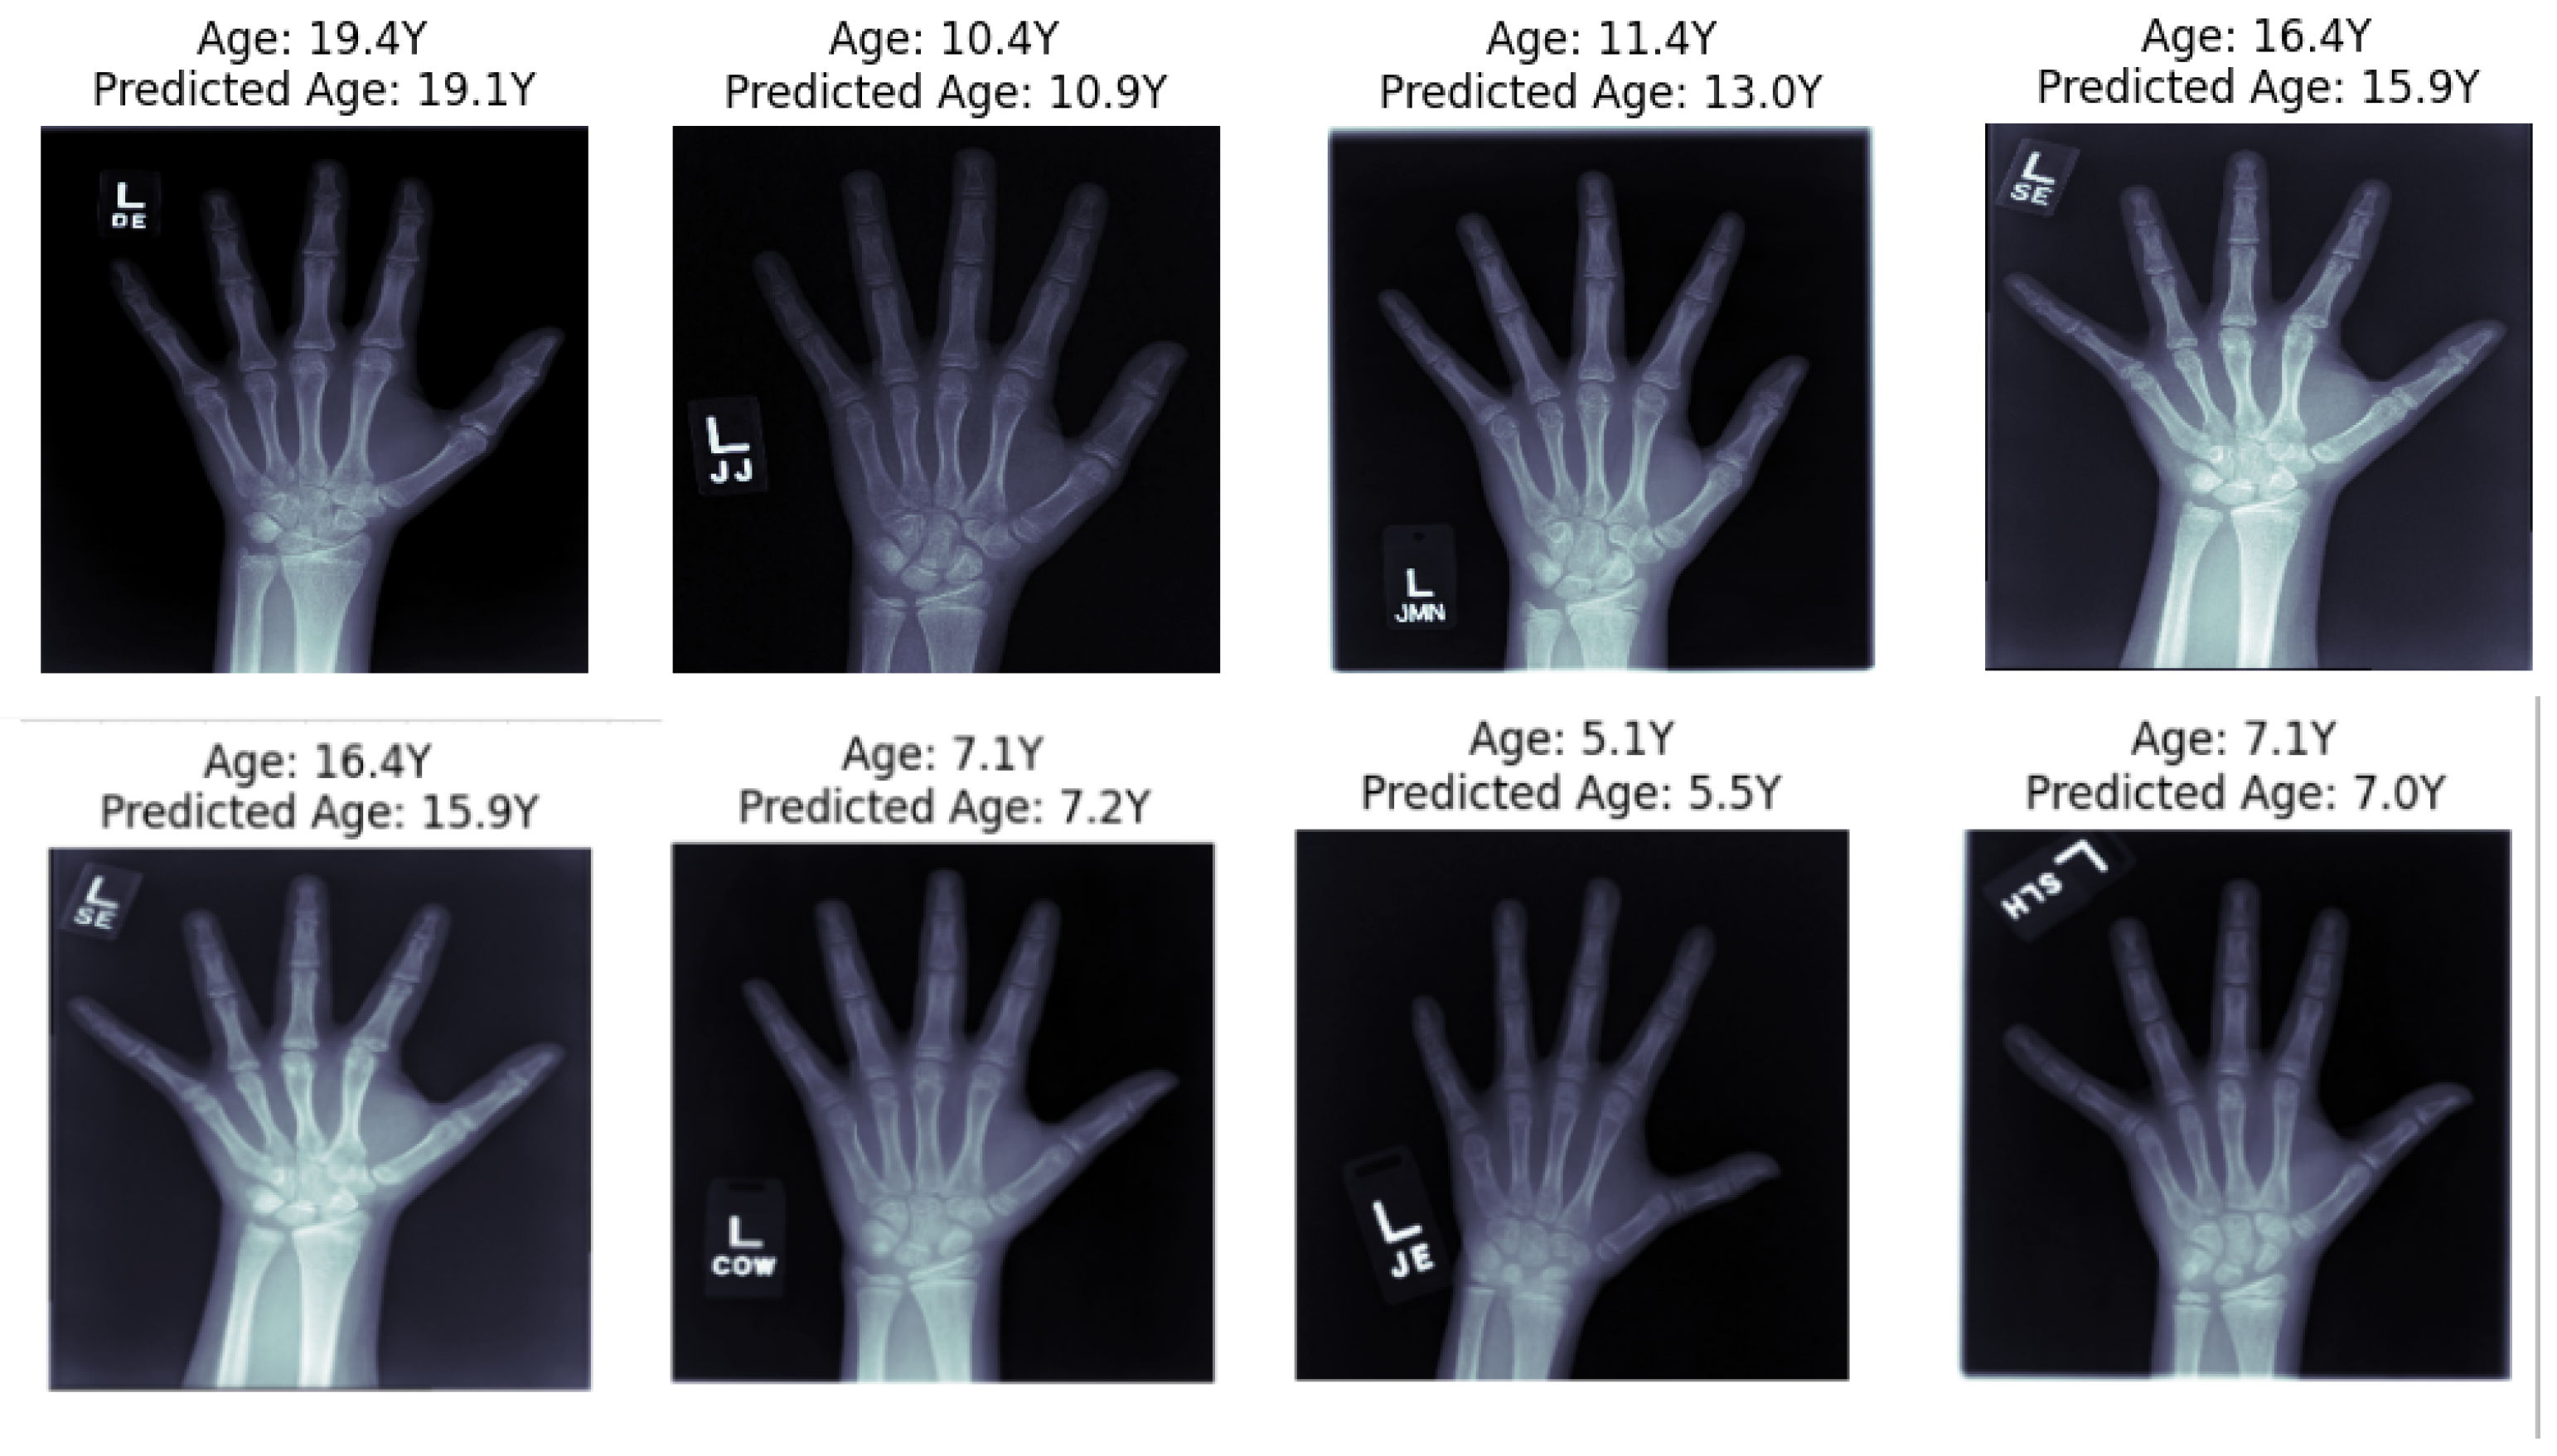
AI-based bone age estimation has improved dramatically since the first generation of tools hit the market around 2018. Current systems claim accuracy within 6 to 12 months of a trained reader's assessment across most populations, and they operate in under 30 seconds per image. That speed makes them attractive for screening purposes and for clinics that don't have pediatric radiologists on staff. But the published validation data still skews toward specific demographics. Some commercial systems were trained primarily on European and North American datasets. When applied to children of African or Middle Eastern descent, the error margins widen. I ran a series of cases last year where the automated system consistently underestimated bone age by 8 to 14 months in a cohort of Somali refugee children. The manual Greulich-Pyle reading was closer to the clinical picture, and the discrepancy only showed up when I compared all three methods side by side. The system wasn't broken. It was just trained on the wrong population. If you're considering implementing an automated system in your practice, the first question you should ask isn't about accuracy. It's about the training data. What demographics was it validated on? What's the error rate outside those demographics? The answers will determine whether it's a useful tool or a liability.
What the Number Actually Means
A bone age of 12 in a 10-year-old child doesn't automatically mean precocious puberty. It doesn't automatically mean anything definitive on its own. It's a single data point that needs to be interpreted alongside height velocity, pubertal stage, bone density, parental heights, and the clinical context. A bone age advanced by 2 years in a 6-year-old with rapid linear growth and breast development is a different situation from a bone age delayed by 2 years in an 8-year-old with failure to thrive. The same number, completely different implications. The biggest mistake I see in clinical practice is treating bone age as a diagnostic conclusion rather than a descriptive measurement. It describes skeletal maturity. It doesn't diagnose the cause of early or delayed maturation. If you need a diagnosis, you order IGF-1, thyroid panels, karyotyping, or MRI depending on the presentation. The bone age tells you the skeleton's status. The rest of the workup tells you why.