The Math You Actually Use on the Floor
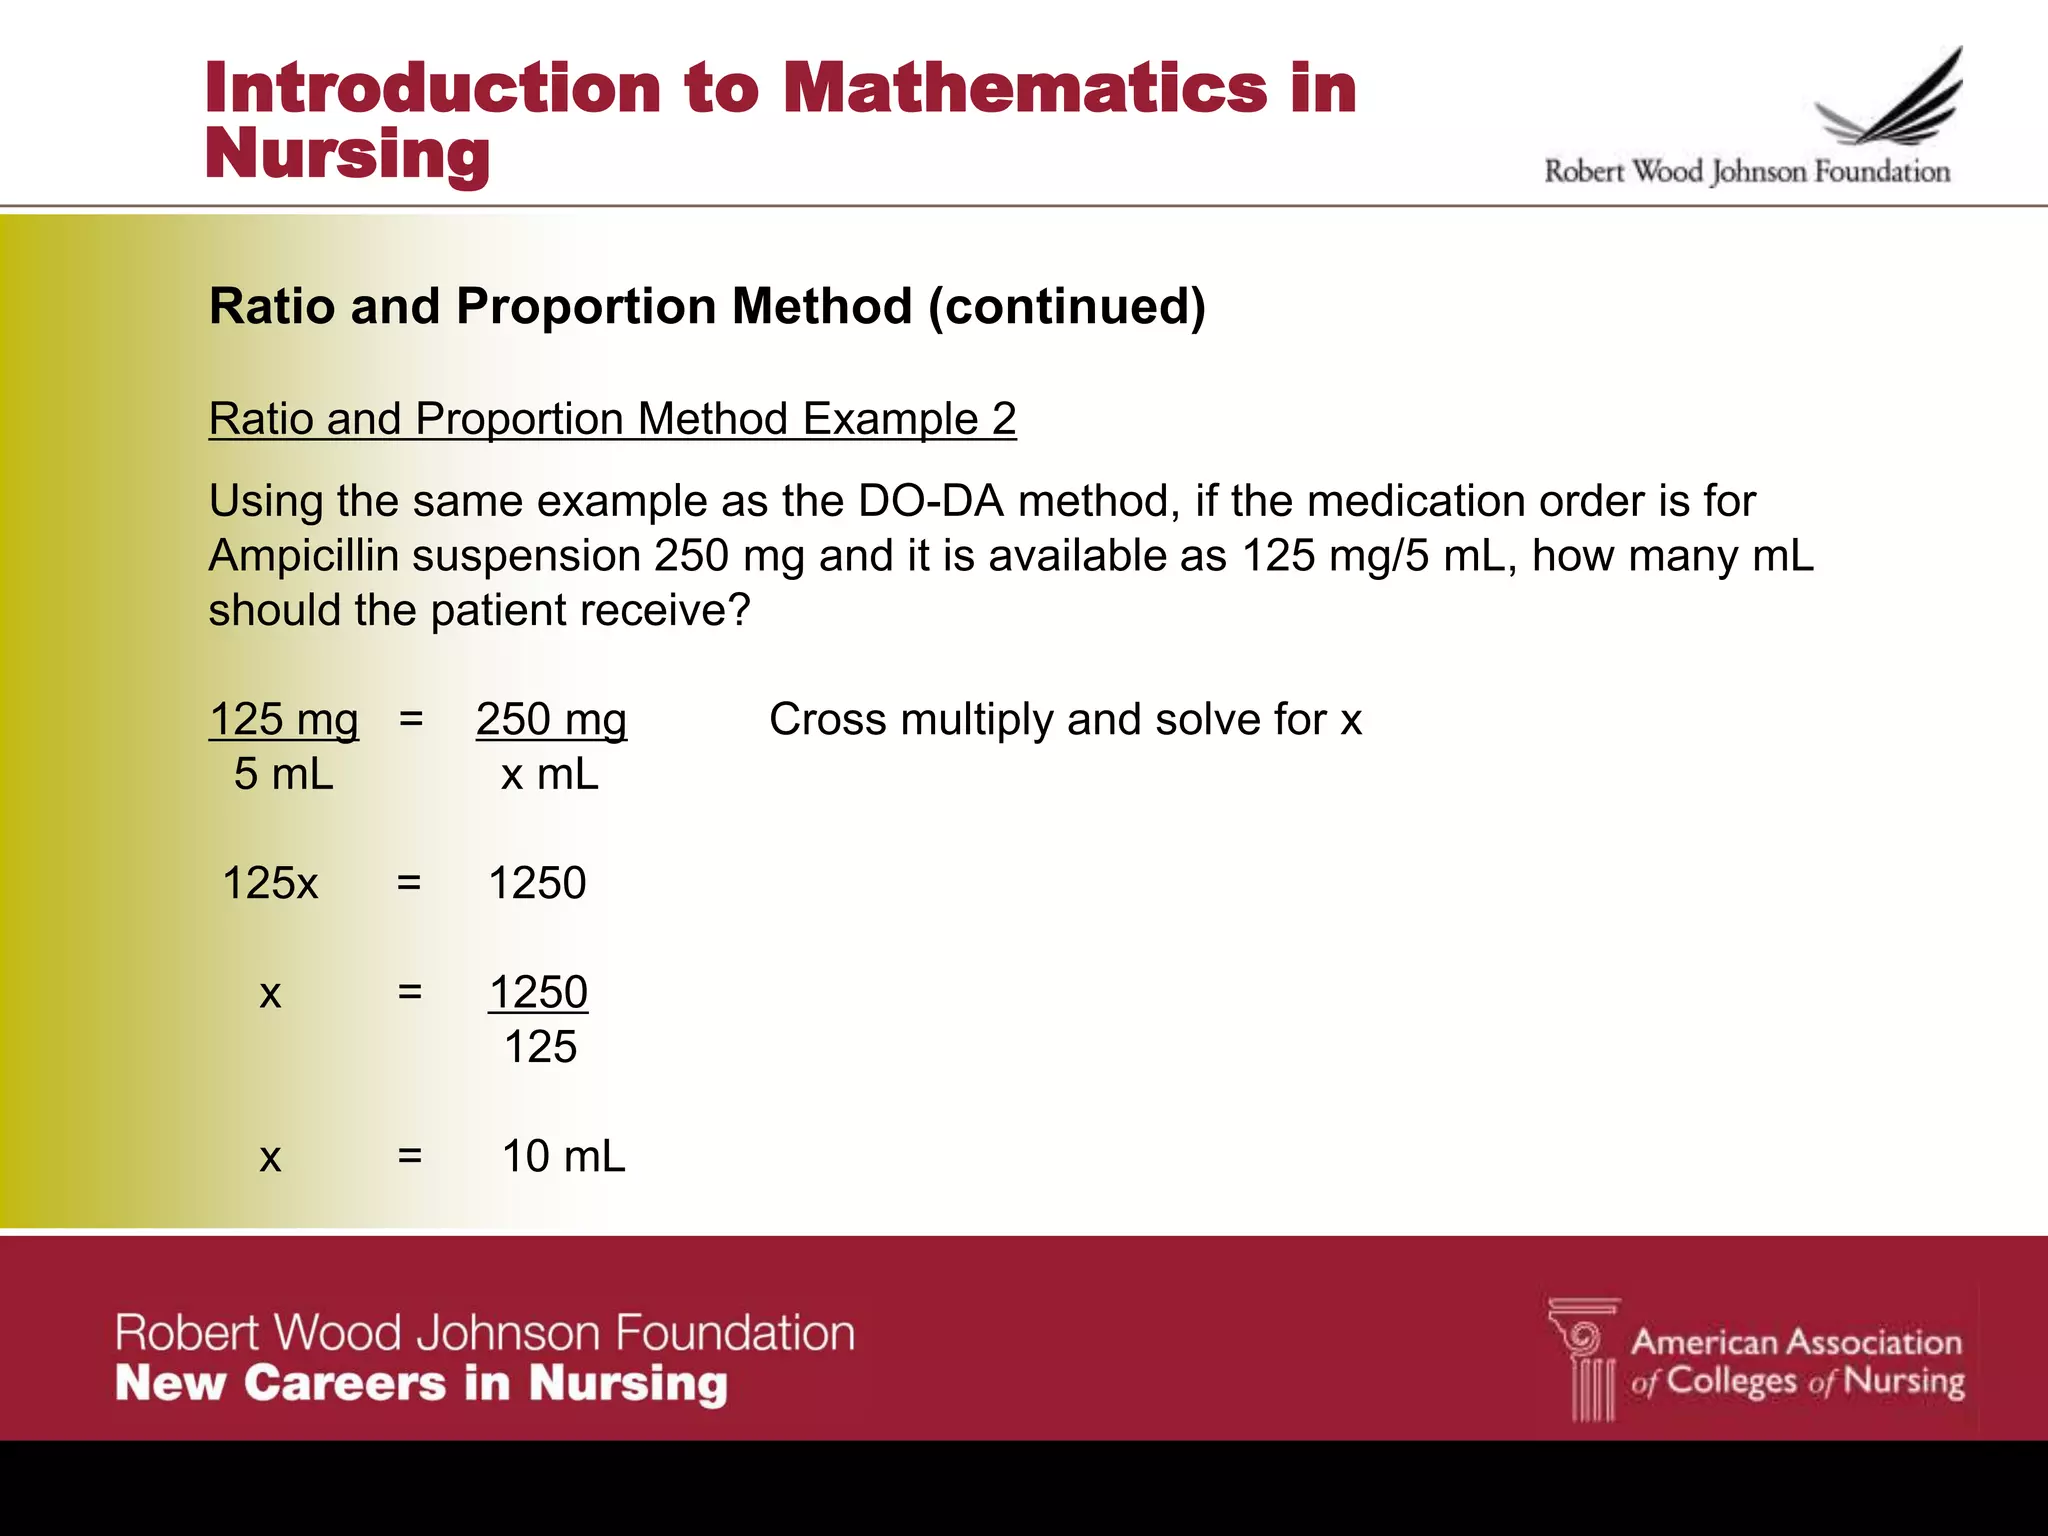
Nurses calculate medication dosages, IV drip rates, fluid balances, and lab value interpretations every single shift. It is not theoretical. It is literal arithmetic done under time pressure while a patient is waiting for something that needs to go in their vein right now. Most nursing programs skim over this, which is why new grads panic when they get to clinicals and realize they cannot do basic dimensional analysis without second-guessing themselves. Here is what actually happens. You get an order for vancomycin 750 mg IV every 12 hours. The vial on the med cart says 500 mg per mL after reconstitution. You need to figure out how many milliliters to draw up. You set up a proportion or use the formula method. 750 divided by 500 equals 1.5 mL. That is it. It sounds simple because it is simple, but the pressure comes from everything else happening around you, not from the math itself.
How Is Math Used In Nursing Beyond Basic Dosage Calculation
IV flow rate calculations are where most people trip up. You have a bag of normal saline with 40 mEq of potassium chloride added, ordered to run at 125 mL per hour. The tubing is microdrip, so 60 drops per mL. You multiply 125 by 60 and divide by 60 minutes to get 125 drops per minute. Easy enough. But then your attending switches the order to 85 mL per hour mid-shift and you are recalculating at 2 AM because the other nurse forgot to update the sheet. This is the real context, not the clean textbook problem. Blood glucose conversions come up constantly in diabetes management. A patient's glucose is 180 mg/dL and you need to document it in mmol/L for the transfer paperwork. You divide by 18 and get 10 mmol/L. Not a complex conversion, but if you do it wrong on a handoff, the receiving team might adjust insulin based on incorrect numbers. I have seen it happen. One nurse multiplied instead of divided and the resident almost ordered a full insulin drip for a glucose reading that looked like 3240 by accident. Nobody got hurt because the attending caught the obviously impossible number, but that is the entire risk of any calculation done without a sanity check. GFR estimation using Cockcroft-Gault or MDRD formulas is another area that matters clinically. You are not doing this by hand during a routine shift usually. Electronic health records handle it. But understanding what the formula means and when it breaks down is something you learn the hard way. The Cockcroft-Gault equation uses actual body weight, which inflates the result in obese patients. I had a patient who was 140 kilograms and the estimated creatinine clearance came out to 95 mL/min, which looked normal. Adjusting to ideal body weight dropped it to 52 mL/min, which changed how we dosed his antibiotics. The EHR does not always apply the right weight adjustment automatically, so you have to know to check.
Base deficit and anion gap calculations show up in critical care and emergency settings. Anion gap is sodium minus chloride minus bicarbonate. A normal range is roughly 8 to 12. If a septic patient comes in with an anion gap of 24, that is a high anion gap metabolic acidosis and you need to act on it. These are not fancy equations. They are subtraction and comparison, but the clinical consequence of getting them wrong is significant. Titrating vasoactive medications requires understanding of units per kilogram per minute. Norepinephrine is typically started at 0.1 to 0.5 mcg/kg/min. Your patient weighs 80 kg. You calculate the base rate and then adjust in small increments based on blood pressure response. The math is straightforward multiplication and division, but the window between underdosing and causing a hypertensive crisis is narrow. I worked a shift where the initial calculation was off by a decimal place because someone transposed 0.05 to 0.5. The patient's blood pressure spiked to 210 over 110 within minutes. We caught it in the hourly rounding check, but that decimal error could have caused a stroke before anyone noticed. Fluid balance tracking is another daily math task. Input includes IV fluids, oral intake, tube feedings, and medication volumes. Output includes urine, drain output, emesis, and insensible losses which you estimate rather than measure directly. A surgical patient on the floor might have 2500 mL of input and 1800 mL of output, giving a positive balance of 700 mL. Over three days, that adds up and you need to recognize the trend before the patient develops pulmonary edema. The calculation itself takes 30 seconds. Recognizing that the trend matters more than any single number is the skill part.
Get the Full Details

One edge case that is worth mentioning specifically. I was covering a med-surg floor and got an order for heparin infusion at 18 units per kg per hour for a patient weighing 67 kg. The available concentration was 25,000 units in 250 mL of D5W. I calculated the hourly rate by multiplying 18 by 67 to get 1206 units per hour, then divided by the concentration of 100 units per mL to get approximately 12 mL per hour. But then I realized the order had been written as 1.8 units per kg per hour and someone had dropped the decimal when transcribing. The original dose was ten times higher than intended. I flagged it with the resident, who confirmed the correction. This is exactly why double-checking your work and questioning orders that seem off matters more than trusting the calculation alone. The tools available today make most of this easier. Smart infusion pumps calculate rates automatically when you program the concentration and desired dose. Pharmacokinetic software handles complex dosing adjustments for renal impairment. Electronic med administration records verify doses against standards before you scan the barcode. None of these eliminate the need to understand the underlying math. They reduce errors, but they also introduce new ones. A pump programmed with the wrong concentration delivers the wrong dose at the right rate. Software that flags a dose as high will still let it through if you override the alert without thinking about why. What helps most is building a mental checklist that you run through every time. Verify the patient's weight is current. Confirm the order matches the calculation. Check the concentration of the medication against what you expect. Do a rough estimate before entering anything into a pump or calculator. If the answer looks wildly different from your estimate, stop and recheck. This takes about 15 seconds per medication and prevents the kind of errors that end up in incident reports.
For studying purposes, dimensional analysis is the most reliable method because it keeps track of units throughout the calculation. You write out every unit, cancel what cancels, and what is left tells you whether you are on the right track. If you are solving for milliliters and your final unit is milligrams per hour, you made a mistake somewhere. Practice with real orders from your clinical rotations rather than generic textbook problems. The numbers and concentrations you encounter in practice are different enough that drilling with fabricated examples does not prepare you well. There is a limit to what math can solve though. Some situations require clinical judgment that no calculation covers. A patient with a normal anion gap who is tachycardic and confused might have a different problem than the numbers suggest. A drug level that falls within the therapeutic range does not guarantee the dose is right for that individual patient. Math is a tool, not a substitute for thinking about the person in the bed.