Understanding the Mitotic Index in Cancer Research
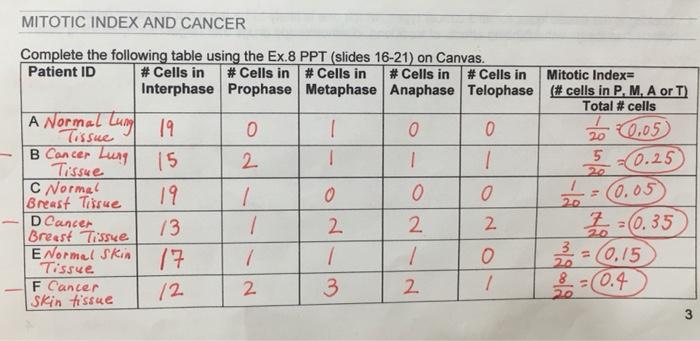
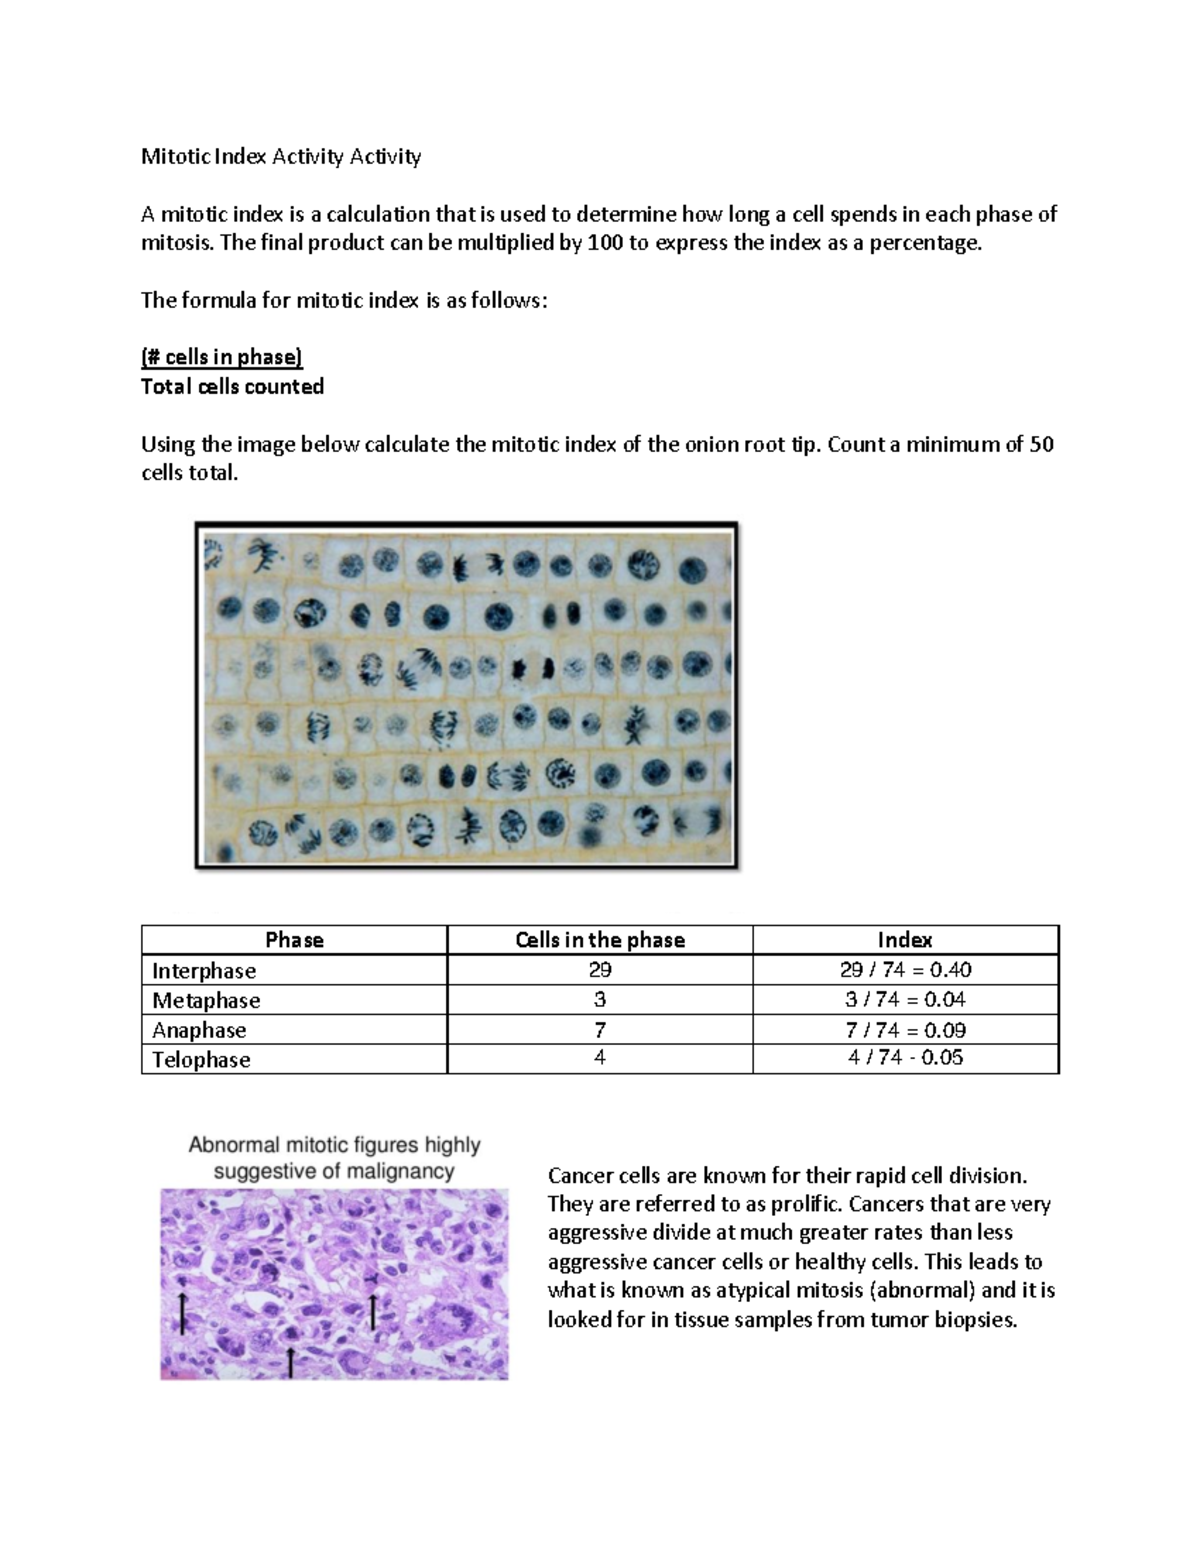
The mitotic index is essentially a count. You look at a tissue slide, identify cells actively dividing, and divide that number by the total cells you examined. The result tells you how fast a tumor is growing. Simple on paper. Messy in practice. Researchers use this metric to grade tumors, predict outcomes, and sometimes decide between treatment options. A higher mitotic index generally means more aggressive cancer. But it is not a standalone diagnostic tool. It is one piece of a larger puzzle that includes histological grade, molecular markers, and clinical staging.
How Is Mitotic Index Used In Cancer Studies Answer Key
The answer key your professor or textbook is probably looking for centers on proliferation rate and tumor grading. Specifically, the mitotic index quantifies the fraction of cells in active division within a sampled area. In cancer studies, this number helps classify how malignant a tumor likely is. Standard methodology involves selecting a representative high-power field under the microscope, usually 40x magnification, and counting mitotic figures across a defined number of fields. Different organizations recommend different field counts. The Royal College of Pathologists in the UK suggests counting 10 high-power fields for breast cancer. Some labs use area-based counting instead. Both approaches aim to capture enough cells to make the number statistically meaningful. I spent a few years running mitotic counts in a pathology lab, and the most frustrating part was never the counting itself. It was the variability between pathologists. Two people looking at the same slide could easily arrive at different mitotic indices. The difference comes down to how each person defines a "mitotic figure." Some count cells with clearly visible chromosomes. Others include cells in earlier stages of division where chromosomes are less distinct. This inconsistency is a real problem in research studies because it introduces noise into the data.
To handle this, many studies now use digital pathology platforms with AI-assisted mitotic figure detection. The software flags potential mitotic cells, and a pathologist confirms them. This does not eliminate inter-observer variability completely, but it reduces it significantly. One study I read found that digital assistance brought the coefficient of variation down from around 25 percent to roughly 12 percent for breast cancer mitotic counting. Another thing people miss is that the mitotic index is highly dependent on sampling. A tumor can have areas of high proliferation and areas of low proliferation. If you sample only the wrong region, your mitotic index will be misleading. The standard workaround is to identify the area of highest mitotic activity first, often called the "hot spot," and then count there. This is particularly important in melanoma and soft tissue sarcomas where mitotic count directly affects staging. There are also biological factors that complicate interpretation. Hormonal therapy can temporarily suppress mitotic activity in breast cancer. Chemotherapy does the same thing, sometimes dramatically. If a biopsy is taken after neoadjuvant treatment, the mitotic index will reflect treatment effect rather than the tumor's natural behavior. Researchers have to account for this by either timing biopsies before treatment or adjusting their analysis accordingly.
Get the Full Details

Then there is the issue of fixed tissue. Formalin fixation time matters. Under-fixed tissue can make mitotic figures harder to recognize because the chromatin structure is not preserved well enough. Over-fixed tissue can make chromosomes look smudged and indistinct. I once had a batch of slides where the fixative had been changed halfway through without anyone updating the labeling. The mitotic counts came back artificially low across the board. It took three days to figure out what happened and another week to reprocess the affected samples. The mitotic index also interacts with other grading systems in ways that are not always straightforward. In the Nottingham Grading System for breast cancer, mitotic count is one of three components, each scored from one to three. The total score ranges from three to nine. But a tumor with a score of seven on mitotic index alone might still end up in a lower overall grade category if the tubule formation and nuclear pleomorphism scores are low. This is why the mitotic index should never be interpreted in isolation. Some cancers rely on mitotic index more heavily than others. Gastrointestinal stromal tumors, for example, use mitotic count per 50 high-power fields as a primary criterion for risk stratification. A GIST with fewer than five mitoses per 50 HPFs has a very different prognosis than one with more than ten. The cutoff values matter a lot in these cases because they determine whether a patient gets adjuvant therapy or just surveillance.
If you are looking for a straightforward answer key summary, the main points are: the mitotic index measures cell proliferation, it helps grade tumor aggressiveness, it is used alongside other pathological features, and it requires careful standardized methodology to be reliable. That covers what most courses expect. The reality of using it in actual research is considerably more complicated than any textbook answer key will admit.