Metabolism rates and testing windows
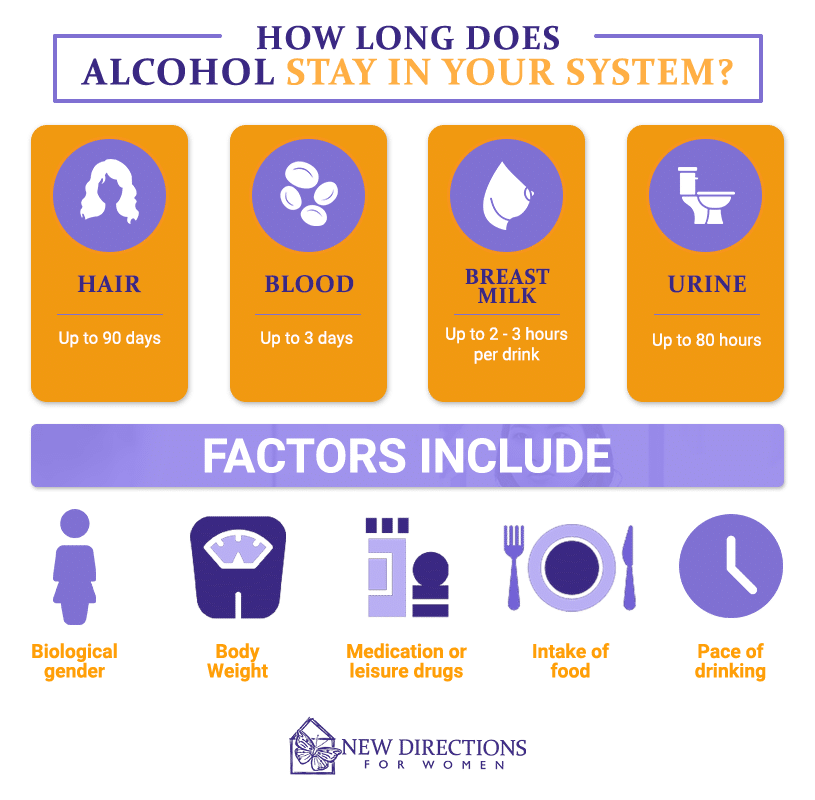
Alcohol leaves your body at a fairly predictable rate for most people, but the numbers shift depending on several factors that matter more than you might expect. The standard assumption is about one standard drink per hour, but that baseline breaks down quickly when you look at real-world conditions. Your body weight, sex, liver health, food intake, and even genetic variations in alcohol dehydrogenase enzymes all change how fast ethanol gets broken down and eliminated. For a single standard drink, you are looking at roughly one hour for complete metabolism through the liver. That means drinking two beers means about two hours before your blood alcohol concentration drops back to zero. But the thing nobody tells you is that this one-per-hour rule only applies to the liver's oxidative pathway, which accounts for about 90 percent of elimination. The remaining ten percent exits through your breath, urine, and sweat, which is why breathalyzers and urine tests can still detect alcohol even after your blood level has normalized. I spent several years working with occupational health clients who kept getting false positives on drug screens. One case stands out: a client had eaten at a bakery before his test and used an alcohol-free mouthwash. The urine EtG test came back positive for 48 hours after what he insisted was only coffee and pastries. We traced it to the ethanol content in the bakery products and the mouthwash itself. The workaround was requesting a creatinine-normalized split-sample test and cross-referencing with a blood ethanol panel rather than relying solely on the urine marker. It added about four days to the turnaround but eliminated the dispute.
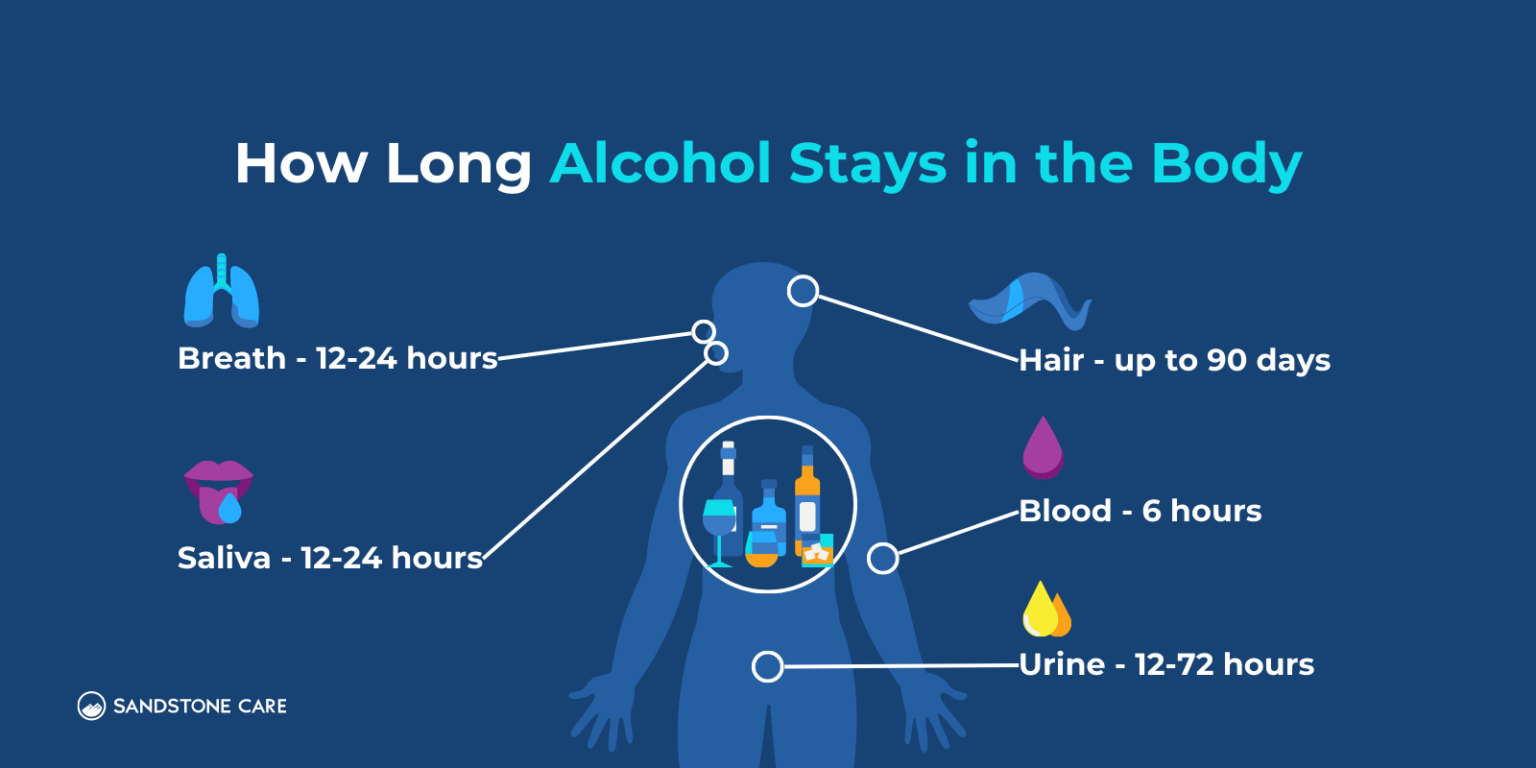
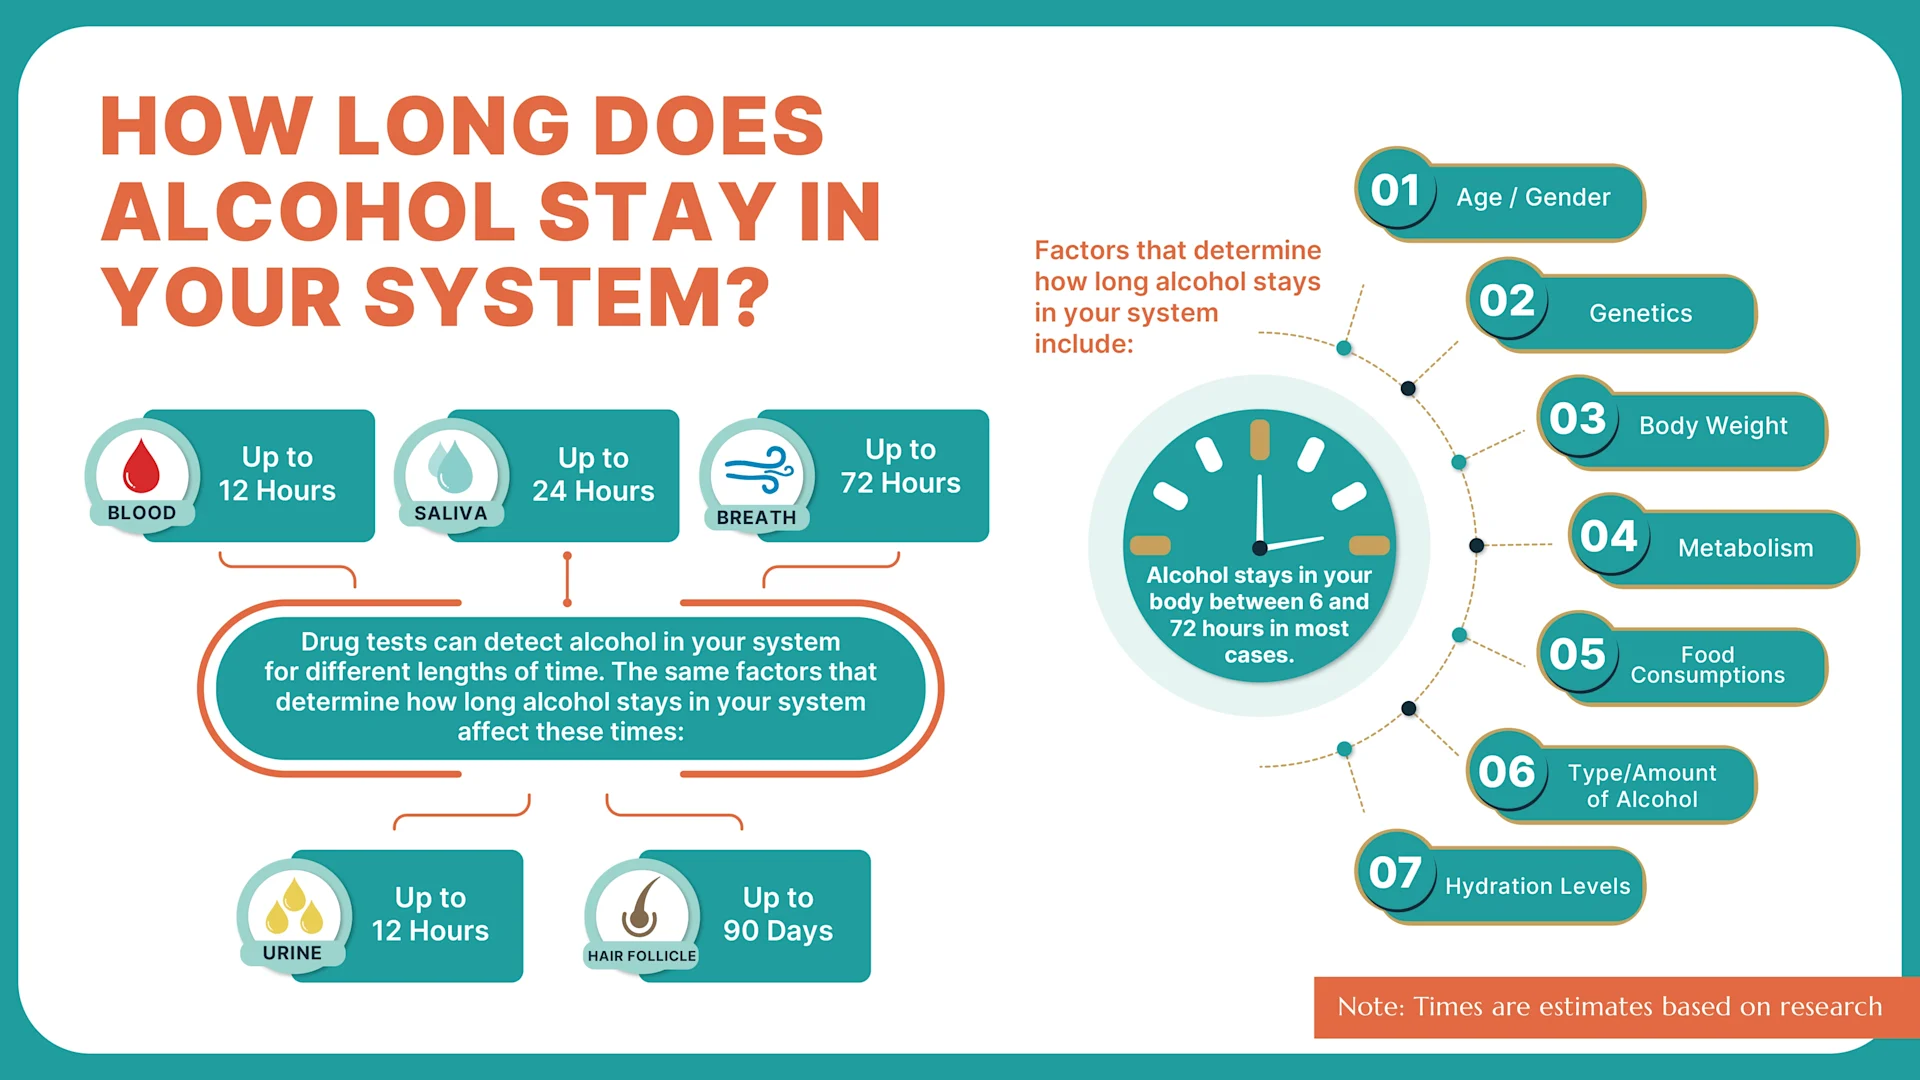
The half-life of ethanol in the bloodstream is approximately five to seven hours depending on concentration and individual metabolism. This is different from the elimination rate most people cite because half-life describes exponential decay while the one-per-hour rule describes zero-order kinetics. At low concentrations, your body shifts toward first-order elimination where the rate depends on current blood alcohol level. At higher concentrations, the enzymatic pathways saturate and you get that steady zero-order rate instead. This is why someone who has been drinking heavily will clear alcohol more slowly per drink than someone having their first one. Blood tests detect alcohol for up to 12 hours after the last drink. Breath tests have a similar window but are affected by recent mouth alcohol contamination, which is why most protocols require a 15-minute observation period before testing. Urine tests for ethanol itself show results within 12 hours, but EtG metabolite testing extends that window dramatically to anywhere from 24 to 80 hours depending on the cutoff threshold and hydration status. Hair follicle testing can detect alcohol consumption patterns over the past 90 days, though it is less common for routine screening. Food in your stomach changes the absorption curve significantly. A high-protein, high-fat meal can delay gastric emptying by two to four hours, which flattens the peak blood alcohol concentration and spreads the elimination window out. This does not reduce total alcohol exposure, but it changes the timing profile enough that impairment tests and driving calculations become less accurate when people factor in only the drink count without considering recent food intake.
Caffeine does not speed up alcohol metabolism. This is one of the most persistent myths and one I see cause real problems in clinical settings. Coffee only affects perceived sobriety, not actual blood alcohol concentration. I had a patient in his late twenties who drank four whiskeys over three hours, consumed multiple espressos, and felt enough to drive. His breath alcohol reading was 0.18 percent, nearly three times the legal limit. The caffeine masked his sedation symptoms while his coordination and reaction time were equally impaired. This pattern shows up repeatedly in emergency department documentation. Female subjects typically achieve higher blood alcohol concentrations than male subjects of equal weight consuming the same amount, due to lower total body water percentage and reduced gastric alcohol dehydrogenase activity. The difference usually translates to about 20 to 25 percent higher peak BAC for women. Liver disease, particularly cirrhosis, can reduce metabolic clearance by 40 to 60 percent. Certain medications like metronidazole and cephalosporins trigger disulfiram-like reactions that slow acetaldehyde metabolism, causing accumulation of the toxic intermediate and extending the functional impairment window well beyond the ethanol elimination period. Hydration status affects urine-based testing more than blood or breath testing. Concentrated urine from dehydration can produce artificially elevated EtG concentrations, while excessive fluid intake before testing can dilute results below the laboratory cutoff threshold. Most forensic labs now flag specimens with abnormal creatinine or specific gravity values, but not all do. If you are dealing with a situation where timing precision matters, a blood ethanol test remains the most reliable single measurement.
Get the Full Details

The acetaldehyde produced during ethanol metabolism is the compound responsible for hangover symptoms and tissue damage, not the ethanol itself. People who carry certain ALDH2 gene variants, particularly those of East Asian descent, cannot efficiently convert acetaldehyde to acetate. This causes flushing, tachycardia, and nausea even after modest consumption. Their ethanol clearance rates are actually normal, but the toxic metabolite lingers longer, making the functional impairment window asymmetric relative to the measured BAC. This is a factor that standard elimination calculators completely ignore. Sleep accelerates perceived recovery but does not change the biochemical elimination rate. The one-per-hour liver metabolism rate continues regardless of whether you are awake or asleep. What sleep does improve is cognitive recovery through clearance of adenosine and other neuromodulators that accumulate during intoxication. You will feel better after eight hours of sleep even if your BAC has not dropped significantly, which creates a dangerous gap between subjective feeling and objective impairment. This gap is what I see driving the majority of impaired driving cases among people who "only had a few drinks" and went to sleep. Individual variation in CYP2E1 induction from chronic alcohol use can increase metabolic capacity by up to 30 to 40 percent in heavy drinkers. This microsome-mediated oxidation pathway becomes more active with repeated exposure, creating a tolerance effect that is separate from neural adaptation. Heavy chronic drinkers may eliminate alcohol faster than light drinkers of equal body weight, which complicates any one-size-fits-all calculation. There is no reliable way to know whether you are inducing this pathway without specialized enzymatic testing.
When people ask me how long until they are clear for a breath test, the practical answer depends on whether they need zero alcohol in their system or just below a specific threshold. For a breathalyzer set at 0.08 percent, someone at 0.12 percent would need roughly two to three hours depending on their individual elimination rate. For complete clearance with no detectable ethanol, a 12-hour buffer from the last drink covers most scenarios, but heavy chronic consumption with possible enzyme induction requires more conservative estimates. There is no supplement, exercise routine, cold shower, or food that meaningfully increases alcohol elimination speed. The liver processes ethanol at a rate constrained by enzyme kinetics and hepatic blood flow. Anything that claims to detoxify you faster is selling something you do not need. The only reliable variables are time, body composition, liver function, and the initial amount consumed. Everything else is noise.