So You're Asking How Many Layers Of Skin Do We Have
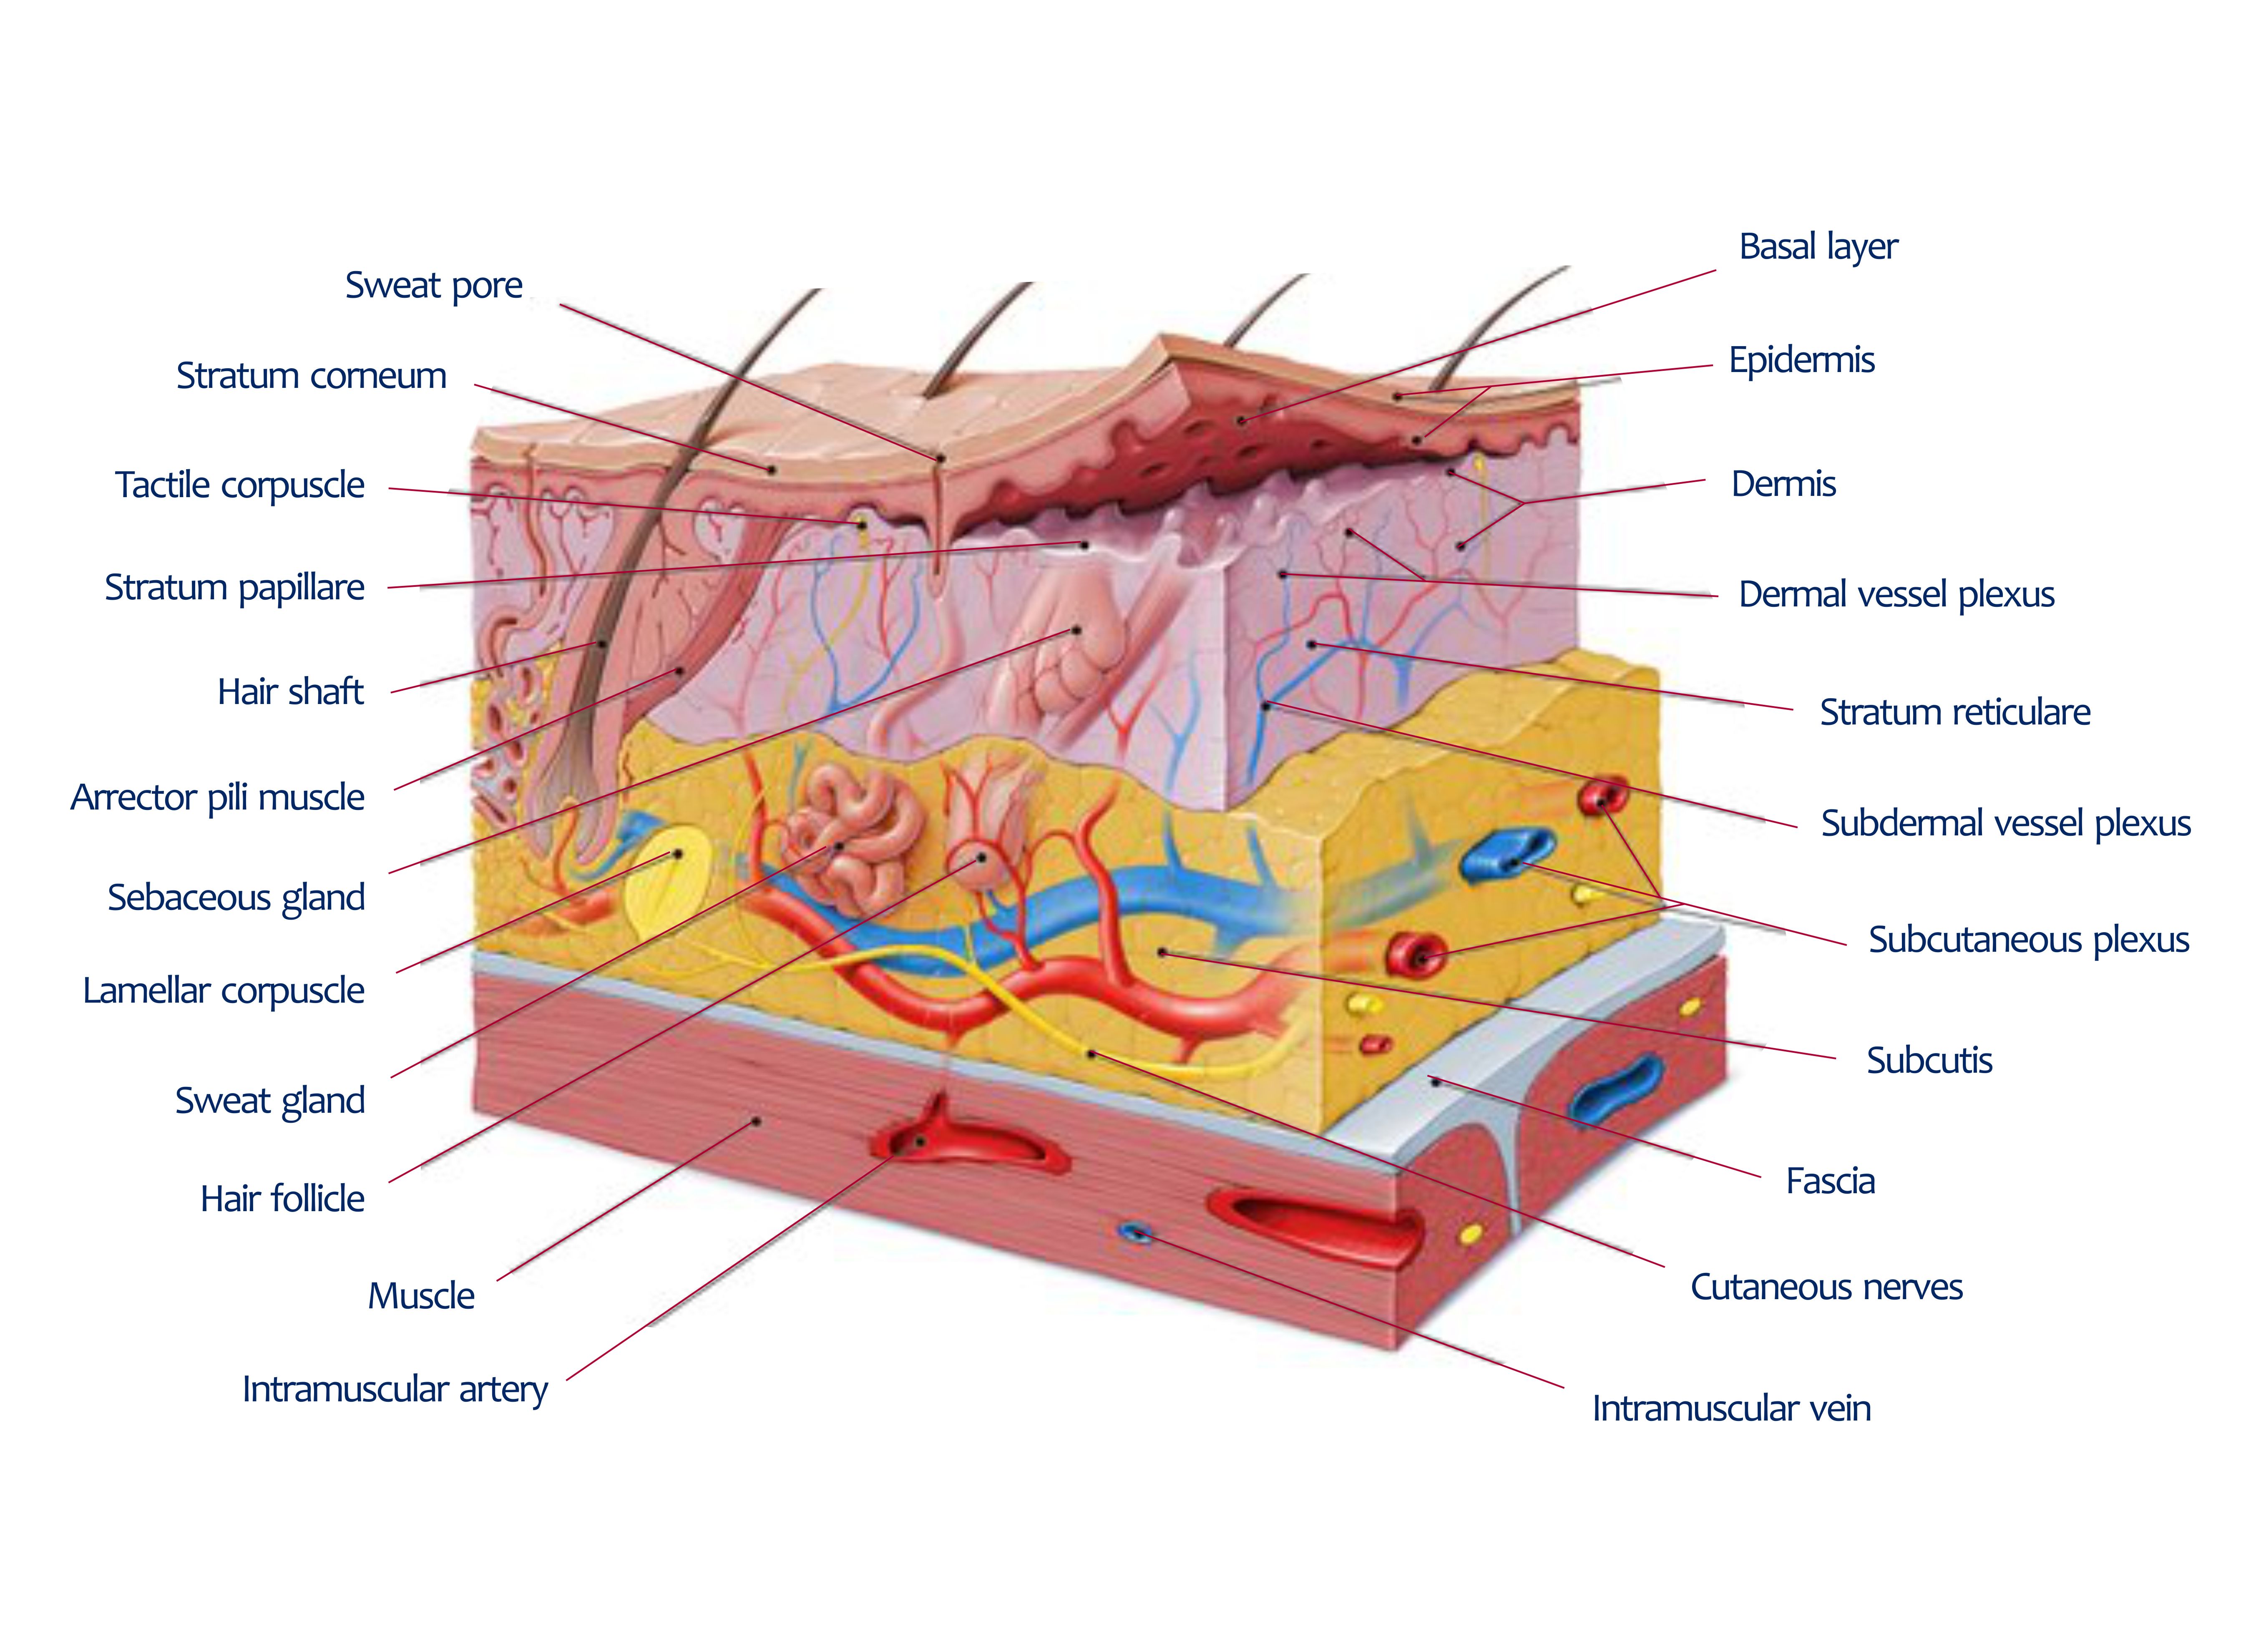
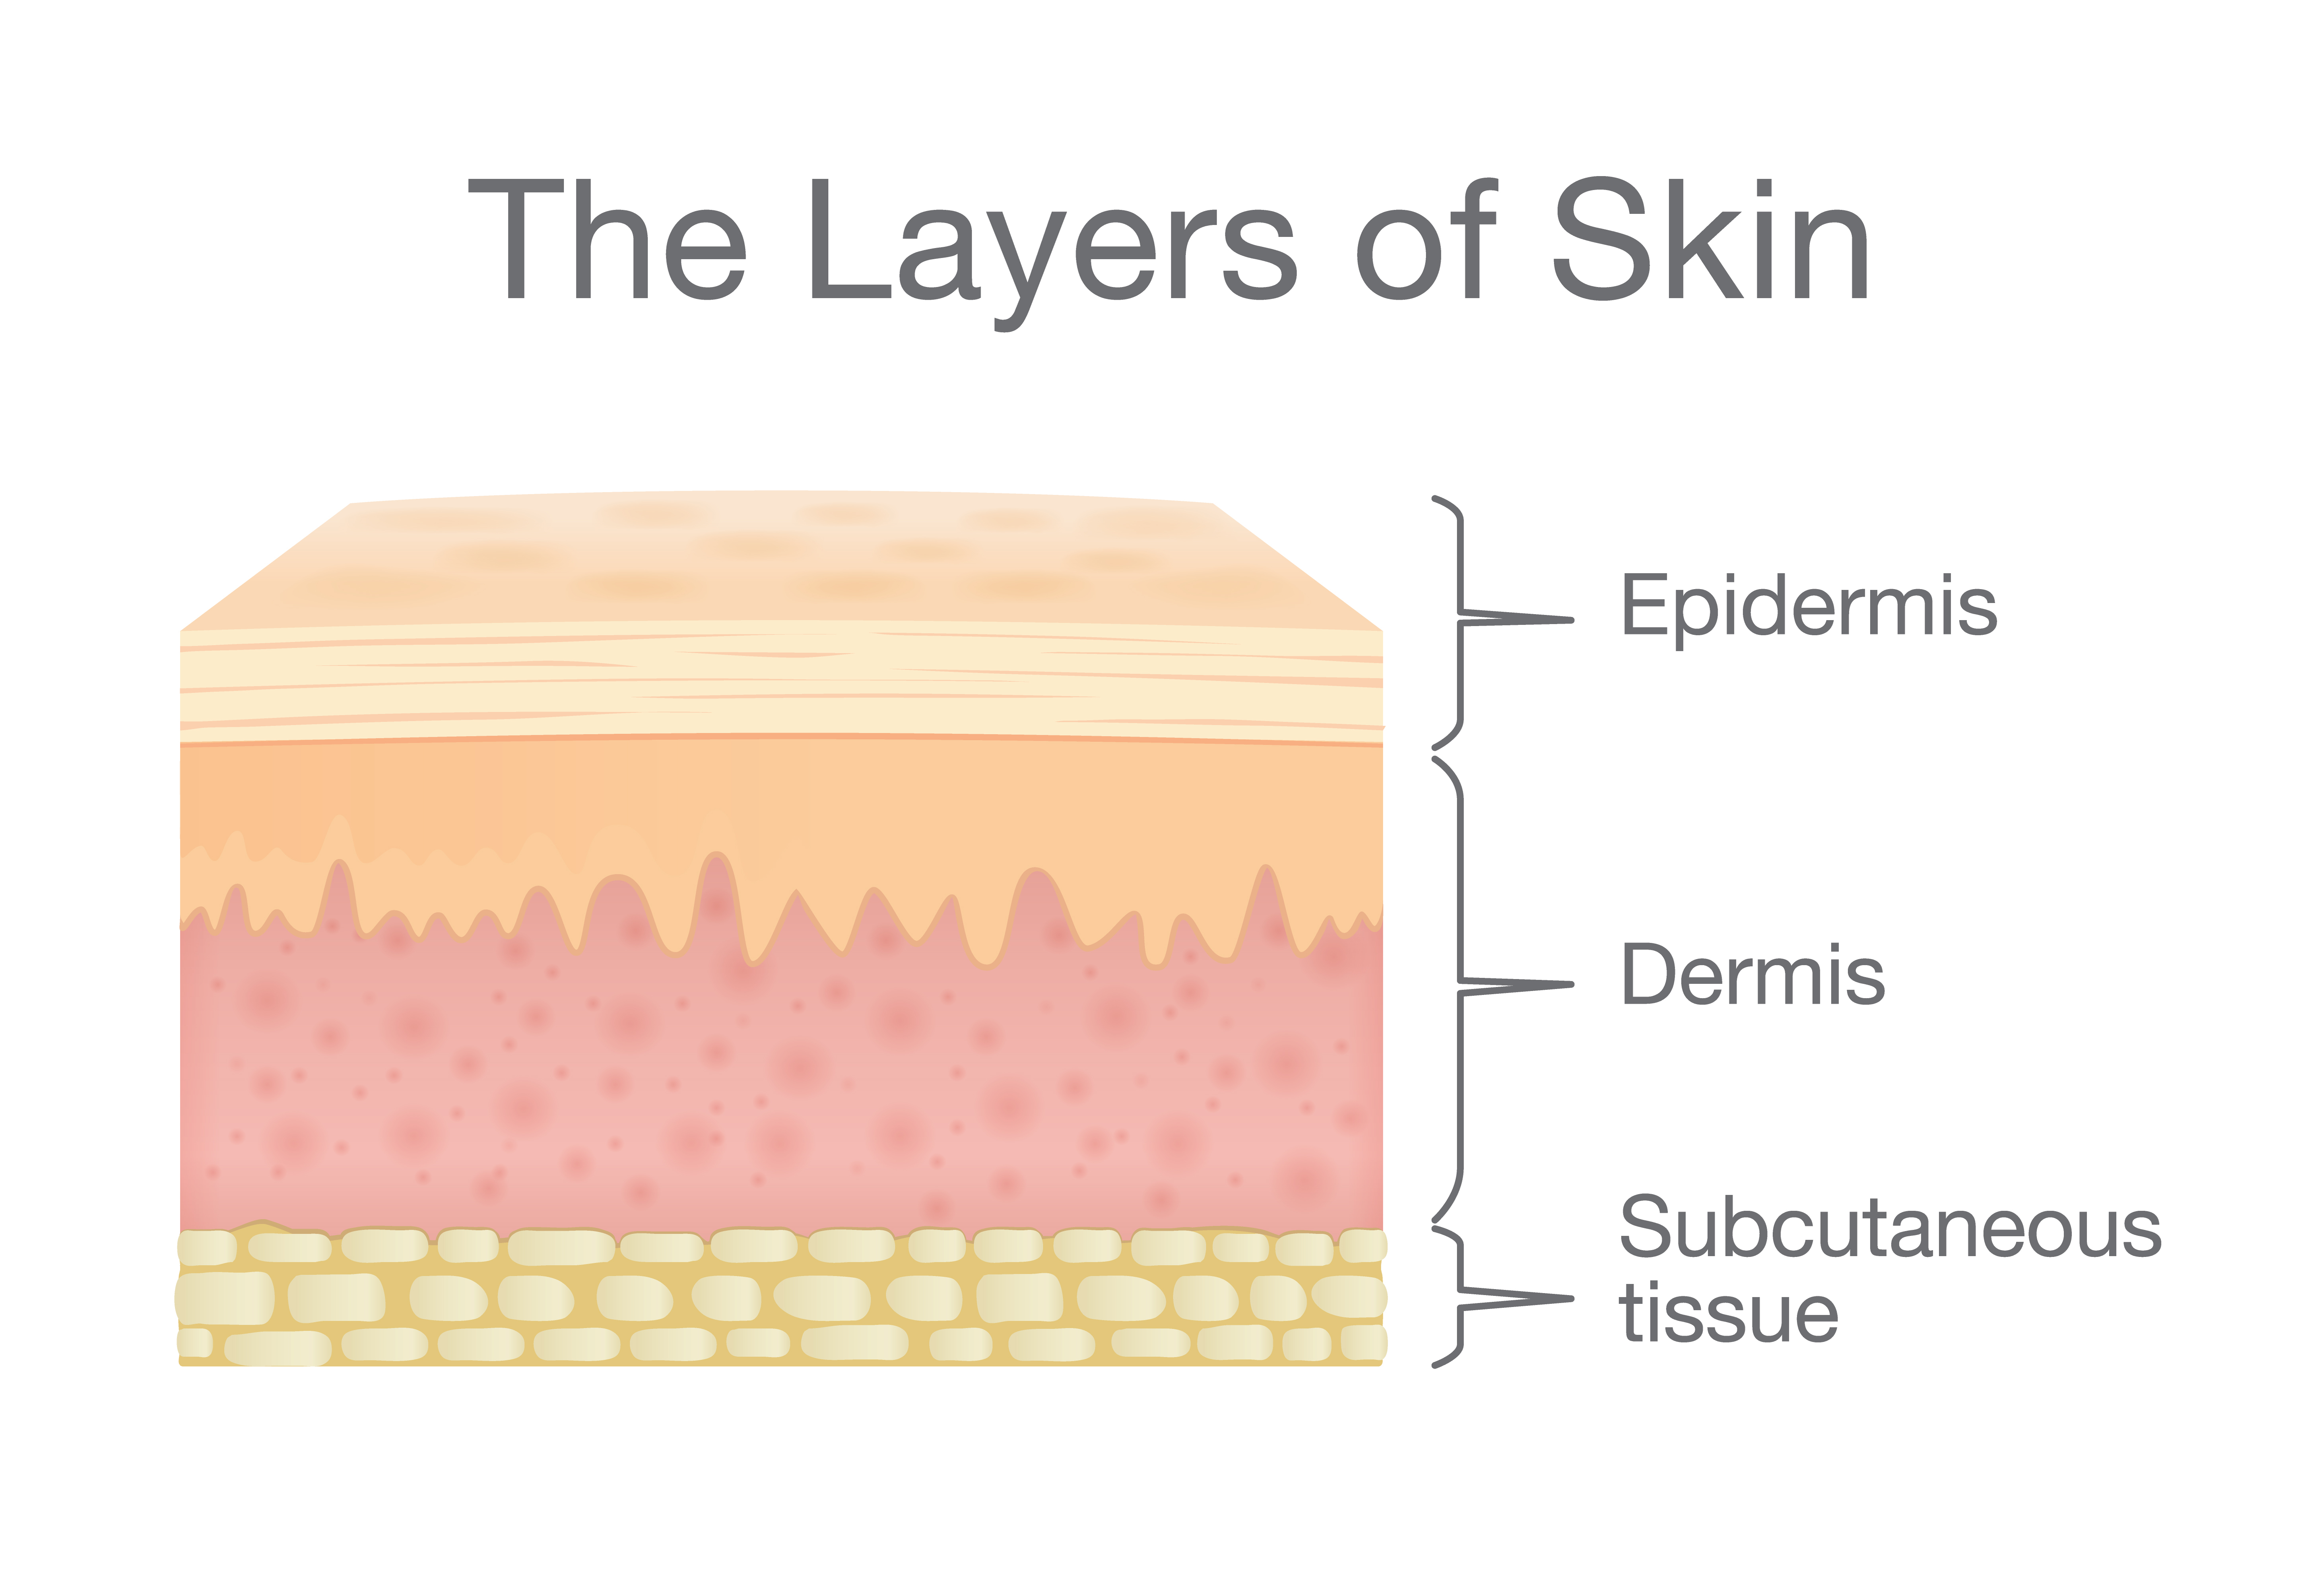
I ran into this exact question last year when a med student asked me during clinic hours. She had her textbook open to the dermatology chapter and was genuinely confused because two different sections of the book gave two different numbers. One said two. The other said five. She looked at me waiting for a single clean answer, and I realized this is more common than you'd think. People search for this because the information is genuinely fragmented across sources. If you're talking about the skin as a complete organ viewed with the naked eye, you have two primary layers: the epidermis on the outside and the dermis underneath it. Below those sits the hypodermis, also called subcutaneous tissue, but most anatomists don't count that as part of the skin proper. It's more of a connection between the skin and whatever lies beneath — muscle, bone, fascia. The hypodermis is made mostly of fat and loose connective tissue, and its thickness varies wildly depending on where you are on the body and your overall body composition. If you're talking about the epidermis at a microscopic level, which is where the real confusion comes from, you have four or five sub-layers, depending on where you measure. The five-layer model applies to thick skin — palms, soles, the backs of your hands. The four-layer model applies to thin skin covering the rest of your body. This distinction matters clinically because thick skin lacks hair follicles and has a different sweat gland distribution, which changes how certain conditions present.
What Those Five Layers Actually Are
Going from the outside surface inward, the epidermis stratifies through these zones: Stratum corneum — this is the dead, flattened cell layer you're constantly shedding. It's the actual barrier that keeps water in and pathogens out. A person loses roughly 30,000 to 40,000 of these cells every minute under normal conditions. That's not dramatic. That's just background metabolism. The corneum is about 10 to 20 cells thick, varying by body region. Stratum lucidum — this one only exists in thick skin. It's a thin, translucent band of dead keratinocytes that sits right beneath the corneum. You won't find it on your forearm or your face. Pathologists use its presence or absence as a quick diagnostic clue when examining biopsies.
Stratum granulosum — the granular layer. Cells here are transitioning from living to dead, packing themselves with keratohyalin granules and lamellar bodies that release lipids to form the waterproof seal. This is where the real barrier function gets built. Damage here — think chronic hand washing, solvent exposure, or certain dermatitides — is what causes the cracking and weeping people describe as "broken skin barrier." Stratum spinosum — the spiny layer. This is where most of the active biology happens. Langerhans cells patrol here as immune sentries. Melanocytes dump pigment into surrounding keratinocytes. Cells are connected by desmosomes, which give the layer its characteristic spiny appearance under the microscope. This layer provides most of the epidermis's tensile strength. Stratum basale — the basal layer. Single row of columnar cells sitting on the basement membrane. This is the stem cell compartment. Every keratinocyte in your entire epidermis traces back to divisions that happen here. Turnover time from basale to corneum is roughly 28 to 42 days in healthy young adults, slowing with age and sun damage.
Get the Full Details

Why The Hypodermis Confuses Everyone
Here's where I lost a patient once — or rather, where I lost a conversation. A colleague was explaining liposuction anatomy and casually referred to "three layers of skin" while counting the hypodermis as a skin layer. The patient nodded along, then later asked me directly how many layers she actually had. She'd read somewhere it was three and wanted confirmation. The issue is that lay sources and even some professional materials aren't consistent about whether the hypodermis counts. Standard anatomical terminology — Terminologia Anatomica, the gray's anatomy framework — treats the cutis (skin) as epidermis plus dermis only. The hypodermis is subcutis, separate. But in plastic surgery, dermatology procedures, and cosmetic contexts, people routinely reference it because it's structurally continuous and functionally relevant. Neither camp is wrong. They're just answering slightly different questions. If you include the hypodermis, you get three. If you don't, you get two macroscopic layers plus four or five microscopic epidermal subdivisions. The answer "two" is the most technically correct for gross anatomy. The answer "five" is the most technically correct for epidermal histology. The answer "three" is common in clinical shorthand but anatomically imprecise.
Counter-Intuitive Things Most People Miss
First: the number of layers isn't uniform across your body. The soles of your feet have five distinct epidermal layers because they need maximum abrasion resistance. Your eyelids have only three — the stratum lucidum is absent, and the granulosum is barely distinguishable. This regional variation is why certain conditions behave differently in different locations. Psoriasis on the scalp looks nothing like psoriasis on the eyelid, even though it's the same disease process. Second: the stratum corneum isn't just dead cells. It's a structured composite material — dead keratinocytes embedded in a lipid matrix that's essentially biological mortar. Think of it like brick and mortar construction. Remove the lipids (which is what harsh surfactants and over-exfoliation do), and the bricks stay but the wall falls apart. That's why moisturizers that contain ceramides, cholesterol, and fatty acids in roughly a 1:1:1 molar ratio actually repair barrier function, while plain hydration doesn't. Third: the dermis isn't a single layer either. It has a papillary dermis (loose connective tissue, capillaries, sensory endings) and a reticular dermis (dense irregular collagen, elastic fibers, appendages). Some sources count these as sub-layers, which pushes your total even higher if you're being thorough.
When The Standard Model Breaks Down
The five-layer epidermis model assumes healthy, normal skin. It fails in several common scenarios. Chronic sun exposure thickens the stratum corneum dramatically — that's solar lentigo and actinic keratosis territory. Diabetes can alter turnover kinetics without changing the layer count. Vitiligo destroys melanocytes in the basale but leaves the layer structure intact. Scars replace organized epidermis with disorganized collagen that lacks normal stratification entirely. Palmar and plantar skin is the biggest edge case. It's classified as "thick skin" specifically because of that extra stratum lucidum, but it also has a notably thicker stratum corneum — up to 150 cells thick in some areas of the sole. The dermis underneath is similarly reinforced with dense collagen bundles oriented to handle shear stress. This is why calluses form where mechanical stress concentrates and why blisters happen at the dermal-epidermal junction rather than within the epidermis itself.

A Practical Note From Working With Skin
When I'm evaluating barrier function clinically — and I see this more often than you'd expect in people who wash their hands excessively, work with solvents, or have eczema — I don't count layers. I look for signs that the layering has gone wrong. Dullness suggests a compromised corneum. Redness and stinging point to basale or spinosum irritation. Weeping means the barrier has failed completely and the dermis is exposed to the environment. The layer model is useful for understanding, but the clinical picture is what actually guides treatment. Topical treatments penetrate differently depending on which layer you're targeting. Corticosteroids need to reach the spinosum and basale to suppress inflammation effectively. Emollients work primarily in the corneum. Antifungals like terbinafine accumulate in the keratin-rich layers. Knowing which layer is which isn't academic — it determines whether a treatment will actually reach its target.
How Many Layers Of Skin Do We Have — Final Clarification
Two macroscopic layers if you mean the skin organ: epidermis and dermis. Four or five microscopic layers if you mean the epidermis alone, with the fifth appearing only in thick skin. Three if you're counting the hypodermis, which some contexts do and others don't. The number you should carry forward depends entirely on what question you're actually trying to answer. Anatomy exams want two. Histology exams want five. Dermatology consultations usually want neither number — they want to know whether your barrier is intact.