Understanding Cannabis Mortality: What the Data Actually Says
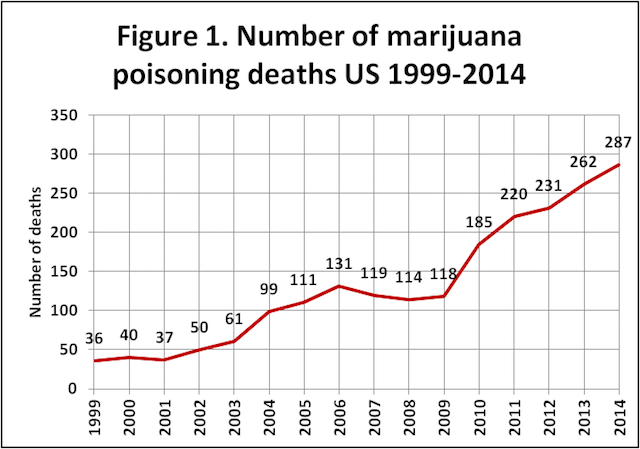
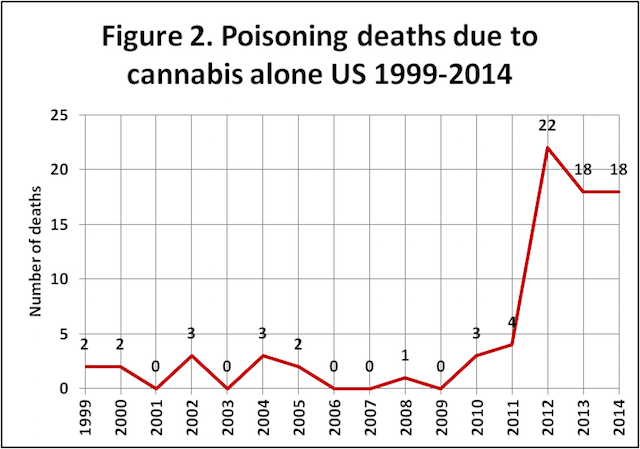
People ask this question a lot, usually because they've heard conflicting claims online. The straightforward answer is that there are no scientifically documented cases of death caused directly by cannabis overdose in humans. The lethal dose (LD50) of THC in animals is so astronomically high that it would be physically impossible for a human to consume enough plant material to reach a toxic threshold. That said, the full picture is more nuanced than a simple zero count. When you search this, most reliable sources point to zero confirmed fatalities from direct cannabis toxicity. The National Institute on Drug Abuse and various peer-reviewed studies consistently report no recorded deaths from pure cannabis overdose alone. That doesn't mean cannabis is risk-free, which is where the nuance comes in. The deaths that do appear in statistics are almost always indirect. Emergency room visits spike after cannabis use, particularly among first-time or heavy users experiencing acute anxiety, paranoia, or tachycardia. Driving incidents involving THC-positive individuals are another category where cannabis plays a role, though causation versus correlation is notoriously difficult to establish. A positive toxicology screen doesn't mean the person died because of weed — it just means weed was in their system.
I ran into this directly when helping someone interpret a relative's autopsy report a few years back. The cause of death was listed as accidental asphyxiation, but the toxicology showed THC at 20 nanograms per milliliter. The family wanted to know if cannabis killed them. It didn't. But impairment from cannabis likely contributed to the chain of events that led to the fatal outcome. That's the distinction most people miss when they're Googling mortality numbers. Synthetic cannabinoids are an entirely different problem. Products labeled as "spice" or "K2" have caused dozens of deaths and thousands of hospitalizations. These are not cannabis. They're laboratory-made compounds that hit the same CB1 receptors with far more unpredictable potency. When people conflate synthetic cannabinoids with natural cannabis, the statistics get muddied, and fear gets inflated.
Why the Confusion Persists
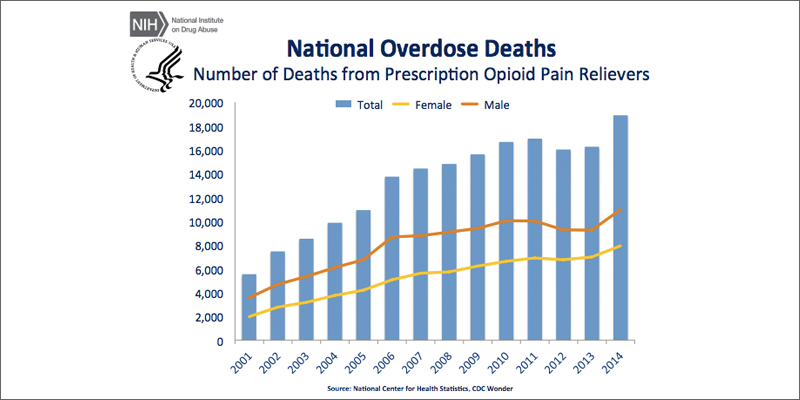
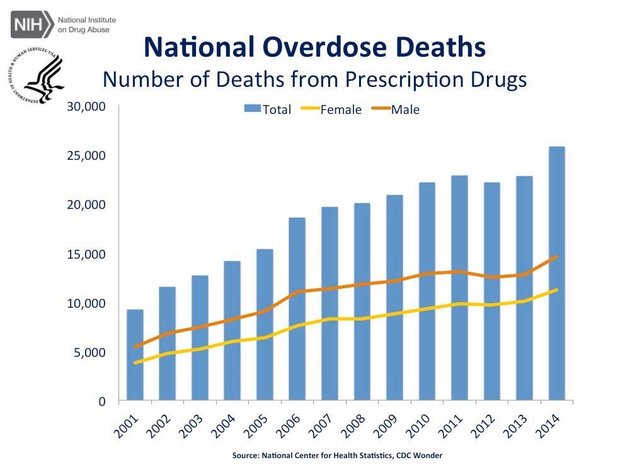
One counter-intuitive thing about this topic: the absence of direct fatalities is actually a well-established pharmacological fact, not a gap in the data. THC's mechanism of action simply doesn't depress respiratory function the way opioids do. That's the key difference. Opioids shut down the brainstem's drive to breathe. THC doesn't touch that system at lethal doses in humans. This is why you see opioid deaths climbing while cannabis-related deaths remain effectively at zero on a direct basis. Another thing beginners in this space often overlook: the route of administration matters enormously for risk assessment. Smoking cannabis introduces cardiovascular stress through combustion byproducts and carbon monoxide. Edibles introduce delayed onset times that lead to accidental overconsumption, which is where most ER visits come from. Neither pathway causes lethal toxicity, but both carry real — if non-fatal — risks. I once spent three hours explaining to a patient's family member that a cannabis-related death claim they'd read on a forum was based on a single case report that had since been retracted. The paper had confused correlation with causation. The patient had pre-existing cardiac disease and died of a heart attack after using cannabis. The article framed it as "weed killed this person." That's not how medical attribution works, and it's a pattern I see repeated in health literature every few months.
Get the Full Details
What the Numbers Actually Show
Emergency department visits related to cannabis have increased significantly since legalization in various US states. Colorado reported roughly 1,200 to 1,500 cannabis-related ER visits annually in the years following recreational legalization, according to published health department data. Most of these were for anxiety, psychosis, or vomiting — symptoms of cannabinoid hyperemesis syndrome in chronic daily users. None were fatal. Population-level studies tracking long-term cannabis users have not identified a mortality signal attributable to cannabis itself. A 2017 review in the journal Lancet Psychiatry found that while cannabis use disorder is real and treatment-worthy, direct mortality from the substance remains unestablished. The mortality risk is in the behaviors surrounding use, not the pharmacology. That said, there are legitimate downsides to treating cannabis as completely harmless. Chronic heavy use is associated with cognitive decline in adolescent users, increased risk of psychotic episodes in predisposed individuals, and respiratory issues from long-term smoking. These are health consequences. They're just not lethal ones in any documented case.
The Practical Takeaway
If you're trying to understand risk, focus on what actually kills people around cannabis use: driving impaired, mixing with alcohol or opioids, using unregulated products, or triggering underlying cardiovascular or psychiatric conditions. The substance itself, at the doses available in legal markets, does not produce lethal toxicity in humans. That's the data. It's also why you won't find a single verified case in the medical literature going back decades. The question keeps coming up because the internet rewards sensational claims. Zero deaths sounds like a cover-up to people who've seen horror stories about friends having bad trips or hearing about ER visits. But absence of evidence isn't evidence of absence when you're dealing with a substance that has been used for millennia and studied extensively for decades. The zero count is real, and it reflects basic human pharmacology, not propaganda.