Understanding Artificial Insemination Success Rates
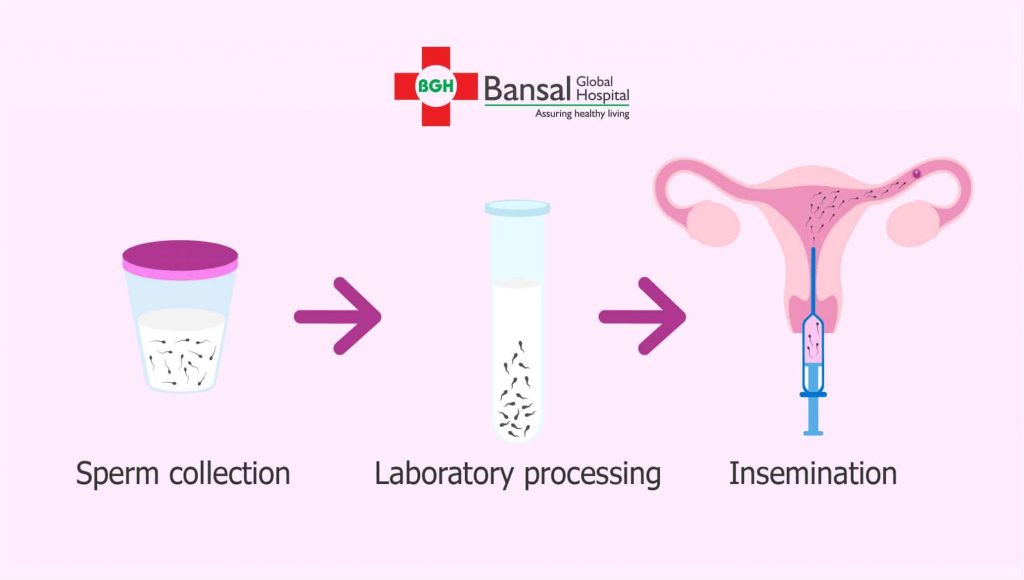
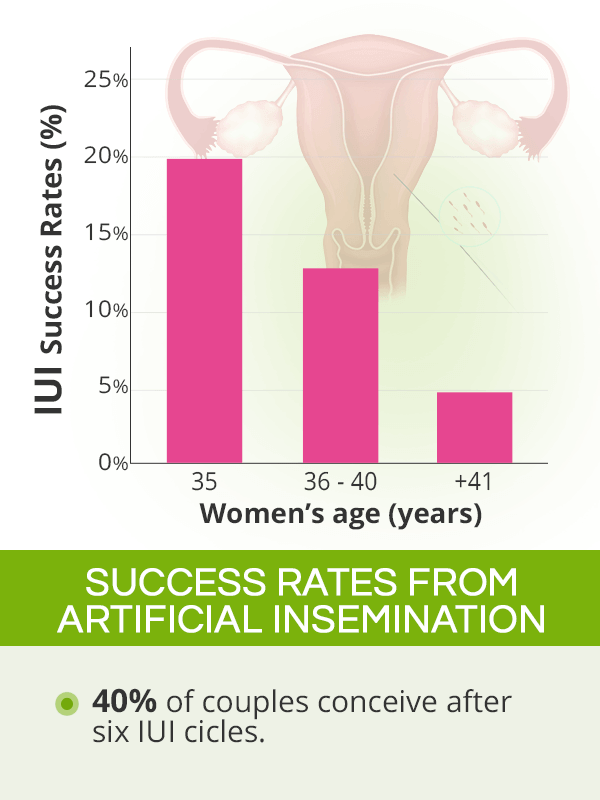
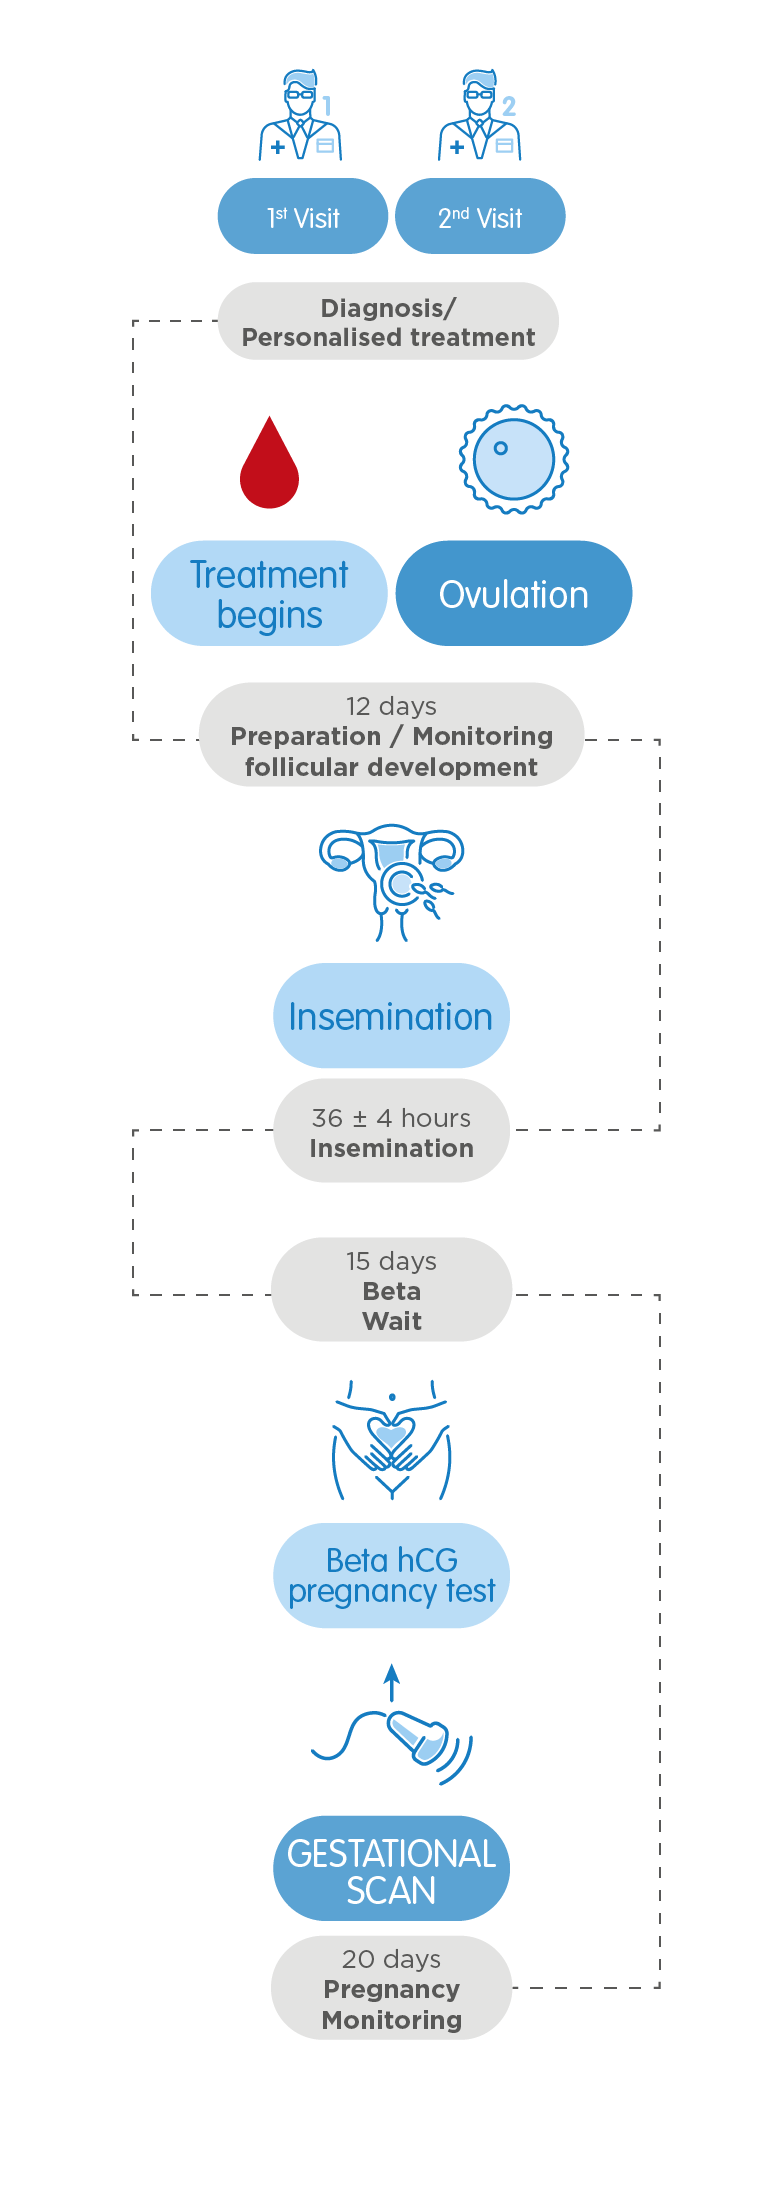
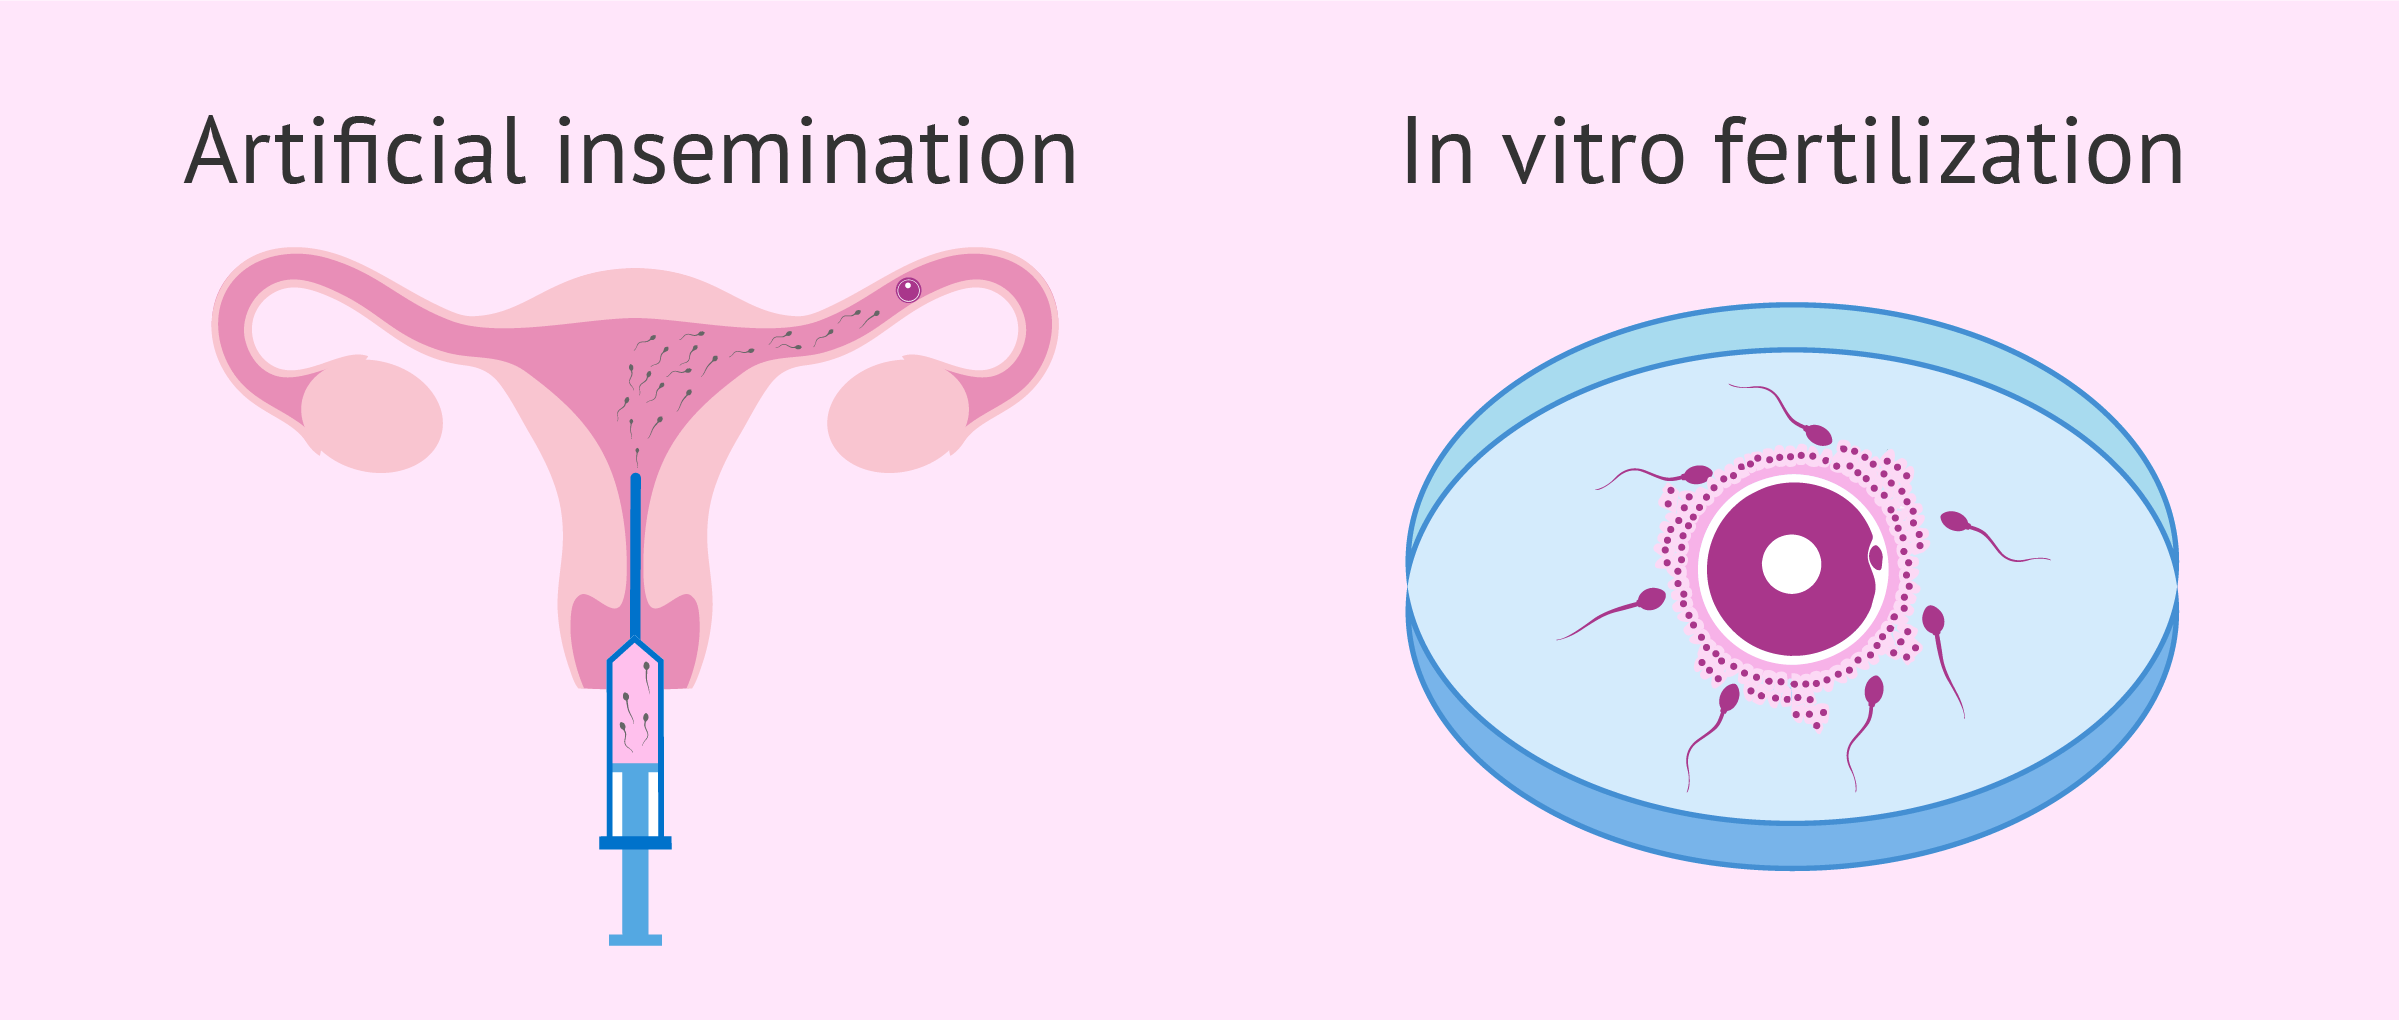
Artificial insemination is not a magic bullet, but it is a well-understood medical procedure with predictable outcomes when managed correctly. The success rates vary significantly depending on age, underlying fertility issues, sperm quality, and the clinic's methodology. Here is what the data actually says and how to interpret it. For women under 35, per-cycle success rates typically range from 10 to 20 percent with well-timed intrauterine insemination (IUI). That number drops to roughly 5 to 10 percent for women over 40. These are live birth rates per cycle, not just positive pregnancy tests, which is what most people actually care about. Over six cycles, cumulative success rates can reach 40 to 50 percent for younger women with unexplained infertility or mild male factor issues. The procedure itself is straightforward. Sperm is washed and concentrated in the lab, then placed directly into the uterus using a thin catheter. It takes about five minutes. There is no anesthesia. Most people walk out and go back to work the same day. The real variable is timing, and that is where mistakes happen.
I worked with a clinic that was consistently underperforming on IUI success rates for their older patients. We tracked the data and found the issue was not sperm preparation or technique. The problem was ovulation induction protocols. They were using clomiphene citrate alone for women over 38, when follicle-stimulating hormone (FSH) injections combined with hCG triggering produced significantly better results for that demographic. Switching protocols moved their over-38 success rates from 3.2 percent per cycle to about 8 percent. It was a small change that made a measurable difference, but nobody had bothered to look at the breakdown by age group before that.
Key Factors That Influence Success
Ovarian reserve is the single most important predictor. Anti-Müllerian hormone (AMH) levels and antral follicle counts tell you more about IUI success potential than age alone. A 38-year-old with an AMH of 2.5 has a better prognosis than a 34-year-old with an AMH of 0.6. This gets overlooked constantly. Sperm parameters matter more after processing than people expect. Total motile sperm count post-wash is the critical number. Anything below 5 million post-wash significantly reduces success rates. Above 10 million, the incremental benefit diminishes. This is why the wash matters, not just the raw semen analysis. Tubal patency is non-negotiable. Both fallopian tubes need to be open for IUI to work. A hysterosalpingogram (HSG) should be done before starting. I once saw a couple go through three failed IUI cycles before discovering one tube was blocked. That was a waste of time and money that could have been avoided with basic screening.
Get the Full Details
When IUI Fails and What Comes Next
If you have done three to six well-timed IUI cycles without success, moving to in vitro fertilization (IVF) is the standard recommendation. IVF success rates per cycle are substantially higher across all age groups. For women under 35, IVF live birth rates per cycle are around 50 to 55 percent at reputable clinics, compared to 10 to 20 percent for IUI. The cost difference is significant too. A single IUI cycle with medication runs roughly $1,000 to $4,000 depending on location and medications. A single IVF cycle typically costs $12,000 to $20,000. But when you factor in three to six IUI attempts before switching, the total investment often exceeds one IVF cycle while still yielding lower success. There are scenarios where IUI simply will not work. Severe male factor infertility with total motile sperm count below 1 million post-wash. Bilateral tubal blockage. Moderate to severe endometriosis. These cases bypass IUI entirely and go straight to IVF with intracytoplasmic sperm injection (ICSI). The clinic should tell you this upfront, not after you have already spent months on IUI.
Practical Considerations Most Guides Miss
The luteal phase support after IUI is often inadequate. Progesterone supplementation starting 2 to 3 days post-procedure is standard protocol at good clinics. Skipping this step can reduce implantation rates by 15 to 20 percent without anyone noticing immediately because pregnancy is less likely in the first place. Multiple gestation risk is real. With ovulation induction, there is a 5 to 10 percent chance of twins and a 1 to 2 percent chance of triplets or more. Higher-order multiples carry significant health risks for both mother and babies. Many clinics now recommend canceling cycles if more than three follicles reach mature size before triggering, which reduces success rates slightly but improves safety outcomes substantially. The psychological toll of repeated failures is underestimated. Each negative test triggers the same hormonal cycle and emotional response. After three or four failed attempts, burnout is common. Having a clear plan before starting, including how many cycles you will attempt before pivoting, reduces anxiety and prevents wasted months.
IUI remains a valid first-line treatment for specific patient populations. Unexplained infertility, mild male factor, cervical factor, and donor sperm cases respond best. But understanding the actual numbers, knowing when to stop, and recognizing the protocols that actually move the needle are what separate people who get pregnant from people who cycle through treatments without direction.