What Actually Happens When You Eat Something
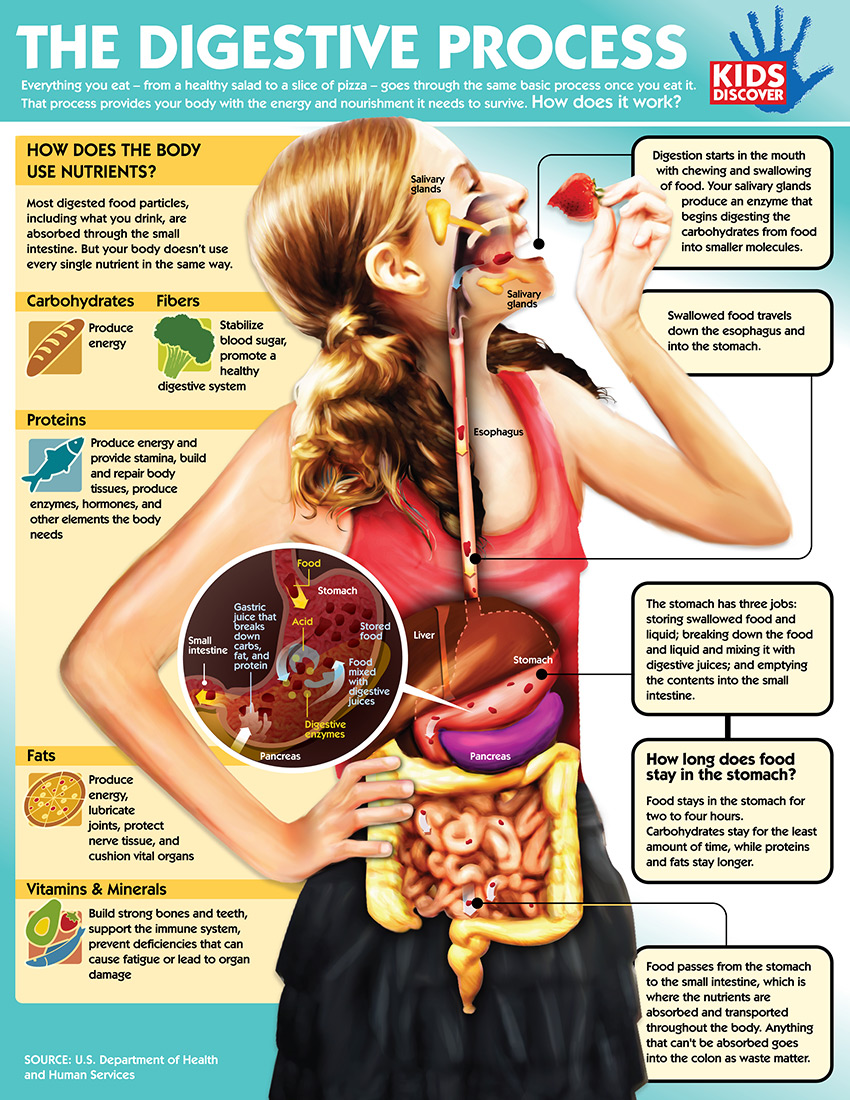
The digestive system is a long tube that runs from your mouth to your anus, and it's roughly nine meters long in adults. Most of that length is accounted for by the small intestine, which is folded up inside your abdomen in a way that would look chaotic if you could see it outside the body. The tube isn't just a passive pipe. It's lined with muscle layers, glandular tissue, and neural networks that coordinate every step of the process. Food enters the mouth and mechanical breakdown begins immediately. Molars grind and premolars shear. Saliva contains amylase, which starts breaking down starches into maltose before the food even leaves your mouth. This is why taste changes when you hold a plain cracker in your mouth long enough. The chemical process starts at that moment.
Understanding How The Digestive System Works
Once you swallow, the bolus travels down the esophagus through peristalsis, which is a wave of smooth muscle contraction that pushes food forward. This happens regardless of gravity, which is why people can digest food while upside down. The lower esophageal sphincter then opens to let the bolus enter the stomach and closes behind it. The stomach is a muscular sac that churns food with gastric juices. Hydrochloric acid drops the pH to around 1.5 to 2.0, which denatures proteins and kills most incoming pathogens. Pepsin begins protein digestion at that acidic pH. The chyme then passes through the pyloric sphincter into the duodenum, the first section of the small intestine. This is where bile from the liver and gallbladder mixes in, along with pancreatic juice containing bicarbonate and multiple enzymes. The bicarbonate neutralizes the acidic chyme. Without that neutralization, the intestinal lining would be damaged. The pancreas is particularly important here. It produces lipase for fat digestion, trypsin and chymotrypsin for further protein breakdown, and nucleases for nucleic acids. Most absorption happens in the jejunum and ileum, the middle and lower sections of the small intestine. The inner surface is covered in villi and microvilli, which increase the absorptive surface area to roughly 250 to 300 square meters. That's a surprisingly large surface, roughly the size of a tennis court, packed into a space no bigger than your torso. Nutrients pass through the intestinal epithelium into the bloodstream or the lymphatic system. Fats take the lymphatic route through lacteals because they're too large to enter blood capillaries directly.
The large intestine absorbs water and electrolytes. Bacterial fermentation here produces short-chain fatty acids and certain vitamins like K and biotin. The remaining material is stored in the rectum until defecation. The entire process from mouth to elimination typically takes between 24 and 72 hours, though transit time varies significantly between individuals and depends on diet, activity level, and gut flora composition. I worked with a patient once who had chronic fatigue and unexplained weight loss after a gastrointestinal infection. Standard workup came back normal. Endoscopy showed no ulcers or tumors. The issue turned out to be bacterial overgrowth in the small intestine, specifically in the jejunum where it shouldn't have been present in high concentrations. The SIBO test confirmed it. I had her do a lactulose breath test since that's more accessible than a jejunal aspirate, and the results showed an early peak in hydrogen, which indicated bacterial fermentation happening too high up in the small intestine. She was on rifaximin for 14 days and the symptoms improved within a week. The key insight was that the standard tests were missing it because the overgrowth was in the small bowel, not the colon where most people look first. There are a few things about digestion that most people get wrong or overlook entirely. One is that the stomach does not primarily absorb nutrients. It absorbs some alcohol and aspirin, but the vast majority of absorption happens downstream. Another counter-intuitive point is that bile is not produced by the gallbladder. The gallbladder only stores and concentrates bile. The liver produces it continuously. The gallbladder squeezes it out when CCK is released in response to fat entering the duodenum.
Get the Full Details

A common pitfall is assuming that enzyme supplements will fix malabsorption problems. They sometimes help, but they rarely address the root cause. If someone has poor fat absorption, checking for gallbladder function and pancreatic exocrine output is more useful than reaching for over-the-counter enzyme pills. Pancreatic insufficiency, for example, is diagnosed with a fecal elastase test, not by trial and error with supplements. The digestive system also has a well-documented gut-brain axis. The enteric nervous system contains roughly 500 million neurons, which is more than the spinal cord. These neurons communicate with the brain via the vagus nerve and influence mood, stress responses, and even cognitive function. People with IBS frequently report anxiety and depression at higher rates, and this isn't just psychological. The signaling is bidirectional and physiological. There are clear limitations to how well the digestive system can handle certain situations. Chronic alcohol consumption damages the gastric mucosa and impairs pancreatic function. High-dose NSAIDs like ibuprofen and naproxen reduce prostaglandin protection in the stomach lining, which is why ulcers are a known side effect. Some medications, like bisphosphonates for osteoporosis, can cause esophageal ulceration if they get stuck on the way down. You're supposed to stay upright for 30 minutes after taking those.
Intestinal transit time can be thrown off by almost anything. A bout of food poisoning slows things down through inflammation. Travel changes both what you eat and the water you drink, and that alone can disrupt patterns for weeks. The microbiome doesn't reset quickly. Fecal transplants work for recurrent C. diff because they're essentially resetting the ecosystem, which shows how dependent digestion is on the bacterial population rather than just the host organs. For anyone trying to understand their own digestion, tracking what you eat alongside symptoms for a couple of weeks is more informative than any single test. Food diaries are tedious but they reveal patterns that clinical testing misses. Lactose intolerance, for instance, is often self-diagnosed correctly by the patient long before any breath test is ordered. The limiting factor is that correlation doesn't equal causation. Eliminating dairy might make you feel better because you're eating less fat overall, not because of the lactose specifically. The pancreas deserves more attention than it gets. It's both an endocrine and exocrine organ. The exocrine part handles digestion. The endocrine part handles blood sugar regulation through insulin and glucagon. When the exocrine function fails, malabsorption follows. When the endocrine function fails, you get diabetes. Both can happen simultaneously in chronic pancreatitis, which is usually caused by long-term alcohol use but can also result from genetic mutations or autoimmune conditions.
The liver is another organ that gets reduced to a single function in most explanations. It produces bile, yes, but it also filters blood from the gut through the portal vein before that blood reaches systemic circulation. It stores glycogen, synthesizes clotting factors, produces albumin, and processes drugs and toxins. Every substance absorbed from the digestive tract passes through the liver first. That's called first-pass metabolism and it's why some drugs can't be taken orally. Hydration matters more for digestion than most people realize. The digestive tract secretes roughly seven liters of fluid daily through saliva, gastric juice, bile, pancreatic juice, and intestinal secretions. Most of that fluid is reabsorbed, but dehydration reduces secretion volume and slows motility. Constipation is one of the earliest signs of inadequate fluid intake, and it's often dismissed as something to ignore until it becomes severe. The role of the mesentery has only recently been properly recognized in mainstream anatomy. It's not just a scaffolding structure. It's a continuous membrane that suspends the intestines and contains its own lymphatic and vascular supply. Research into the mesentery is still evolving, and it may explain some of the connections between gut inflammation and systemic conditions that don't fit neatly into existing models.

If you're dealing with persistent digestive issues that haven't responded to basic dietary changes or over-the-counter remedies, the next step isn't more experimentation. It's targeted testing. Stool studies, breath tests, blood work for celiac disease and pancreatic function, and sometimes imaging or endoscopy. The order matters. You start with the least invasive and move up. The system itself will tell you where the problem is, usually through the symptoms, but the symptoms are nonspecific. Fatigue and weight loss point somewhere different than burning epigastric pain after meals. There's no single explanation that covers all variation in how digestion works between people. Genetics, environment, diet history, medication use, and stress levels all interact. The model is consistent but the expression varies. Understanding that variance is where the practical knowledge comes from, not from memorizing the textbook pathway.