The Problem With Everyone's Tidal Volume Calculations
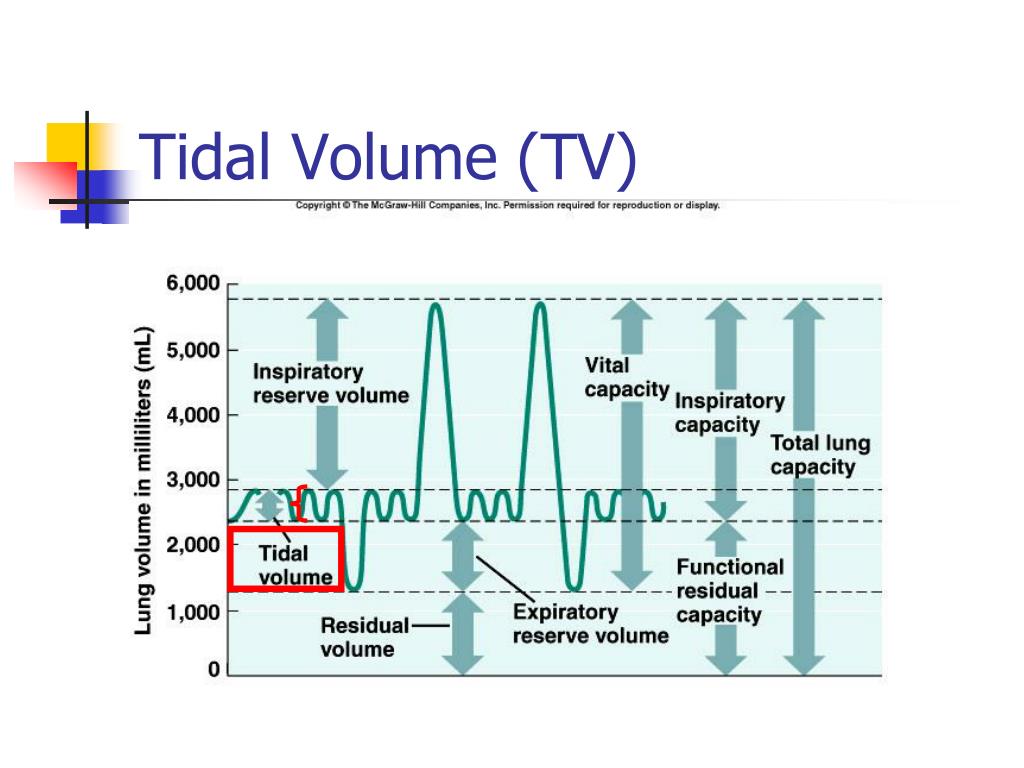
I've been running ventilators in ICUs for over a decade, and I still see people pulling tidal volume numbers out of thin air. They grab the textbook ideal body weight formula, punch it into a calculator, and call it a day. Here's what they're missing: the math is only the starting line. The standard formula everyone quotes is simple enough to scribble on a napkin. You take ideal body weight and multiply by 6 to 8 milliliters per kilogram. That gives you your tidal volume in milliliters. For a person who weighs 70 kilograms, that's roughly 420 to 560 milliliters per breath. The catch nobody mentions upfront is that ideal body weight has nothing to do with actual weight. If you just plug the number from the scale into the equation, you're going to ventilate someone way too aggressively. Let me show you how to actually get the ideal body weight right.
For men, the Devine formula goes like this: 50 kilograms plus 2.3 kilograms for every inch over five feet. For women, it's 45.5 kilograms plus 2.3 kilograms per inch above five feet. So a woman who is five foot seven inches tall would be 45.5 plus 2.3 times seven, which comes out to about 61.6 kilograms ideal body weight. Multiply that by six, and you're looking at roughly 370 milliliters of tidal volume, not the 490 you'd get if you used her actual weight of, say, 80 kilograms. I learned this the hard way back in 2018. I had a 110-kilogram man, obese and in respiratory failure from ARDS. I calculated his tidal volume off his actual weight instead of his ideal weight. His plateau pressure went through the roof within minutes. The alveoli couldn't handle it. I cut his volume back down to 350 milliliters based on ideal body weight, and the pressures stabilized immediately. That mistake could have caused real barotrauma. Since then, I've made sure I always convert to ideal body weight first, every single time, without exception.
Where the Standard Formula Falls Apart
The 6 to 8 mL/kg range works fine for most people with normal lungs. But normal lungs are the minority in the ICU. When someone has established ARDS, the protocol shifts to 4 to 6 mL/kg of ideal body weight, sometimes lower. The ARDSNet trial proved this back in 2000, and it's now standard of care. If you're treating acute lung injury or ARDS and you're still using 8 mL/kg, you're running against the evidence. There's another edge case that trips people up consistently. When calculating tidal volume for a patient on high PEEP, the delivered volume can be less than what you set on the ventilator because the gas compresses in the circuit. I once had a situation where a patient was set for 450 milliliters but the exhaled volume coming back was only 320 milliliters. The ventilator's internal tubing compliance was eating up about 130 milliliters. You have to account for that by multiplying the circuit pressure by the compliance factor, which is usually around 2 to 3 milliliters per centimeter of water pressure for adult circuits. Without that adjustment, your tidal volume is wrong and you don't know it. Another thing worth mentioning: this whole calculation assumes you're using volume-controlled ventilation. If you're in pressure-controlled mode, the tidal volume is whatever it ends up being based on the set pressure, the patient's lung compliance, and the resistance. You can't directly set a tidal volume in that mode. You set the inspiratory pressure and monitor what comes out. I've seen junior residents get confused by that constantly. They ask why their tidal volume keeps changing when they think they've set it. You haven't set it. You've set a driving pressure and the lungs decide the rest.
Get the Full Details
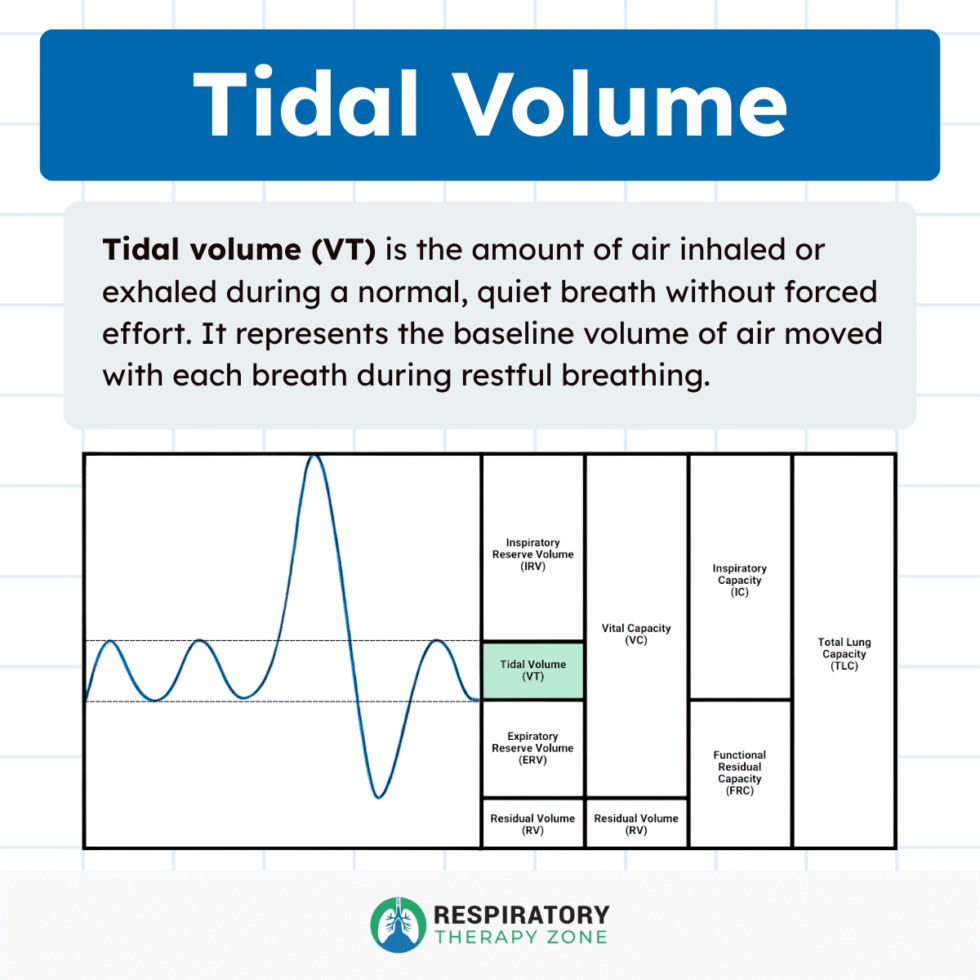
So here's the practical workflow I use, every time, without skipping steps. First, determine whether the patient has ARDS or acute lung injury. If yes, you're targeting 4 to 6 mL/kg of ideal body weight. If the lungs are relatively normal, 6 to 8 mL/kg is reasonable. Second, calculate ideal body weight using the Devine formula, double-checking the height and the sex-based formula. Third, account for circuit compliance loss if the peak pressures are high. Fourth, check the plateau pressure after delivering that volume. If the plateau pressure is above 30 centimeters of water, drop the tidal volume by 10% and recheck. Fifth, verify the actual exhaled tidal volume matches what you calculated, not just what the ventilator display says, because the display includes the compressed gas in the tubing. That last step is where most errors hide. The ventilator shows you what it delivered, but the patient received less because some of it stayed compressed in the breathing circuit. I track this by comparing the set volume against the measured exhaled volume every time I adjust the settings. The difference tells me how much compliance loss I'm dealing with in that particular circuit setup. The formula itself is elementary. The difficulty is in knowing which version of the formula applies, which assumptions are actually true for the patient in front of you, and what you do when the numbers don't match the clinical picture. I've seen plenty of patients where the textbook calculation looked perfect on paper and the patient still deteriorated because something real-world got ignored. Plateau pressures, auto-PEEP, dynamic compliance trends, changes in sedation level affecting spontaneous effort. The math is easy. The judgment is the hard part.