Building Interactive Training Systems for Nursing Simulations
I spent three years building clinical decision-making modules for a hospital network that wanted to replace their paper-based orientation with something that actually kept residents engaged. The result was a browser-based simulation where students triaged virtual patients, interpreted lab values in real time, and learned to prioritize care under time pressure. It worked better than expected, but not in the ways most people assume it would. The core insight that most designers miss is that nursing isn't really about memorizing protocols. It's about pattern recognition and decision-making under uncertainty. A student who can recite the steps for administering IV medication doesn't mean they'll catch the one thing that makes a patient's condition deteriorate. So I structured the gameplay around ambiguity, not correctness.
How To Create Gameplay For Nursing That Actually Teaches Something
Start with the assessment loop. Every scenario should force the player to gather data before making decisions. Blood pressure, heart rate, respiratory rate, level of consciousness. Let them click on vital signs, order labs, review medication lists. The frustration you want to cultivate is the same frustration nurses feel in real shifts. You don't have all the information, and you still have to decide. I built a specific scenario around a post-operative patient whose vitals were deteriorating slowly. The trick was that the change was gradual enough that players who didn't chart readings every five minutes missed the trend entirely. One resident told me he failed three times before realizing that the answer wasn't in any single number, but in the trajectory. That moment is the entire point of the exercise. The challenge comes when you try to balance authenticity with playability. Real nursing documentation takes hours. Real patient assessments involve interruptions, missing information, and conflicting priorities. If you simulate that literally, players will quit. So you compress time, you simplify the environment, but you preserve the cognitive load. The patient's condition should always be slightly worse than the data suggests. That gap between what they see and what's happening is where learning occurs.
Another problem I ran into is the evaluation metric. How do you grade a nursing decision? Most people default to checking whether the player chose the right action, but that misses half the learning. A student might select the correct intervention but do it after unnecessary delays, or they might prioritize symptoms over root causes. I started tracking decision timing, information gathering sequence, and whether players revisited earlier assumptions when new data arrived. Those metrics correlate better with clinical performance than simple right-or-wrong scoring. You'll need to decide what platform you're building for. Browser-based tools like Unity WebGL or Phaser keep accessibility high and deployment simple. If you want mobile compatibility or offline use, a native build makes sense. I've seen teams waste months trying to perfect responsive design when the actual constraint was content quality. The technology is secondary. The scenarios are what students remember. Content creation is where most projects stall. Writing a single realistic patient case with multiple branching paths takes about two weeks for an experienced writer who understands clinical workflows. That's not counting peer review by nursing faculty, which adds another week minimum. The team I worked with had four full-time writers and still moved slower than we expected. The bottleneck isn't writing. It's maintaining clinical accuracy across hundreds of decision points.
Get the Full Details
.jpg)
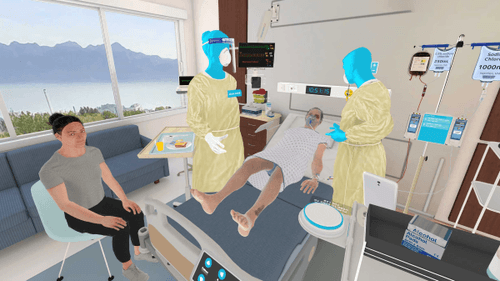
Here's a practical workaround that saved us months. Instead of building branching narratives from scratch, we mapped existing clinical guidelines as decision trees. The Institute for Safe Medication Practices has publicly available flowcharts for common medication errors. The American Heart Association publishes cardiac arrest algorithms. You can convert those directly into gameplay branches. Students are already familiar with the structure, which reduces the cognitive overhead of learning your system. Audio and visual design matter less than you'd expect. I used static images with CSS animations for vital sign changes and simple sound effects to indicate alerts. One hospital tried a full 3D environment with animated characters and complained that players spent more time clicking around the room than assessing patients. Less polish often means better learning outcomes because it forces attention onto the data, not the presentation. The biggest limitation I encountered is scale. A truly comprehensive nursing simulation would require thousands of scenarios to cover the breadth of clinical practice. Most teams build maybe fifty to a hundred. That's enough for orientation training, but it won't prepare someone for every situation they might face. If your goal is certification prep or advanced clinical judgment, you need either an enormous content library or a procedural generation system that creates scenarios dynamically. Both approaches have serious flaws. Procedural generation tends to produce unrealistic edge cases that don't teach generalizable skills.
Another downside is that these systems can't replicate human interaction. Role-playing patient conversations, reading emotional cues, managing family dynamics. All of that happens in clinical rotations but almost never in digital simulations. I've seen programs claim their tool replaces bedside teaching. That's inaccurate. These systems supplement clinical experience. They don't replace it. Be honest about what your product does and doesn't do. If you're starting fresh, I'd recommend building a minimal prototype before investing heavily in production. Create one complete scenario with three to five decision points, test it with actual nursing students, and iterate based on where they struggle. The prototype phase usually reveals more about what works than any amount of planning. We spent six weeks prototyping and discovered that players consistently misinterpreted certain lab values. That feedback shaped every scenario we built afterward. Tools worth considering include Twine for narrative prototyping, Godot for lightweight 2D builds, or Unity if you need more complex interactions. For multiplayer scenarios where multiple students manage the same patient, Node.js with WebSockets handles real-time state reasonably well. Database-wise, PostgreSQL keeps things simple for structured patient data, though a document store like MongoDB offers more flexibility for variable clinical information.
The market for this kind of tool is growing but fragmented. Academic institutions buy enterprise licenses, hospitals use it for onboarding, and independent educators sell standalone scenarios. Pricing varies from free open-source projects to forty thousand dollars for fully supported institutional deployments. If you're building this as a business, clarify whether you're selling software or selling educational outcomes. Those are different products with different sales cycles and different buyers. What I wish someone had told me before starting is that clinical accuracy requires clinical expertise. No amount of programming skill compensates for scenarios that don't reflect how medical decisions actually work. Partner with nurses early and often. Pay them for their time. Their feedback will save you from building something that looks plausible but teaches the wrong habits.
.jpg)