What nobody tells you about spotting motor speech delays in kids
A five-year-old came to my clinic last year who could flap his lips, buzz on vowels, and imitate animal sounds on command. Try having him say "ba-ga-da" and he'd produce "ga-ba-da" with varying success across trials. Same child, same request, different failures each time. That inconsistency is the thing that separates apraxia from almost everything else. Phonological disorders are predictable. Apraxia is not. I've seen speech pathologists miss this for months because the kid sounded fine on spontaneous words but fell apart on structured tasks. That's not a sign of improvement. That's a sign of grafted motor planning.
How To Diagnose Childhood Apraxia Of Speech
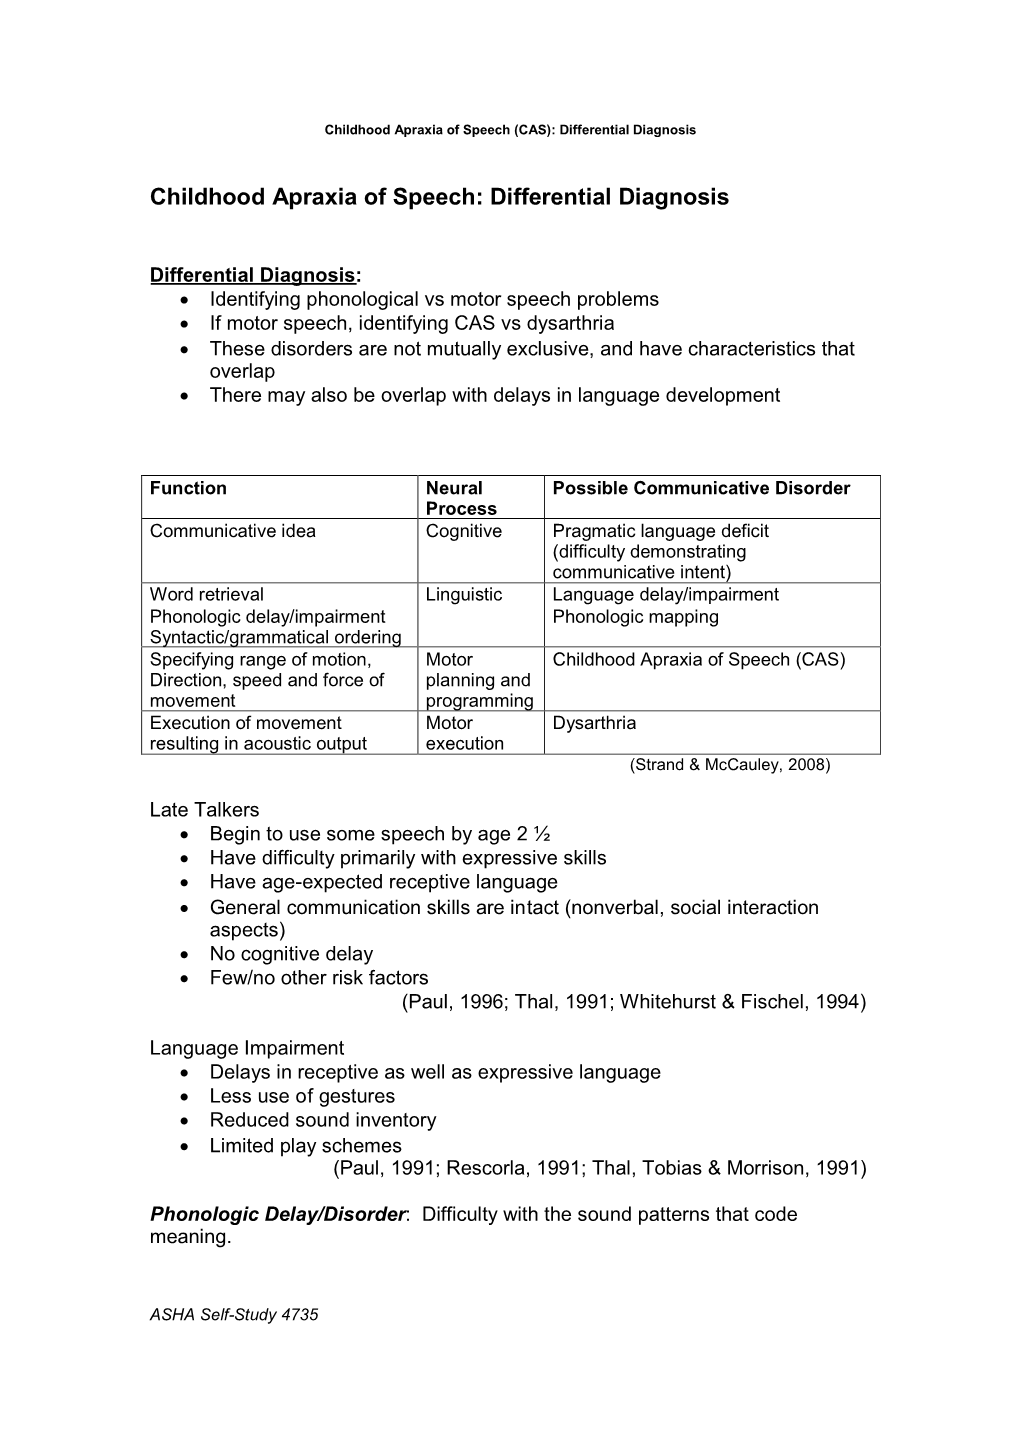
There is no single test. The gold standard remains clinical observation using the ASHA criteria, which breaks down into three core features: inconsistent consonant and vowel errors across repetitions, distorting vowels and consonants, and prosodic abnormalities including mismatched stress and rhythm. You layer on secondary markers like gapping between syllables, abnormal touch and tongue movement, and increased difficulty with longer or more complex utterances. But the criteria alone won't save you. I had a child recently who checked every box on paper and yet turned out to be a severe phonological disorder with a co-occurring hearing fluctuation. Pure audiometry missed the mid-frequency dips because the kid passed on one ear and failed on the other during the same session. We ended up doing tympanometry and speech audiometry alongside the standard screening, and the full picture emerged only after that.
What actually happens during an assessment
You start with a case history that goes beyond "is he talking?" You ask about oral non-speech motor tasks. Can the child sequence lip and tongue movements on command? Pretend to blow, lick, and chew in order. Most kids with pure language delays handle this fine. Kids with apraxia struggle here too, and that overlap is one reason the differential takes time. Then you move to speech sampling. Natural play is useful but insufficient on its own. You need elicited samples across different word lengths and structures. Three-syllable sequences like /apa/ and /adada/ are revealing because they require rapid motor sequencing. A child who can say "mommy" but cannot approximate "banana" in any stable form is raising a flag. A child who says "nana" consistently but never attempts the full word might just be simplifying. The difference matters for treatment planning. I once worked with a child whose parents insisted he was "word bombing" and had a huge vocabulary at home. In the clinic, he produced roughly twelve intelligible words and those twelve varied across sessions. What looked like a typical expressive language gap was actually a motor planning deficit hiding behind parental hope. Getting parents to accept the discrepancy is the harder part, not the diagnosis itself.
Get the Full Details

Tools that help and tools that don't
The PRESECan and the Dynamic Evaluation of Motor Speech Function are standardized instruments designed for this population. They add structure and can be useful for tracking progress, but they are not diagnostic keys on their own. I've seen both used correctly and incorrectly, usually because the examiner treats the scores as definitive rather than as one data point among many. Instrumental measures like electromagnetic articulography or ultrasound can show tongue movement patterns, but they are expensive, require specialized equipment, and are rarely available outside research settings. For most clinicians, good-quality video recording and careful listening are more practical and often just as informative for the initial identification. One thing I wish were more widely understood: acoustic analysis software like PRAAT can reveal vowel space reduction and abnormal intonation patterns that the ear misses in real time. A child might sound approximately clear on casual listening but show a compressed vowel space that correlates with the motor planning difficulty. This is especially useful when the child's speech is variable enough that impressionistic judgment becomes unreliable.
Counter-intuitive things to keep in mind
Kids with co-occurring phonological disorders can mask apraxia. The phonological errors create noise that makes it harder to see the motor planning issues underneath. I've spent entire sessions trying to separate the two before committing to a diagnosis. It's not always clean. Conversely, a child with apraxia might initially present with what looks like typical development because single words are intact. The breakdown appears only when the demands increase. That delayed recognition is frustrating but common. The diagnosis often lands months after the first red flag, sometimes not until the child enters preschool and the gap between ability and performance becomes impossible to ignore. There is also the issue of dialect and bilingualism. If a child speaks a dialect where certain consonant clusters are routinely simplified, you need to account for that before calling it apraxic. I work with several bilingual families where the initial concern was apraxia and the eventual picture was a second-language acquisition pattern that looked similar but required a completely different intervention approach. Consulting with a clinician familiar with the child's linguistic background is essential here.
When the diagnosis remains uncertain
Sometimes you simply cannot determine whether apraxia is present alongside other disorders. In those cases, the practical move is to target the most impactful area first. Motor speech intervention can be beneficial even when the full diagnostic picture is unclear, and it does not interfere with identifying a phonological disorder later. The risk is over-treating or under-treating, and both directions happen regularly in practice. Early referral to a pediatric SLP who specializes in motor speech is the single most reliable action. General pediatricians are not trained to differentiate this from typical language delay, and parents often hear "wait and see" until the child is well past the window where targeted intervention is most effective.