Why Most Head To Toe Assessment Documentation Gets Rejected
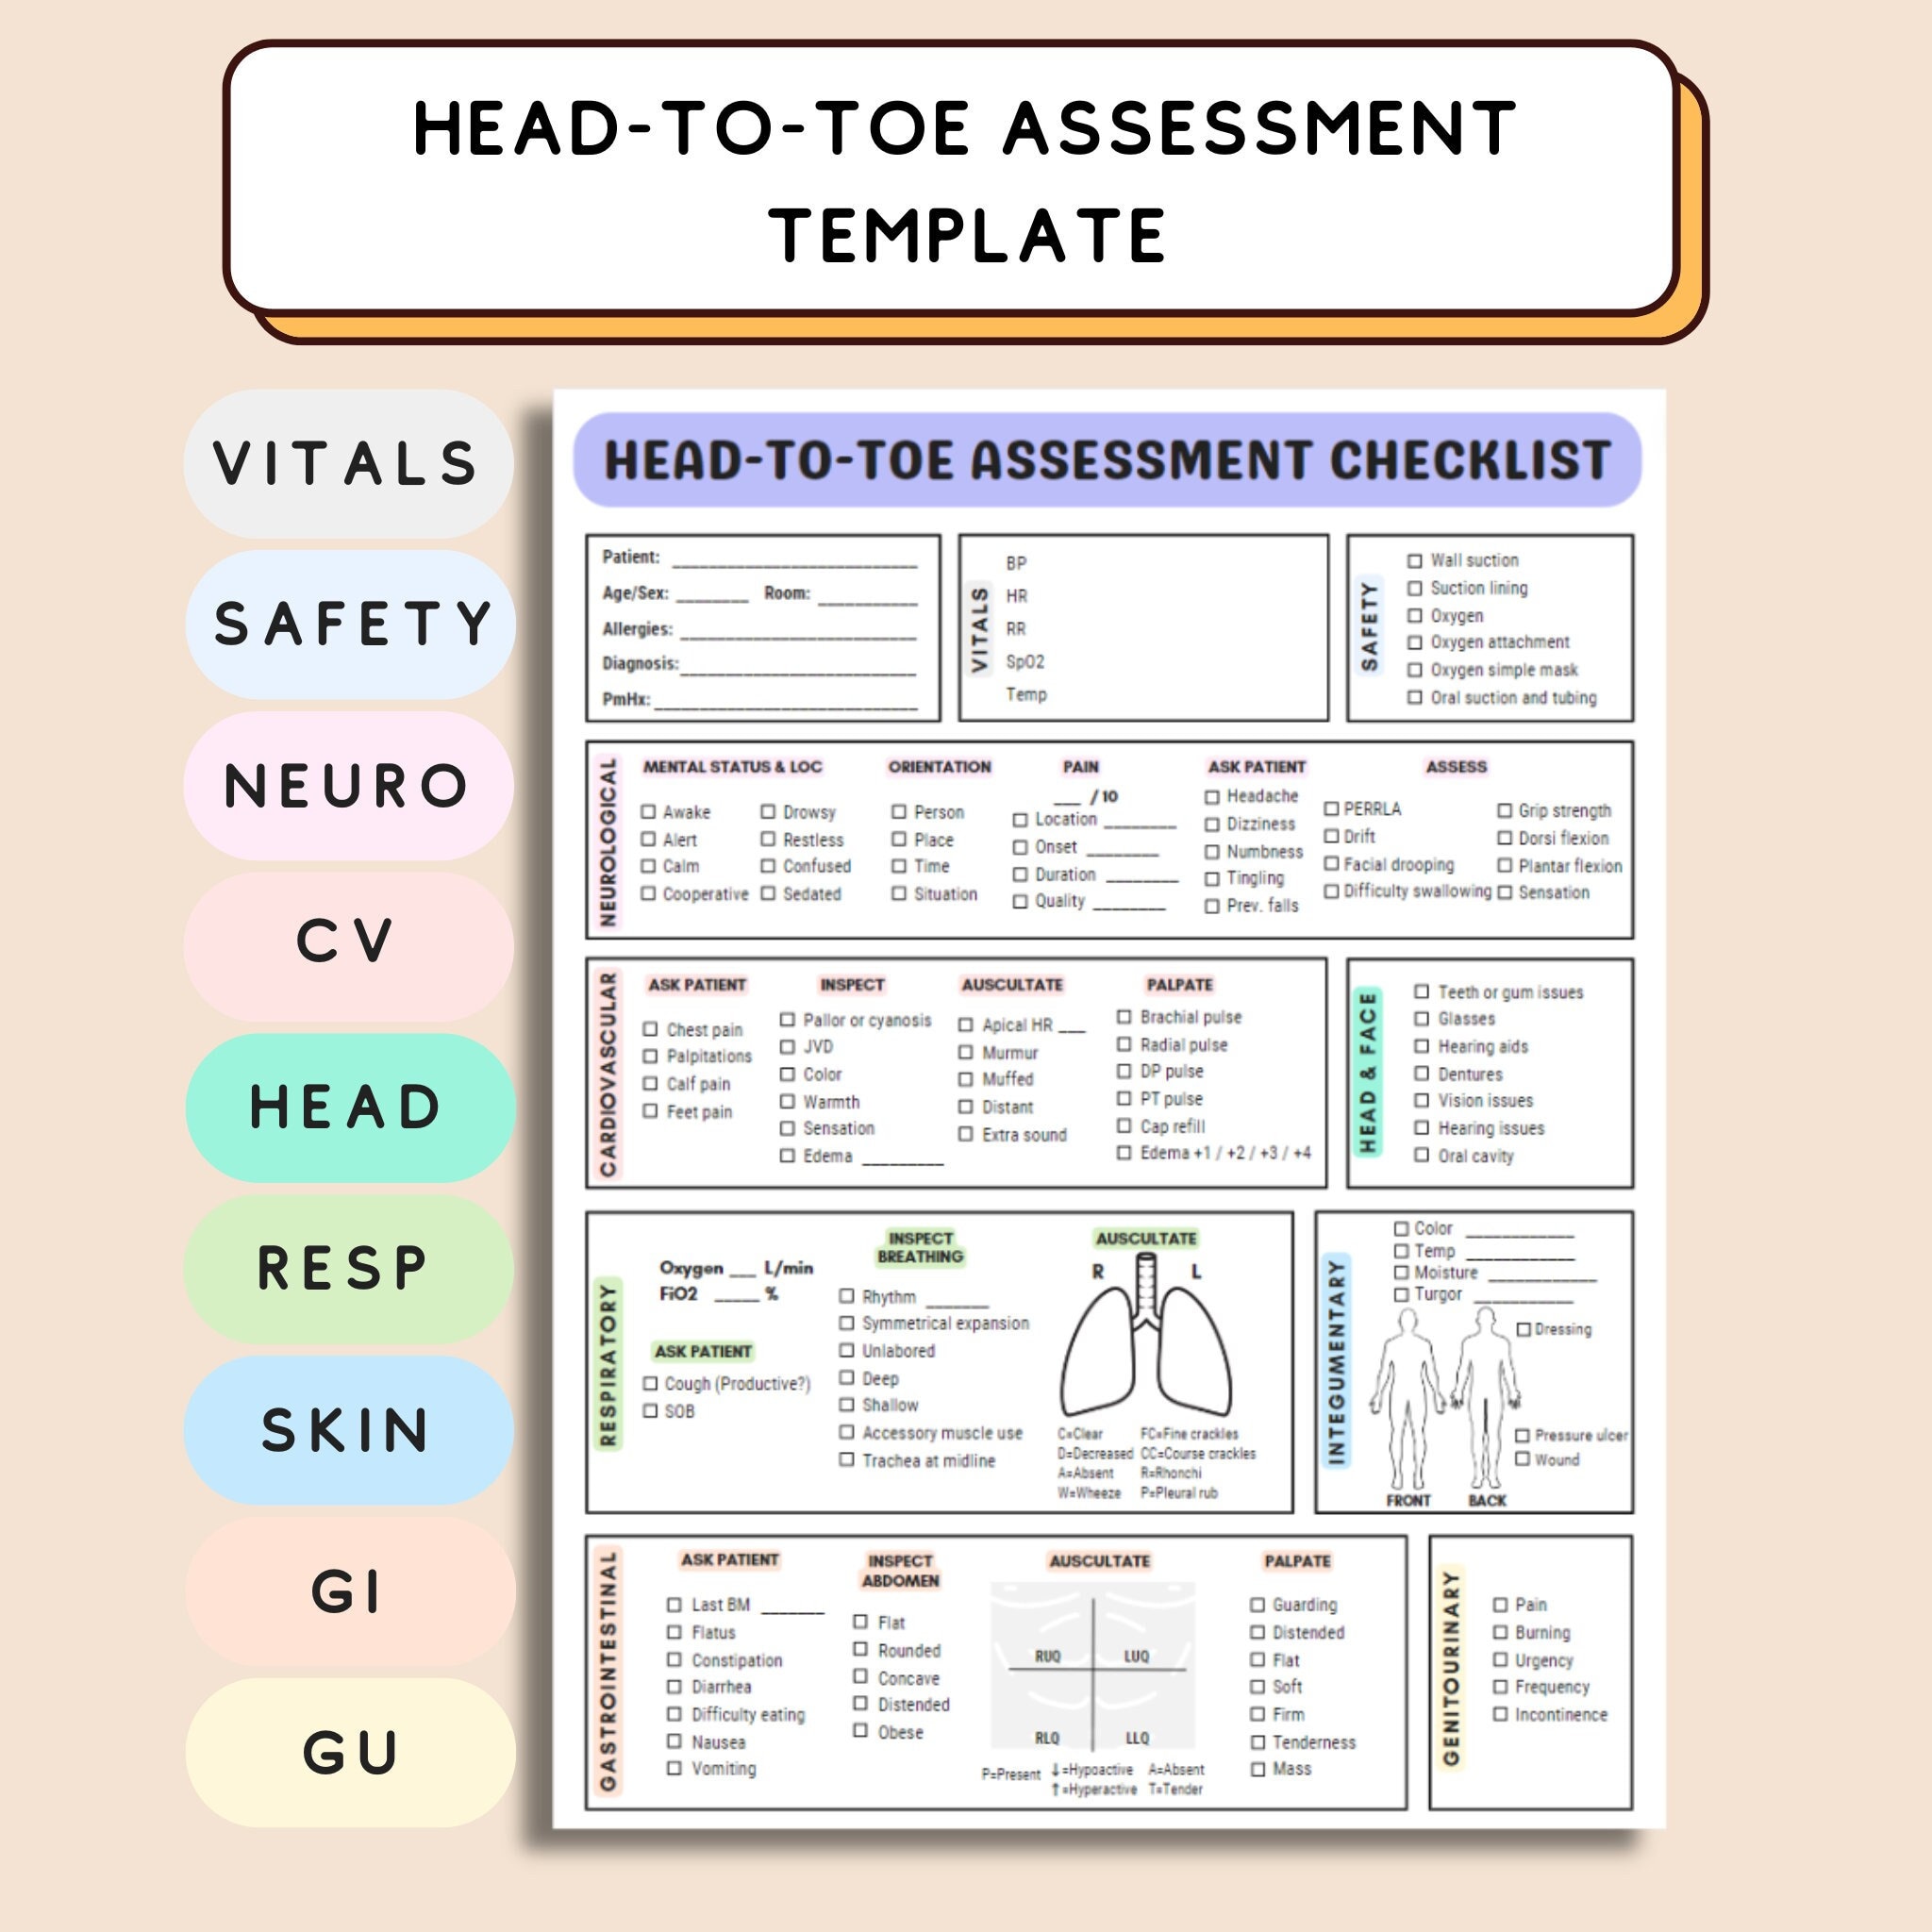
I used to chart like I was trying to pass a forensic exam. Every sentence perfectly structured, every adjective carefully placed. Then my preceptor told me the case manager spent more time decoding my notes than actually reading them. That's when I stopped performing and started documenting. The process itself is straightforward. You start at the head and work down systematically. The trick is making it usable for the next person who touches the patient.How To Document A Head To Toe Assessment
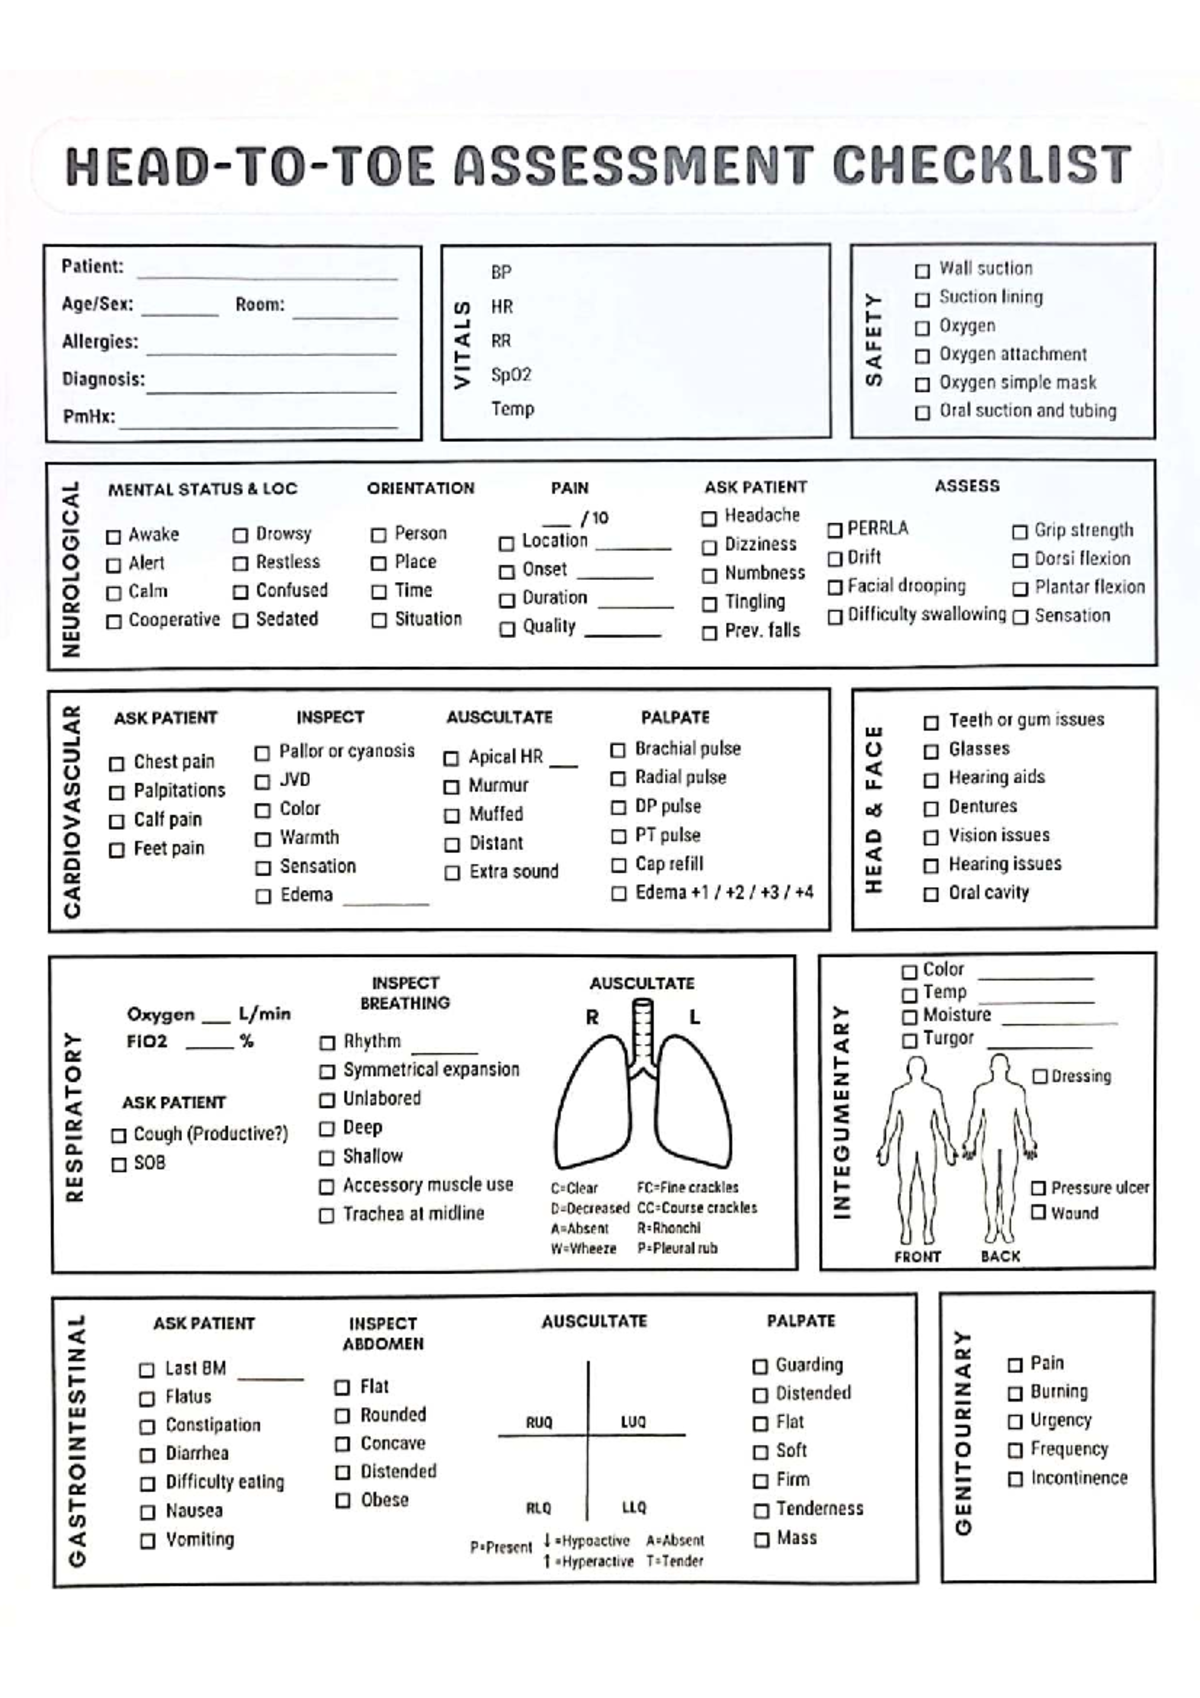
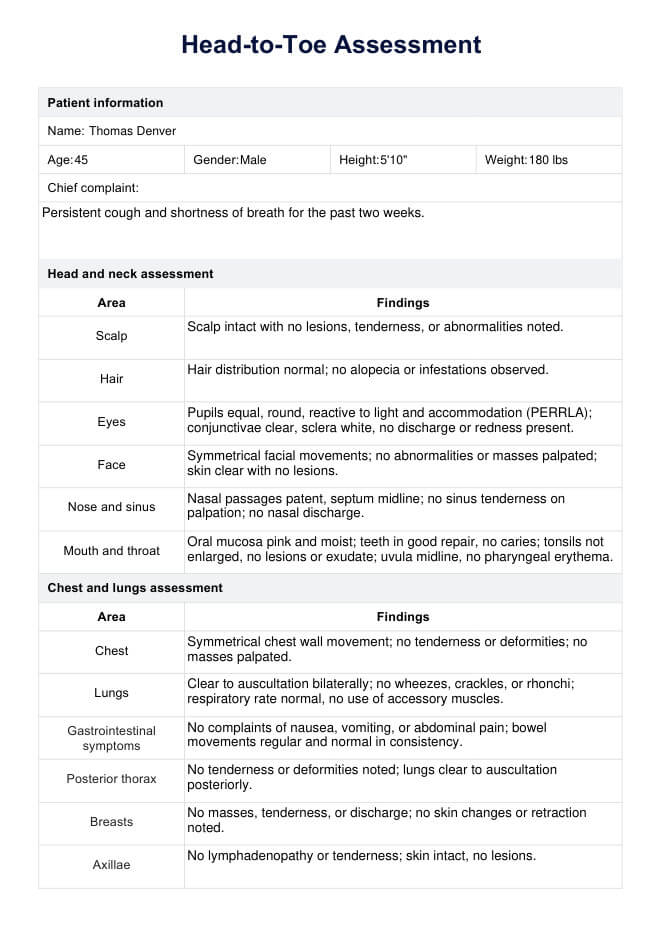
Head and Face: Note pupil reaction, extraocular movements, and any facial asymmetry. Don't just write "PERRLA" and move on. Write the actual size in millimeters. Write the latency of response. I had a resident dismiss my note because it said "normocephalic" without mentioning the mild periorbital edema he would have caught if he'd actually looked at the patient. Documentation is not a checkbox exercise. It's a record of what you observed with your own eyes. Eyes, Ears, Nose, Throat: This section gets rushed. It doesn't need to be. Document conjunctiva color, scleral icterus, nasal mucosa appearance, and oropharynx findings. If you're doing trauma, check for Battle's sign and raccoon eyes. These take hours to develop. Catching them early matters. Neck: Assess range of motion, jugular venous pressure, thyroid palpation, and lymph nodes. Document JVP at a specific angle — 30 degrees or 45 degrees, not just "elevated." I once saw a readmission happen because the original note said "neck supple" without noting a non-reducible goiter that had been there the entire stay. The patient was sent home with instructions to follow up in three weeks. They came back in respiratory distress.
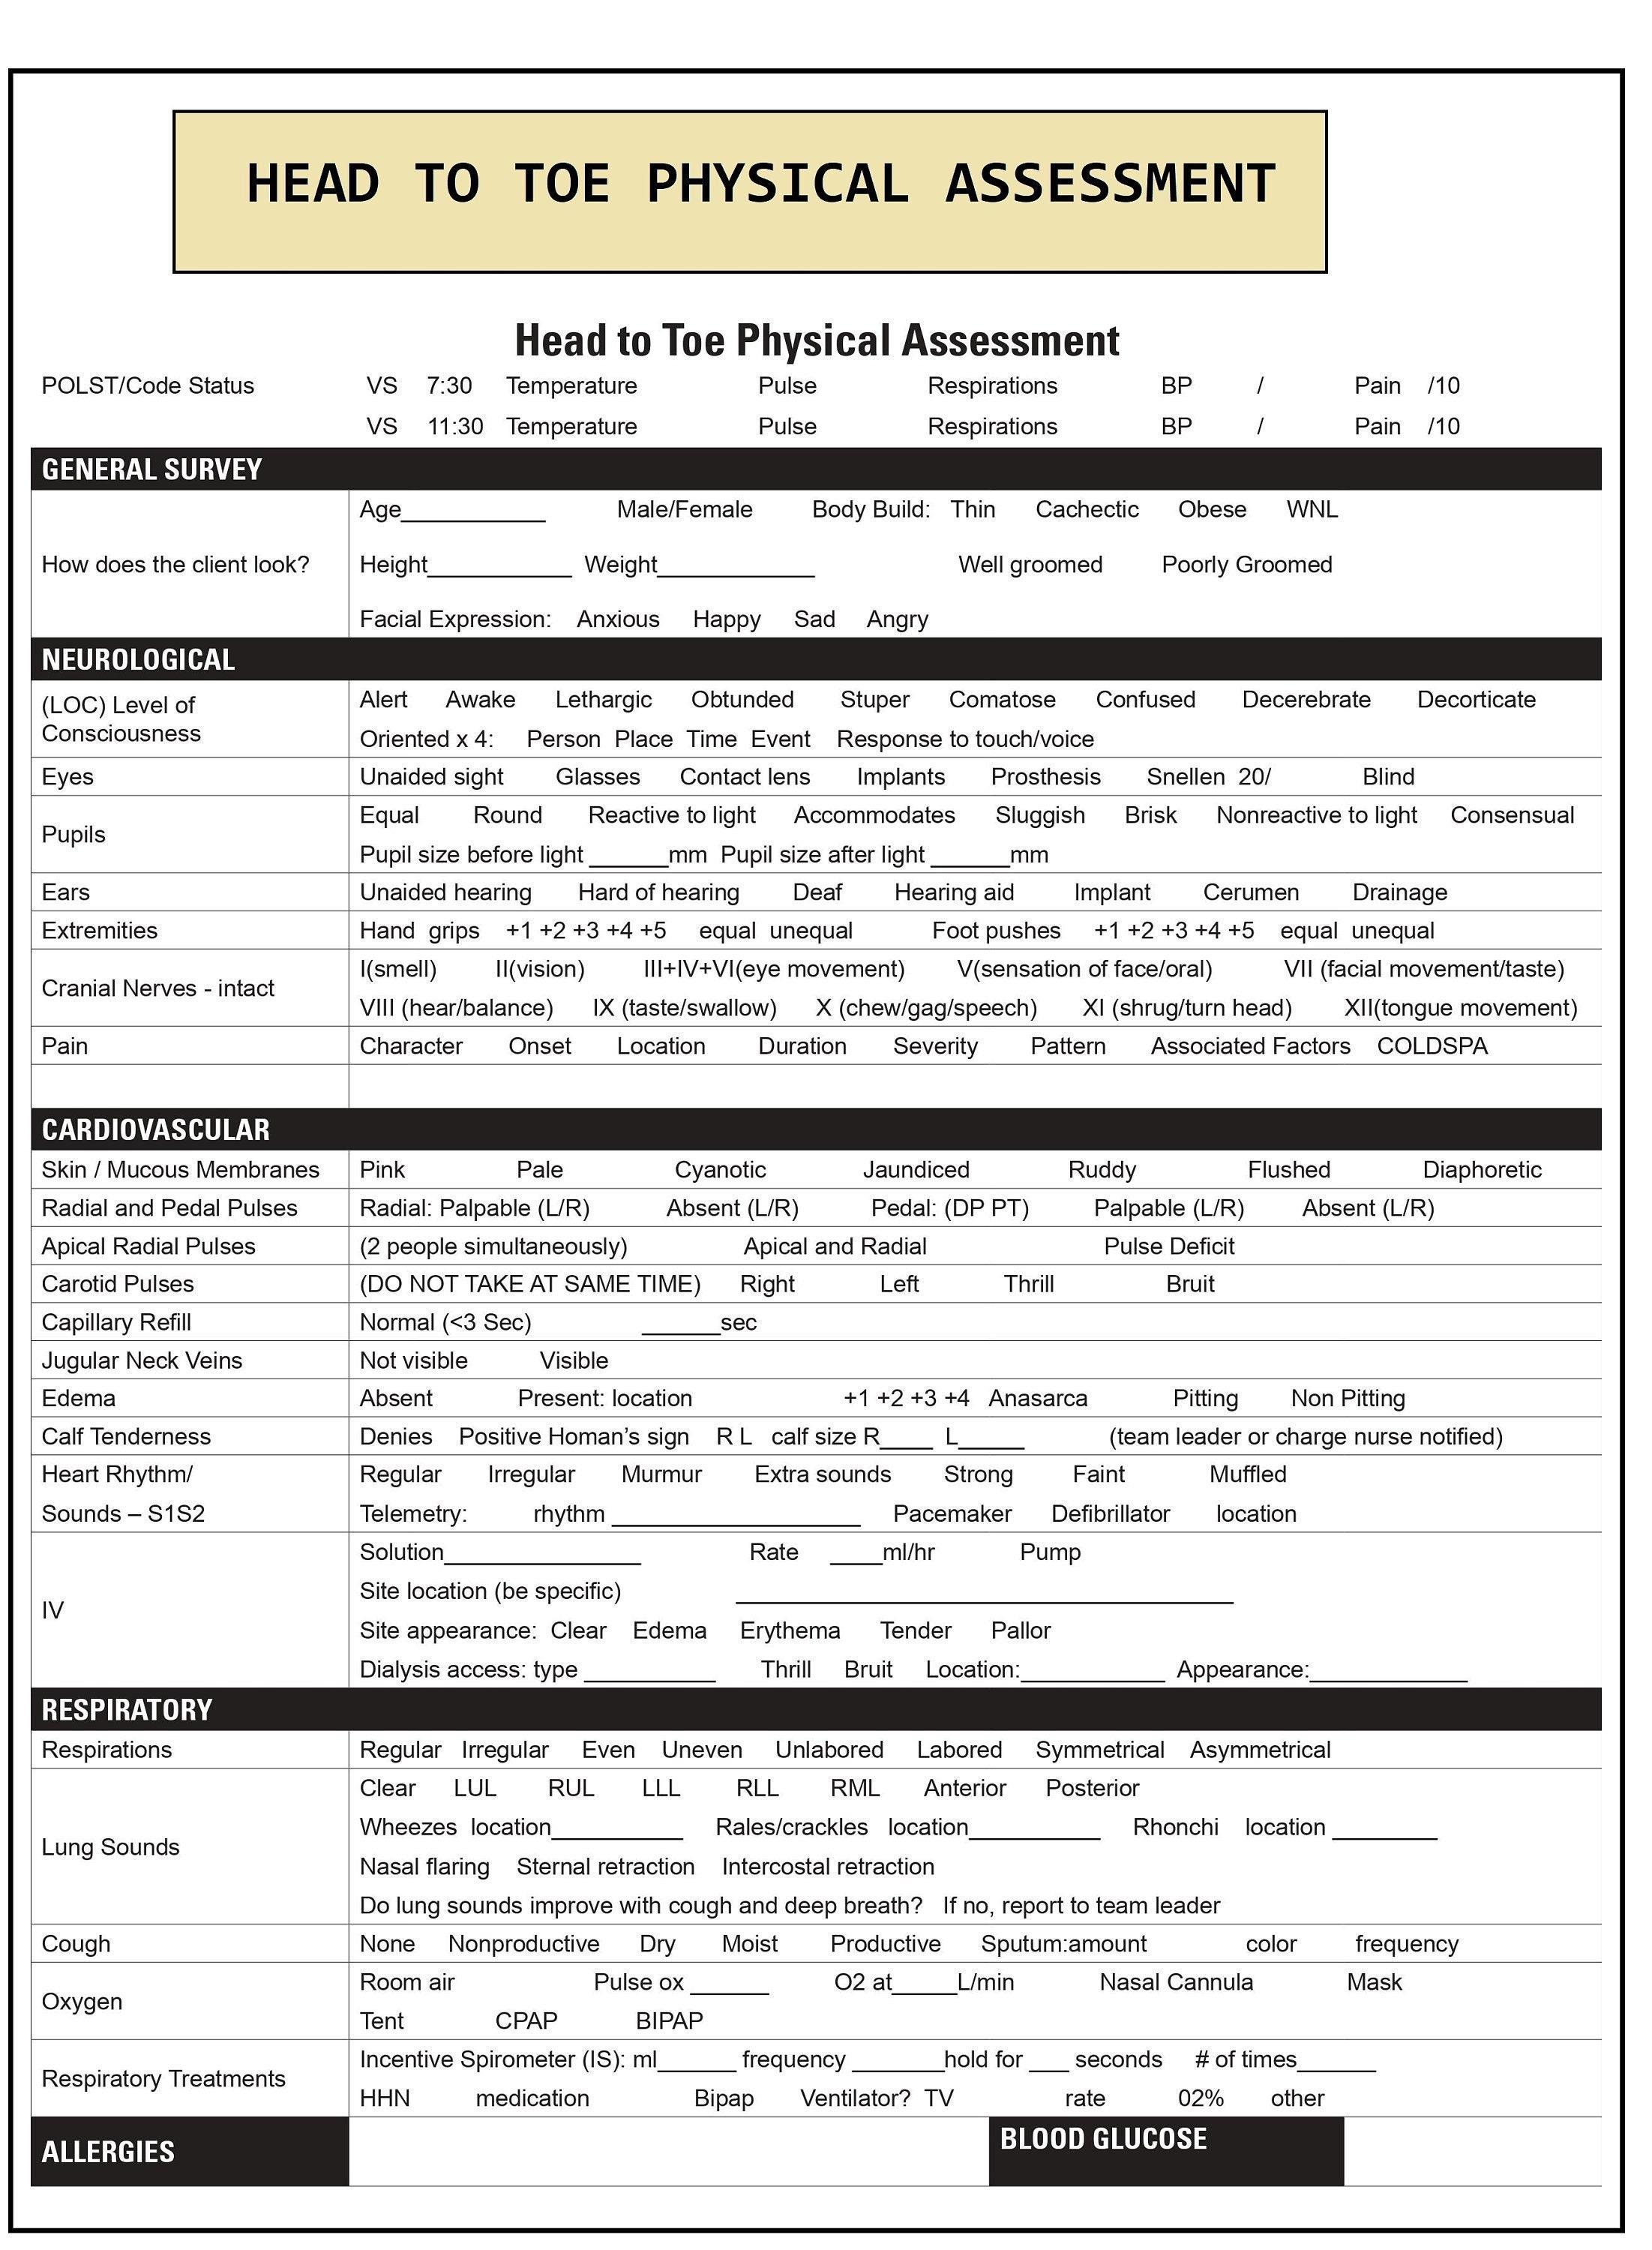
Chest and Lungs: Inspection, palpation, percussion, auscultation. Notate breath sounds by lobe and location. Right upper lobe anterior versus right lower lobe posterior are different findings even though they're both "lung sounds." If there are crackles, specify whether they're fine or coarse. If wheezes are present, document expiration versus inspiration predominance. Cardiac assessment needs S1 and S2 clarity, murmurs described by timing and radiation if present, and point of maximal impulse location. Regular rhythm or irregularly irregular — these terms mean something clinically. Use them correctly. Abdomen: This is where most documentation falls apart. Listen before you palpate. Always. Document bowel sounds by quadrant and duration — "present in all four quadrants" is meaningless without specifying how long you listened. Four seconds per quadrant is the minimum. Document bowel sound character: normoactive, hypoactive, hyperactive. Then move to palpation. Superficial versus deep. Tenderness location with a clock-face or anatomical landmark system. Liver edge, spleen tip, any masses. I prefer the anatomical landmark approach because clock-face descriptions confuse other providers who are thinking in terms of organ systems. A mass in the right upper quadrant near the costal margin tells you something different than "a mass at the two o'clock position." Extremities: Motor strength graded 0-5. Sensation to light touch and proprioception. Peripheral pulses documented as 0-4+ or palpable/diminished/absent. Edema graded in centimeters of pitting. Capillary refill time in seconds. I use the term "cap refill under 3 seconds" rather than "CRT normal" because normal varies by age and ambient temperature. A CRT of 3 seconds in a cold OR is different from 3 seconds on a warm med-surg floor.
Neurological: Level of consciousness using AVPU or GCS. Pupil checks again if you didn't do them in the head section. Motor strength in all four extremities. Sensation to pain and light touch in dermatomes if the patient is neuro-compromised. Deep tendon reflexes graded appropriately. Gait assessment if applicable. Balance testing if relevant to the reason for admission. Skin: Color, temperature, moisture, turgor, integrity. Pressure injury staging using the NPUAP classification. Any rashes described by morphology, distribution, and extent as a percentage of body surface area. I document wound measurements in centimeters with a diagram reference. Photographs help but they don't replace written documentation when the imaging system goes down at 2 AM. Psychosocial: This section is optional depending on your facility but highly recommended. Mood, affect, speech pattern, thought process. Screen for safety if indicated. Family support system. Health literacy assessment. These details shape the discharge plan more than any lab value.
Get the Full Details