How to Document Lung Sounds Nursing
Percussion comes before auscultation every single time. If you skip straight to the stethoscope, your documentation will be messy and your findings unreliable. Start with the patient sitting upright, expose the back fully, and have them take three slow, deep breaths before you even lift the diaphragm to their chest. I once had a respiratory therapist argue with me for twenty minutes about a chart entry because I documented "diminished" instead of "decreased." The medical records department flagged it as vague. The workaround was simple: I started using "absent," "decreased," "normal," "increased," and " adventitious" as my standardized vocabulary. It cut the clarification requests down to nearly zero. Your facility may have its own preferred terminology, so check the policy manual on day one. You do not want to redo work because you skipped reading it.
How To Document Lung Sounds Nursing: The System That Actually Works
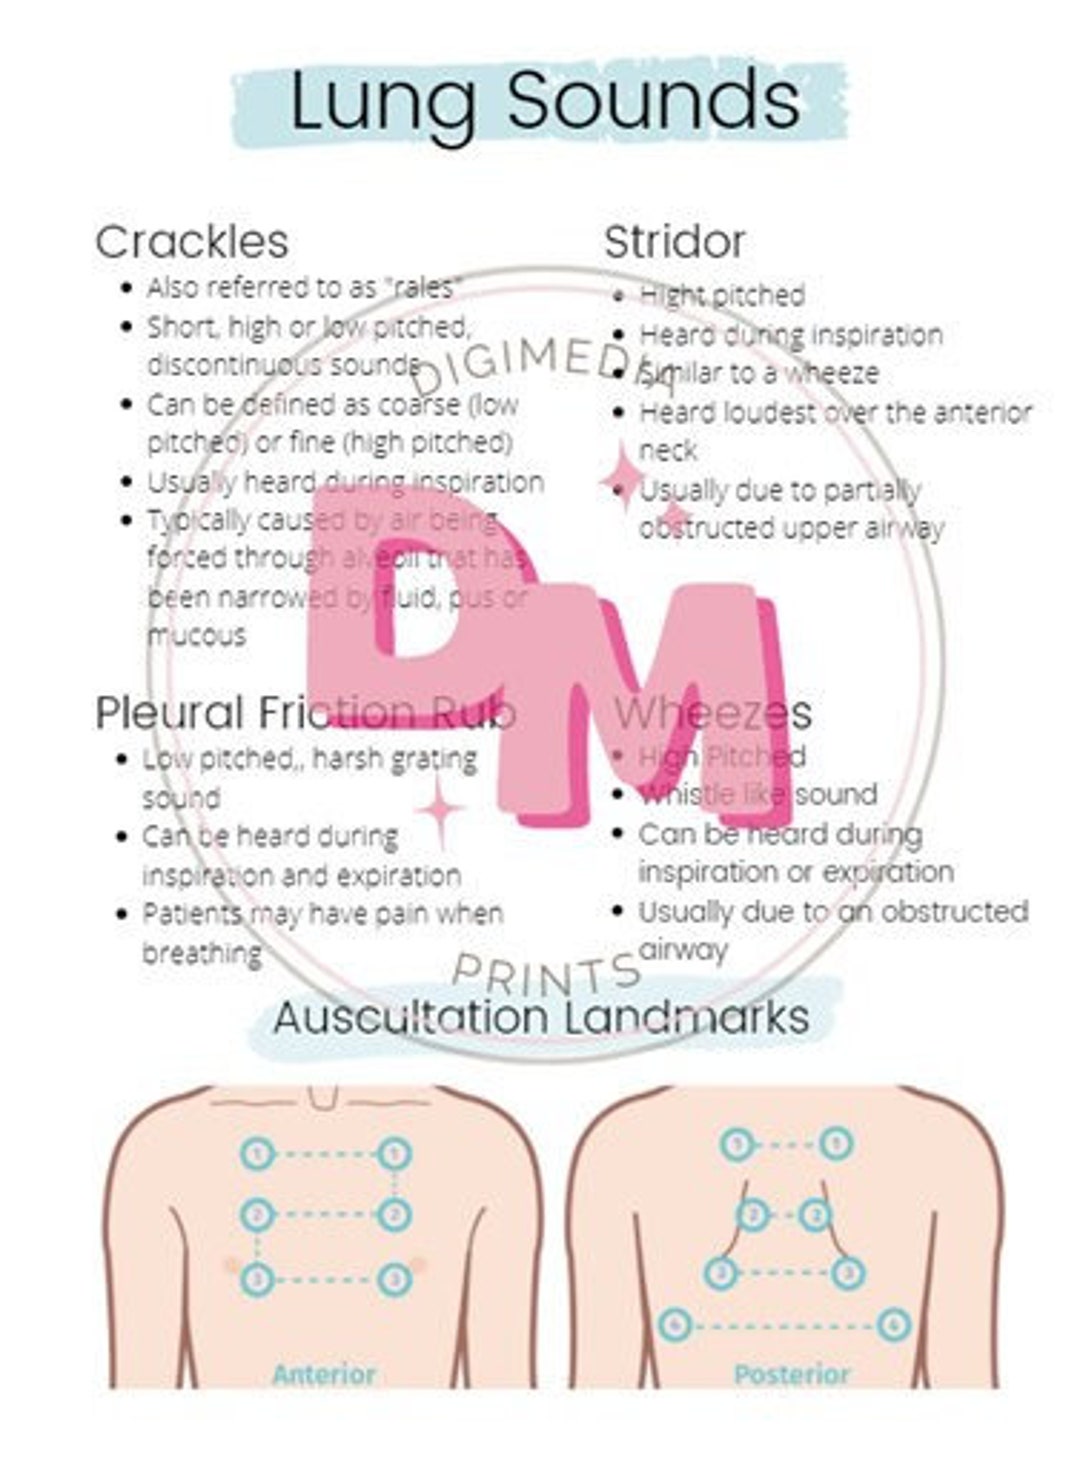
The standard approach is segmental documentation. You divide the posterior lung fields into the upper, middle, and lower lobes on both sides, plus the anterior fields around the clavicles and the lower chest. You listen at each designated point while the patient breathes deeply through an open mouth. Breathe in through the nose, breathe out through the mouth. Shallow breathing masks a lot of abnormal sounds, so you will miss things if you let the patient just pant normally. Documentation format that I use across every shift goes like this: location, quality, intensity, and any adventitious sounds. For example: "Clear to auscultation bilaterally in all fields. No wheezes, rales, or rhonchi noted. Respiratory rate 16, unlabored." If there is something abnormal, you specify exactly where. "Crackles noted at left base posterior field, fine, occurring at end-inspiration, unchanged with cough." That level of specificity is what protects you when the attending physician reads the chart and when a reviewer looks at it six months later. Here is a detail most new grad nurses miss: the scapulae need to be retracted laterally before you auscultate the upper lobes behind them. If you do not move the shoulder blades, you are listening through muscle and bone and calling it clear when it is not. I learned this the hard way on a medical-surgical floor when a patient with a small posterior infiltrate was documented as clear by three different nurses in a row because nobody bothered to properly position the arms. The attending found it on the chest x-ray two hours later during rounds.
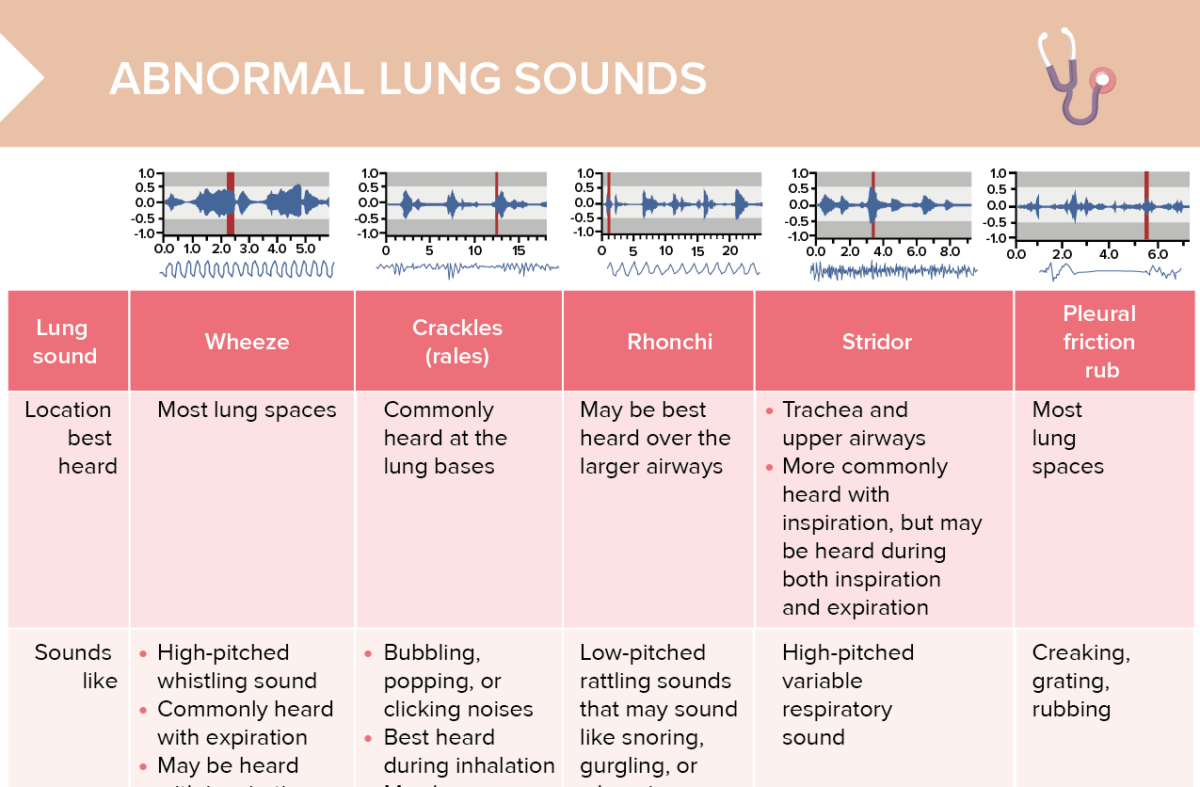
When documenting adventitious sounds, distinguish between crackles and wheezes with precision. Fine crackles are high-pitched, brief, and popping — they sound like hair rubbed between your fingers near your ear. Coarse crackles are lower, louder, and bubble-like. Do not just write "crackles present." Write the size, the timing within the respiratory cycle, and whether they clear with a cough. Pneumonia crackles do not clear with coughing. Atelectasis crackles sometimes do. That distinction changes the clinical picture entirely. Wheezes are continuous musical sounds, predominantly expiratory in asthma and COPD, but they can appear inspiratory in severe obstruction. Stridor is different — it is an upper airway sound, harsh and crowing, usually inspiratory, and it warrants immediate escalation. Document it as "stridor" specifically, not as a wheeze. Confusing the two in your notes has real consequences. I had a patient with epiglottitis once where the initial nursing assessment noted "wheezing" in the chart. By the time the team recognized it was actually stridor, the airway was compromised. Documentation language matters under pressure. Pleural friction rubs are another sound that gets miscopied regularly. They sound like two pieces of leather rubbing together and occur during both inspiration and expiration. They do not clear with coughing. If you suspect one, have the patient hold their breath briefly — the sound disappears when the lung is static because the pleural layers stop moving against each other. Document the finding along with the observation that it resolves with breath-holding, because that confirms it is a friction rub and not an unrelated adventitious sound.
Get the Full Details

Intensity of breath sounds is part of proper documentation too. Bronchial breath sounds heard over the peripheral lung fields indicate consolidation. Vesicular sounds over the base of the heart and near the axillae are normal. If you hear bronchial sounds in a place where vesicular should be, document it explicitly: "Bronchial breath sounds noted at right middle lobe anterior field, consistent with possible consolidation." Linking the finding to the likely pathology in your documentation gives the physician something actionable rather than just a raw observation. Vocal resonance testing is underutilized but worth including when you suspect consolidation. Have the patient say "ninety-nine" or "one, two, three" while you listen with the diaphram. Normal transmission is faint and muffled. Increased resonance — where the words come through clearly and sharply — is bronchophony and points to consolidated lung tissue. Egophony is when the patient says "e" and it sounds like "a" through the stethoscope. Weberness is when a whispered phrase is heard clearly and intensely. Each one maps to a different clinical state, and documenting which test you performed and what you heard adds significant value to the record. One practical bottleneck you will run into is time pressure. If you are short-staffed and trying to document lung sounds for twelve patients, you will be tempted to copy the previous shift's notes. Do not do this. Electronic health records flag copied content, and if a patient's condition deteriorates, the copied documentation becomes legal liability. A quick two-minute assessment per patient takes less time than defending a chart that shows no change over three days when the patient actually developed pneumonia on day two.
If your facility uses structured nursing flowsheets with checkbox options for lung sounds, learn the mapping between the checkboxes and the narrative documentation requirements. Some systems default to "clear lungs bilaterally" unless the nurse manually overrides it. A checkbox does not capture nuance. When findings are abnormal, switch to narrative documentation rather than relying on the dropdown menu. The checkbox system cannot handle "fine crackles at left base only, present since 0600, increased in intensity by 1000" the way a sentence can. Finally, include the patient's positioning and effort during the assessment. "Lung sounds assessed with patient in high-Fowler's position, breathing deeply and spontaneously" tells the reader that the assessment was performed under optimal conditions. If the patient was too weak to take a deep breath, document that too: "Able to complete only two deep breaths before fatiguing, breath sounds diminished at bases bilaterally, likely positional rather than pathological." You are recording the context, not just the sound. That context is what separates competent nursing documentation from a bare-bones checklist entry.