The Basics of Skin Turgor Assessment
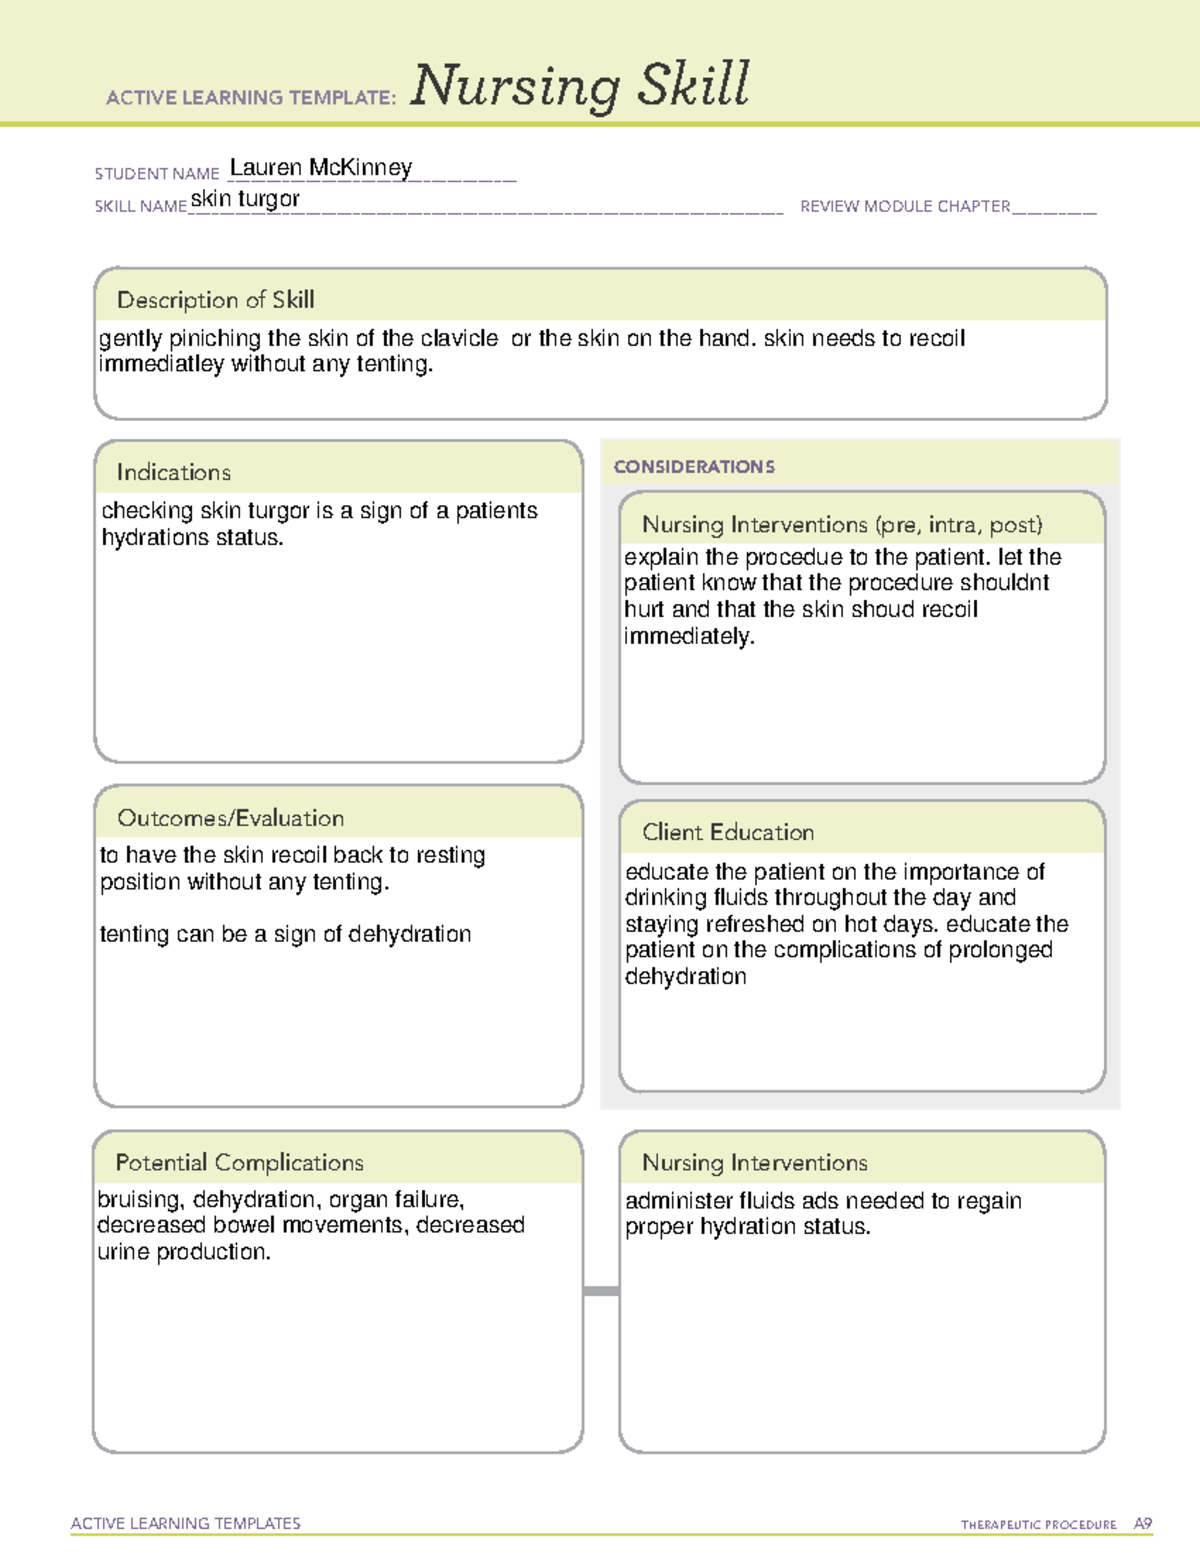
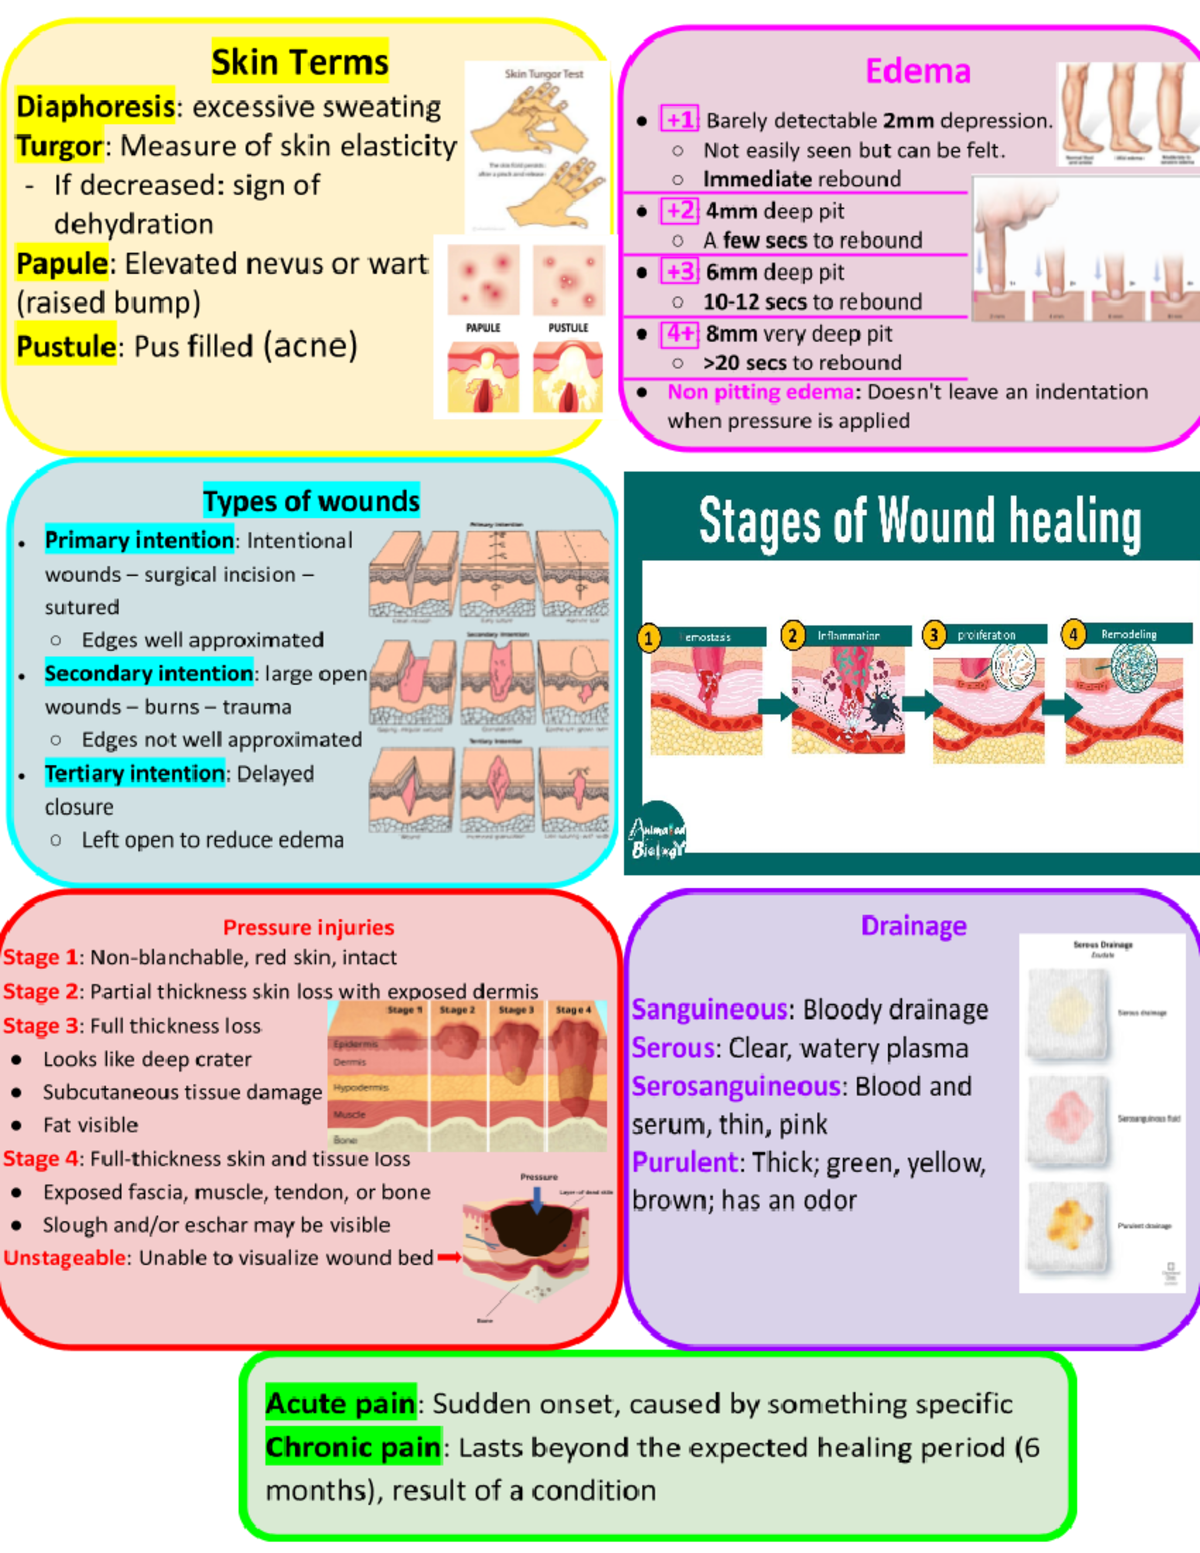
Skin turgor is the skin's ability to return to its normal position after being pinched or lifted. When you document it properly, you're recording whether a patient's hydration status is intact or compromised. The standard method involves gently pinching the skin on the patient's lower arm or chest, holding it for a couple seconds, and releasing it. If it snaps back quickly, that's normal turgor. If it remains tented or takes several seconds to return, that's decreased skin turgor. I've been doing this assessment in clinical settings for years, and honestly, the documentation part is where most people get sloppy. You need to be specific about timing, location, and the actual observed behavior. "Normal turgor" isn't enough. Write exactly what you saw and when.
How To Document Skin Turgor
Start with the location of assessment. Write down the anatomical site you tested. I usually go with the sternum area for elderly patients because the skin on their hands and arms can be thin and friable, which gives false readings. For younger patients, the subclavian area or volar forearm works fine. Document it like: "Skin turgor assessed at [location] - [result] - [duration of recoil if abnormal]." Here's the specific problem I ran into that changed how I document this. I had a patient whose skin turgor on the forearm looked decreased. I documented it as tenting with a 3-second return. Then I reassessed at the sternum and got normal results. The forearm finding was a red herring caused by age-related skin changes, not dehydration. Now I always note if I had to use an alternative site and why the primary site was unreliable. If the turgor is normal, document it as "skin turgor immediate recoil at [site]" and move on. If it's decreased, record the time it took for the skin to return to flat position. Two seconds or more is generally considered abnormal. Write the exact count. Don't approximate.
Pitfalls and Limitations to Watch For
Skin turgor testing has real limitations that you should factor into your documentation. It's not a reliable standalone indicator of hydration in several common scenarios. Elderly patients frequently show decreased skin turgor due to natural collagen loss and reduced elastin, not necessarily dehydration. Their skin just doesn't snap back the way it used to regardless of fluid status. If you document this without context, you might be recording a chronic finding as an acute one. Similarly, patients with severe edema or significant obesity make skin turgor assessment nearly impossible. The skin is too saturated or too thick to lift properly. In those cases, I document "skin turgor unassessable due to [edema/obesity]" and move on to other hydration markers. Don't force a reading just because you need something in the chart. Other indicators matter more in ambiguous cases. Check mucous membranes, capillary refill time, urine specific gravity, and vital signs like orthostatic blood pressure changes. If skin turgor is questionable but those other markers are normal, the turgor finding likely isn't clinically significant. Document the discrepancy rather than leaning hard on a single test that has known limitations.
Get the Full Details
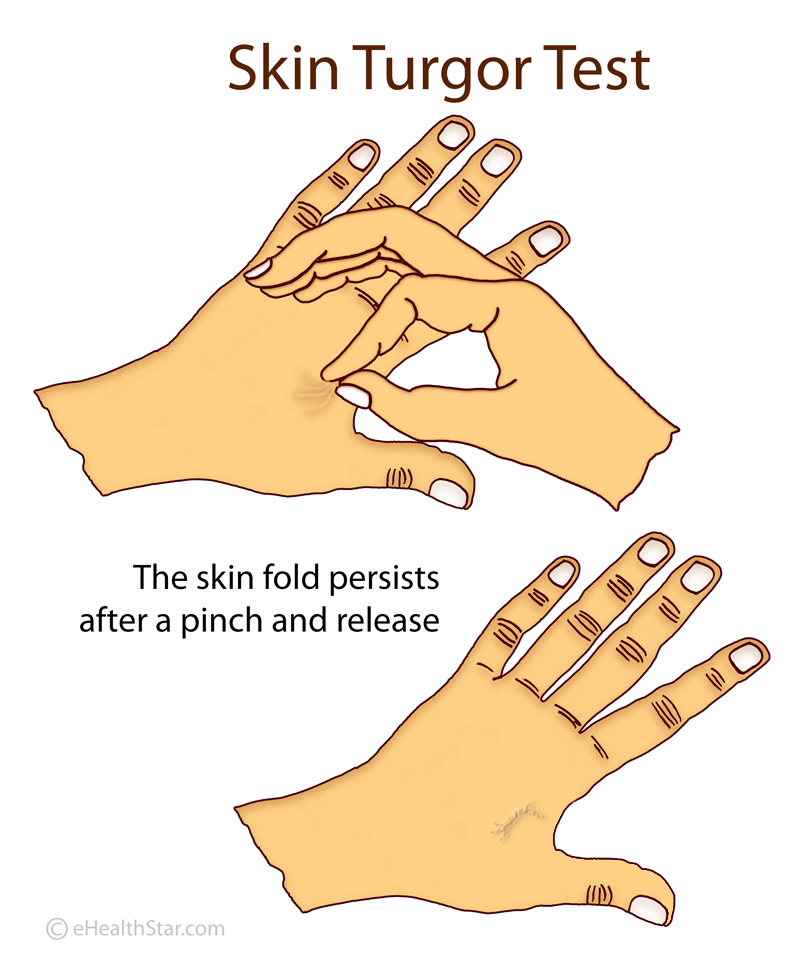
I typically spend about 30 seconds on a proper skin turgor assessment if done correctly. The documentation part takes another minute if you're writing it in real time rather than back-charting from memory, which is where most errors creep in.