Setting Up for the Procedure
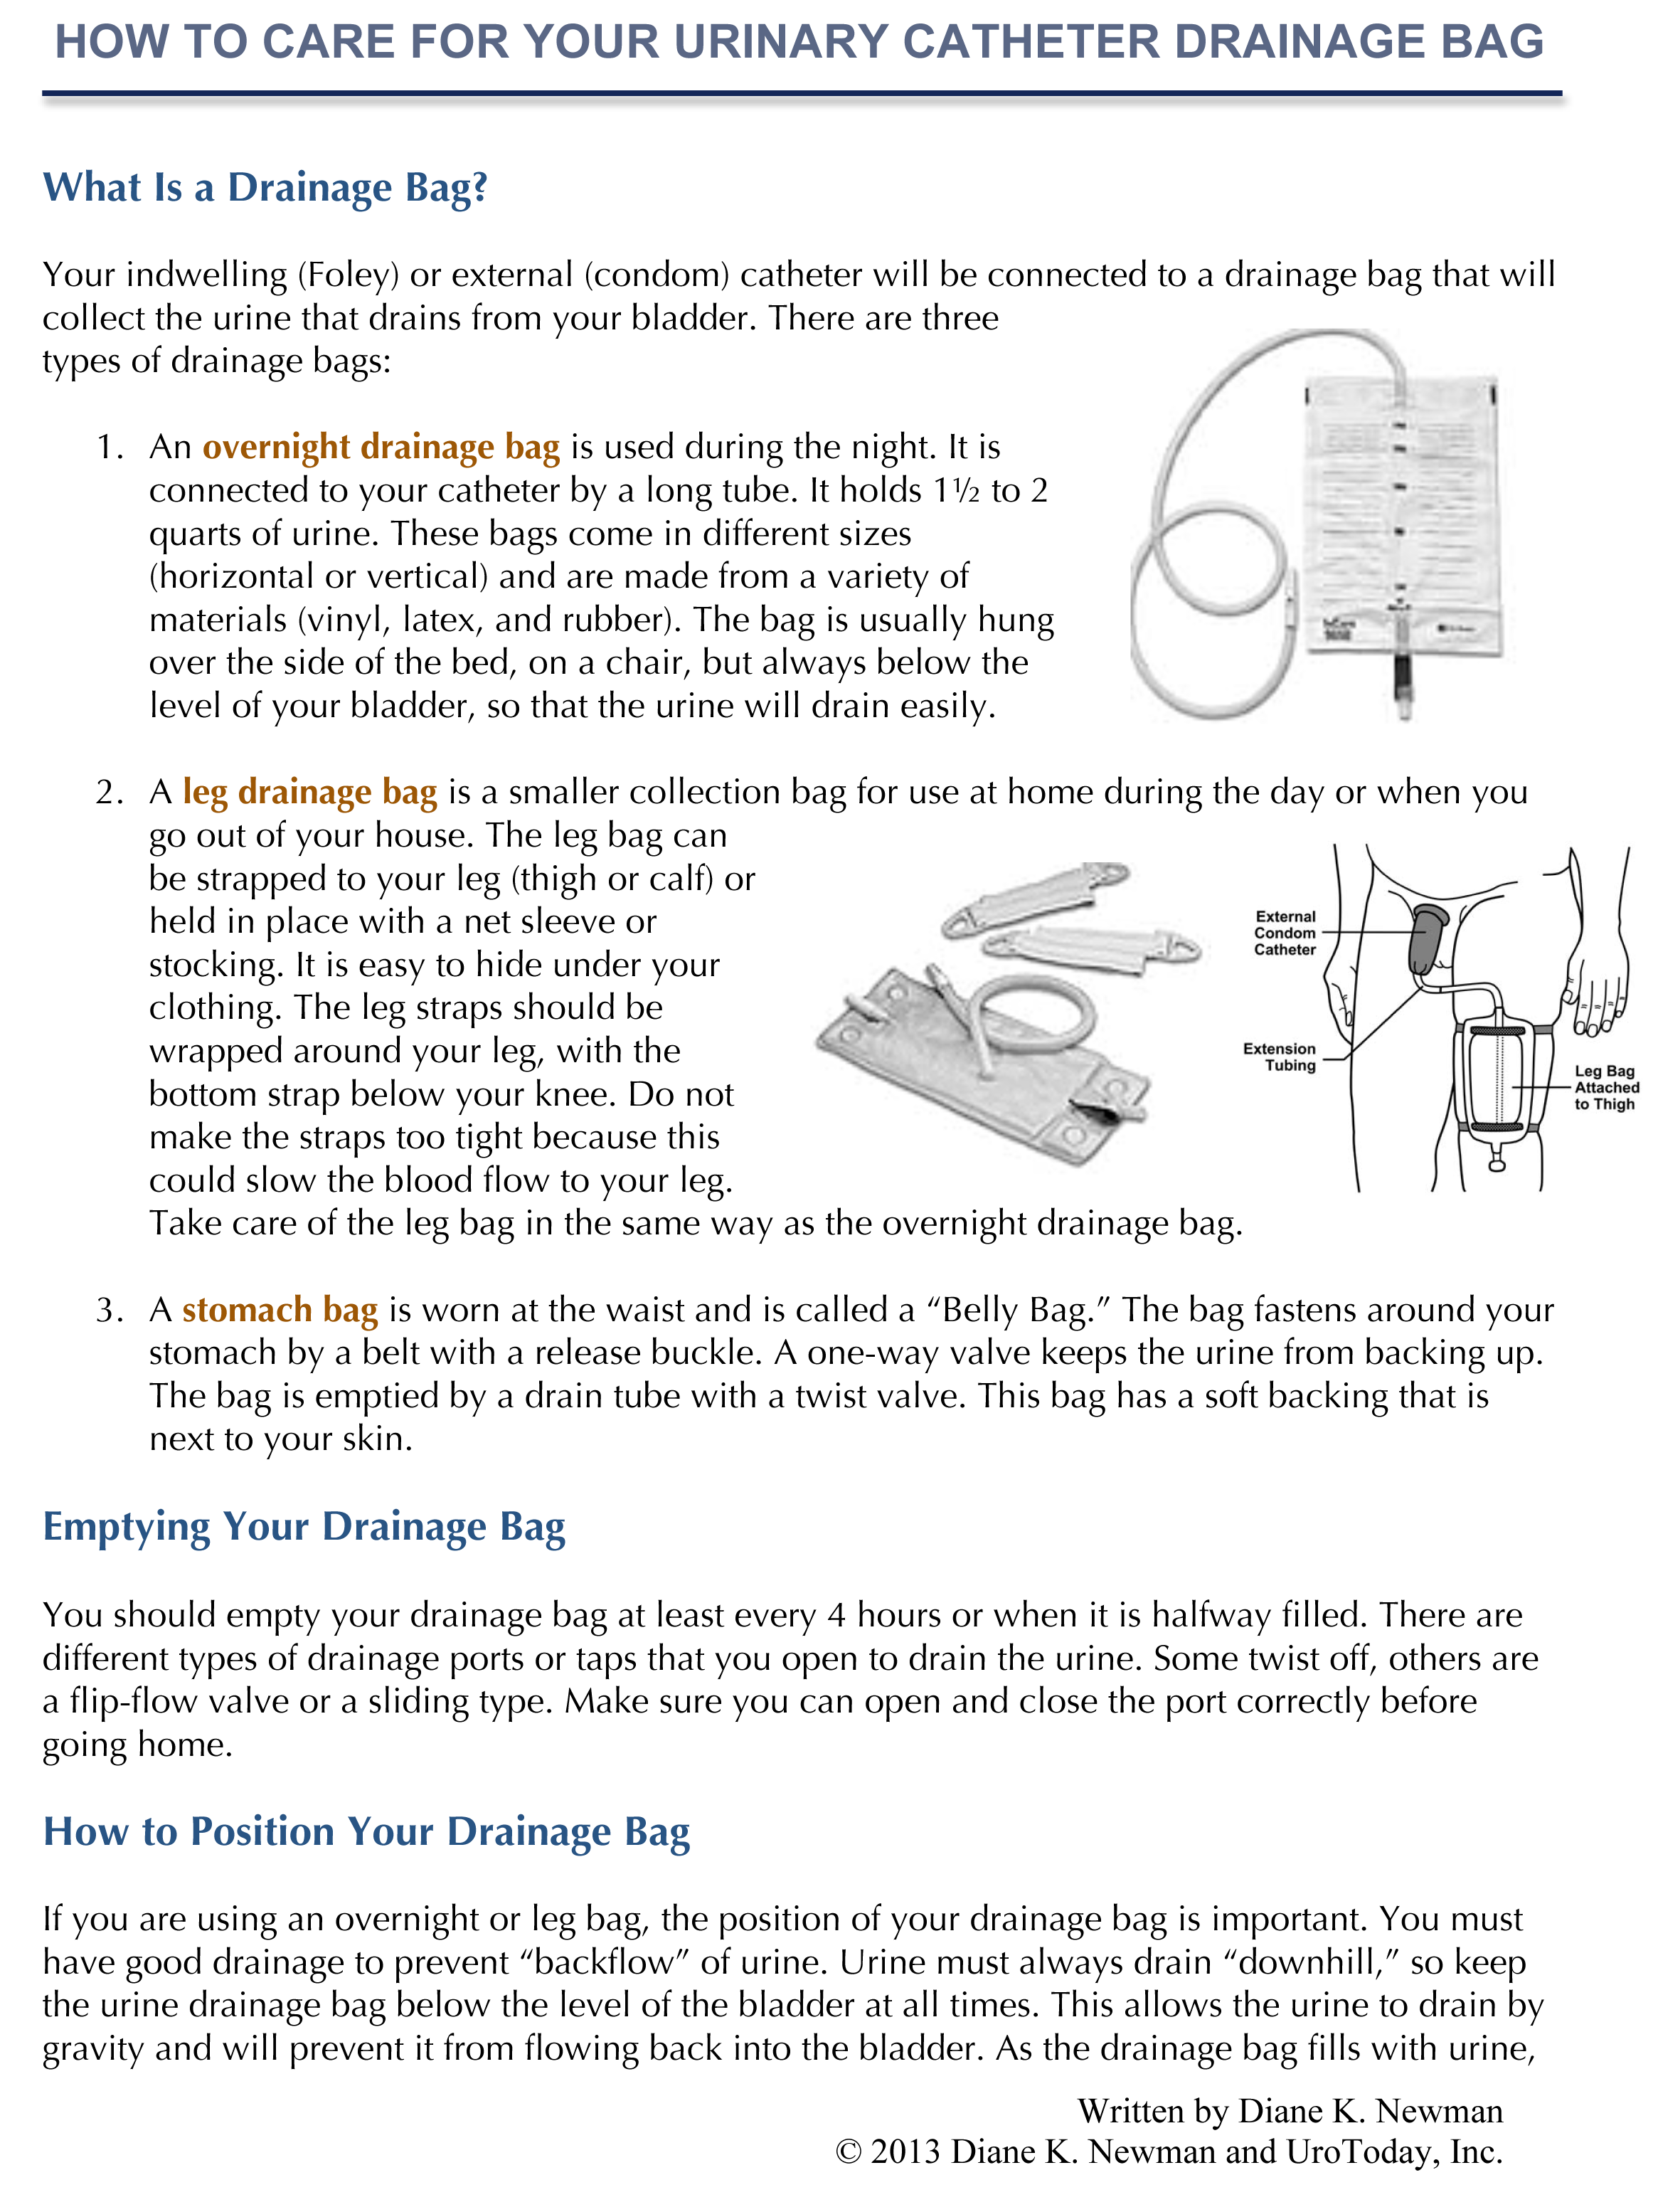
You need clean hands and a clean environment, but I won't tell you to wash them for twenty seconds like a textbook. Just wash them. The real issue most people get wrong is not planning where the bag empties to. You'd be surprised how many patients try to drain into a toilet that's half full or into a sink that's already cluttered with medications and personal items. Find a stable surface before you start, ideally something you can set the drainage container on without worrying about tipping it over. The catheter bag itself is usually connected to the patient via a tube that runs from the urethra. There's a spigot or valve near the bottom of the bag where the urine exits. That's your access point. Most bags use either a clamp-style valve or a twist-and-pull spigot. If you've never done this before, spend thirty seconds examining which type you're dealing with. They work differently, and forcing a clamp that's designed to twist will damage the connection.
How To Drain A Catheter Bag Step By Step
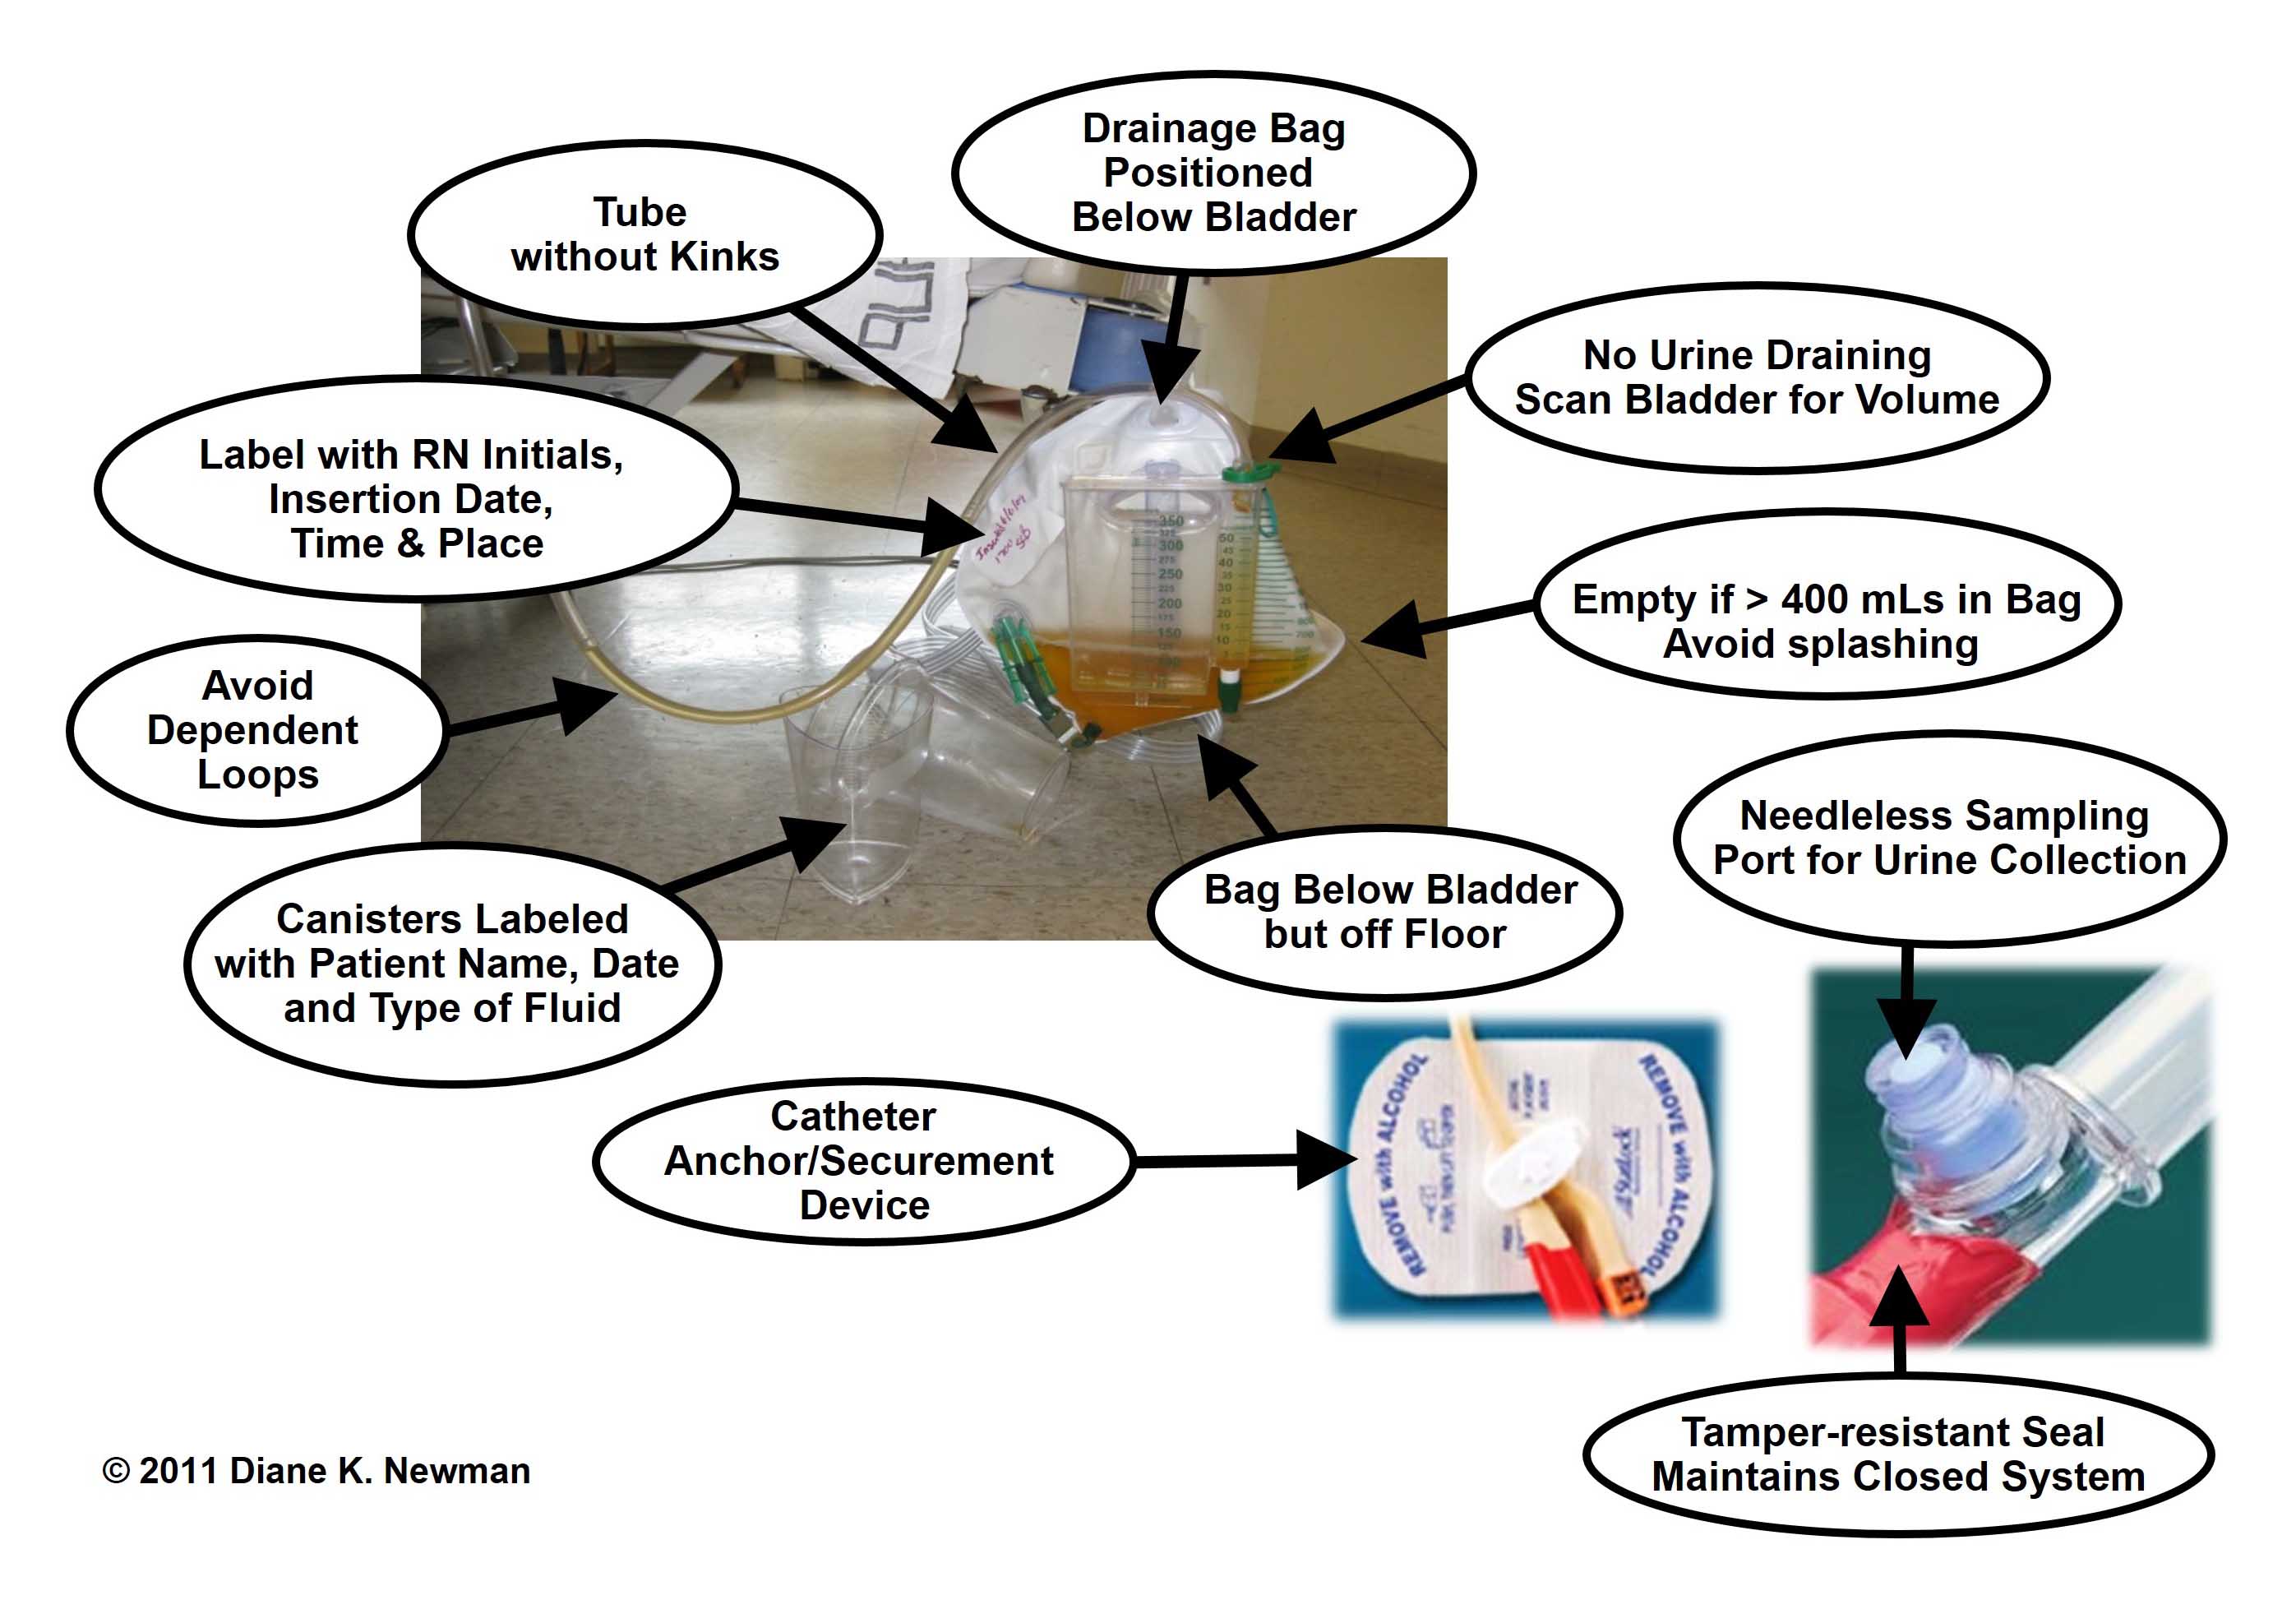
Position yourself so you can see the valve clearly. If the patient is in bed, pull the bag down to where you can access it, but keep the tubing attached and avoid pulling hard on the catheter itself. Yanking on the catheter causes real pain and can cause bleeding. I had a situation once where someone was draining a bag for a post-surgery patient and caught the tube on the bed rail, yanked it about two centimeters, and the patient ended up with significant hematuria that required a bladder irrigation for hours. Never rush this part. Place your drainage container directly under the valve. Then open the valve slowly. Don't just pop it wide open. You want a controlled flow, not a firehose effect that splashes around the container. Urine is typically pale yellow to amber in color. Cloudy urine isn't necessarily abnormal, but strong odor or visible particles should be noted. The color and consistency are useful information that should be recorded, especially if this is being done in a clinical setting. Once the bag is empty, close the valve before removing the container. I've seen bags that aren't fully closed, and the residual urine inside the bag can leak out during transport. It's a small detail that creates a mess and potentially spreads bacteria. After closing the valve, return the bag to its proper position. The tube should have a gentle curve with no kinks. Kinked tubing blocks flow and can cause backpressure on the bladder, which is uncomfortable and not ideal.
Dispose of the urine according to local protocols. In a home setting, pouring it down the toilet is standard. In a facility, there may be specific disposal containers. Don't mix up your settings. I once watched a trainee pour what they thought was drainage fluid into a regular waste bin because they hadn't confirmed the protocol. The infection control person was not happy about it.
Get the Full Details

Common Complications and What to Watch For
The biggest problem with catheter bags is blockage. Hair, sediment, or blood clots can obstruct the tubing. If the bag hasn't emptied in several hours and the patient isn't showing signs of bladder distension, check the tubing first. Run your fingers along the tube from the patient toward the bag to dislodge any obstructions. Don't clamp and release repeatedly as some people think that will flush the system. It doesn't. It just increases pressure uncomfortably. Biofilm buildup inside the bag itself is another issue that people overlook. Over time, a slimy film forms on the interior walls. This is normal and happens regardless of how well you maintain the system. The solution is replacing the bag on schedule. Most guidelines suggest changing the drainage bag every one to two weeks depending on usage, but the catheter itself may stay in place much longer. Don't confuse the two replacement schedules. If you encounter resistance when opening the valve, stop. Don't apply more force. The valve mechanism can be delicate, and stripping the threads or breaking the seal turns a simple drainage task into a full bag replacement emergency. I've replaced three or four bags in a single shift because someone forced a stuck valve. It's frustrating and wasteful.
When to Call for Help
Certain situations require professional intervention. If urine is leaking around the catheter site instead of through the tube, if the patient develops fever or chills after a draining session, or if you see bright red blood that doesn't clear within a few minutes, these are not routine findings. Document the time, color, volume, and any symptoms. This information is valuable for the clinician who will follow up. Another scenario where you should not attempt drainage alone is when the patient has a newly placed catheter, typically within the first twenty-four hours. The tract isn't fully established, and any manipulation carries higher risk of trauma. In those cases, the nursing staff or urology team should handle the initial drainage events. The catheter bag system is straightforward when everything is working normally. The problems arise from assumptions, rushing, or skipping the visual inspection step. Take twenty seconds to look at the tubing, the valve, and the fluid before you do anything else. Most complications become obvious in those twenty seconds if you're paying attention.