Locating the Apical Pulse in Clinical Practice
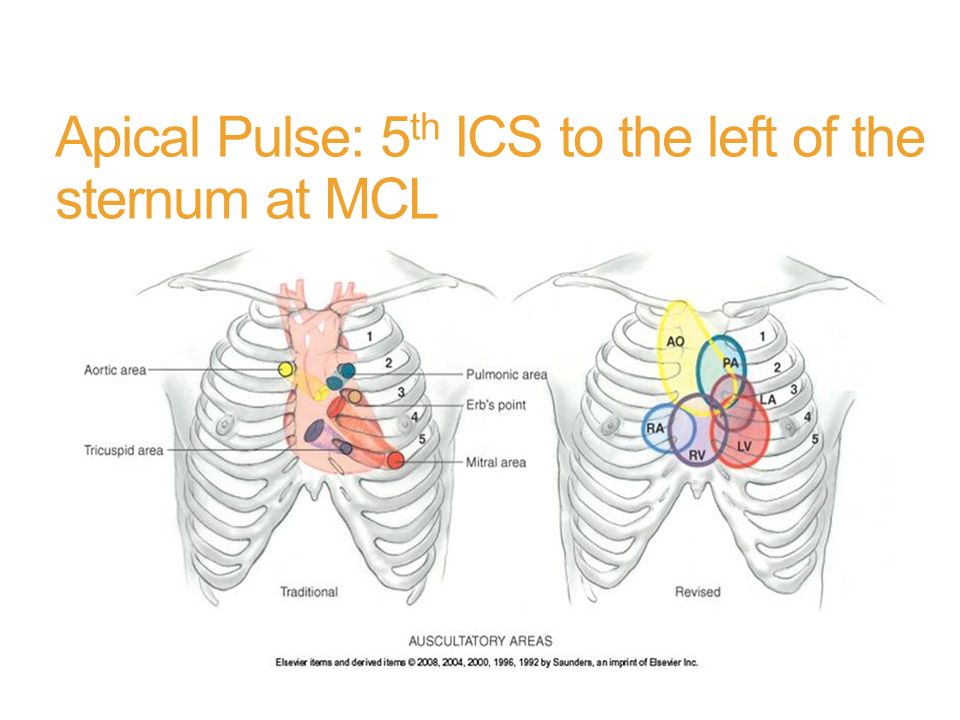
The apical pulse is the heartbeat you hear or feel at the point of maximal impulse on the chest. It sits around the fifth intercostal space at the midclavicular line on the left side. Most people miss it on the first try because they don't know exactly where to press or which tool to use. I still remember working night shift in a med-surg unit trying to get a baseline rate on a patient with a BMI of 42 and poor perfusion. The monitor was reading one thing, the radial pulse was barely there, and I needed an accurate count before giving digoxin. That's when I learned the hard way that the textbook location isn't always the same as the practical location. Start by positioning the patient supine with the upper body slightly elevated if they can tolerate it. Expose the chest adequately. Don't just glance at anatomy diagrams and plop your stethoscope wherever. Use your fingers to find the left nipple, trace up one intercostal space, and move inward toward the midclavicular line. That's the general area. Now press gently with the diaphragm of your stethoscope and listen.
Some patients, particularly those with COPD or cardiomegaly, have their PMI displaced laterally or inferiorly. I've seen it shift three centimeters out from the midclavicular line in severe left ventricular hypertrophy. If you're not finding anything at the standard location, move your stethoscope slowly in a two-centimeter radius until you hear the clearest S1 and S2. The loudest point isn't always the textbook point. Count for a full sixty seconds. Don't estimate. In atrial fibrillation especially, the irregularity becomes obvious only when you count long enough. I once caught a bigeminal rhythm that was completely hidden when I counted for fifteen seconds. The rate looked normal at a glance. It wasn't. The bell of the stethoscope picks up lower frequency sounds and can sometimes help you detect a S3 or S4 gallop while you're at it. That's extra information you're getting for free during an otherwise routine check. I use it whenever the heart sounds are soft or the patient has a thicker chest wall.
Document the rate, rhythm, and any abnormalities you hear. Note the patient's position, what you used, and the exact location where you found the best sound. Future clinicians will thank you. I've pulled charts where someone had written "apical pulse 78" with no location noted, and I spent ten minutes hunting because the patient's heart was clearly shifted from the typical position. If you cannot auscultate reliably due to loud environment, patient body habitus, or equipment limitations, consider having an ultrasound available. Bedside cardiac ultrasound can visualize the apex directly and give you a precise rate in seconds. It's not always an option in every setting, but when it is, it eliminates the guesswork entirely. I switched to that approach for my bariatric patients about five years ago and stopped struggling with questionable counts altogether. Common mistakes include counting for only thirty seconds and doubling it, pressing too hard with the stethoscope which occludes underlying vessels, and not accounting for patient position. A standing pulse will read slightly higher than a supine one in some people. Also, don't confuse the apical pulse with the precordial taps you can sometimes see on thin patients. That visual impulse is real but it's not a substitute for auscultation.
Get the Full Details
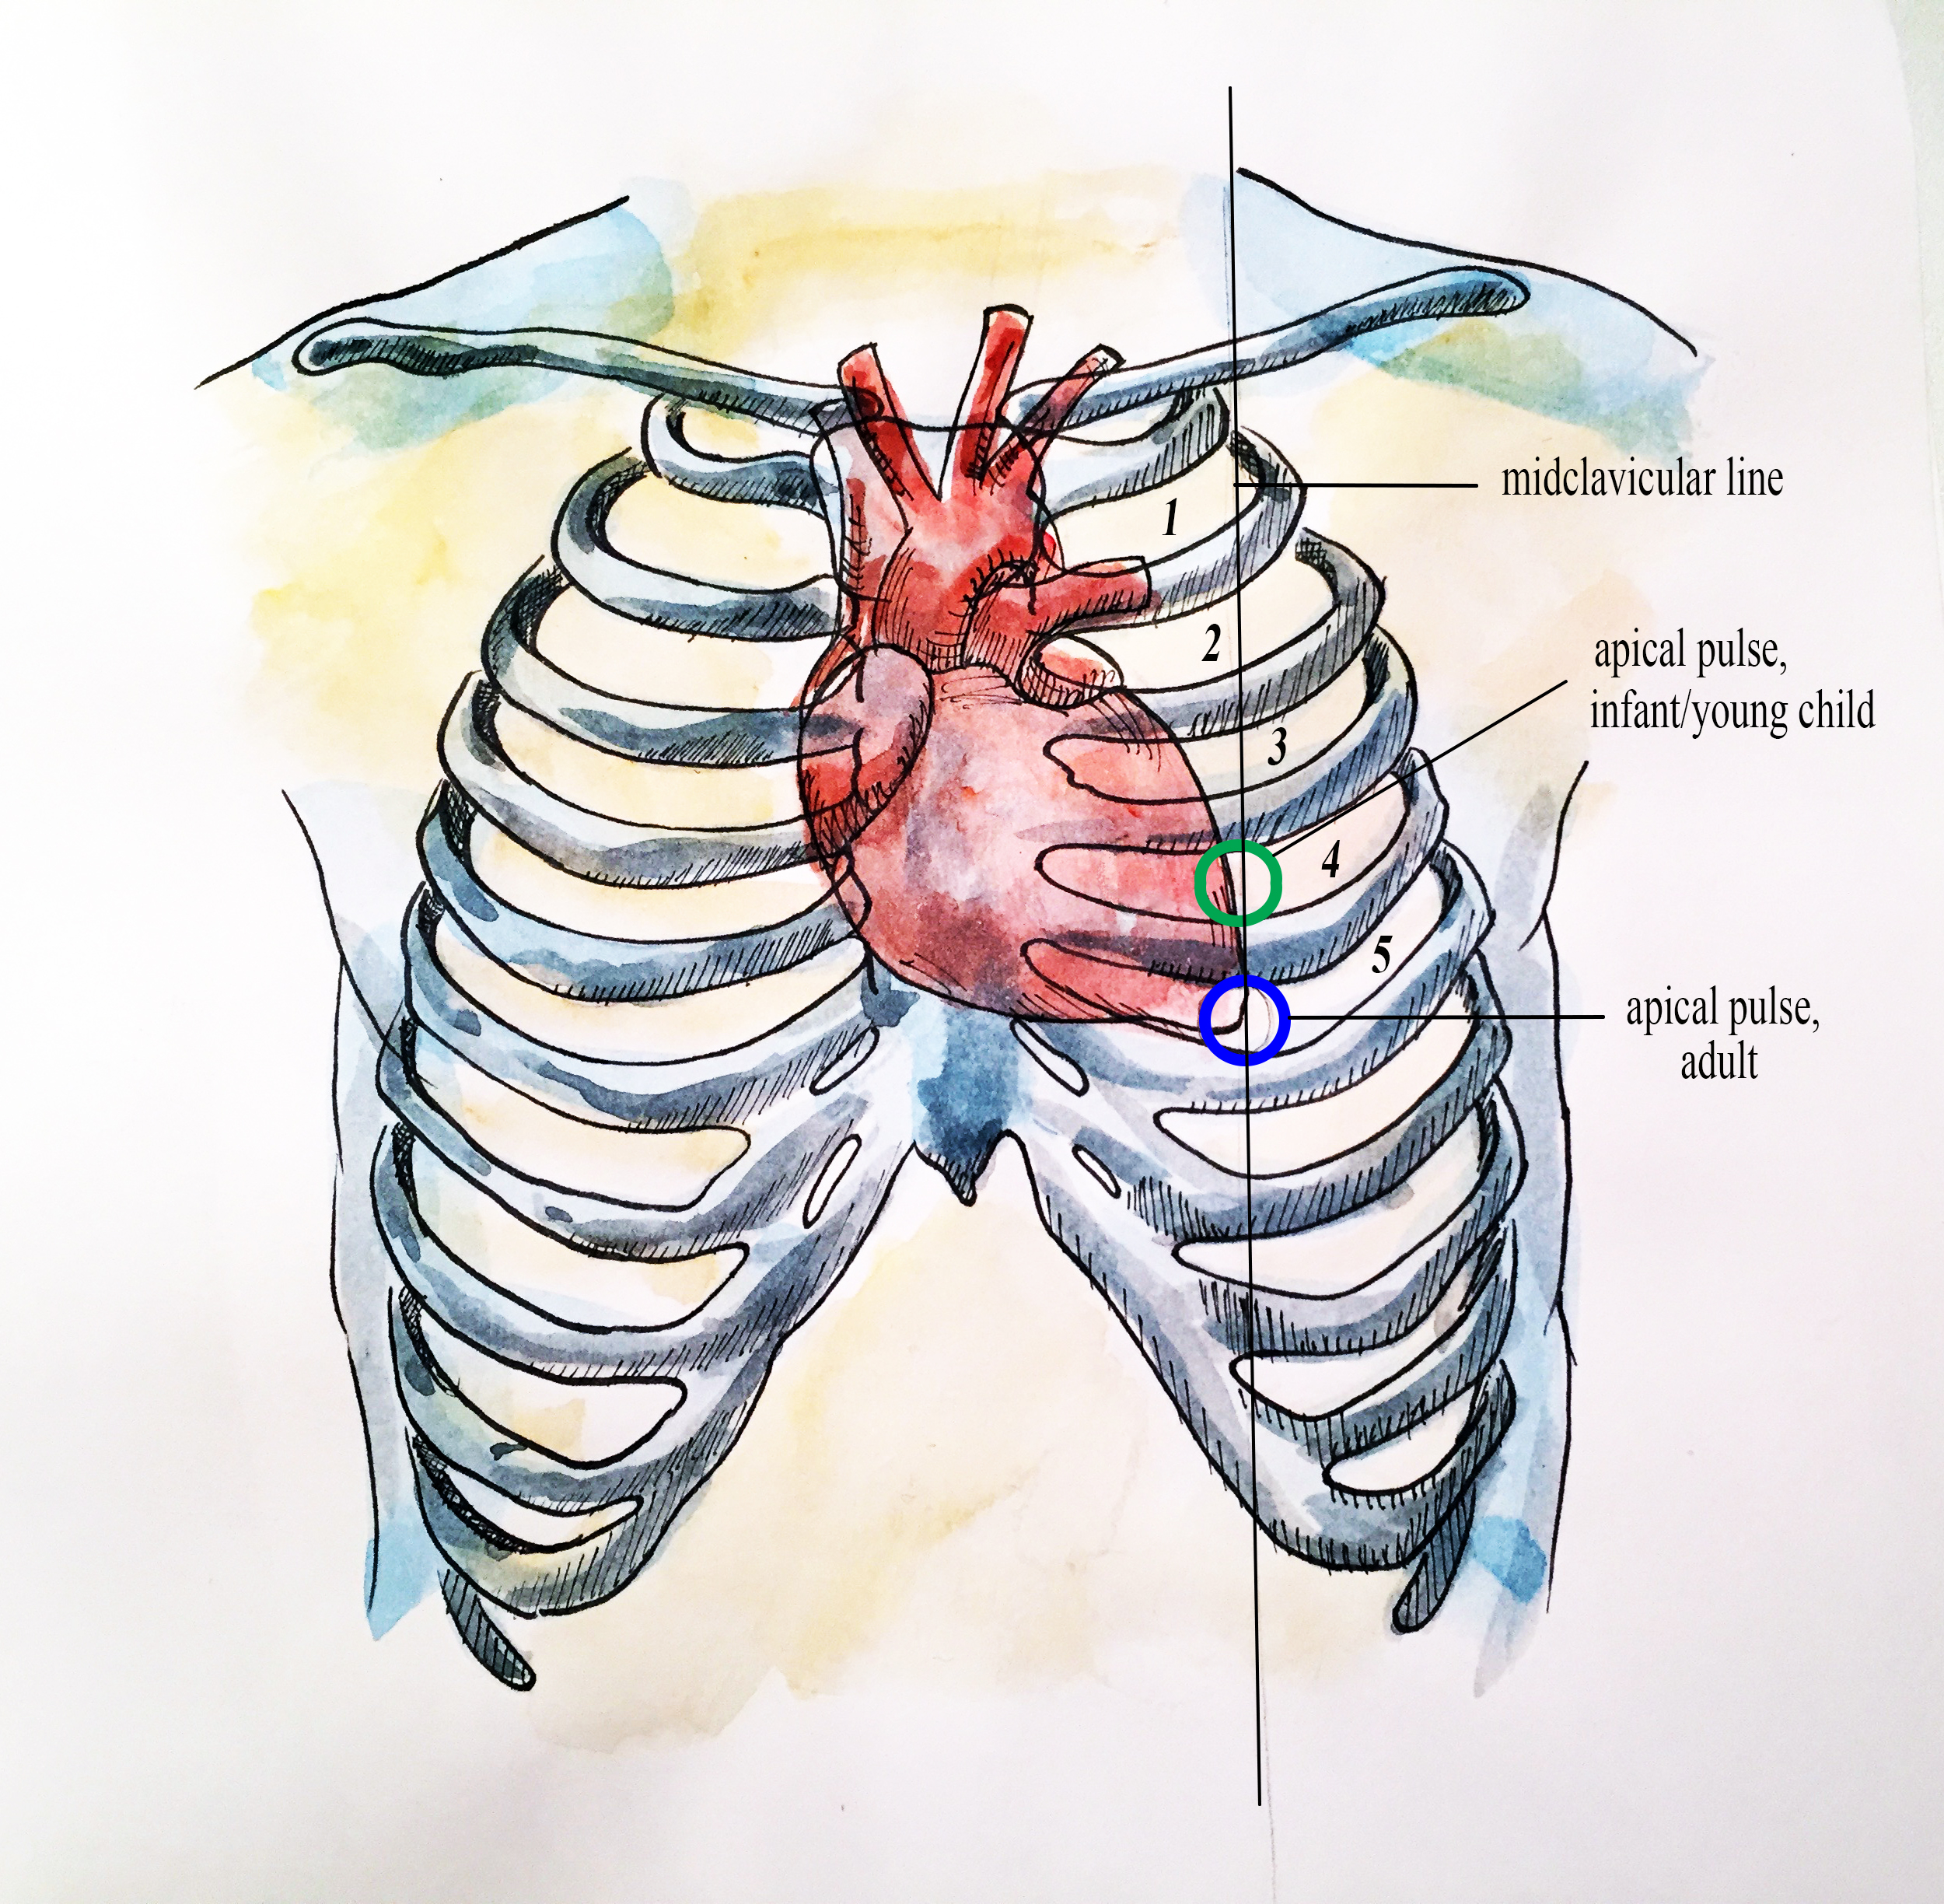
The apical pulse remains the gold standard for heart rate assessment in clinical settings. It takes practice to get good at finding it quickly and accurately. You'll find your rhythm within a few dozen attempts, and then it becomes second nature.