The Biology You Actually Need to Know
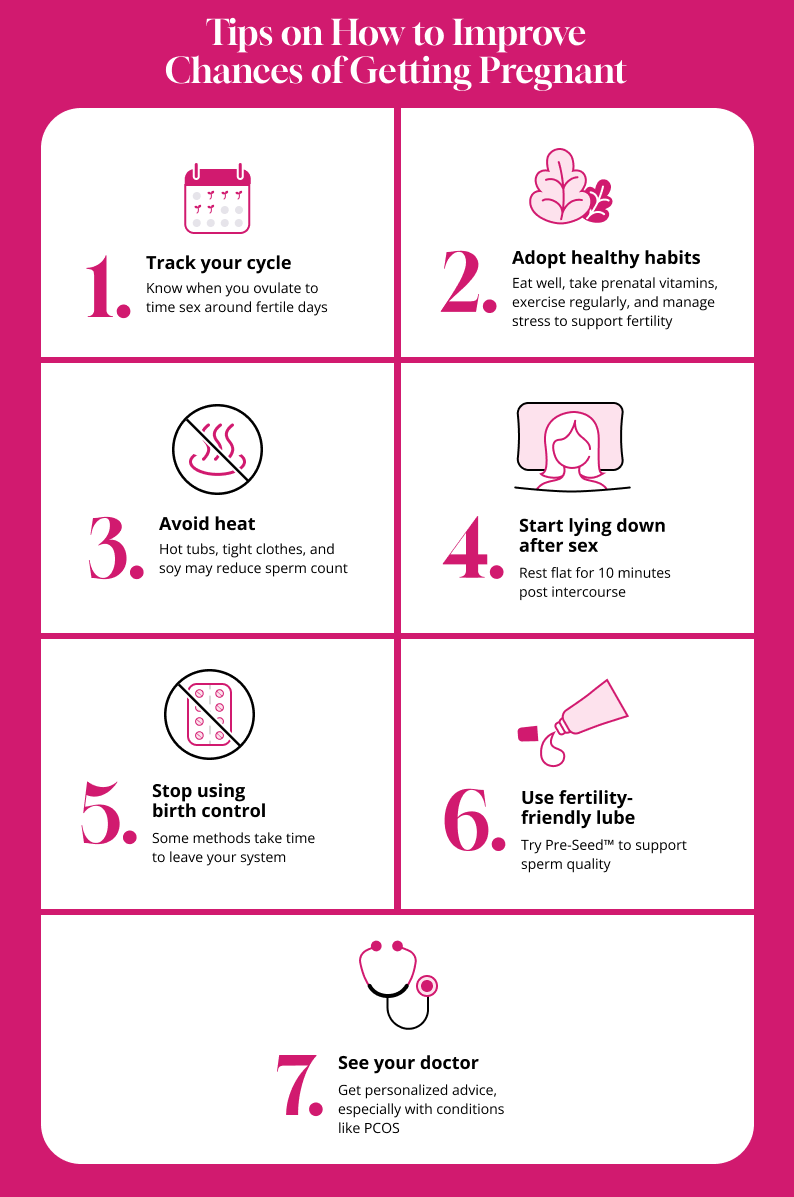
Pregnancy happens when sperm meets egg within a very narrow window. The egg lives for about 12 to 24 hours after ovulation. Sperm can survive inside the female reproductive tract for up to five days, sometimes longer depending on cervical mucus quality. That means the fertile window is roughly six days long — the five days before ovulation plus the day of ovulation itself. Most people land pregnant by timing sex during that window, but the details matter more than you'd think. The single most effective approach is tracking your cycle using a combination of methods. Ovulation predictor kits (OPDs) detect the luteinizing hormone (LH) surge that precedes ovulation by about 24 to 36 hours. Basal body temperature (BBT) charting confirms that ovulation actually occurred by showing the post-ovulatory temperature shift, which typically rises 0.5 to 1 degree Fahrenheit. Cervical mucus observation rounds out the picture — fertile-quality mucus at its peak resembles raw egg whites, stretching and clear, which helps sperm travel. When you cross-reference all three, you're not guessing where you are in your cycle, you're actually seeing it. I spent months relying on apps alone before realizing most cycle prediction apps are just guessing based on averages. One woman I worked with had a 35-day cycle on paper but was actually ovulating between day 18 and day 28 across different months. The app told her to start trying on day 21 and she kept coming up empty. Once she started tracking OPK results and BBT alongside the calendar, she caught her actual ovulation pattern and conceived three months later. The app wasn't wrong in a vacuum — it just couldn't account for her biological variability.
Timing and Frequency
Daily sex during the fertile window is fine for most couples, but every other day is often recommended because it maintains sperm count without causing depletion concerns. Sperm production takes roughly 72 hours to fully replenish, so daily ejaculation can slightly lower count per sample, though studies show daily intercourse still yields comparable pregnancy rates to every-other-day scheduling. If sperm parameters are already on the lower side, every other day becomes more important. A semen analysis is a cheap, high-value test most people skip unnecessarily. Here's something people get wrong: positioning, legs in the air, staying horizontal afterward — none of it matters clinically. There's zero evidence these help. Gravity isn't a factor. Sperm reach the cervix within minutes regardless. What matters is timing and sperm health on both sides.
Common Mistakes That Slow You Down
Most couples under 35 who have been trying for less than a year haven't actually done everything right yet. They've had sex a few times around what they thought was ovulation but didn't confirm it. They used lubricants that kill sperm — many commercial brands, including some popular ones like Astroglide and KY Jelly, have spermicidal properties. If you need lubrication, use something labeled fertility-friendly like Pre-Seed or Conceive Plus, which are pH-balanced and isotonic with semen. Stress doesn't directly prevent ovulation in most cases, but the anxiety of tracking can make sex feel like a chore, which reduces frequency and enjoyment. Don't turn intimacy into a spreadsheet exercise. Use the data as a guide, not a master. Have sex when you want to have sex, and use the fertile window as a boost rather than a mandate.
Get the Full Details

When to Seek Help
If you're under 35 and haven't conceived after 12 months of well-timed intercourse, see a reproductive endocrinologist. If you're 35 or older, seek evaluation after six months. If your cycles are irregular — meaning they vary by more than seven days in length — go sooner. Irregular cycles often signal ovulatory dysfunction, commonly from conditions like PCOS or thyroid disorders. A basic workup includes Semen analysis for the male partner, blood work checking progesterone (to confirm ovulation), TSH and prolactin levels, and an HSG to check if the fallopian tubes are open. I've seen too many people go years without getting that first round of tests because they assumed they needed to "try harder" before medical help was appropriate. Time is the variable you can't get back. The earlier you identify a problem, the simpler the intervention usually is. Simple ovulation induction with letrozole can resolve issues that otherwise take years to sort out. Tubal blockages are another common finding that only shows up on imaging — you won't know until you look.