The Reality of Insurance-Covered PT Visits
Most physical therapy clinics operate on a thin margin where every authorized visit count matters. Insurance companies set limits based on what they consider medically necessary, and those numbers aren't always generous. Understanding how the system actually works gives you leverage that most clinics walk into blind. The process starts with documentation that crosses a specific threshold. Insurance reviewers don't deny claims because they want to be difficult. They deny them because the paperwork doesn't meet their medical necessity criteria. The difference between a claim that sails through and one that gets pushed back usually comes down to a few specific data points in your notes. I need to be straightforward about something here. There is no magic code or loophole that guarantees unlimited visits. Insurance plans have contractually defined visit caps, and those caps are enforced. What you can influence is whether the patient qualifies for a re-certification or an increase in authorized visits. That distinction matters.
The Documentation Threshold
Every major payer—Blue Cross, Medicare, United, Cigna—has their own medical necessity criteria for physical therapy. Medicare uses Local Coverage Determinations, while commercial payers often rely on InterQual or Milliman guidelines. You don't need to memorize all of them, but you do need to know which framework your payer operates under. When a claim comes back denied for lack of medical necessity, the first thing you check is whether the documentation aligns with the correct criteria set. Here is what most clinics get wrong. They document the treatment they provided instead of documenting why the treatment is still medically necessary. These are two different things. A note that says "patient received 30 minutes of therapeutic exercise and manual therapy" is a treatment log. A note that says "patient has not met functional goals and requires continued intervention to achieve X" is a medical necessity argument. Insurance reviewers look for the latter. Specifically, your documentation needs to address ongoing progress or lack thereof, any barriers to discharge, and measurable outcomes at each stage of treatment. Without measurable outcomes, you have no basis for requesting additional visits. Numbers matter. Range of motion measurements, disability index scores, functional independence measure scores—these are the things that carry weight in a reconsideration request.
Re-Certification and Continuation of Care Requests
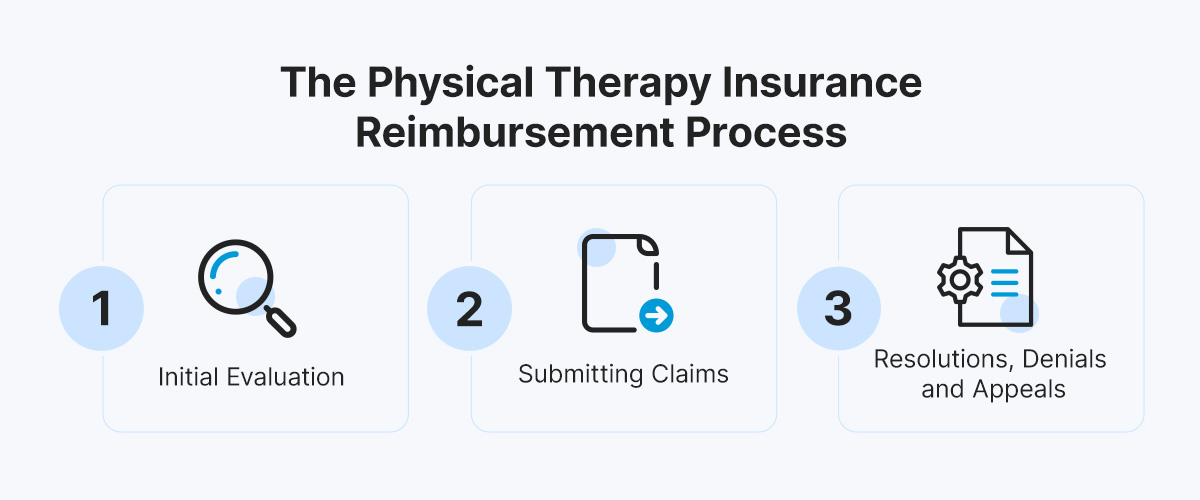
When a patient reaches their authorized visit maximum and still has unmet goals, you submit a re-certification request or a continuation of care request, depending on the payer. This is where the actual work happens. The request needs to justify why the original plan was insufficient and what the extended plan looks like. I ran into a specific situation a few years ago with a Medicare patient who had hit their annual PT visit cap and was clearly making progress but hadn't reached discharge readiness. The initial re-certification was denied. What I learned from that denial is that Medicare Administrative Contractors evaluate whether the remaining goals are realistic within the requested extension. My first request had asked for twenty additional visits when the patient realistically needed eight. The contractor flagged the discrepancy and denied it outright. My workaround was to break the request into two phases. First, I submitted a request for ten visits focused on the immediate remaining goals, with clear benchmarks for re-evaluation at visit five. The second phase outlined what would happen at that re-evaluation point. This got approved. The key insight is that payers respond better to scoped, conditional requests than they do to open-ended asks for more visits. It shows you are tracking outcomes, not just collecting sessions.
Get the Full Details

Common Pitfalls That Kill Approvals
There are patterns I see repeatedly that lead to denials or delays. The first is vague goal statements. "Improve mobility" is not a measurable goal. "Achieve independent stair negotiation with minimal assist" is measurable. The second is inconsistent functional status reporting. If the initial evaluation shows a patient who cannot stand from a chair without assistance and the note three weeks later shows they can do it independently, the reviewer will question why additional visits are still needed. Either the patient improved faster than expected or the documentation didn't capture the current status accurately. A third pitfall is failing to include the prescribing provider's supporting documentation. Some payers require the referring physician or nurse practitioner to sign off on continued treatment. If your clinic handles this internally and the physician isn't aware the authorization is expiring, you lose time waiting for a signature that never comes. Set up a standing process where referral providers are notified thirty days before any authorization expires.
The Peer-to-Peer Option
When a re-certification request is denied and the written appeal process feels like it is going nowhere, a peer-to-peer review is available with most commercial plans and Medicare. This is a phone conversation between your reviewing clinician and the payer's medical director or reviewing physician. It is not a casual chat. You need to go in prepared with the specific denial reason, your clinical justification, and the relevant outcome measures. The peer-to-peer route works best when the denial is based on a misinterpretation of the clinical picture rather than a hard policy limit. I have seen denials reversed in fifteen minutes when the reviewing physician clarified that the payer had only seen partial documentation and was missing context about comorbidities affecting recovery. But if the denial is because the patient genuinely has no unmet goals, a peer-to-peer will not change the outcome. Be honest about which category you are in before you invest the time.
Advanced Considerations
Some payers differentiate between acute and chronic conditions in their visit allowances. A rotator cuff repair might have a different authorization framework than chronic low back pain. Understanding these distinctions helps you frame your requests appropriately. Acute post-surgical cases typically receive more generous initial authorizations, and extending those is somewhat straightforward if progress is documented. Chronic conditions face stricter scrutiny from the start, which means your initial documentation needs to be even more rigorous. Another nuance that is worth noting involves concurrent care. If a patient is receiving occupational therapy or speech therapy alongside physical therapy, some payers allow those to run on separate authorization tracks. This is not universal, but it is worth checking with the specific plan. A patient might already have remaining OT visits that could address overlapping functional goals, which could free up PT authorization for more specialized interventions. Finally, there is a practical limitation to keep in mind. No amount of documentation will overcome a payer contract that has a hard annual cap with no re-certification pathway. Some employer-sponsored plans, particularly self-funded ones, operate this way. In those cases, the only option is to appeal through the employer's benefits administrator or explore alternative payment arrangements. Pushing documentation harder against a hard contractual limit is wasted effort. Know the difference between a denial you can fight and a denial you cannot before you invest hours into a strategy that has no path to success.

The effective clinics in this space treat insurance authorization the same way they treat clinical care—with intentionality and documentation standards that match the requirements. It is tedious, it is repetitive, and it rarely gets recognition from providers who would rather be seeing patients. But the revenue impact of getting visit counts right is real, and the skill in navigating it is something you develop through repeated exposure to the actual decision-making patterns of the payers you work with.