Understanding the Reality of Chronic Psoriasis Management
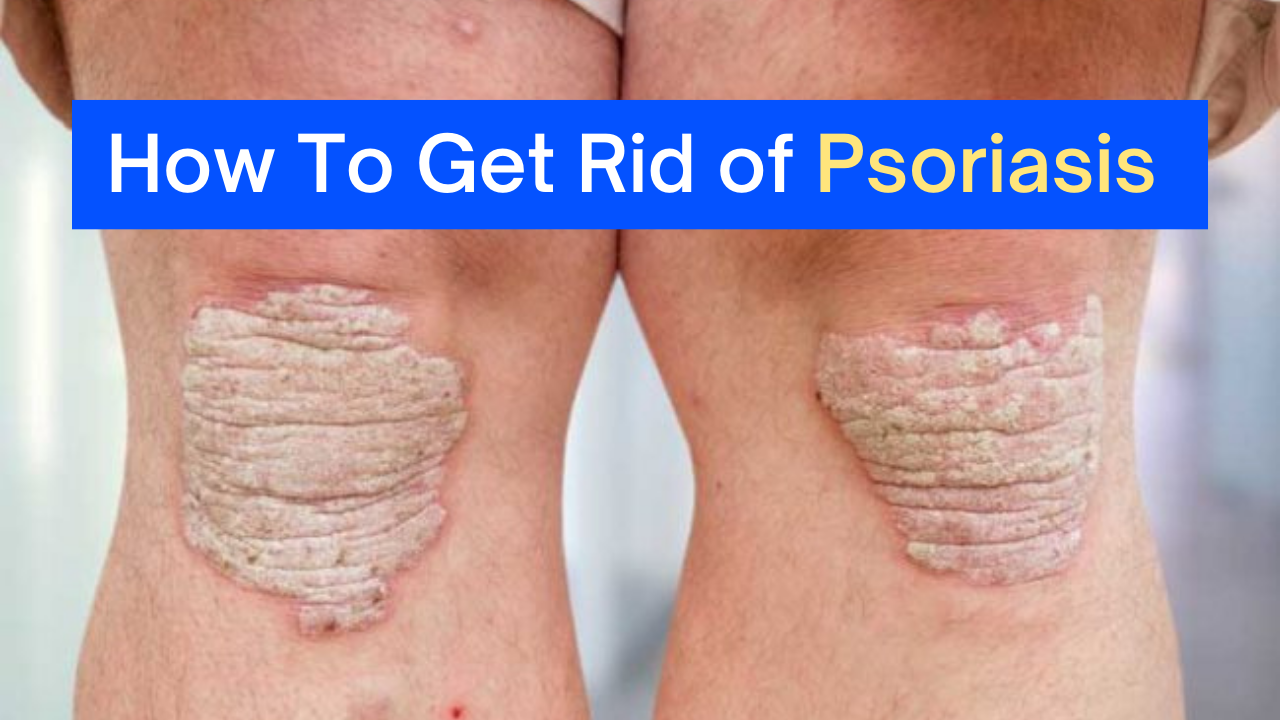
Psoriasis is an autoimmune condition where the immune system incorrectly attacks healthy skin cells, causing them to multiply far faster than they should. Normal skin cell turnover takes about 28 days. In psoriasis, that process compresses down to three to four days. The result is thick, scaly plaques that can appear anywhere on the body. Most commonly, you see them on the elbows, knees, scalp, and lower back. But they show up on hands, fingernails, and sometimes the entire body in more severe cases. The disease follows a unpredictable pattern. Flare-ups come and go, often triggered by stress, infections like strep throat, cold weather, or certain medications. I've seen patients who manage perfectly for months, then get hit hard after a routine dental procedure because the inflammation spiked systemically. That's just how it works. There is no universal trigger list that applies to everyone.
How To Get Rid Of Psoriasis
Before we go further, I need to be direct about something most websites won't tell you clearly. You cannot permanently get rid of psoriasis. It is a chronic, lifelong autoimmune disease. Anything claiming otherwise is selling you something. What you CAN do is achieve remission, where symptoms disappear entirely for extended periods, and manage flares when they return. The goal is quality of life, not elimination. The treatment ladder starts with topicals. For mild cases, over-the-counter corticosteroid creams and ointments work well enough. Things like hydrocortisone 1% or triamcinolone 0.1% prescribed by a doctor. The key point most people miss is application technique. You apply a thin layer, not a thick coat. Rubbing it in until it absorbs matters more than quantity. I had a patient once who was applying triple the recommended amount because he thought more medication meant faster results. His skin actually thinned from overuse, making the psoriasis worse in those spots. We cut his application down to a pea-sized amount for each palm-sized area and the improvement was visible within two weeks. When topicals aren't enough, you move to phototherapy. Narrowband UVB light therapy is the standard approach. Patients typically go to a clinic two to three times per week for several months. It's not glamorous but the response rates are solid, around 70 to 80 percent of patients seeing significant clearing. The catch is maintenance. Once you clear up, you usually need ongoing sessions once a week or every other week to stay clear. Stop the sessions and the psoriasis tends to return within months.
For moderate to severe cases, systemic treatments become necessary. Traditional oral medications like methotrexate, cyclosporine, or acitretin work but carry significant side effect profiles. Methotrexate requires regular blood work to monitor liver function. Cyclosporine can raise blood pressure and affect kidney function over time. These drugs aren't first-line for a reason, but they save people when nothing else works and psoriasis is covering large percentages of their body surface area. The biologics changed everything for severe patients. These are injected or infused medications that target specific parts of the immune system.adalimumab (Humira), adalimumab (Humira), ustekinumab (Stelara), secukinumab (Cosentyx), and guselkumab (Tremfya) are just a few options. Response rates are high, often 70 to 90 percent of patients seeing major clearing. But the cost is brutal without good insurance. Even with coverage, prior authorizations can take weeks. I watched a patient wait six weeks for approval while her psoriasis spread across her chest and arms. The workaround was asking her dermatologist for a bridge prescription or a patient assistance program application from the manufacturer simultaneously. Another thing nobody emphasizes enough is the gut-skin connection. Some patients find that dietary changes meaningfully reduce flares. Cutting alcohol helps many people. Some respond to eliminating gluten or reducing sugar intake. This isn't universal but it's worth tracking. I kept a patient on a simple food and flare diary for three months. She identified that dairy was a consistent trigger for her. She eliminated it and her next two flare-ups were dramatically milder than previous episodes. That single change saved her from stepping up to biologics at that time.
Get the Full Details
Stress management is practically a treatment modality at this point. The link between psychological stress and immune dysregulation in psoriasis is well documented. I don't say this to sound preachy. I say it because I've seen patients where the most effective intervention wasn't a drug but a sustained reduction in work stress. Whether that means therapy, meditation, changing jobs, or whatever actually works for you, addressing stress isn't optional if you want long-term control. Nail psoriasis is its own special frustration. It affects about half of people with plaque psoriasis and doesn't always correlate with skin severity. Thickening, pitting, and separation of the nail from the bed are common. Topicals rarely penetrate well enough to help nail psoriasis. Systemic treatments or injections into the nail fold are usually required. This is another area where patience matters. Nails grow slowly. Even effective treatment takes four to six months to show visible improvement in fingernails and longer for toenails. Psoriatic arthritis develops in roughly 30 percent of psoriasis patients. Joint pain, stiffness, and swelling are the warning signs. If you notice any of these, see a rheumatologist immediately. Early intervention prevents permanent joint damage. Delaying treatment by even a few months can result in irreversible changes visible on X-ray. This isn't scare tactics, it's clinical reality.
The emotional toll of living with visible psoriasis is significant. Depression and anxiety rates are higher in psoriasis patients than the general population. This isn't a side note. It's a core part of the disease burden. Seeking mental health support alongside dermatological treatment is standard practice for good reason. The two are connected and treating both improves outcomes. There is no single path that works for everyone. What clears one person's skin completely might do nothing for another. The genetic and immune variations between individuals are too large. Working with a dermatologist who will try different approaches and adjust based on your response is the only reliable strategy. Be honest about what you're experiencing, report side effects promptly, and don't accept treatment plans that don't address your quality of life concerns.