
Reflux is annoying and nobody seems to agree on what actually fixes it permanently
I spent about three years bouncing between antacids, PPIs, and dietary experiments before I figured out what was actually moving the needle for me. Most people treat reflux like it's one thing. It isn't. Acid comes up for different reasons in different bodies, and the fix depends entirely on which mechanism is driving your symptoms. Let me walk through what I learned the hard way.
How To Get Rid Of Reflux: figuring out your type first
The most important thing nobody tells you is that reflux falls into distinct categories, and running the wrong strategy for your type just wastes time and money. The big ones are LPR (laryngopharyngeal reflux, sometimes called silent reflux because you don't feel the classic heartburn), typical GERD, and bile reflux. They feel somewhat similar but respond to completely different approaches. With typical GERD, stomach acid crosses a loose lower esophageal sphincter. With LPR, the same thing happens but the acid reaches your throat and voice box, so you get chronic cough, hoarseness, or that constant need to clear your throat instead of heartburn. Bile reflux is different again — it involves bile from the small intestine backing up, and PPIs do basically nothing for that because the problem isn't acid. I made the mistake of assuming I had standard GERD when I actually had LPR. I was chugging omeprazole at dinner time for months and my throat symptoms didn't budge. Switching to an alginate-based treatment like Gaviscon Advance (the UK version with higher sodium alginate concentration) after meals and before bed was what finally cut the throat symptoms. That was a genuinely expensive lesson.
The mechanical fixes that actually matter
Most advice focuses on diet. Diet matters less than you'd think if the underlying issue is mechanical. Your LES (lower esophageal sphincter) is a valve. If it's loose or getting periodically relaxed when it shouldn't be, no amount of avoiding trigger foods will fully solve the problem. You need to work on the mechanics. Elevation during sleep is the simplest high-impact change. I raised the head of my bed about six inches using wooden blocks under the bedposts rather than just stacking pillows. Stacking pillows makes you bend at the waist, which actually increases abdominal pressure and makes things worse. Just tilting the entire upper frame works. This alone reduced my nighttime symptoms by maybe sixty percent. Meal timing is the second mechanical lever. Eating within three hours of lying down is the single most reliable trigger for reflux episodes. I set a hard rule: last bite of food by 7 PM, bed by 10 PM. That window matters more than what you eat in most cases. Your stomach needs time to actually empty before gravity stops helping you.
Get the Full Details
Abdominal pressure is the hidden factor. Tight waistbands, heavy lifting right after eating, and even straining during bowel movements can push content past a weak LES. I switched to loose clothing after meals and started treating constipation aggressively because I noticed a clear pattern — hard stools correlated with worse reflux the next day. It's the same pressure dynamics, just coming from below instead of above.
Dietary adjustments that are worth the effort
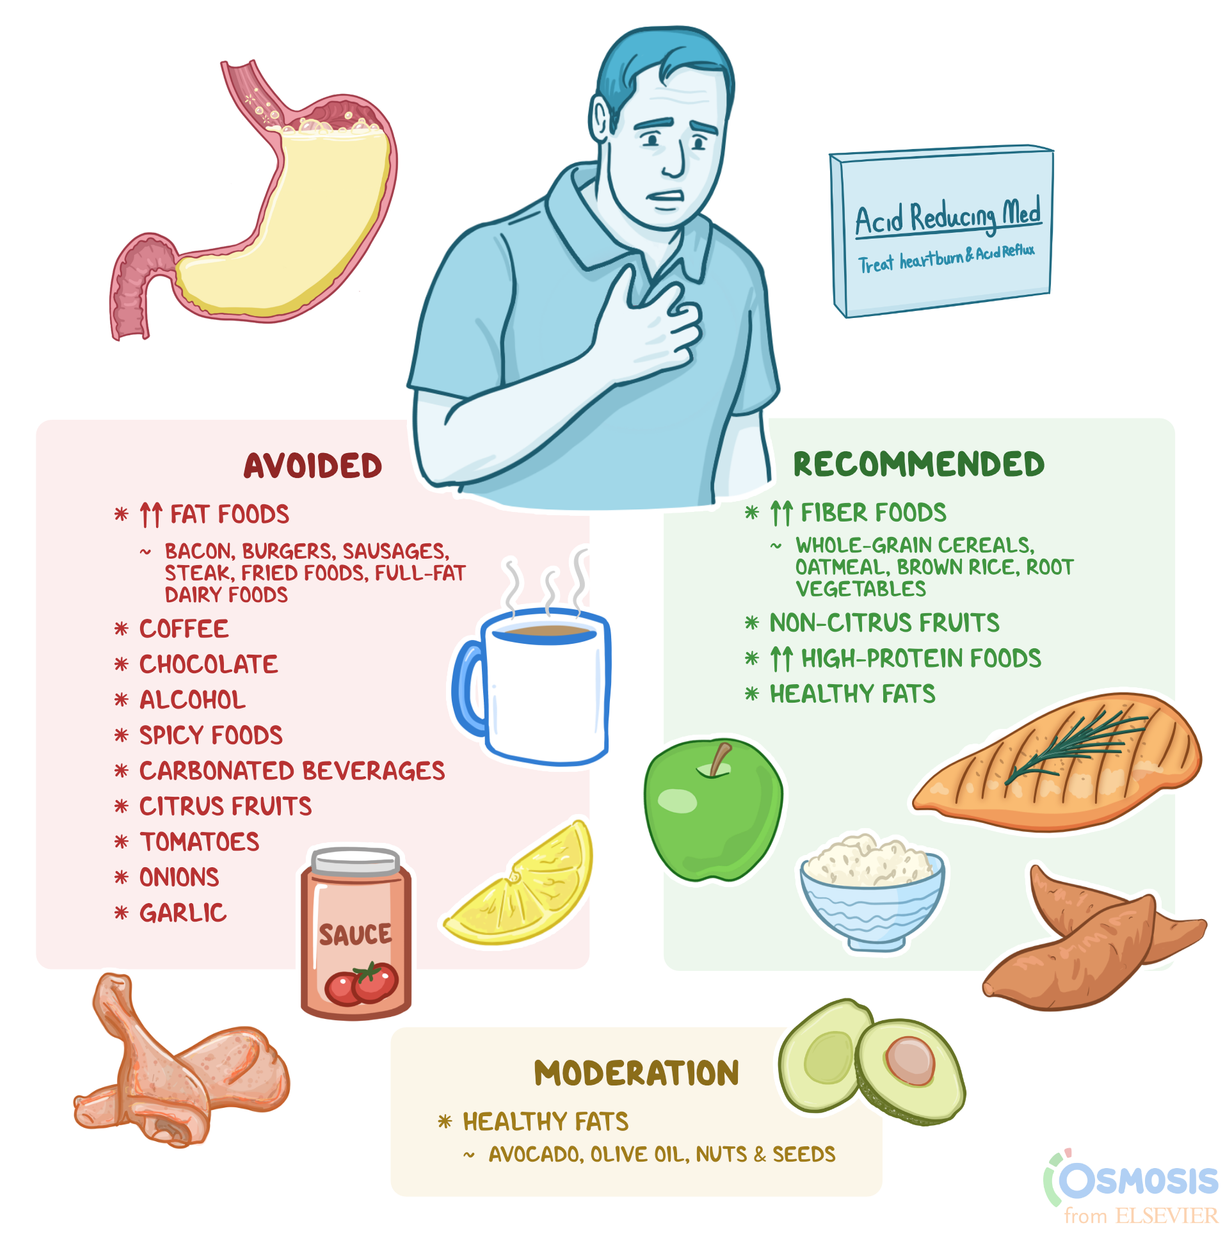
Not all trigger foods are created equal. The usual suspects — spicy food, citrus, tomato, chocolate, caffeine, alcohol — affect people differently. I kept a simple symptom log for two weeks and found that only two items on that list actually moved the needle for me: alcohol and large meals. Everything else was noise. The biggest dietary mistake I see people make is going too restrictive too fast. Cutting out every potential trigger at once makes it impossible to figure out what's actually causing your symptoms. Start with the three most common ones — large meals, alcohol, and eating too close to bedtime — and evaluate for two weeks before adding more restrictions. Meal size matters more than meal content. A huge plate of safe foods will trigger reflux more reliably than a small portion of borderline trigger foods. I cut my portions roughly in half and ate every three to four hours instead of two large meals. That change alone was the single most effective dietary shift I made.
Bland diets don't work long-term because you can't sustain them. The goal isn't to eliminate triggers forever. The goal is to find your personal threshold and manage around it.

Medications and when they help or hurt
PPIs like omeprazole, pantoprazole, and esomeprazole reduce acid production. They're effective at healing esophagitis and reducing symptoms for typical GERD. But they're not a permanent solution and they have real downsides you should know about. Long-term PPI use is associated with decreased magnesium absorption, increased risk of C. difficile infection, possible bone density effects over years of use, and acid rebound when you stop taking them. I tapered off mine over eight weeks by halving the dose for two weeks, then every other day for two more weeks. Skipping the taper is how I got three days of hellish rebound acid hypersecretion. Don't skip the taper. H2 blockers like famotidine are weaker but have fewer long-term risks. I found them useful as a standby on days when PPIs felt like overkill. Antacids provide immediate but short-lived relief — they neutralize acid that's already there but don't prevent reflux from happening.
Alginates deserve more attention than they get. Products with sodium alginate form a physical raft on top of stomach contents that blocks reflux from reaching the esophagus. They work mechanically rather than chemically, so they're safe for longer-term use. The UK formulation (Gaviscon Advance) has a much higher alginate concentration than the US version, which is why people report dramatically different results depending on where they buy it. This is genuinely important and almost nobody mentions it. Bile reflux doesn't respond to PPIs. For that, prescription medications like ursodeoxycholic acid or bile acid sequestrants are what doctors typically use. If PPIs aren't touching your symptoms and you have a history of gallbladder removal or gastric surgery, bile reflux should be on the differential.
When to stop self-treating and see a doctor
There are red flags that mean you need professional evaluation, not another round of home experiments. Difficulty swallowing, unexplained weight loss, vomiting blood, black tarry stools, anemia, or chest pain that radiates to your arm or jaw. Any of those warrant an urgent visit. Even without red flags, if you've been managing reflux on your own for more than two weeks without meaningful improvement, or if you need daily medication to function, you should get evaluated. An endoscopy can show Barrett's esophagus, hiatal hernias, or other structural issues that change the treatment plan entirely. I had a small hiatal hernia that I didn't know about, and knowing about it changed how I approached everything — certain positions and eating habits that worked for regular GERD made my symptoms noticeably worse.

How To Get Rid Of Reflux in stubborn cases
If conservative measures and medications aren't enough, there are surgical and procedural options. Linx is a ring of magnetic beads placed around the LES that reinforces the valve while still allowing food through. Nissen fundoplication wraps the top of the stomach around the LES to tighten it. Both have tradeoffs. Fundoplication can cause difficulty swallowing and inability to vomit. Linx has erosion and migration risks. Neither is trivial. These procedures work best for people who have documented GERD on testing and respond to PPIs but don't want to be on them long-term. They're not magic bullets. I knew someone who had Nissen fundoplication and still had intermittent symptoms because the wrap loosened over time. Surgery changes anatomy but doesn't guarantee a cure. The bottom line is that reflux management is iterative. You try something, you track results for a couple weeks, you adjust. The people who get it under control aren't the ones who find one perfect solution — they're the ones who systematically figure out what combination of mechanical, dietary, and medical interventions works for their specific case.


