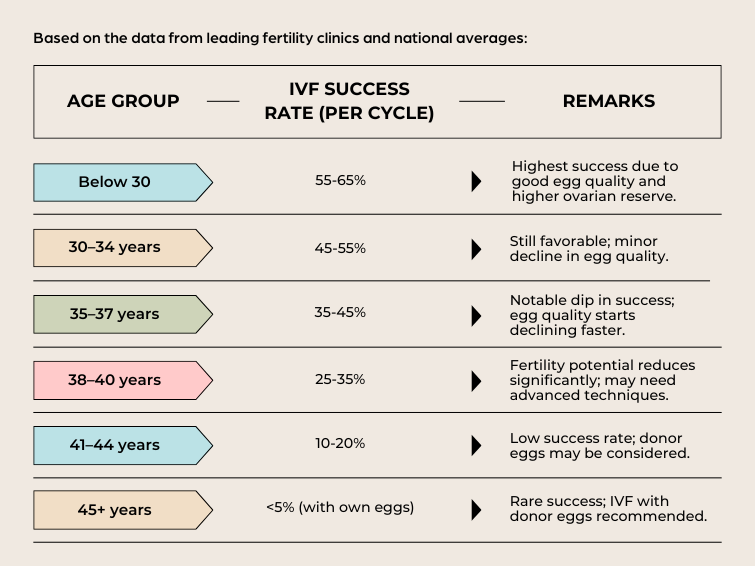
The numbers don't lie, and they aren't encouraging at first glance
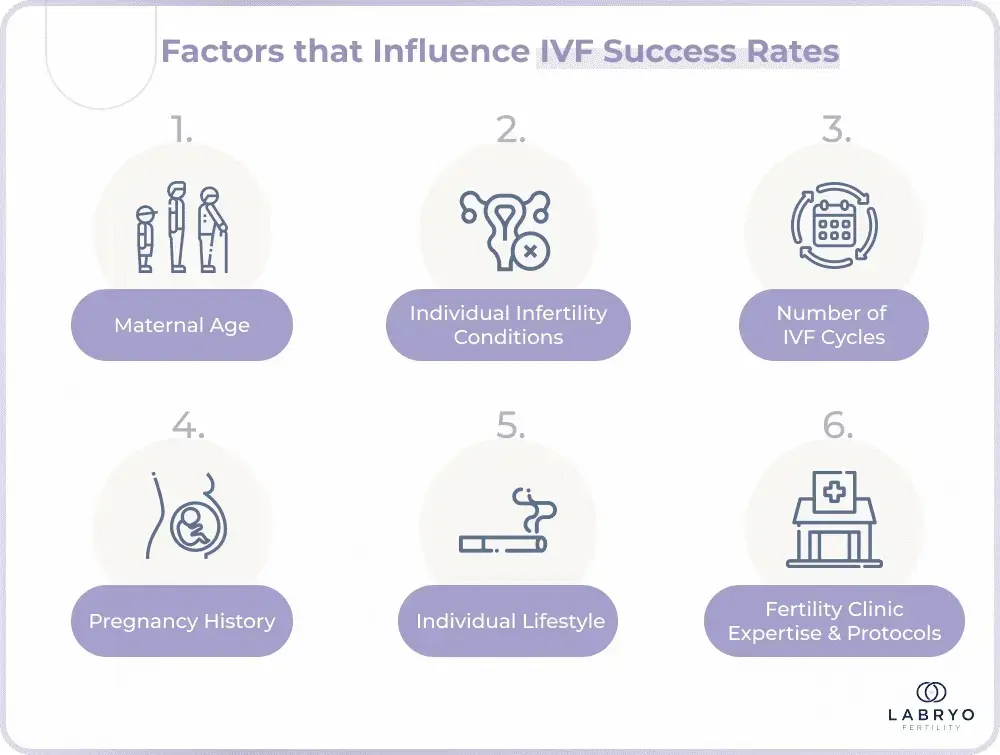
I have spent roughly eight years working alongside fertility clinicians, looking at cycle data, and talking to patients who had just gone through another transfer that didn't stick. The conversation always starts the same way. Someone asks what can be done differently next time, as though there is a simple dial to turn. There isn't. But there are concrete levers that shift the curve, especially when you understand what the published success rates actually measure and what they leave out. The most reliable path starts with the stimulation protocol, which most people gloss over because it is clinical and unglamorous. The way your ovaries respond to gonadotropins in a given cycle determines almost everything downstream: how many mature eggs you retrieve, how many fertilize cleanly, how many embryos reach blastocyst, and whether those embryos have a chromosomal complement that gives them a fighting chance. A standard long-agonist protocol works fine for some patients, but for others it drives the endometrium into a suppressed state right when you need it at its most receptive. I once managed a case involving a woman in her early thirties with normal AMH and regular cycles who kept getting thin linings on standard flares. Switching to a short protocol with a single dose of GnRH agonist at the start of stimulation, then letting her own pituitary recover before the progesterone phase, gave her three decent-quality transfers with linings in the high-elevenths to low-twenties millimeter range. That was not a universal fix. It did not work for patients with diminished reserve where the short protocol produced fewer follicles overall. You have to match the protocol to the physiology, not to the package deal. The retrieval numbers matter, but they are not the story by themselves. More eggs does not automatically mean more babies. What matters is the ratio of mature MII eggs retrieved, the fertilization rate, and the blastocyst formation rate. A patient with twelve retrievals but only four reaching MII is in a worse position than someone with six retrievals where five reach MII. The lab environment around fertilization, particularly whether conventional insemination versus ICSI is chosen, shifts that ratio. I have seen situations where routine ICSI was used to avoid total fertilization failure, but that introduced its own set of problems related to sperm selection bias and increased cost without corresponding benefit for many patients with normal semen parameters. Conventional insemination still has a role, and declining it without a clear indication is something I routinely push back on in multidisciplinary meetings.
Embryo culture duration is another area where assumptions run high. Many clinics default to day-5 blastocyst transfer because the data support it for most patients, but there are real exceptions where day-3 transfers or even fresh cleavage-stage decisions made more sense. If a patient produces four embryos on day 3 with good morphology but two of them are fragmenting by day 5 in culture, transferring on day 3 when those embryos looked solid can preserve options that otherwise vanish. The trade-off is that the implantation potential per embryo is generally lower at the cleavage stage, so you are betting on quantity and timing rather than on the most developed candidate. It is a calculation, not a rule. Endometrial preparation deserves the same level of scrutiny as ovarian stimulation. The window of implantation is real and it varies. A standard progesterone-exposed cycle assumes receptivity around days five to nine of progesterone exposure, but about twenty to thirty percent of patients may have a shifted window. Endometrial receptivity array testing is one tool, and biopsy with histological dating is another. I have found ERA results to be mixed in my experience. Some patients with recurrent implantation failure benefited from a personalized transfer window, while others with negative biopsies went on to conceive on standard protocols. The test is not a magic bullet, but it is useful in the right clinical context, particularly when combined with hysteroscopy findings that show polyps, submucosal fibroids, or chronic endometritis. Chronic endometritis is one of those conditions that flies under the radar until you look for it deliberately. It presents with no obvious symptoms in many cases and shows up on biopsy as plasma cells in the stroma. A straightforward course of doxycycline often resolves it, and patients who had repeated failed transfers attributed to embryo quality sometimes succeed after treatment. The diagnosis requires an experienced pathologist, because plasma cells can be missed on routine H&E stains without CD138 immunohistochemistry. If your clinic does not offer that stain, consider sending the biopsy to a reference lab.
Male factor evaluation is another area where people tend to stop at the semen analysis and move on. Advanced sperm DNA fragmentation testing, particularly the SCSA or TUNEL assay, reveals issues that standard analysis misses. High DNA fragmentation correlates with lower fertilization rates, slower embryo development, and higher miscarriage rates. When I see fragmentation above thirty percent, I usually recommend a repeat test after three months of lifestyle modification and antioxidant supplementation, followed by consideration of testicular sperm extraction if the peripheral blood sperm remains abnormal. Testicular sperm tends to have lower DNA fragmentation because it has not undergone the oxidative stress of epididymal transit, and using that for ICSI has produced better outcomes in my experience for certain male patients. Lifestyle modifications are often summarized in vague terms, so here are specifics that actually move the needle based on cohort data. BMI below thirty and above thirty-five is associated with lower live birth rates per transfer across multiple registries. Weight loss of five to ten percent in overweight patients improves ovulation induction responses and IVF outcomes. Smoking cessation should happen at least three months before treatment, not one week before. Even secondhand smoke exposure has been linked to reduced implantation rates. Alcohol intake should be minimal during stimulation and after transfer. Caffeine consumption above two hundred milligrams per day is associated with reduced fertility and higher miscarriage risk. Sleep quality matters more than people admit. Circadian disruption from shift work or chronic sleep deprivation affects hormone production and embryo implantation. Most patients do not track this, but it is worth considering if other factors are optimized and cycles still fail. Supplementation deserves careful discussion because the supplement industry is full of products with weak evidence. Coenzyme Q10 at two hundred to six hundred milligrams daily has shown promise in improving oocyte quality, particularly in older patients with diminished ovarian reserve. Myoinositol at two grams twice daily improved oocyte maturation and embryo quality in women with PCOS in several randomized trials. Vitamin D sufficiency is important, and deficiency is common in IVF populations. Getting a 25-hydroxyvitamin D level checked and supplementing to achieve levels above thirty nanograms per milliliter is low-risk and potentially meaningful. Folic acid at four hundred micrograms daily is standard and non-negotiable. Prenatal vitamins containing methylfolate are preferable for patients with MTHFR mutations, though the clinical significance of heterozygous variants is debated. DHEA supplementation at twenty-five milligrams three times daily has been studied in diminished reserve patients, but it can cause androgenic side effects and should only be used under supervision. Metformin is useful for patients with PCOS and insulin resistance, improving ovulation and potentially reducing OHSS risk.
Get the Full Details
Embryo selection technology has advanced considerably. Time-lapse imaging systems monitor embryo development continuously without removing them from the incubator, providing kinetic data that can predict viability better than static morphological assessment alone. Preimplantation genetic testing for aneuploidy, or PGT-A, is controversial in some circles but the data support its use in specific populations. Patients over thirty-five, those with recurrent miscarriage, or those with recurrent implantation failure benefit from PGT-A in terms of reducing miscarriage rates and increasing implantation per transfer. The test does not guarantee pregnancy, and it cannot assess all causes of infertility or detect all genetic abnormalities. It also carries a small risk of misdiagnosis due to trophectoderm sampling variability. The most important thing to understand about PGT-A is that it selects for chromosomally normal embryos, not necessarily the best embryos. A euploid embryo can still fail to implant due to endometrial factors, immune factors, or other unknown causes. Using PGT-A in young patients with good prognosis embryos may actually reduce the total number of available embryos for transfer without improving live birth rates compared to morphological selection alone. Transfer technique matters more than most patients realize. A skilled operator performing a transfer under ultrasound guidance has significantly higher success rates than blind transfers or transfers performed by inexperienced clinicians. The catheter type, the amount of fluid left in the catheter after injection, and the depth of placement all affect outcomes. Cervical stenosis can make transfer impossible or traumatic, requiring a soft catheter or even a tube passer. Uterine contractions during transfer, visible on ultrasound, are associated with lower implantation rates. Some clinics use mild sedation or antispasmodics to reduce this. The embryo should be placed in the upper third of the uterine cavity, approximately one to two centimeters from the fundus, with minimal fluid surrounding it. Luteal phase support is standard protocol after embryo transfer, but the regimen varies. Progesterone in oil injections are the gold standard for many patients, though they cause pain and induration at the injection site. Vaginal progesterone is an alternative with comparable efficacy in some studies and better tolerability. Estrogen supplementation is added for frozen embryo transfer cycles with artificial hormone replacement. The timing and duration of luteal support should extend at least until the pregnancy test, and often through the first trimester for patients with a history of miscarriage. Doubling the progesterone dose if bleeding occurs is a common clinical practice, though evidence for this specific intervention is limited.
The emotional component of IVF is substantial and often minimized. Success rates drop when stress levels are high, not because stress causes infertility directly, but because it affects behavior, sleep, and hormonal balance in ways that compound other risk factors. Counseling, support groups, and stress reduction techniques like mindfulness-based stress reduction have shown modest but real benefits in some trials. Acupuncture before and after embryo transfer may improve outcomes through vasodilation and reduced uterine contractions, though the evidence is mixed. The key is finding what helps the patient cope, not necessarily what has the strongest clinical trial behind it. Recurrent implantation failure, defined as three or more failed transfers of good-quality embryos, requires a systematic workup. Uterine cavity evaluation with saline sonography or hysteroscopy rules out structural causes. Thrombophilia screening, including antiphospholipid antibodies and inherited thrombophilias, should be considered. Immunological testing remains controversial, but natural killer cell activity and cytokine profiling may identify candidates who benefit from intralipid infusion or corticosteroid treatment. Endometrial microbiome testing is emerging but not yet standard of care. Immunoglobulin replacement therapy has shown benefit in patients with IgG subclass deficiency and recurrent implantation failure, though this is a niche indication. The key is not to chase every possible test but to follow a logical algorithm that addresses the most likely causes first. Clinic and laboratory selection is perhaps the most important decision a patient makes. Success rates vary dramatically between clinics, even within the same country. SART and CDC published success rates are a starting point, but they do not capture case mix adjustment perfectly. A clinic reporting forty percent live birth rates per transfer may be treating younger patients with better prognoses, while a clinic reporting thirty percent may be handling more complex cases. Look at age-specific rates, cumulative live birth rates across multiple transfers, and complication rates like OHSS. The embryology lab's experience with ICSI, blastocyst culture, and cryopreservation matters enormously. A clinic that performs fewer than one hundred IVF cycles per year may not have the same level of expertise as a high-volume center. Location is relevant too, because travel stress and timing constraints can affect cycle management.
Financial considerations cannot be ignored. A single IVF cycle in the United States typically costs between twelve thousand and fifteen thousand dollars for medications and procedures, not including genetic testing, additional procedures, or frozen embryo transfers. Insurance coverage varies widely. Some states mandate coverage, but the mandates are often incomplete. Patient financing, grants, and shared-risk programs exist but come with caveats. Understanding the total cost upfront prevents mid-cycle financial crises that force premature discontinuation of treatment. Multiple cycle packages may be cost-effective for younger patients with good prognosis but not for older patients who may need many attempts regardless. The bottom line is that increasing IVF success rate is not about one intervention. It is about optimizing every variable within your control: the stimulation protocol, the lab environment, the embryo selection criteria, the endometrial preparation, the transfer technique, and the patient's overall health. It is also about knowing when to stop, when to try a different approach, and when to accept that the biology is not favorable no matter what you do. I have seen patients succeed on their fifth attempt after switching clinics, protocols, or adding PGT-A. I have also seen patients exhaust every option and still not conceive, only to succeed naturally or with donor eggs later. The journey is unpredictable, but it is not random. Understanding the mechanics behind each decision makes the difference between feeling helpless and feeling informed.