What Actually Happens When Your Blood Sugar Goes Rogue
Most people find out they have diabetes because something obvious finally broke. Like waking up with your feet numb or needing to pee three times during the night and assuming it's just age. I've seen this play out enough times that the pattern is almost predictable. Someone ignores the early signs for two or three years because they feel "fine," and by the time they get to a clinic, their HbA1c is sitting at 9 or 10. There are actually a few different ways this disease reveals itself, and knowing which one you're dealing with matters more than you'd think. Type 2 diabetes can simmer quietly for a decade. Type 1 hits fast and hard. Gestational shows up during pregnancy and sometimes disappears after delivery. Each one has a different timeline, different warning signs, and very different treatment paths.
How To Know If You Have Diabetes
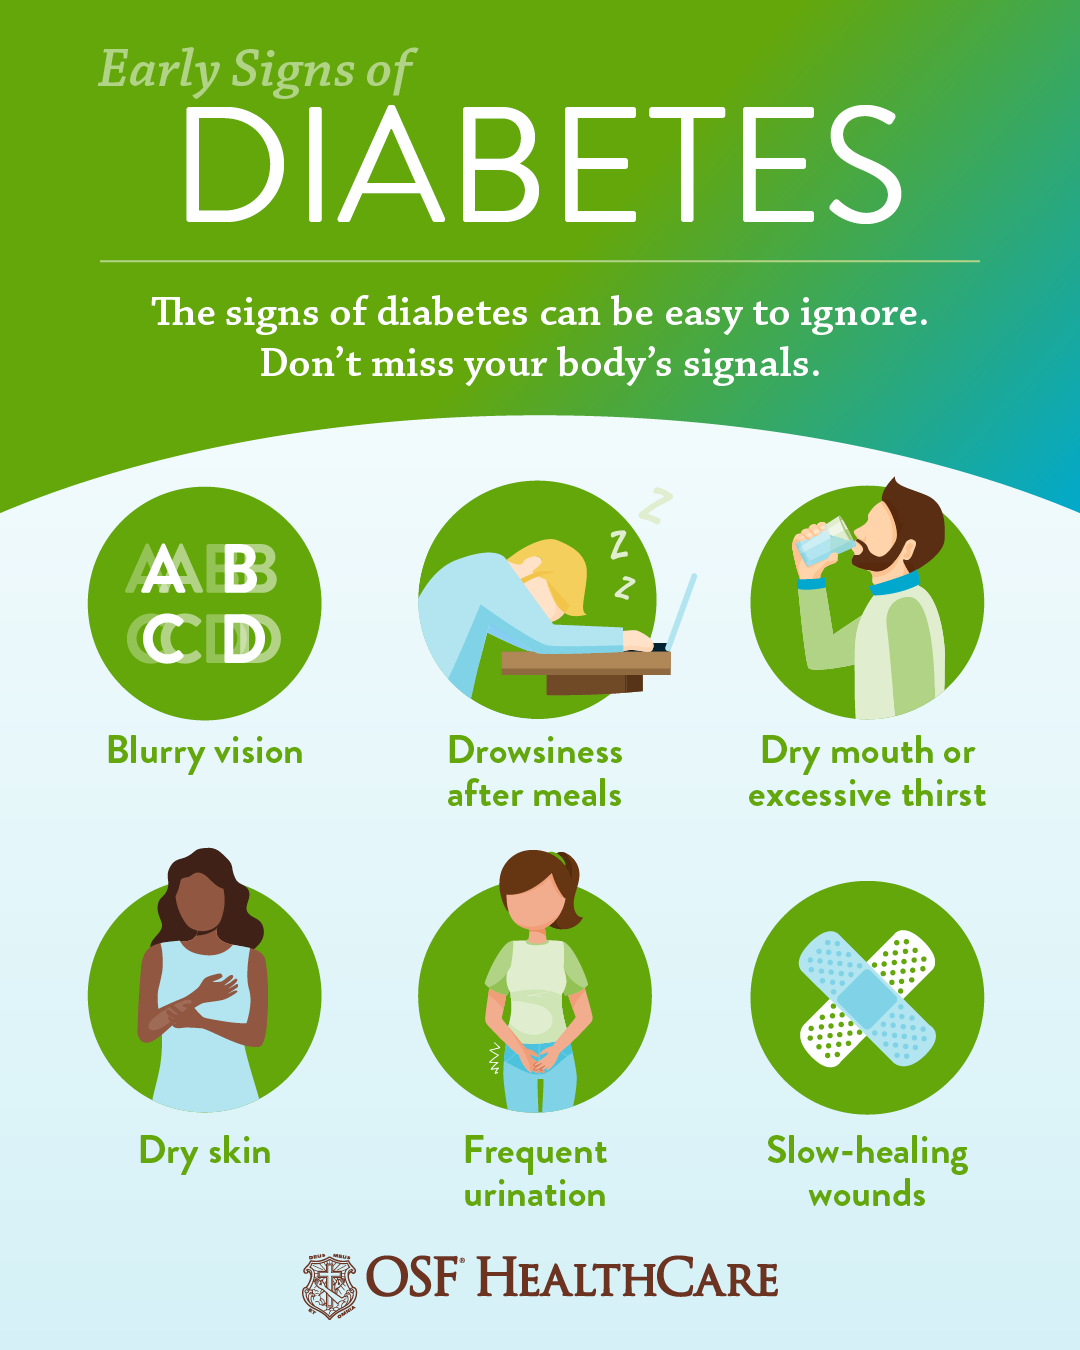
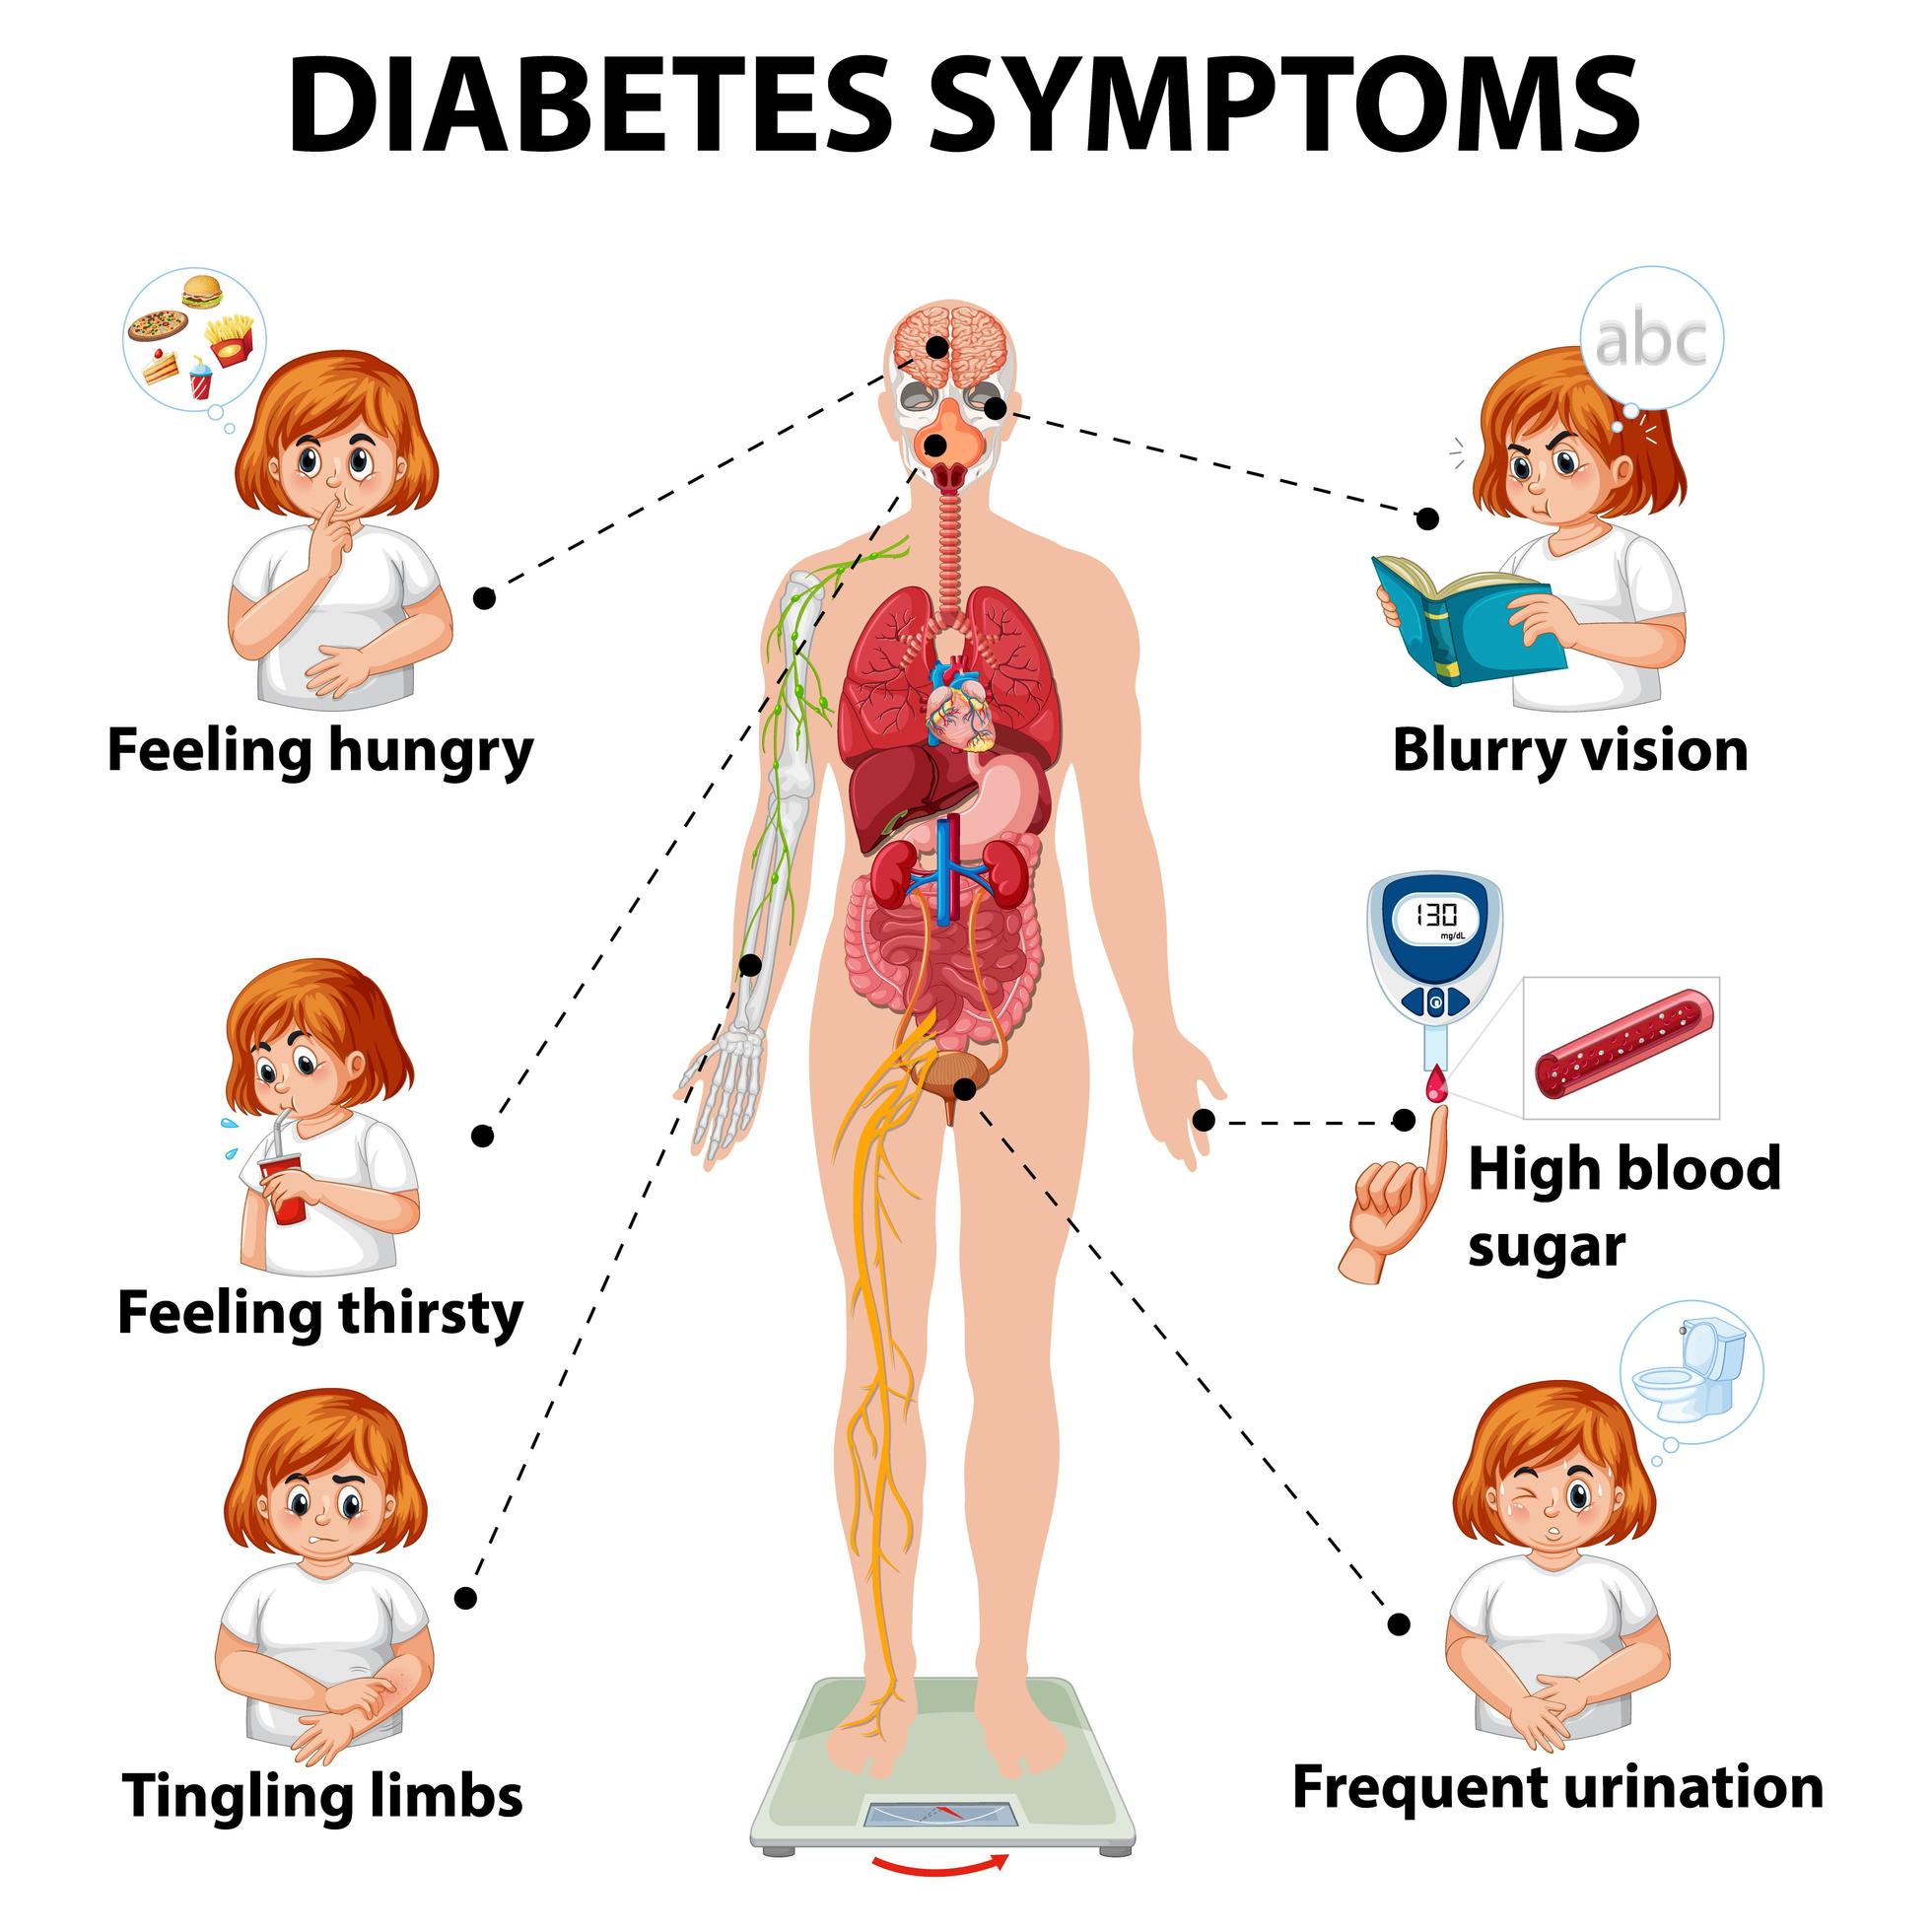
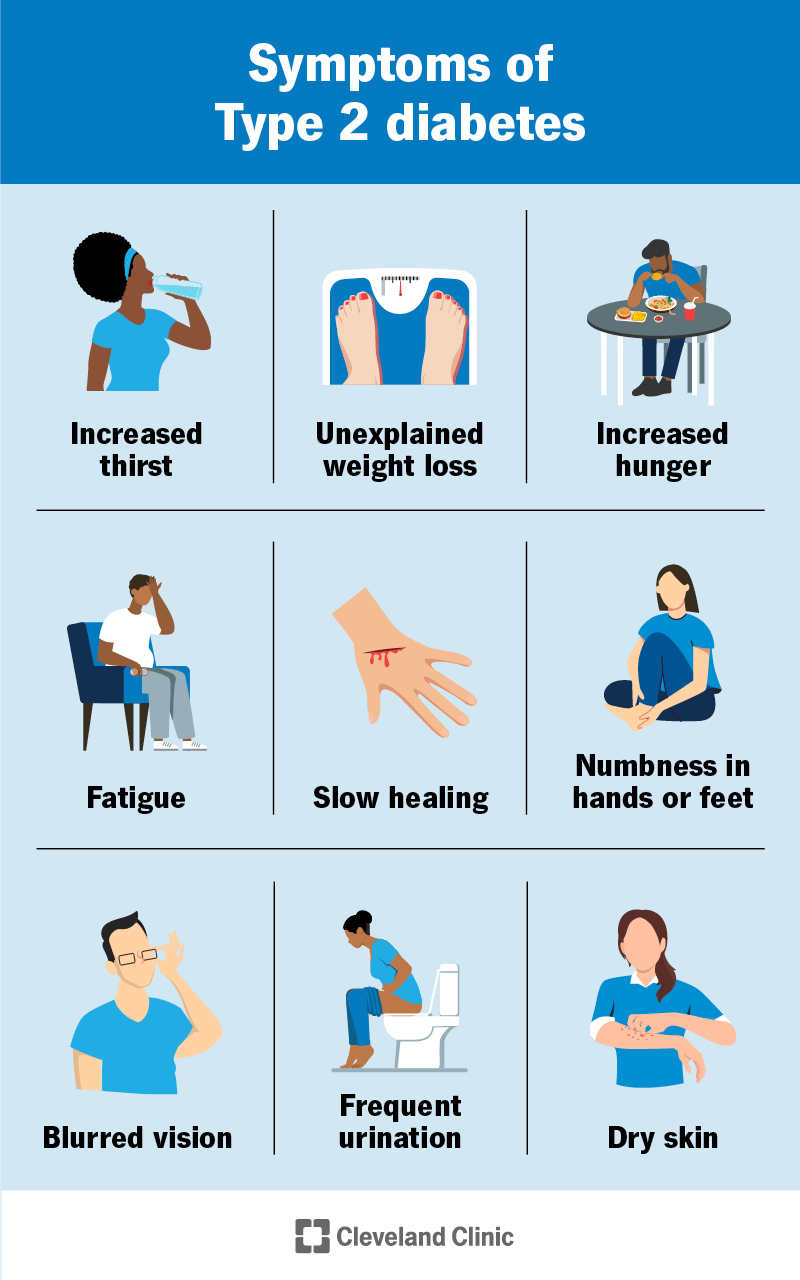
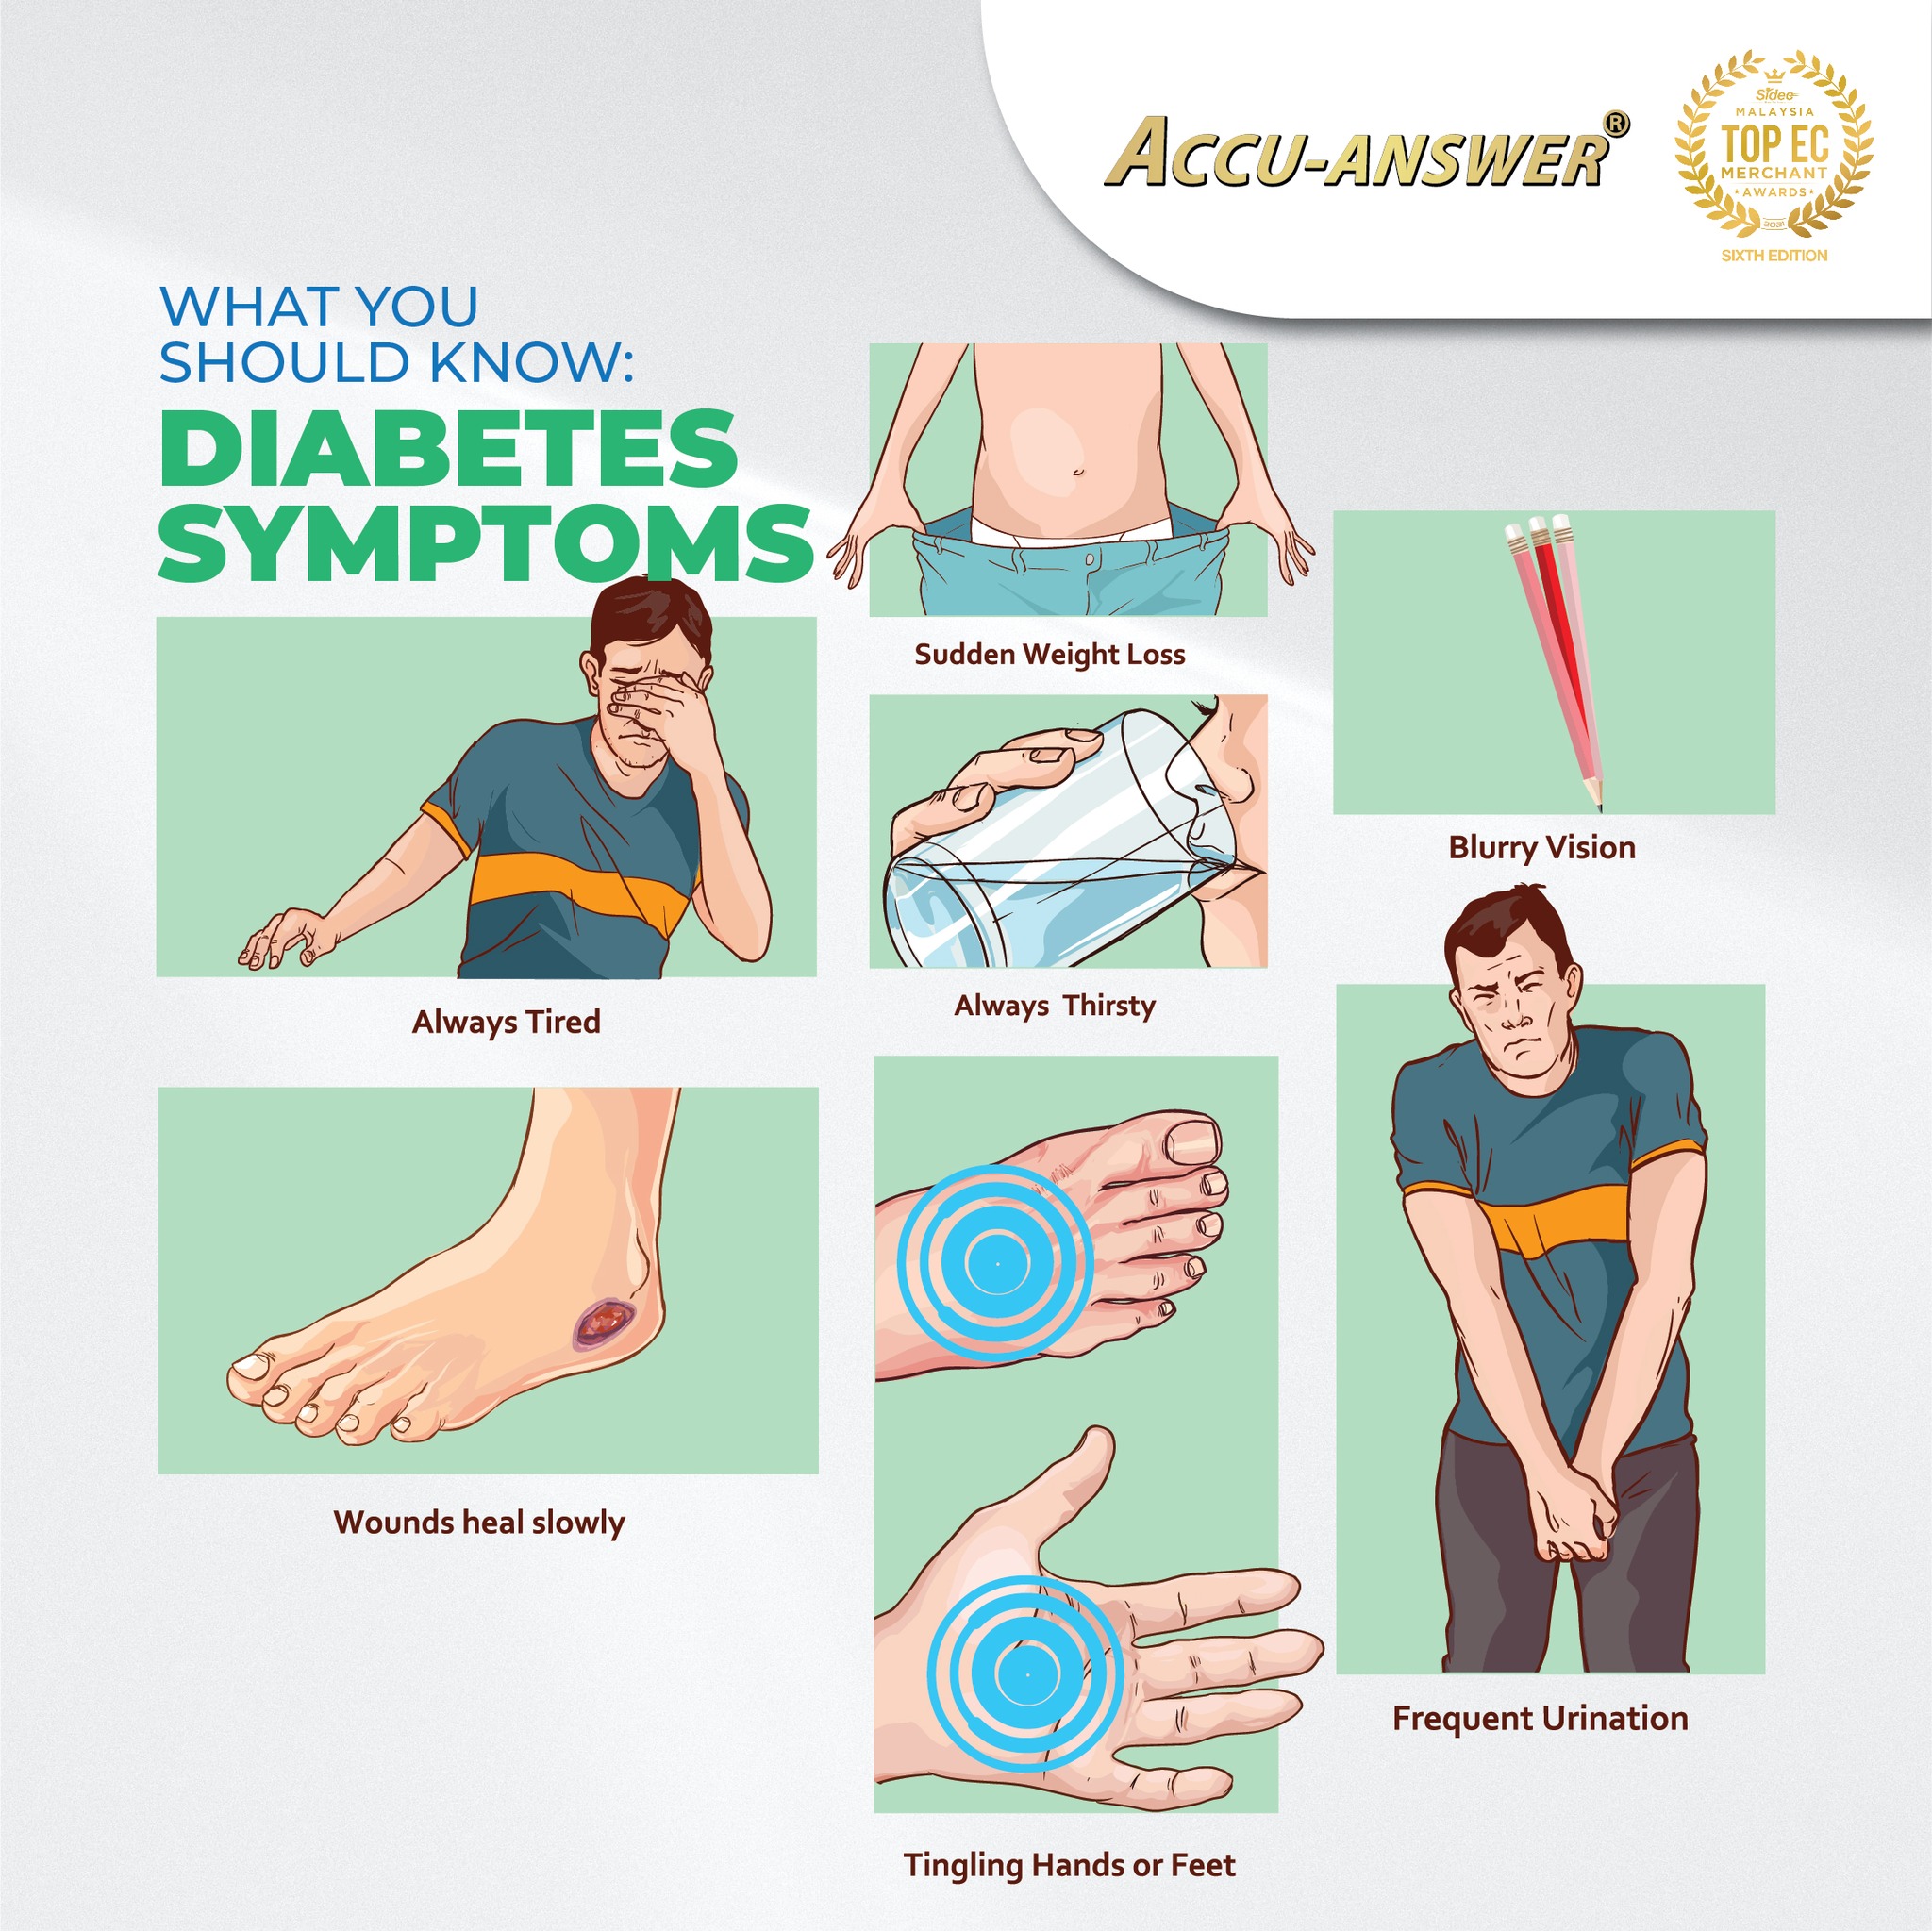
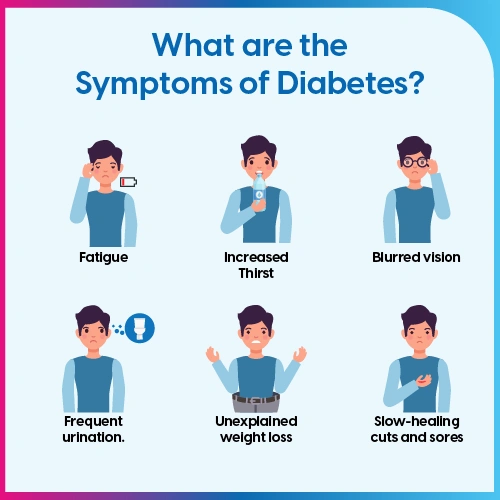
The clinical answer is straightforward but incomplete. You need blood tests. A fasting blood glucose test measures your sugar after not eating for at least eight hours. Normal is below 100 mg/dL. Prediabetes sits between 100 and 125. Diabetes is 126 or higher on two separate tests. The HbA1c test tells you your average blood sugar over the past two to three months. Below 5.7% is normal. Between 5.7% and 6.4% is prediabetes. 6.5% or above is diagnostic for diabetes. Then there's the oral glucose tolerance test, which involves drinking a sugary liquid and having your blood drawn every hour or so for a couple of hours after. Here's the thing nobody tells you: those tests have blind spots. An HbA1c of 5.8% looks fine on paper, but if you just got off a course of oral steroids for a rash, that number is completely unreliable. Steroids spike blood sugar dramatically and skew HbA1c readings for weeks. Same deal if you have anemia, sickle cell trait, or any condition that affects red blood cell turnover. In those cases, HbA1c becomes mostly decorative. You'd want a fructosamine test instead, which measures glycosylated protein over the past couple of weeks rather than months. It's less commonly ordered but far more accurate when your red blood cells aren't behaving normally. On the symptom side, the classic triad is polyuria, polydipsia, and polyphagia. That's excessive urination, excessive thirst, and excessive hunger. Your body floods your bloodstream with glucose it can't use, so your kidneys pull extra water to flush it out. You get dehydrated. You drink more. The cycle continues. Unexplained weight loss is another red flag, particularly for Type 1, where your body starts burning fat and muscle for energy because insulin isn't doing its job shuttling glucose into cells.
I once had a patient who literally failed every standard diabetes screening but ended up diagnosed anyway. Her fasting glucose was normal. Her HbA1c was 5.9%. She felt terrible though, constantly exhausted, foggy, and constantly hungry. We ran a continuous glucose monitor for two weeks as a research option and what we found was striking. She wasn't diabetic by the numbers, but her blood sugar spiked to 280 mg/dL after breakfast almost every day, then crashed to 55 by early afternoon. Those postprandial spikes never showed up in any standard test. This is what I mean about the limitations of routine screening. If you only check fasting glucose and HbA1c, you miss a huge chunk of people who are struggling with glucose intolerance after meals. Another counter-intuitive detail: being thin doesn't protect you from Type 2 diabetes. I see this misconception constantly. Lean people can absolutely develop insulin resistance and Type 2. It's called lean diabetes or Type 1.5, and it's increasingly common, especially in Asian populations where the threshold for metabolic risk sits at a lower BMI than the standard guidelines account for. A person who weighs 160 pounds and has a BMI of 23 can have the same metabolic dysfunction as someone at 280 pounds. There's also the matter of latent autoimmune diabetes in adults, or LADA. This is Type 1 diabetes that develops slowly in adulthood, often misdiagnosed as Type 2 because of the patient's age. People with LADA are typically prescribed metformin and told to manage diet, and they slowly get worse over months or years because their pancreas is actually being attacked by their own immune system. The key difference is that LADA patients eventually need insulin, while typical Type 2 can sometimes be managed with oral medications alone. Testing for GAD antibodies and C-peptide levels can distinguish between the two. A low C-peptide with positive GAD antibodies means autoimmune destruction is happening regardless of how old you are.
Get the Full Details
If you're trying to figure out whether you should get tested, here are the official screening guidelines from the American Diabetes Association. Get screened at age 35 if you're overweight or obese, and again every three years if results are normal. Start earlier and test more often if you have additional risk factors: a parent or sibling with diabetes, a history of gestational diabetes, high blood pressure, low HDL cholesterol, high triglycerides, PCOS, physical inactivity, or belonging to certain racial and ethnic groups with higher prevalence rates. The ADA specifically calls out African American, Hispanic, Native American, Asian American, and Pacific Islander populations as having higher risk at lower BMI thresholds. Home testing kits exist now, which changes the accessibility question entirely. There are FDA-cleared home blood glucose meters and some companies offer mail-in dried blood spot tests for HbA1c. The home meters are reasonably accurate if you calibrate them properly and use fresh strips. The dried blood spot tests have wider confidence intervals than lab-based HbA1c. A result of 6.2% from a home kit might actually be 5.8% or 6.6% in a lab. Use home tests for tracking trends, not for making a diagnosis. Only a clinician can diagnose diabetes, and only a lab can confirm it. The uncomfortable truth about diabetes screening is that most diagnosed cases were already at stage 3 or 4 before anyone noticed. Stage 1 is prediabetes with no symptoms. Stage 2 is early Type 2, still mostly silent. By Stage 3, the damage to blood vessels, nerves, and kidneys has been accumulating for years. Every year of undiagnosed Type 2 diabetes increases your risk of cardiovascular disease by about 8%, according to longitudinal studies. That's not dramatic in any single year, but it compounds aggressively over a decade.
So if you want to know whether you have diabetes, the practical path is: get a fasting glucose and HbA1c through your primary care provider, discuss whether you need an oral glucose tolerance test based on your risk profile, and if your results are borderline or your symptoms persist despite normal numbers, push for further investigation rather than accepting the screening as definitive. Don't let a single normal lab visit close the door. One data point is never enough.