Understanding the actual mechanics before you start throwing things at it
Blood pressure is your arteries pushing back against the volume and force of blood being circulated through them. The numbers you see on a cuff — like 120 over 80 — represent systolic pressure during a heartbeat and diastolic between beats. When both climb consistently above 130/80, that's stage one hypertension by most current guidelines. It's a mechanical problem, not a mysterious one, and the interventions that actually move the needle are fairly boring. I'll be honest with you — most of what you'll read online about lowering blood pressure is either way too vague or dangerously oversimplified. Let me give you the specifics because the difference between "eat healthier" and knowing exactly what to do is the difference between dropping four points or forty. The single most impactful change is sodium reduction, but not in the way people think. Cutting table salt isn't enough. The problem is ultra-processed foods, restaurant meals, and packaged goods hiding salt under names like monosodium glutamate, disodium inosinate, and sodium bicarbonate. A standard American diet averages around 3,400 milligrams daily. Getting down to 1,500 is the target most studies show meaningful results at. Track it for a week first using something like Cronometer just to see where you actually are. You'll be shocked how much hidden sodium is in bread alone.
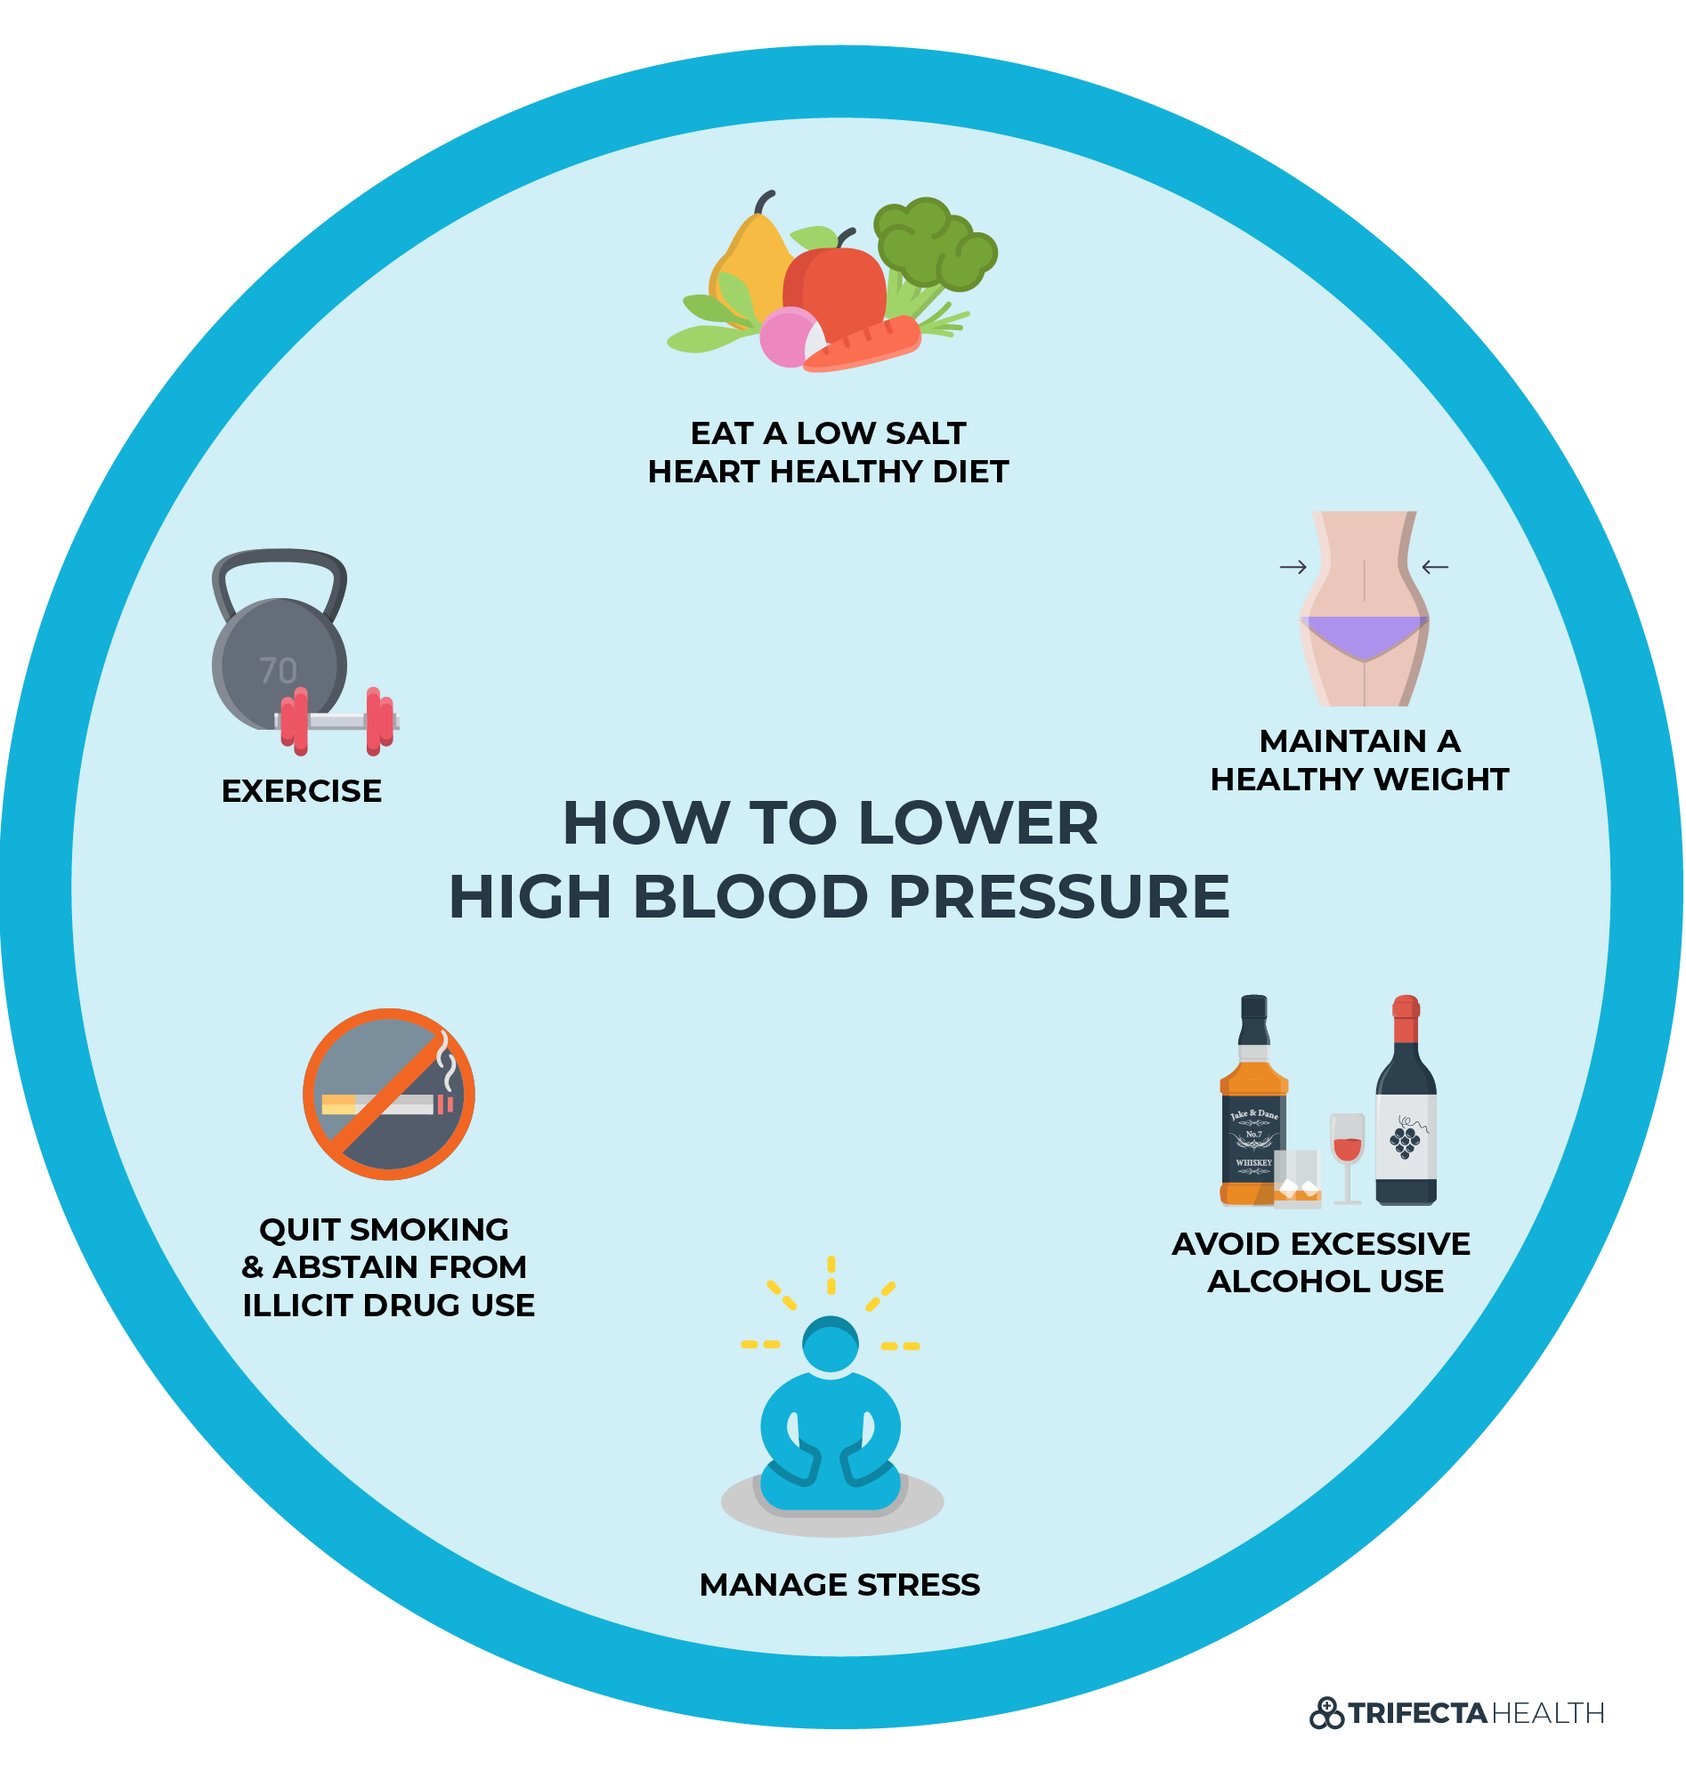
Dietary approach matters enormously. The DASH diet — Dietary Approaches to Stop Hypertension — was literally designed for this and it works. The core mechanism is increasing potassium intake while lowering sodium. Most people don't get enough potassium. Bananas get all the credit but they're mid-tier sources. A baked sweet potato has more potassium than a banana. Spinach, Swiss chard, white beans, and salmon are far more efficient. Aim for 3,500 to 4,700 milligrams of potassium daily through food if your kidneys are healthy. If you have kidney disease, this number changes drastically and you need medical guidance. Movement without specificity is useless for blood pressure. What matters is consistent aerobic exercise at moderate intensity for at least 150 minutes per week. That means something like brisk walking where you can talk but not sing. Resistance training twice weekly adds incremental benefit, but the aerobic component is what drives the acute vasodilation effect that translates into lower resting pressure over time. A meta-analysis from 2023 showed average reductions of about five to seven millimeters of mercury systolic from aerobic training alone. That's clinically significant. Alcohol is one of the most underestimated factors. More than two drinks daily for men or more than one for women pushes pressure up in a dose-dependent relationship. The mechanism involves sympathetic nervous system activation and impaired baroreceptor function. Reducing intake from heavy to moderate drinking often drops systolic pressure by three to five points within weeks. It's almost suspiciously effective and virtually free.
Stress management gets dismissed as fluffy advice, but chronic stress keeps cortisol and adrenaline elevated, which constricts blood vessels and increases cardiac output. It's real physiology, not wishful thinking. But here's the practical problem I encountered: most people try meditation or breathing exercises and quit after two weeks because they don't feel different. The issue isn't that these techniques don't work. It's that they require consistency over months, not days. I found that isometric handgrip exercises were far easier to adopt and actually showed measurable blood pressure reductions in studies. Two minutes of holding a light handgrip at 30 percent max contraction, three times per session, twice daily, resulted in systolic drops of four to eight points in clinical trials. It's mundane enough that people actually do it consistently. Weight loss is perhaps the most powerful intervention if you carry excess weight. Every kilogram of fat loss reduces systolic pressure by roughly one millimeter of mercury. A ten-kilogram loss can meaningfully shift your numbers. But the trick most people miss is that even modest weight loss of five to ten percent of body weight produces outsized blood pressure benefits compared to the amount of weight actually lost.
Get the Full Details

Where things get complicated
Here's what nobody warns you about: measurement technique matters more than most people realize. Improper cuff size is the most common error I see. A standard adult cuff on a larger arm reads falsely high. An oversized arm with an undersized cuff can add fifteen to twenty millimeters of mercury to the reading. Use the right cuff. Measure at the same time of day. Sit quietly for five minutes before taking a reading. Feet flat on the floor. Arm supported at heart level. Don't talk during the measurement. White coat hypertension is real. About twenty percent of people have elevated readings at the doctor's office but normal readings elsewhere. Ambulatory blood pressure monitoring or home monitoring over a two-week period is the only way to distinguish this. Conversely, masked hypertension — normal at the clinic but elevated at home — exists too and is dangerous because it goes undiagnosed. If your office readings are borderline, ask about home monitoring. Some medications raise blood pressure without obvious warning signs. NSAIDs like ibuprofen and naproxen can increase systolic pressure by two to five points with regular use. Decongestants containing pseudoephedrine are particularly problematic. Steroids, certain antidepressants, and stimulant medications all have hypertensive effects. If you're on any regular medication and your pressure won't budge despite lifestyle changes, review your medication list with your prescriber.
Here's a hard truth: lifestyle interventions typically lower systolic pressure by ten to fifteen millimeters of mercury in the best-case scenario. That's substantial, but for people at stage two hypertension — readings above 140/90 — lifestyle alone is rarely sufficient. Medication is not a failure of willpower. It's a tool. ACE inhibitors, ARBs, calcium channel blockers, and thiazide diuretics each work through different mechanisms and combining them is standard practice. The goal is getting your pressure to a safe range, and if lifestyle changes plus medication gets you there, that's the outcome that matters. Some secondary causes of hypertension exist and should be ruled out if your pressure is resistant to treatment. Renal artery stenosis, primary aldosteronism, sleep apnea, thyroid disorders, and pheochromocytoma are less common but important. If you're young with severe hypertension, or if your blood pressure suddenly worsens after years of being controlled, these deserve investigation. Sleep apnea alone affects up to fifty percent of people with resistant hypertension and treating it can dramatically improve control. The most practical sequence I'd recommend: get a validated home monitor — an upper arm model from a brand like Omron or Withings — and track your readings twice daily for two weeks before making any changes. Establish your baseline. Reduce sodium to under 2,000 milligrams daily. Add 150 minutes of moderate aerobic activity per week. Limit alcohol. Start the handgrip protocol. Recheck after four weeks. Most people see movement within that window. If not, that's when you bring the data to a clinician and discuss next steps.