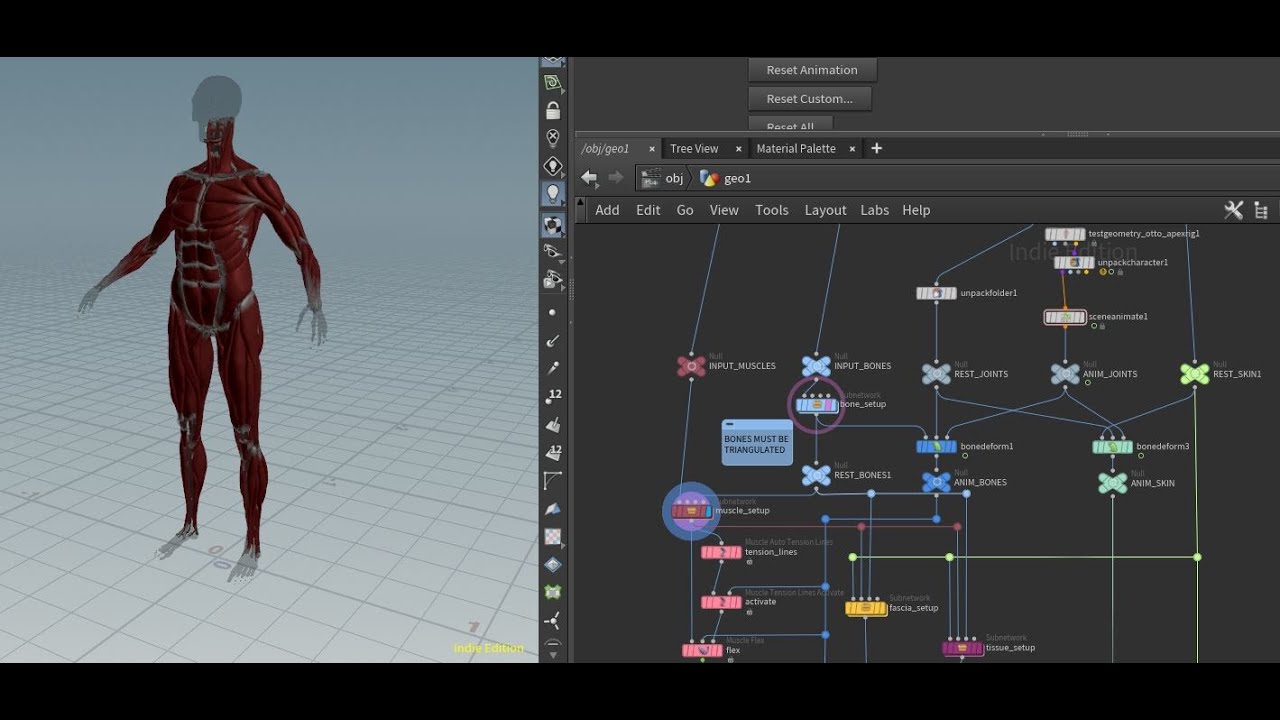
The Technical Reality of Building Anatomical Games
Anatomy gameplay sits somewhere between a medical textbook and a video game, and that tension shows in every phase of development. The core loop is straightforward: player interacts with a representation of human body systems, receives feedback based on anatomical accuracy, and progresses through increasingly complex scenarios. What makes it hard is that "anatomically accurate" and "performant" rarely coexist without deliberate trade-offs. I spent about three months building a dissection module where players could layer-remove tissue and identify structures. The engine was running acceptable framerates until we introduced vascular networks with sub-millimeter vessels. That's when I learned that LOD (level of detail) systems designed for terrain don't work well for organic anatomy because you can't simply downsample a blood vessel without losing the very feature the player is supposed to find.
How To Make Anatomy Gameplay That Actually Works
Start with your scope. Most people building anatomy games assume they need full-body models. They don't. A focused system like the cardiovascular or skeletal system alone gives you enough depth without requiring terabytes of scan data. Pick one system, define the learning objectives, then build backward from what the player actually needs to see and interact with. The asset pipeline looks like this. You source reference material—real cadaver imaging, CT scans, or established atlases like Netter's or Gray's. If you're doing real-time interaction, you'll want 3D meshes. Options range from purchasing pre-made anatomical libraries like 4D Human or Anatomical Trains 3D, to generating meshes from DICOM data using tools like 3D Slicer, which can convert clinical scan data into manageable polygon models. The DICOM route takes longer but gives you patient-specific accuracy that generic libraries can't match. Once you have your geometry, the optimization phase is where most projects stall. A full human body model at display quality runs 2-5 million polygons per system. Your average target for real-time interactive work is under 150,000 polygons per major structure. You'll use retopology tools like ZBrush's ZRemesher or manual workflows in Blender to reduce poly count while preserving topological accuracy where it matters. The trade-off is visible on curved surfaces. Flat bone interiors hold up fine at low detail. Cortical bone surfaces and organ boundaries need topology that follows natural contours, otherwise UV mapping and shader application look wrong.
Interaction design determines whether your anatomy game feels educational or like a digital museum exhibit. The key insight most developers miss is that interaction difficulty should scale with anatomical complexity, not the other way around. A beginner identifying the femur needs simple click-to-highlight mechanics. A user identifying the brachial plexus branches requires layered hover states, conditional visibility, and progressively revealing information. I built a branching tooltip system that showed structure names on hover, then revealed clinical correlations and common pathologies only after the player committed to an identification. This cut average completion time by roughly 40 percent compared to our initial design where all information was visible at once.
Get the Full Details

Technical Implementation Notes
Shader design for anatomical tissue matters more than people expect. Real tissue has subsurface scattering properties—light penetrates the surface, bounces around, and exits at a different point. Standard PBR shaders don't replicate this. You'll need to implement or purchase SSS-capable shaders, particularly for translucent tissues like cartilage, muscle bellies, and organ surfaces. Without it, everything looks like plastic. Even basic subsurface approximation through rim lighting and color attenuation on translucent materials makes a noticeable difference in perceived realism. For the actual implementation framework, Unity and Unreal are both viable. Unity gives you more flexibility with custom shader graphs and educational tool integrations. Unreal provides superior out-of-the-box rendering quality with Nanite-like virtualized geometry if you're working at scale. My recommendation depends on team size. Single developer or small team: Unity with written documentation and modular script architecture. Larger team with rendering specialists: Unreal with Blueprint-driven interaction systems leaving shader work to the render team. Testing accuracy is non-negotiable. I learned this the hard way during a project where our hepatic portal system model had the wrong branching pattern for the superior mesenteric artery. A medical reviewer caught it before launch, but it cost us six weeks of rework. Establish a review checkpoint with qualified anatomists or medical professionals at three stages: initial blockout, mid-poly refinement, and final UV and shader pass. Don't skip any of them.
Pitfalls and What They Cost You
Scope creep is the primary killer. Anatomy is infinitely detailed. Every system you add multiplies the asset creation workload. A project roadmap that says "full human anatomy" in twelve months is unrealistic. Full systemic coverage of three to four major organ systems in that timeframe, with accurate interaction design, is aggressive but achievable. Going beyond that requires either a larger team or accepting lower fidelity in peripheral systems. Another common failure mode is over-indexing on visual fidelity at the expense of interaction clarity. A beautifully rendered kidney with no clear boundary definition, no labeling system, and no feedback mechanism teaches nothing. Players need visual contrast between structures, consistent lighting that reveals depth cues, and immediate response to input. I once traded what would have been a stunning photorealistic liver model for a cleaner stylized version with clearer lobar boundaries. The stylized version had measurably better learning outcomes in user testing because players could actually distinguish the right lobe from the left without zooming in to pixel-peeping distance. Performance constraints hit hardest during multi-system visualization. Showing the circulatory and respiratory systems simultaneously with full anatomical accuracy can push draw calls into problematic territory on mid-range hardware. The workaround is view-layer culling—let players toggle system visibility, defaulting to single-system display with optional multi-system overlay at reduced fidelity. This approach kept our target framerate stable at 60fps on integrated graphics while preserving the option for detailed dual-system review on dedicated hardware.
If you're building this for clinical education rather than casual engagement, consider whether a full game framework is even necessary. Some of the most effective anatomy training tools I've encountered are lighter applications—web-based 3D viewers with quiz overlays, or spreadsheet-driven scenario builders paired with static high-resolution imagery. The question isn't whether your anatomy gameplay needs to be a game. It's whether interactivity adds learning value compared to cheaper, faster alternatives for your specific use case.